
Celiac disease (CD) follows a pattern common to chronic diseases: far more people test positive on a blood test than have proven intestinal damage, and most people with the disease do not know they have it. Knowing how often it occurs, and in whom, sets the context for deciding who to test.
The iceberg of diagnosed and undiagnosed disease
Epidemiological studies often rely on seropositivity: antibodies in the blood against tissue transglutaminase (tTG), the enzyme that is the target antigen of the disease. These studies indicate that the prevalence of asymptomatic and minimally symptomatic CD is much higher than that of frank disease. Some seropositive people have no enteropathy (damage to the small-bowel mucosa) on tissue biopsy, which shows that tissue damage and serological findings fluctuate over time. Therefore, not all subjects who are HLA-DQ2 positive (carriers of the main celiac-associated HLA type) and seropositive for tTG have celiac disease, but they are at high risk of developing CD. The practical consequence is that a positive test and a diagnosis are not the same thing, and that most cases are found by testing people who already have a reason to be tested.
Global prevalence
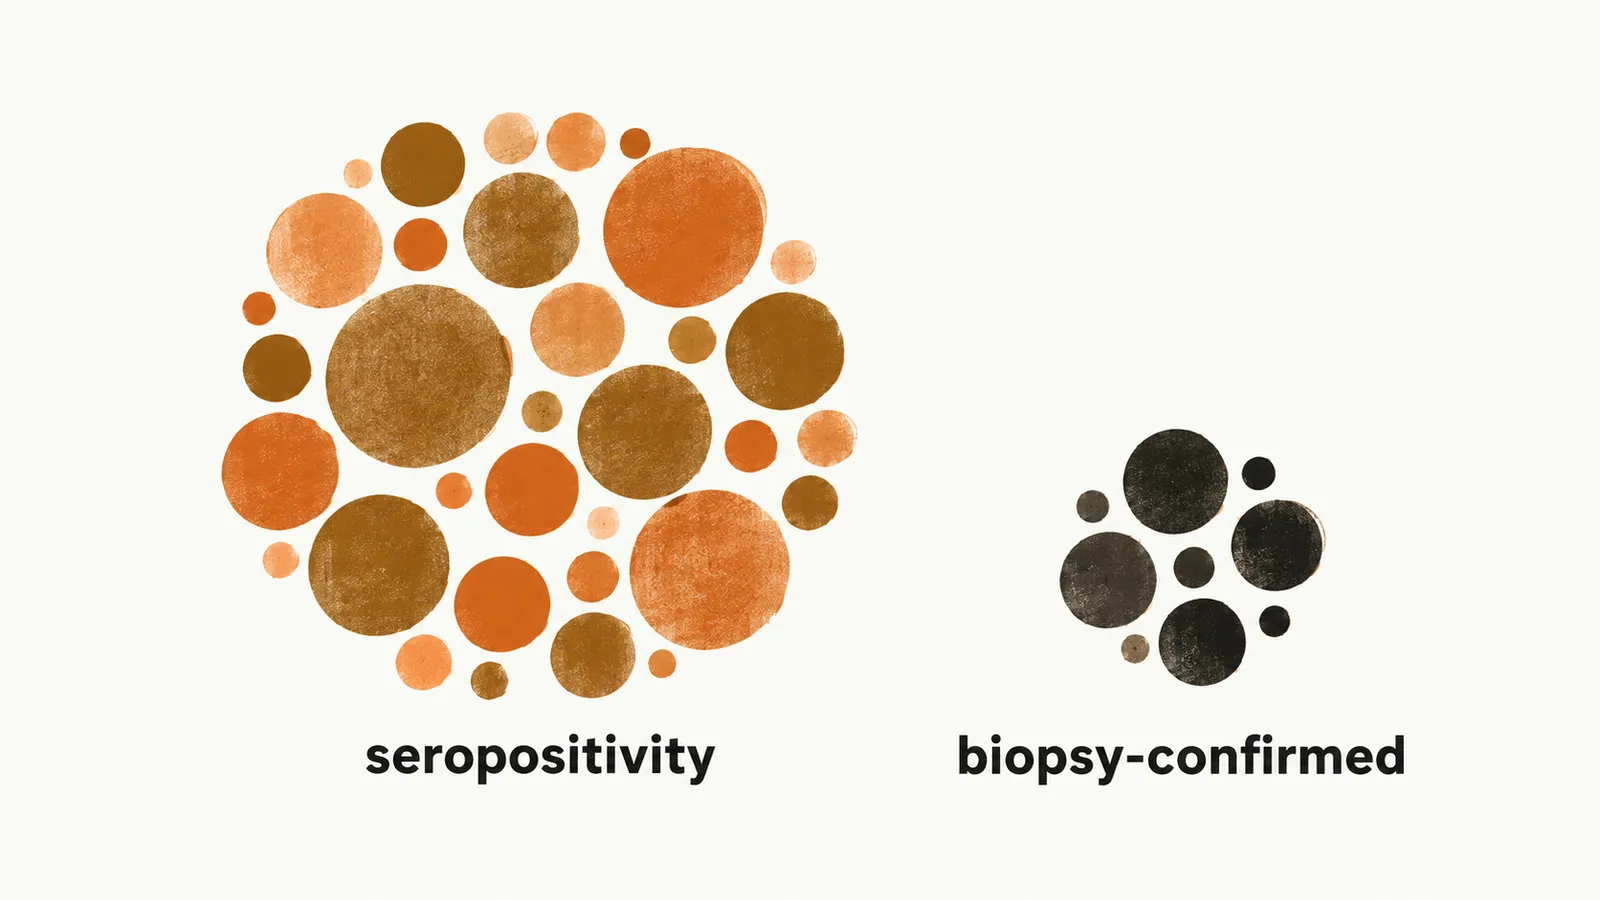
A meta-analysis of population studies estimated a pooled global seroprevalence (the proportion of people who are seropositive) of 1.4% (95% CI 1.1-1.7%) and a pooled prevalence of biopsy-confirmed disease of 0.7% (95% CI 0.5-0.9%). Prevalence varied by region:
- Europe and Oceania: about 0.8%
- North America and Africa: about 0.5%
- Asia: about 0.6%
- South America: about 0.4%
It was also higher in women than in men (0.6% vs 0.4%) and in children than in adults (0.9% vs 0.5%).
Within these averages, local figures differ. The prevalence of celiac disease in Europe is about 1%, with the highest prevalence, about 2.5%, in Finland. US epidemiological studies show a prevalence similar to that in Europe rather than higher, but there is a significant difference between ethnic groups, with the highest prevalence among people of Punjabi ancestry. This ethnic variation matters clinically: celiac disease is not confined to populations of European ancestry, so a low suspicion in other groups is not justified.
Because the disease is common but mostly silent, case-finding rather than universal screening is the practical approach: testing is directed at people with suggestive symptoms, a family history, or an associated condition. How that testing is done, and how a positive result becomes a diagnosis, is the subject of Diagnosis of Celiac Disease.