Where does the excess cortisol come from?
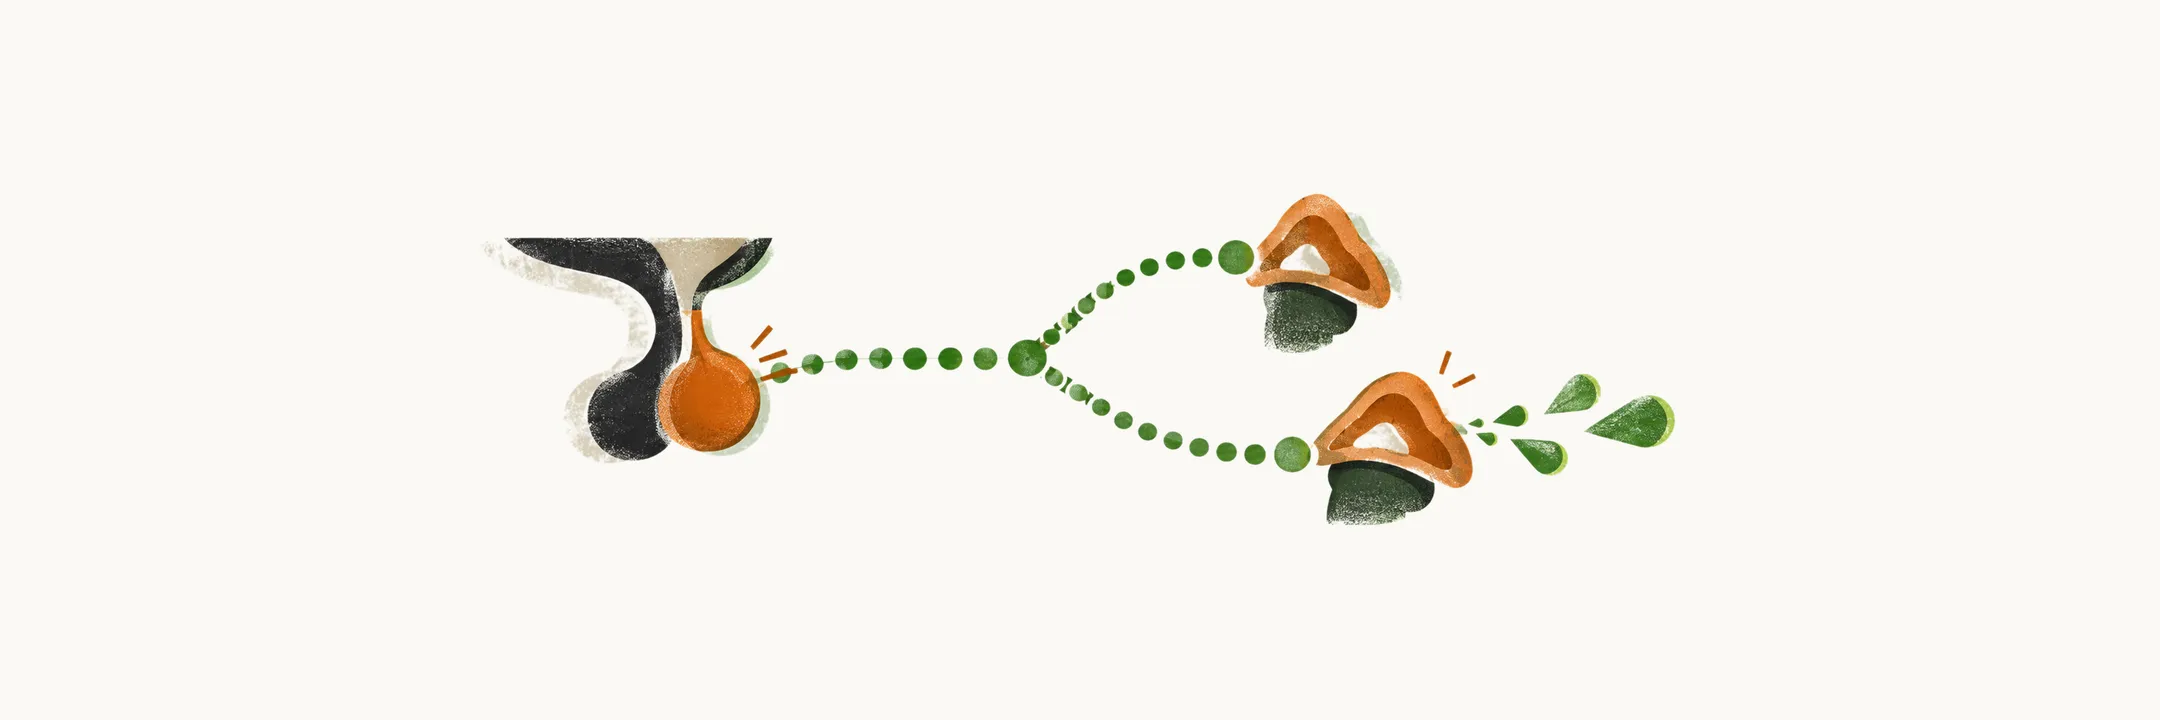
Cushing’s syndrome is a state of chronic glucocorticoid excess. To see where the excess comes from, follow the chain that makes cortisol.
The adrenal glands sit above the kidneys, and their outer layer, the adrenal cortex, makes cortisol. The cortex makes cortisol as far as ACTH tells it to. ACTH is physiologically secreted by the pituitary gland, which lies in the sella turcica. It travels in the blood and acts on all three layers of the adrenal cortex. The pituitary is itself switched on by CRH, the hypothalamic hormone that normally drives pituitary ACTH release.
Cortisol also works back on this chain. Cortisol in the blood acts on the hypothalamus and pituitary to switch CRH and ACTH off. That is the normal brake.
So Cushing’s syndrome arises in one of two ways. Either the adrenal cortex is driven by excess ACTH, or the cortex itself overproduces cortisol. There are two families, and the question is what separates them.
What separates the two families?
The first family is driven by ACTH, and the second runs without it.
In the ACTH-dependent forms, a tumour, pituitary or ectopic, makes the ACTH that drives the glands. The tumour sits outside the adrenal and sends the signal. The adrenal responds to that signal, so the excess starts with the signal. Excessive ACTH secretion produces hyperplasia of the adrenal cortex and nodule formation in it. Circulating glucocorticoids and androgens are often increased as well.
Three ACTH-dependent forms exist. They run the same chain and differ in where the ACTH comes from.
In the ACTH-independent forms, the adrenal cortex acts on its own and ACTH is suppressed. The cortisol brake explains this. When the adrenal makes cortisol without being told to, the cortisol in the blood still acts back on the hypothalamus and pituitary. The brake stays on, so ACTH falls low.
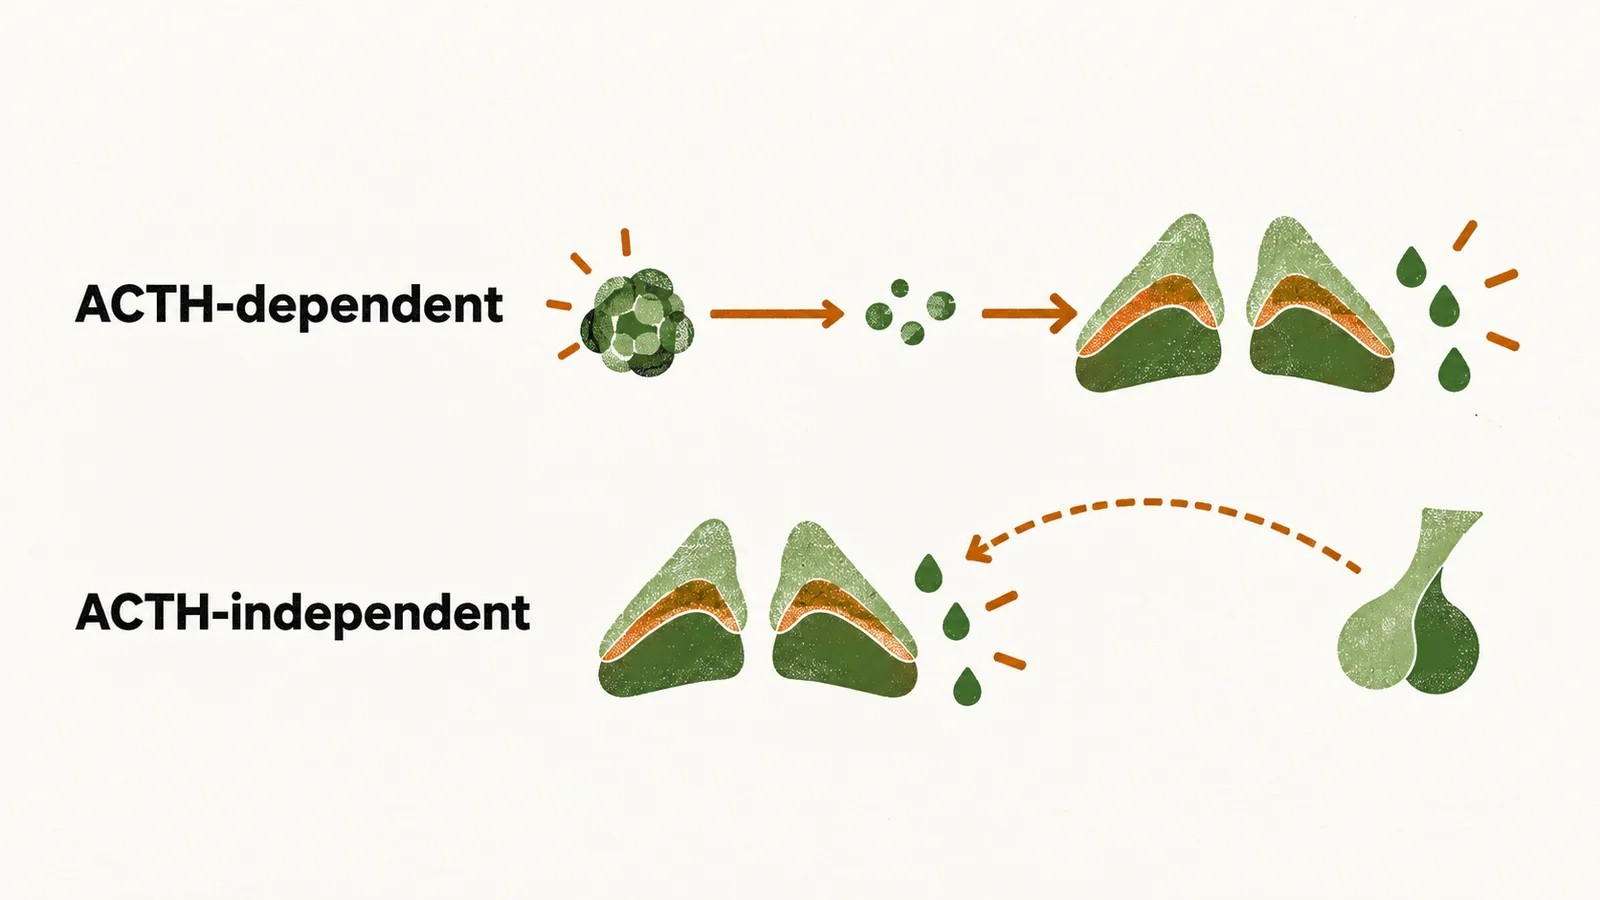
This distinction matters because it decides how each form is investigated and treated.
Which pituitary tumour is the usual source?
The pituitary is the normal source of ACTH, so a tumour of its ACTH-making cells produces the excess from that same gland. This is the pituitary form, called Cushing’s disease.
Cushing’s disease is almost always caused by one corticotroph adenoma. The adenoma is usually benign and usually restricted to the sella turcica.
The main cause of Cushing’s disease is still unknown. Even so, a large amount of information exists about the biochemical changes of the corticotroph tumour. They include a reduced level of p27 protein, a CDK inhibitor, and the presence of chromosomal aberrations.
In patients with the familial syndromes MEN-1 and McCune-Albright syndrome, predisposing mutations lead to pituitary adenomas.
A tumour outside the pituitary can make ACTH too, so the next question is where else the signal starts.
Can a tumour outside the pituitary make ACTH?
Yes. ACTH is not made only by the pituitary. ACTH and other POMC products can be produced by non-corticotroph tumours, and they can cause Cushing’s syndrome. POMC is the precursor molecule from which ACTH is made.
The most common cause of ectopic ACTH syndrome is neuroendocrine small cell lung carcinoma, which accounts for 60% of cases. This tumour arises from neuroendocrine tissue, and that is the tissue making the inappropriate ACTH. About 3-12% of neuroendocrine tumours of the lung make ACTH.
The other main causes are pancreatic neuroendocrine tumours, pheochromocytoma and medullary carcinoma of the thyroid gland. A pancreatic neuroendocrine tumour has been reported making ACTH, and a pheochromocytoma has been reported making both ACTH and CRH.
Neuroendocrine tumours of the lung have a slightly higher incidence in men. Because of that, ectopic ACTH syndrome has a higher prevalence in males.
Some of these tumours make CRH instead, and that raises the next question.
Can a tumour make CRH instead of ACTH?
Yes, though ectopic CRH syndrome is a very rare form of Cushing’s syndrome. CRH from the hypothalamus is the central regulator of the chain that ends in ACTH release. A tumour that makes CRH can therefore switch on the same chain from outside the brain.
Some tumours make CRH and actively release it into the blood. From there it can reach the pituitary, as the hypothalamic hormone does. The CRH-releasing tumours include:
- bronchial neuroendocrine tumours
- thymic neuroendocrine tumours
- small cell lung cancer
- thymic medullary carcinomas
- prostate carcinoma
- pheochromocytoma
- ganglioneuroblastoma
Many, if not all, CRH-releasing tumours also release ACTH at the same time. Such a tumour can push the adrenal with its own ACTH and with the CRH it sends to the pituitary.
With no signal at all, the adrenal itself is the problem.
What happens when the adrenal makes cortisol on its own?
In primary adrenal disease, the adrenal cortex overproduces cortisol on its own, and ACTH is suppressed. The main causes are not completely known. Some genetic mutations and aberrations are involved: over-expression of IGF-2, reduced expression of CDKN1C and reduced expression of H19. Mutation of p53 has a role in a small subset.
Three forms are usually distinguished.
- Adrenal adenoma is mostly encapsulated and weighs about 40 gram.
- Cortisol-secreting adrenal carcinoma is also mostly encapsulated and weighs about 100 gram.
- Primary pigmented nodular adrenal disease (PPNAD), also called micronodular adrenal disease, is a very rare form of Cushing’s syndrome. It is characterised by micronodules in the adrenal cortex, and these make cortisol without the pituitary signal.
PPNAD mostly occurs as part of Carney complex, a rare inherited syndrome. Carney complex belongs to a family of syndromes that includes other endocrine tumours, and PPNAD occurs in association with other abnormalities such as endocrine disorders.
Cushing’s syndrome due to bilateral adrenal dysfunction is characteristic of McCune-Albright syndrome. These patients manifest pigmentation of the skin, fibrous dysplasia of bone and endocrine dysfunction.
Which of all these causes is most common?
How common is each cause?
Glucocorticoid treatment given for other conditions accounts for most cases of Cushing’s syndrome.
The relative prevalence of the forms is:
- Cushing’s disease: 68%
- adrenal adenoma: 8-19%
- adrenal carcinoma: 6-7%
- ectopic ACTH syndrome: 6-15%
- nodular adrenal hyperplasia: 2%
Generally, the prevalence and incidence of Cushing’s disease, adrenal adenoma and adrenal carcinoma are higher in women. For ectopic ACTH syndrome, the most common cause is neuroendocrine small cell lung cancer, and the prevalence is higher in males.
Some high cortisol comes from none of these causes.
Can high cortisol occur with no tumour at all?
Yes. In pseudo-Cushing’s states, patients have all the definitive clinical features of Cushing’s syndrome with some evidence of hypercortisolism.
Stressful conditions such as depression or anorexia nervosa act on the CRH-producing neurons, because CRH is the central hormone of the stress response. They drive excess ACTH secretion, which leads to the pseudo-Cushing’s state. A proposed explanation is that stress keeps the axis chronically stimulated, with CRH, ACTH and cortisol all raised. No tumour is needed for the features to look like Cushing’s.
Pseudo-Cushing’s states resemble true Cushing’s syndrome. Because of this resemblance, telling the two apart becomes a diagnostic problem.
Because pseudo-Cushing’s states look so like the real thing, the next question is what the cortisol excess does to the body, and which signs give it away.