
Cortisol is made in the adrenal cortex by a chain of enzyme steps, and the chain runs when ACTH from the pituitary drives it. Cortisol then acts on the body through its receptors inside the cells. So a treatment has three places to act: the enzymes that make cortisol, the pituitary that sends ACTH, and the receptor where cortisol acts. Surgery goes further and removes the tumour or gland that is the source. Every drug discussed works at one of the three places.
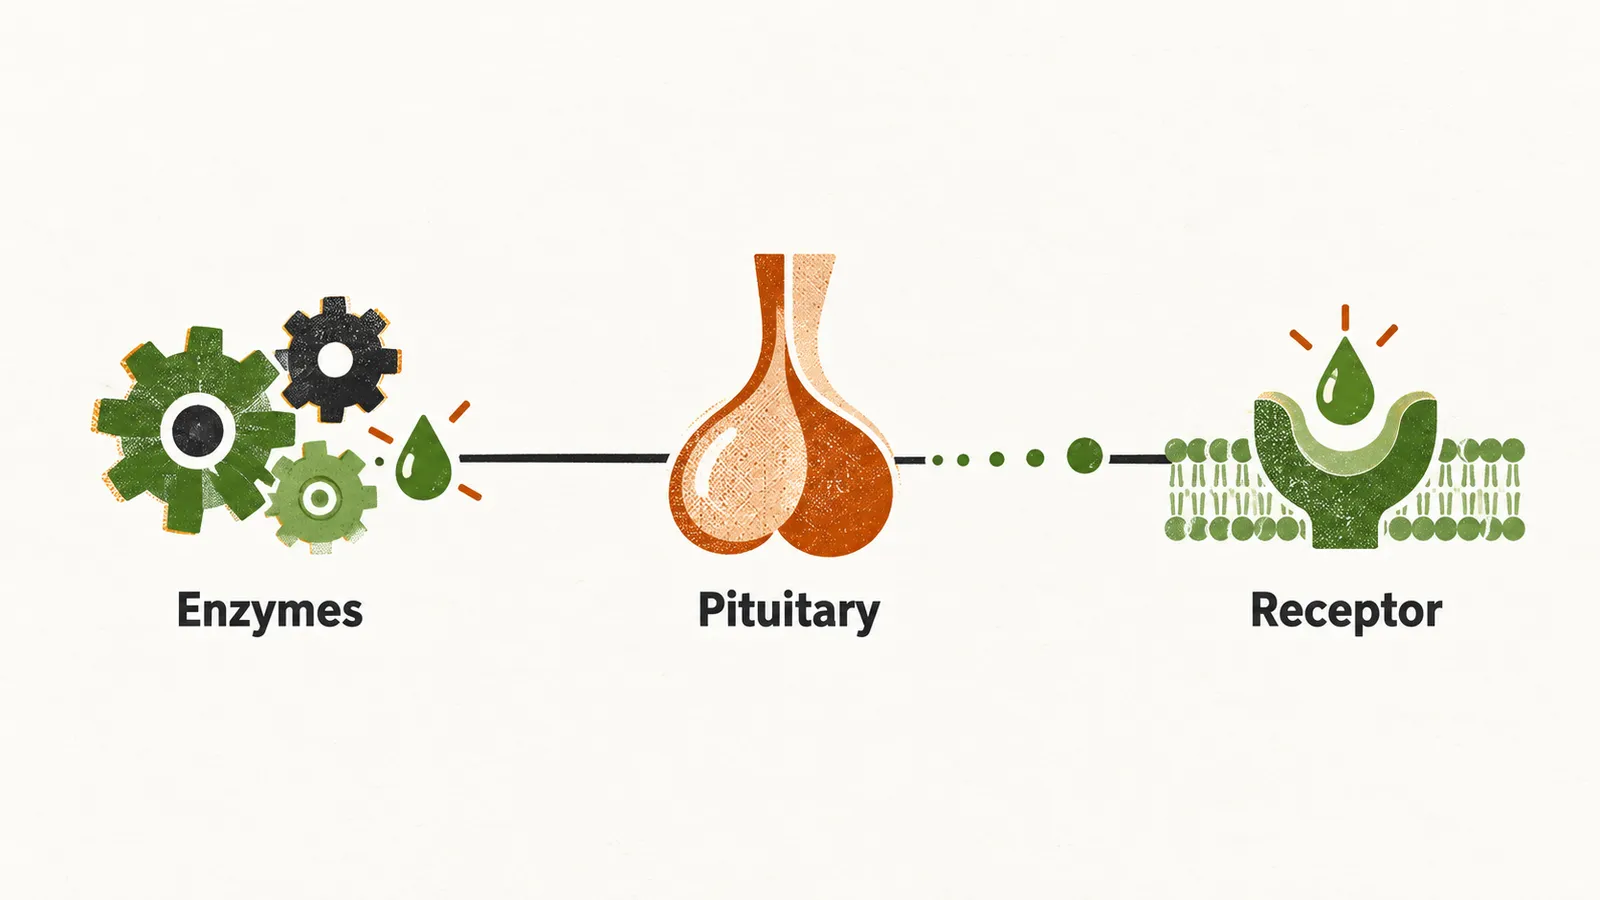
Where can treatment act?
Cushing’s syndrome is chronic glucocorticoid excess, and whether the excess is driven by ACTH or comes from the adrenal glands by itself decides which treatment follows. The treatment follows the cause, which is one of three: an ACTH-secreting pituitary tumour, an ectopic ACTH-secreting tumour, or primary adrenal disease.
The goal is to normalise cortisol levels or to block its action at the receptor. The further goal is that the signs, symptoms and complications of hypercortisolism resolve. Treatment is not started unless the diagnosis is established. Screening tests confirm the excess first, and pseudo-Cushing states can look similar.
Can the harms of cortisol wait for the cause to be removed?
Cortisol that has been high for long also harms the body directly, and the body changes of cortisol excess (fat, skin, muscle, bone, mood) are described in Clinical Manifestations of Cushing’s Syndrome. The consequences of cortisol excess do not disappear at once when the cause is treated. The cortisol-dependent problems are treated directly, alongside treatment of the cause. These problems include diabetes, hypertension, hypokalaemia, dyslipidaemia, osteoporosis, infection and psychiatric illness.
Severe hypercortisolism is associated with infection and thrombosis, and it can be life-threatening. Cortisol excess makes clotting more likely, and that explains the raised risk of venous thrombosis. When complications are present (infection, pulmonary thromboembolism, cardiovascular events, acute psychosis), the hypercortisolism is treated urgently, together with the complication itself.
Because of the raised clotting tendency, patients receive perioperative prophylaxis against venous thromboembolism. Because of the raised risk of infection, they receive age-appropriate vaccination, particularly against influenza, herpes zoster and pneumococcal disease.
The most direct way to remove the source is surgery, so the question is which operation fits which cause.
Which operation fits which cause?
Surgical resection of the causal lesion is first-line treatment for every form.
In Cushing’s disease the ACTH-making adenoma is the source, so taking it out removes the source. The optimal treatment is transsphenoidal selective adenomectomy, which an experienced pituitary surgeon performs through the nose and sphenoid sinus, reaching the pituitary in the sella.
In ectopic ACTH secretion, the tumour is localised and resected, with node dissection as appropriate. When there is no overt metastatic disease, resection cures about three-quarters of patients.
In benign unilateral adrenal disease, unilateral adrenalectomy is curative in nearly all patients.
Surgery does not cure every patient, so what happens when it cannot be used or does not cure?
What happens after the source is removed?
After transsphenoidal surgery, serum sodium and pituitary function are monitored. Hypopituitarism and disorders of water balance can follow the operation.
After successful resection of a pituitary or adrenal source, most patients are hypocortisolaemic for a time. Cortisol switches off ACTH through negative feedback, so during the excess the rest of the hypothalamic-pituitary-adrenal axis has been held down, and its recovery may be delayed once the source is gone. That is why most patients after successful resection need glucocorticoid replacement. The replacement continues until the axis recovers.
Some patients are not cured, and in others the lesion cannot be resected. When the source cannot be removed, which drugs can take its place?
Which drugs block cortisol production?
When the lesion cannot be resected or surgery does not cure the disease, second-line treatment is chosen together with the patient, and several options exist. Drug treatment acts at the three levels of the picture, and the first level is the enzymes that make cortisol.
Steroidogenesis inhibitors block these enzymes, so cortisol synthesis falls.
- Metyrapone acts on 11β-hydroxylase.
- Osilodrostat also acts on 11β-hydroxylase, and so inhibits cortisol synthesis.
- Ketoconazole acts on several steps, including side-chain cleavage and 17-hydroxylase.
- Mitotane acts on 11β-hydroxylase and on cholesterol side-chain cleavage. It also has an additional cytotoxic effect: it destroys adrenal cortical tissue, which impairs cortisol making.
As single agents, steroidogenesis inhibitors normalise cortisol in about half of patients. Combinations of them are used in severe hypercortisolism.
Some drugs act earlier, on the pituitary, so which drugs reduce ACTH itself?
Which drugs and radiotherapy are aimed at the pituitary?
Pituitary-directed drugs reduce ACTH production, by reducing ACTH release from the corticotroph tumour. The somatostatin analogue pasireotide reduces ACTH secretion from the adenoma. It normalises urinary free cortisol in about 40% of patients with Cushing’s disease. The dopamine agonist cabergoline does the same in about 40% of patients with Cushing’s disease. These drugs give better results in milder disease.
Radiotherapy or radiosurgery is used for Cushing’s disease after failed or recurrent transsphenoidal surgery. Medical therapy is continued while the radiotherapy or radiosurgery takes effect.
Cortisol can also be blocked at the receptor, so what does a receptor blocker do?
What does blocking cortisol at the receptor do?
The glucocorticoid receptor antagonist mifepristone blocks cortisol action at the receptor. It is used particularly when diabetes or glucose intolerance is present, because it improves glycaemic control in this setting.
When no drug controls cortisol, must the adrenal glands themselves be removed?
When are both adrenal glands removed?
Bilateral adrenalectomy is used for occult or metastatic ectopic ACTH secretion. It is also used as a life-preserving measure in very severe ACTH-dependent disease that medical therapy cannot control promptly.
After bilateral adrenalectomy the pituitary tumour is left in place. Because it is left in place, it must be monitored.
Adrenal tumours that cannot be removed or that spread raise a separate question.
What about adrenal cancer and bilateral adrenal disease?
In adrenocortical carcinoma, complete resection is attempted. Mitotane is given afterwards as adjuvant therapy. The hypercortisolism is also controlled medically.
In bilateral adrenal disease, the adrenal glands are resected. In bilateral macronodular hyperplasia, medical therapy that blocks aberrant hormone receptors is suggested.
Once cortisol is brought down, how is the patient followed for the rest of their life?
What is the outcome, and what needs follow-up?
Before effective treatment, patients with Cushing’s syndrome had a median survival of about 4.6 years. Patients with active disease have a standardised mortality rate 1.7 to 4.8 times that of the general population. Patients with persistent or recurrent hypercortisolism remain at high risk. Cardiovascular disease, venous thrombosis and infections are the leading causes of excess deaths. Successful treatment improves survival.
Some complications can persist after cortisol normalises: cardiovascular risk, bone fragility, muscle weakness, and cognitive and mood changes. These are followed and treated lifelong.
Why does some damage outlast the cortisol, and what does follow-up look for?