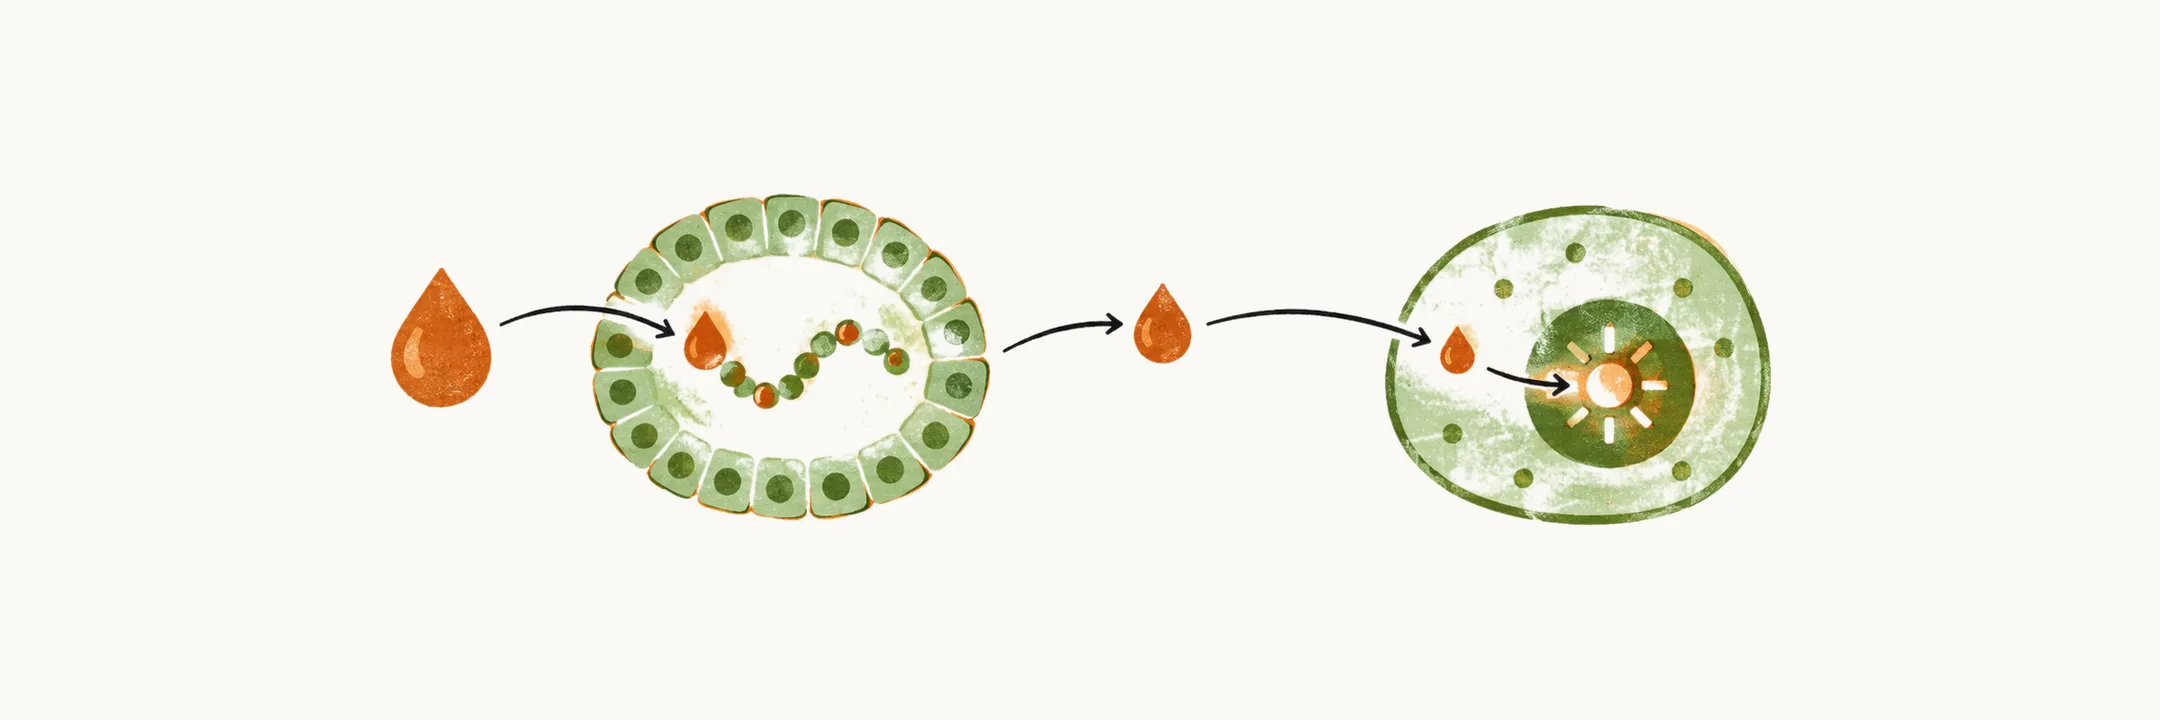
The thyroid gland builds two hormones: thyroxine (T4) and triiodothyronine (T3). Each follicular cell has two faces. Its blood face takes iodide in. Its lumen face looks onto a store of thyroglobulin, the protein the hormone is built on. Iodine crosses the cell and is attached to tyrosines of that protein, and the hormone stays on the protein until the cell takes it back in and cuts it free. Once released, the hormones are carried in the blood and converted to their active form at the tissues. Inside each target cell, T3 then acts from the nucleus, the mitochondria or the cell membrane.
Producing the hormones takes iodine, a set of enzymes and thyroglobulin.
How does iodine get into the cell?
Iodine is the raw material, so the first step in hormone production is its absorption by the follicular cells. The sodium–iodide symporter (NIS) does this very efficiently. NIS is a membrane transporter that carries iodide into the cell. It does not use its own energy: it moves iodide in together with sodium, and the sodium gradient is kept up by the sodium-potassium pump. NIS sits on the basolateral side of the follicular cells, so iodide enters from the blood and then has to cross the cell.
What tells the cell to take it up?
The entry is not automatic. The amount of hormone released and produced is controlled mainly by TSH, and, as the structure note showed, TSH from the anterior pituitary is the main controller of the axis. TSH acts on the side of the follicular cell that faces the blood vessels. There it binds the TSH receptor (TSH-R), a G protein-coupled receptor. Its G protein α subunit activates adenylate cyclase. This increases cAMP production inside the cell. The cAMP signal also turns on the transporter gene: TSH stimulates NIS gene expression, which needs Pax8 binding to the NIS promoter.
TSH is the dominant controller. Some other factors act in the same direction, but far less strongly: insulin-like growth factor 1 (IGF-1), epidermal growth factor, transforming growth factor β (TGF-β), endothelin and several other cytokines.
Why do scans and radioactive treatment work this way?
NIS expression also depends on the blood iodine level. A lower iodine amount means higher NIS expression, and the reverse. This dependence is the basis of thyroid scanning for diagnosis and of radioactive iodine use for treatment. The same transporter takes up radioactive iodide, so a tracer or a treatment dose goes in the way ordinary iodide does. The gland takes up tracer or therapy in proportion to how much iodine it is seeking.
What happens when iodine runs short?
If the cell cannot get iodine, it cannot build hormone. Several regions in the world suffer from iodine deficiency, and it is the leading cause of goiter and of cretinism. Cretinism means intellectual disability together with growth retardation in children. Even slight iodine deficiency causes a slight decrease in IQ in children. Iodine deficiency is a leading preventable cause of intellectual disability. In sufficiently iodinated populations, urinary iodine concentration is more than 100 micrograms per liter of urine. The opposite excess is also linked to disease: foods over-rich in iodine are associated with a higher incidence of autoimmune thyroid disorders.
How is iodide built into hormone?
Building happens on thyroglobulin, the protein precursor of the hormones that fills the lumen of each follicle. So iodide has to reach the lumen before building can start. After entrapment of iodide by NIS, iodide moves to the apical surface, the side facing the lumen. Another transporter, pendrin, is located there and moves iodide out on that side.
At the apical surface, iodide is oxidized and organified to form iodine. Iodide has to be oxidized before it can join a protein. Thyroid peroxidase (TPO) does the oxidation and organification, using hydrogen peroxide made by the dual oxidase DUOX system. Iodine atoms are reactive and attach to tyrosine residues of thyroglobulin, so the hormone is built on that protein.
TPO then couples iodinated tyrosine residues to one another. Which hormone forms depends on which iodinated tyrosines are coupled, so the number of iodine atoms on the residues decides the product:
- two diiodotyrosines give T4;
- one diiodotyrosine with one monoiodotyrosine gives T3.
How is the hormone cut free, and the iodine reused?
The built hormone stays on the protein, so the cell must take the protein back in. After coupling, thyroglobulin is taken back into the follicular cells and processed by lysosomes, which cut the protein open and release the hormone from its peptide links. Residues carrying two or one iodine cannot be reused as they are. The dehalogenase enzyme deiodinates them and recycles the iodine for making new hormone, so scarce iodine is used again.
How does the hormone travel in the blood?
The gland releases mostly T4: in blood, the T4 concentration is about 40-fold higher than the T3 concentration. Tissues convert some of that T4 into T3, so the active hormone is made after release.
Thyroid hormones are hydrophobic, so they need carriers in the watery blood. The carriers shield them and keep a stable free level available for uptake by cells. Three proteins carry the hormones:
- Thyroxine-binding globulin (TBG) has a very low blood concentration, about 2 mg/dl, but a very high affinity for thyroid hormones. It binds so tightly that this small amount of protein carries about 80% of thyroid hormones.
- Transthyretin (TTR) carries up to 10% of thyroid hormones.
- Albumin carries about 10% of T4 and up to 30% of T3. It is abundant but binds weakly.
Which share of the hormone can act?
The carriers hold most of the hormone, so the question is which part is free. More than 99.98% of T4 is in bound form, and 99.7% of T3. A smaller fraction of T4 is therefore free than of T3. Still, the amount of free T4 is higher than that of free T3, because T4 is produced at a higher rate. The free share is what cells take up, so the bound share acts as a reserve.
The controlling mechanisms of the axis work to keep the unbound concentration inside the window of normality. Under physiological conditions, TSH level relates only to unbound thyroid hormone. Total hormone counts the bound share too, so a change in carrier moves the total without changing thyroid status. A person can have an altered total thyroid hormone level with the unbound level in the normal range. Such conditions are called euthyroidism.
How does T4 become the active T3?
Tissues finish the job: several enzymes called deiodinases convert T4 to T3. Three forms of deiodinase exist.
Type I deiodinase converts T4 to T3 and makes most of the T3 that circulates in the blood. It is expressed in thyroid, liver and kidney, and it has low affinity for T4. It is inhibited by propylthiouracil.
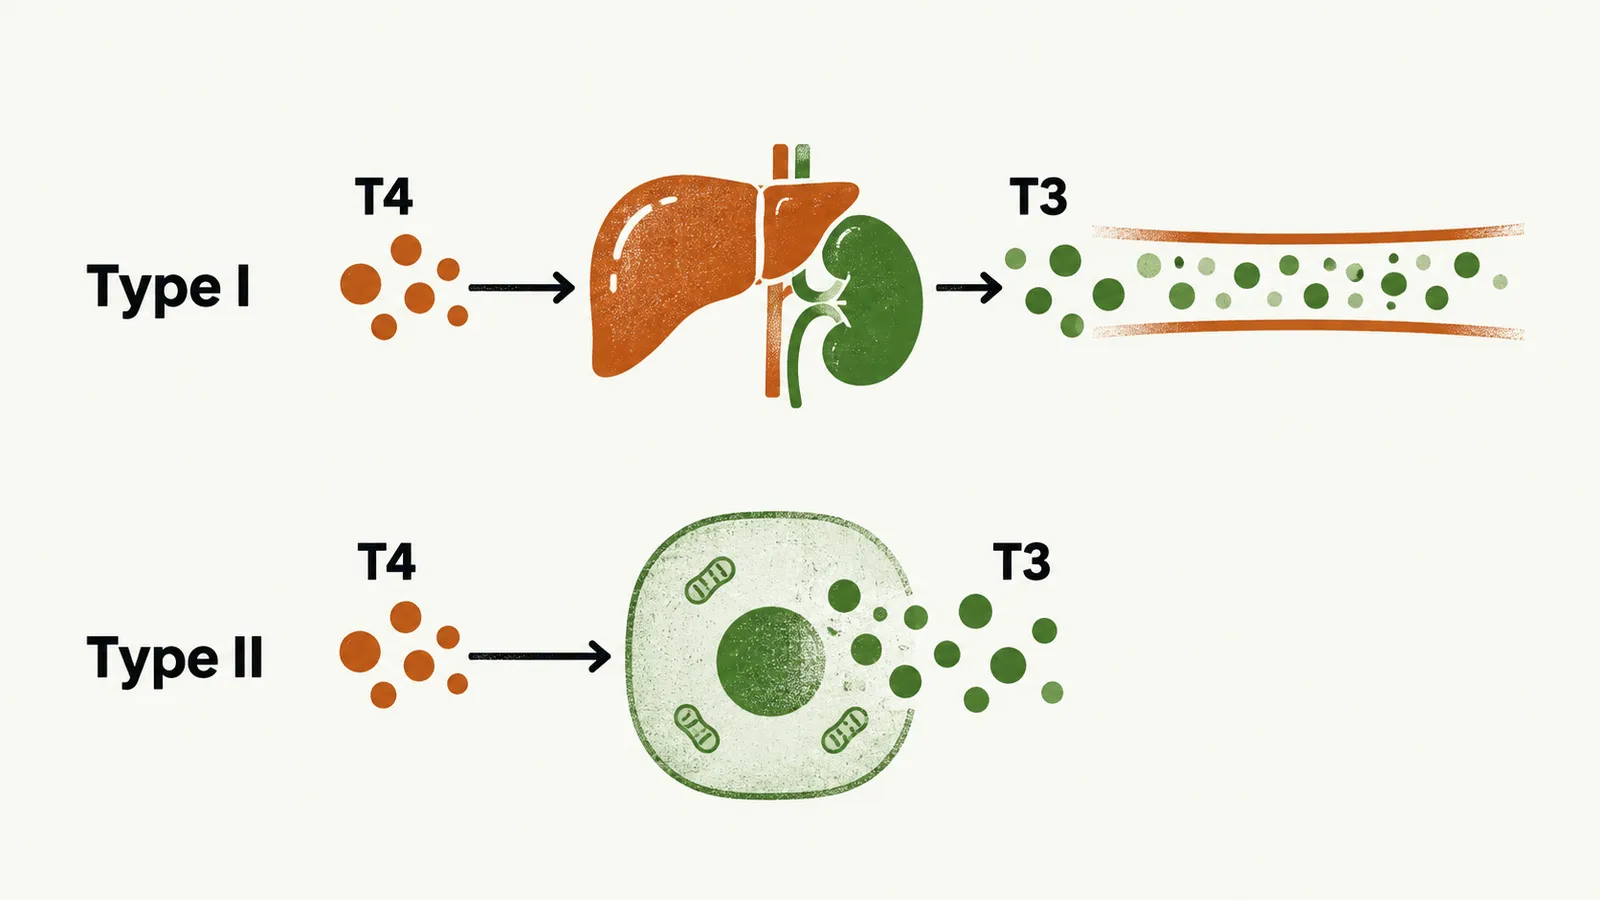
Type II deiodinase also converts T4 to T3, inside the target tissue. It is expressed in pituitary gland, brain, brown fat and thyroid, so the pituitary, brain and brown fat make their own T3 from T4. It has very high affinity for T4, so it binds T4 strongly. Its activity is impaired by fasting and by acute trauma. It is also impaired by some drugs, such as propranolol, amiodarone and glucocorticoids.
Where is hormone switched off?
A third deiodinase works the other way. Type III deiodinase inactivates both T4 and T3. It removes an inner-ring iodine, and it is the main source of reverse T3, an inactive form of the hormone. This is how it switches hormone off.
Type III deiodinase is expressed physiologically in the placenta. A proposed explanation is that it limits how much active hormone reaches the fetus; the same idea has been proposed for the brain. It is also expressed by massive hemangiomas and other tumors. A tumor that expresses type III deiodinase can use up active hormone, and so it can cause hypothyroidism in the patient.
How does T3 act inside a cell?
Once inside, thyroid hormone effect is produced in three main ways.
- The hormone diffuses to the nucleus, where it changes gene expression. It binds receptors of the nuclear receptor family, which act on genes.
- The hormone diffuses to the mitochondria. There a receptor form works as a transcription factor on the mitochondrial genome.
- The hormone acts on the heart and blood vessels through integrin receptors. This route is proposed rather than established: a receptor on the cell surface is thought to act without the hormone entering the cell.
The nuclear and mitochondrial routes use the hormone inside the cell. The integrin route works from the cell membrane.
In the nucleus, the hormone binds one of two receptors: thyroid receptor α (TRα) and TRβ. The TRβ gene makes two forms by alternative promoters, and both bind T3. TRβ is primarily expressed in brain and liver. TRβ-2, a subtype of TRβ, carries the negative feedback to the hypothalamus and thyrotropic cells.
What happens when the receptor is faulty?
The receptor carries both the hormone’s action and the pituitary feedback, so a faulty receptor changes what the blood shows. Resistance to thyroid hormone (RTH) is a genetic condition caused by an autosomal dominant mutation. The mutation, in the THRB gene that encodes TRβ, reduces the activity of the TRβ receptor.
The pituitary is less responsive to the hormone, so its TSH is not pushed down as it would be in a normal gland. Patients with RTH have a high level of unbound thyroid hormone, yet no increase in TSH level. This state is called euthyroid hyperthyroxinemia.
What does this action change?
What the hormone does in tissues, in development and in adult life follows from these actions, so what does it change in a growing brain and in an adult body?