Barrett esophagus is the replacement of the normal squamous lining of the distal esophagus by metaplastic (changed-type) columnar epithelium, a change that follows chronic acid exposure. Knowing who tends to develop it, and which exposures raise or lower the risk, shows which patients to think about.
Who develops it
Barrett esophagus is a disease of middle-aged to older adults, with an average age of about 55 years at the time of diagnosis. It is more common in white men and much less common in Black and Asian people.
Among adults who are examined endoscopically for GERD (gastroesophageal reflux disease) symptoms, about 10–20% have short-segment Barrett esophagus, while 3–5% have long-segment disease. The terms describe how far the metaplasia extends up from the stomach: short-segment disease is less than 3 cm and long-segment more than 3 cm above the esophagogastric junction (EGJ), where the esophagus meets the stomach. Most people with the condition never develop cancer: across the whole group, the risk of progression to adenocarcinoma is about 0.12 to 0.33% per year.
Factors that raise the risk
GERD is the main risk factor. The squamous lining is not built to withstand acid, so the more often and the longer the distal esophagus is exposed to refluxed gastric contents, the greater the chance that the columnar change develops.
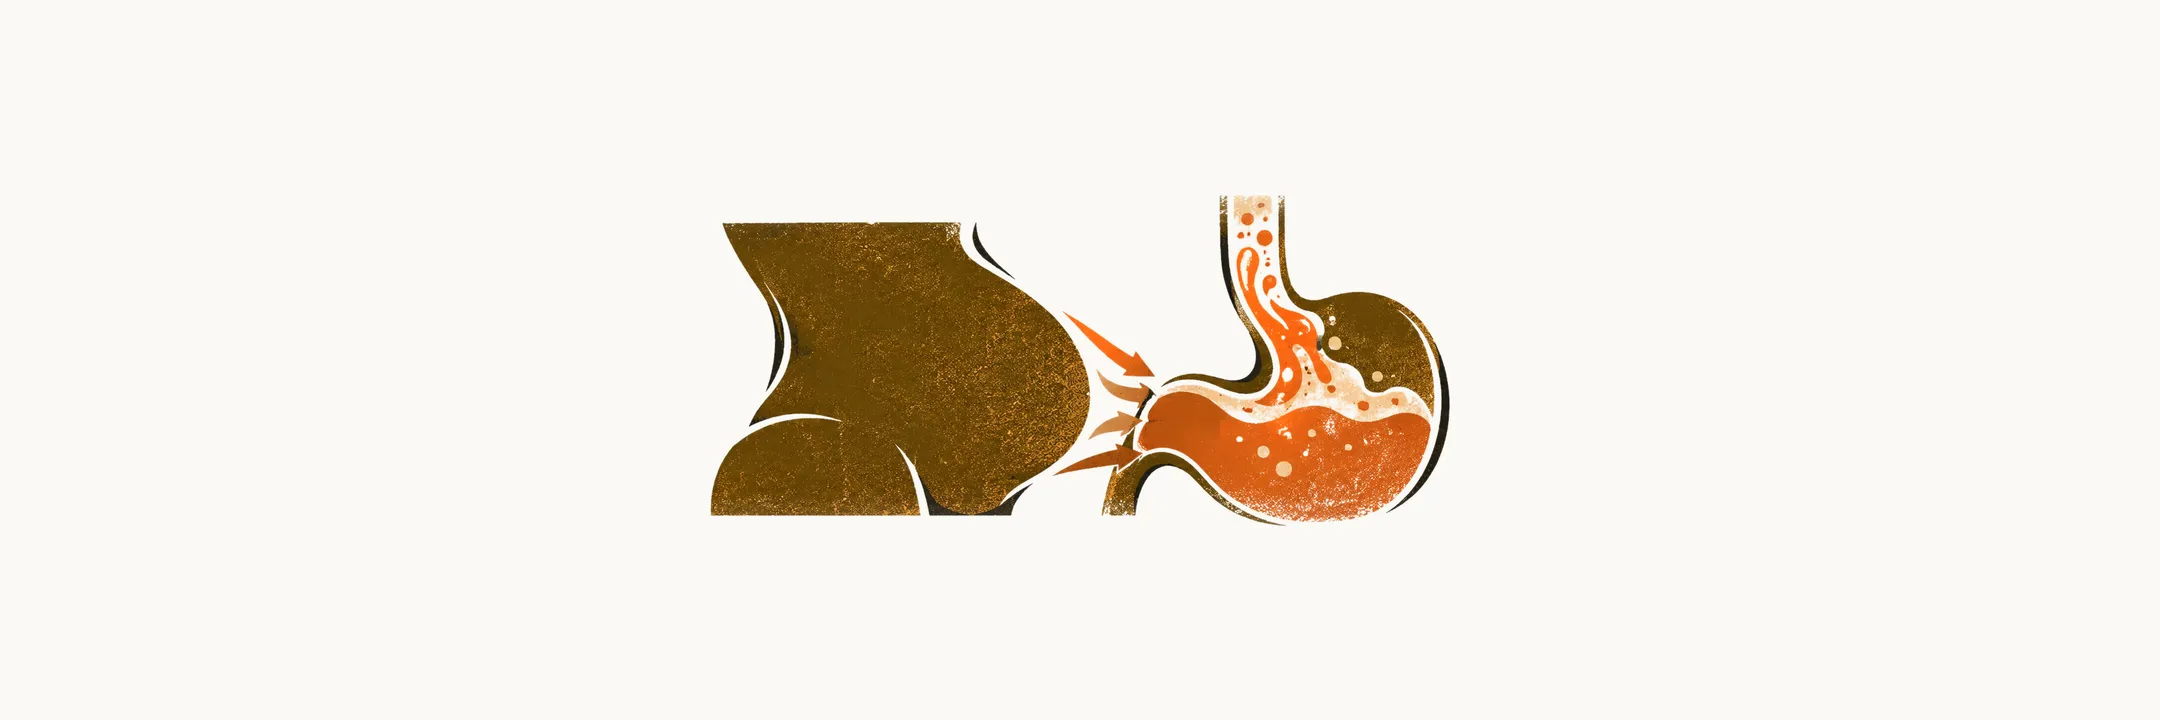
Central obesity, meaning fat concentrated in the abdomen, also raises the risk. The likely mechanism is mechanical: abdominal fat increases intra-abdominal pressure, which promotes reflux of stomach contents across the lower esophageal sphincter into the esophagus.
Smoking and alcohol consumption increase the risk of squamous cell carcinoma of the esophagus. For adenocarcinoma of the esophagus and Barrett esophagus the picture is different: alcohol consumption appears not to affect the risk, while smoking produces a modest increase in risk.
Factors suggested to be protective
Two factors have been suggested to be protective:
- H. pylori infection, in the subsets in which it reduces the rate of gastric acid production
- NSAIDs (nonsteroidal anti-inflammatory drugs)
Both are only suggestions. How repeated acid exposure actually turns the squamous lining into columnar epithelium is the question that follows from these risk factors.