Why can adrenal function be tested at all?
The HPA axis is a closed loop, and cortisol restrains the release of CRH and ACTH (the brake described in The HPA Axis and the Control of Glucocorticoid Production). That brake does not care where the glucocorticoid came from: an exogenous glucocorticoid suppresses ACTH the same way the patient’s own cortisol does. A loop that corrects itself answers a disturbance in a known way, so a push from outside can be applied and the reply read. An answer that departs from the known one points to a fault. This is why adrenal function can be tested.
Each test asks a different question of the loop:
- Can ACTH be suppressed?
- Can the adrenal gland respond to ACTH?
- Can the whole axis be driven by stress?
These questions concern different links of the chain: the brake itself, the end station (the gland) and the input that drives the chain from the top. The first push is on the brake.
Can ACTH be suppressed?
Dexamethasone is a synthetic glucocorticoid. It acts on the negative feedback of the axis. Because the hypothalamic and pituitary receptors bind it, the feedback loop reads dexamethasone as cortisol, so it suppresses the release of CRH and ACTH. It also does not interfere with the cortisol measurement, so the cortisol measured afterwards is the patient’s own.
The fall in ACTH is judged by the resulting fall in cortisol. Cortisol lies downstream of ACTH, so when ACTH falls the cortex has less to respond to and cortisol falls with it.
Whether the axis responds to dexamethasone, and how much dexamethasone is needed, localises the source of an excess of cortisol. Whether, and how far, the axis obeys the brake depends on where the excess begins.
What does the response to dexamethasone say about the source of excess cortisol?
The three possible sources differ in how much feedback they still obey.
| Source of excess cortisol | What ACTH does | Why |
|---|---|---|
| Adrenal gland itself | The test changes nothing | The high endogenous cortisol already suppresses CRH and ACTH, so there is little ACTH left to suppress |
| Pituitary | A low dose does not suppress ACTH; a higher dose suppresses it, and ACTH falls | The ACTH-secreting corticotroph cells are relatively resistant to feedback, so they still respond, but only to a larger push |
| Ectopic ACTH | The ACTH level does not change | Ectopic neuroendocrine tissue is mostly resistant to feedback, even at high doses |
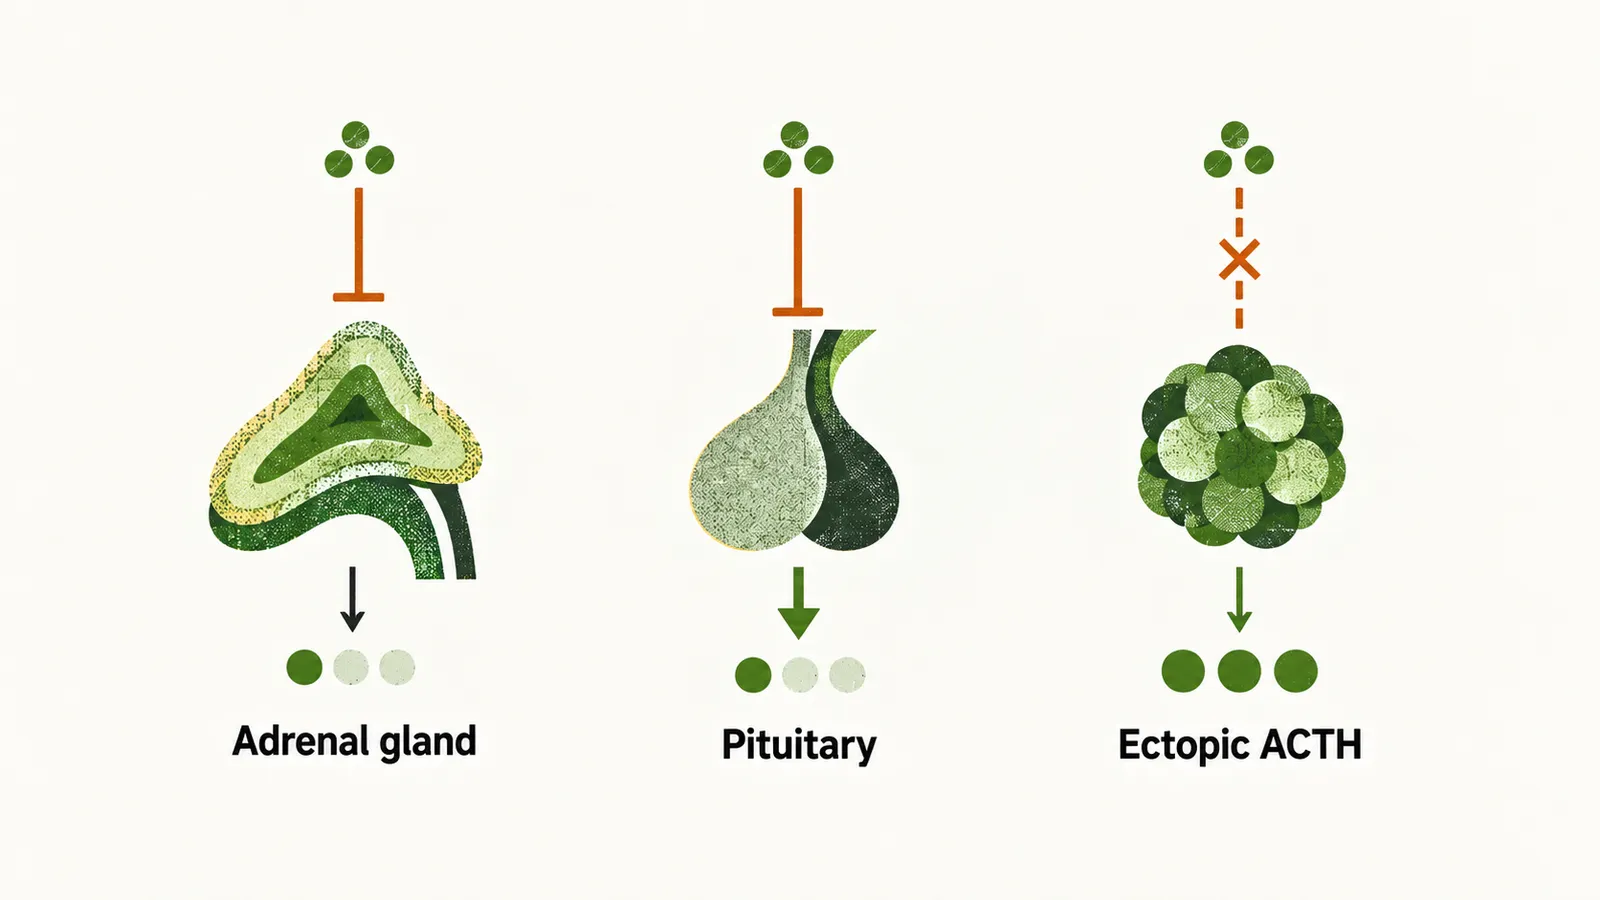
In the adrenal case the brake is already pressed, and adding dexamethasone cannot lower an ACTH that is already low. The ectopic tissue lies outside the axis, so feedback mostly fails to reach it and ACTH stays where it was.
Dexamethasone leaves the gland alone. A second question asks the gland directly.
Can the gland itself respond?
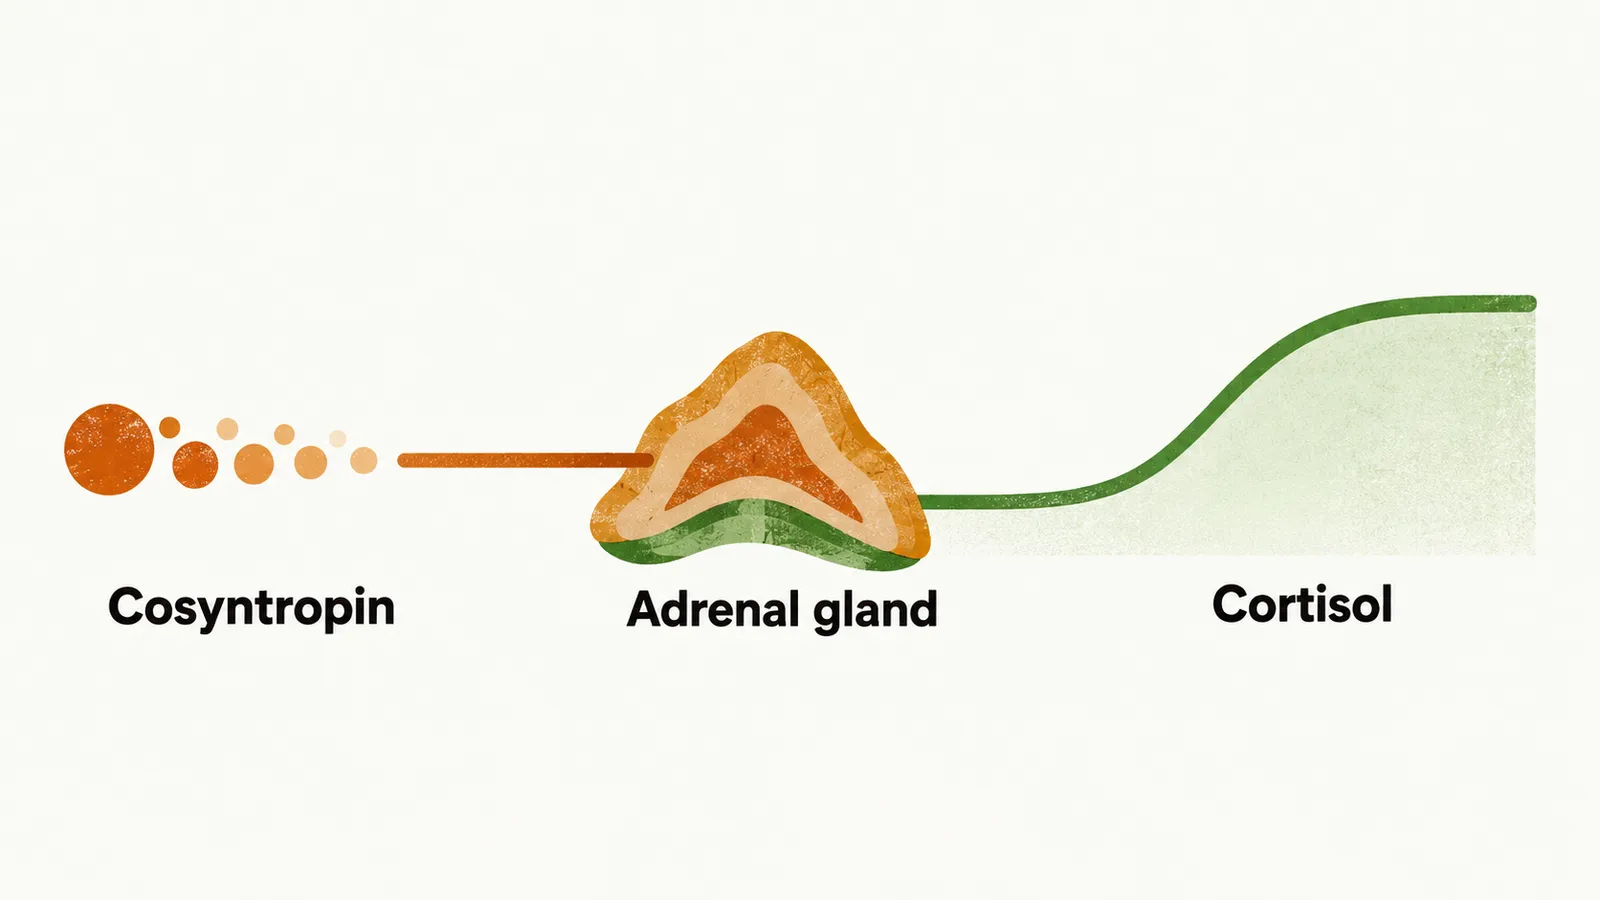
Cosyntropin is the first 24 amino acids of ACTH, and these 24 amino acids carry ACTH’s biological activity. Giving cosyntropin therefore reproduces what ACTH does at the cortex.
The cosyntropin stimulation test asks whether the adrenal gland can mount a cortisol response to that signal. The signal arrives from outside, at the gland itself, so the hypothalamus and pituitary are bypassed and the cortisol reply reflects what the cortex can do. Cosyntropin is given intramuscularly or intravenously, and cortisol is measured afterwards. A normal response is a cortisol above 15–20 microgram/dL at 30–60 minutes after administration.
Why is the cosyntropin test the usual first choice?
The cosyntropin test is the usual first-line method for assessing glucocorticoid deficiency. The reason lies in the alternative, the insulin tolerance test, which is contraindicated in cerebrovascular disease, coronary artery disease and seizure. The insulin tolerance test deliberately lowers blood glucose, and hypoglycaemia is a risk in those conditions.
What if the whole axis must be driven?
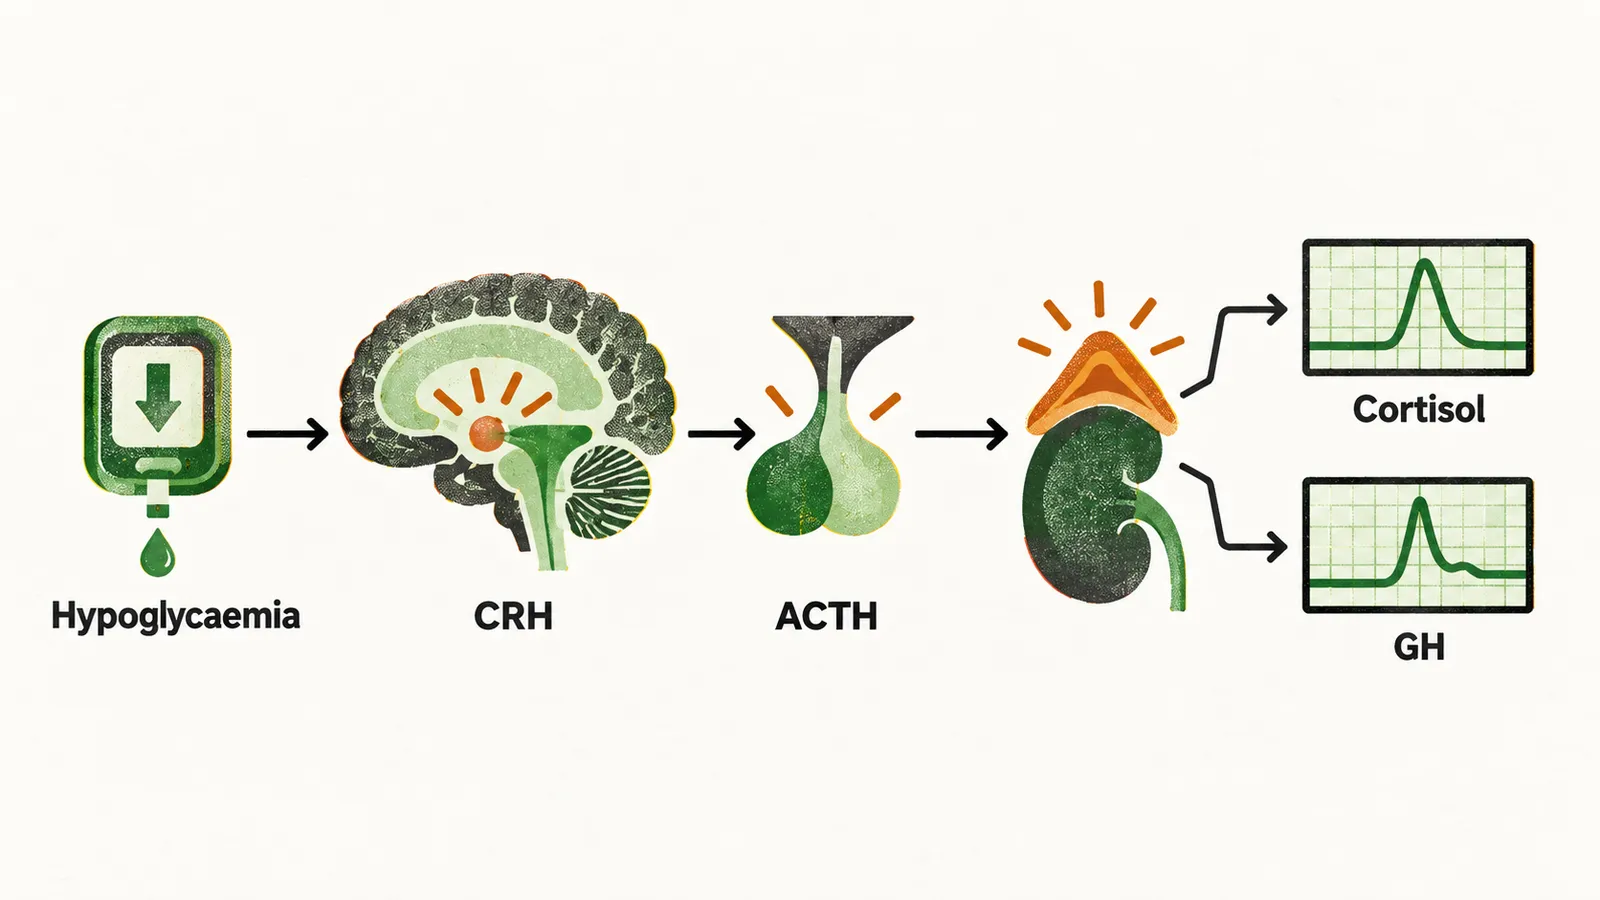
The third question treats the axis as a whole. The insulin tolerance test (ITT) drives the whole axis from above. The stress enters at the top, so a normal answer needs the hypothalamus, the pituitary and the gland all to work.
A high dose of insulin produces hypoglycaemia, and the body treats hypoglycaemia as a severe form of endogenous stress. It releases CRH and ACTH, and at the same time growth hormone (GH). Glucose, cortisol and GH are measured at 0, 30, 60 and 120 minutes after the injection: the glucose shows that the stimulus was delivered, and the cortisol and GH show the reply. The normal physiological response is defined as a cortisol above 20 microgram/dL plus a GH above 5.1 microgram/L.
If the loop answers abnormally, which disorder of the cortex lies behind it?