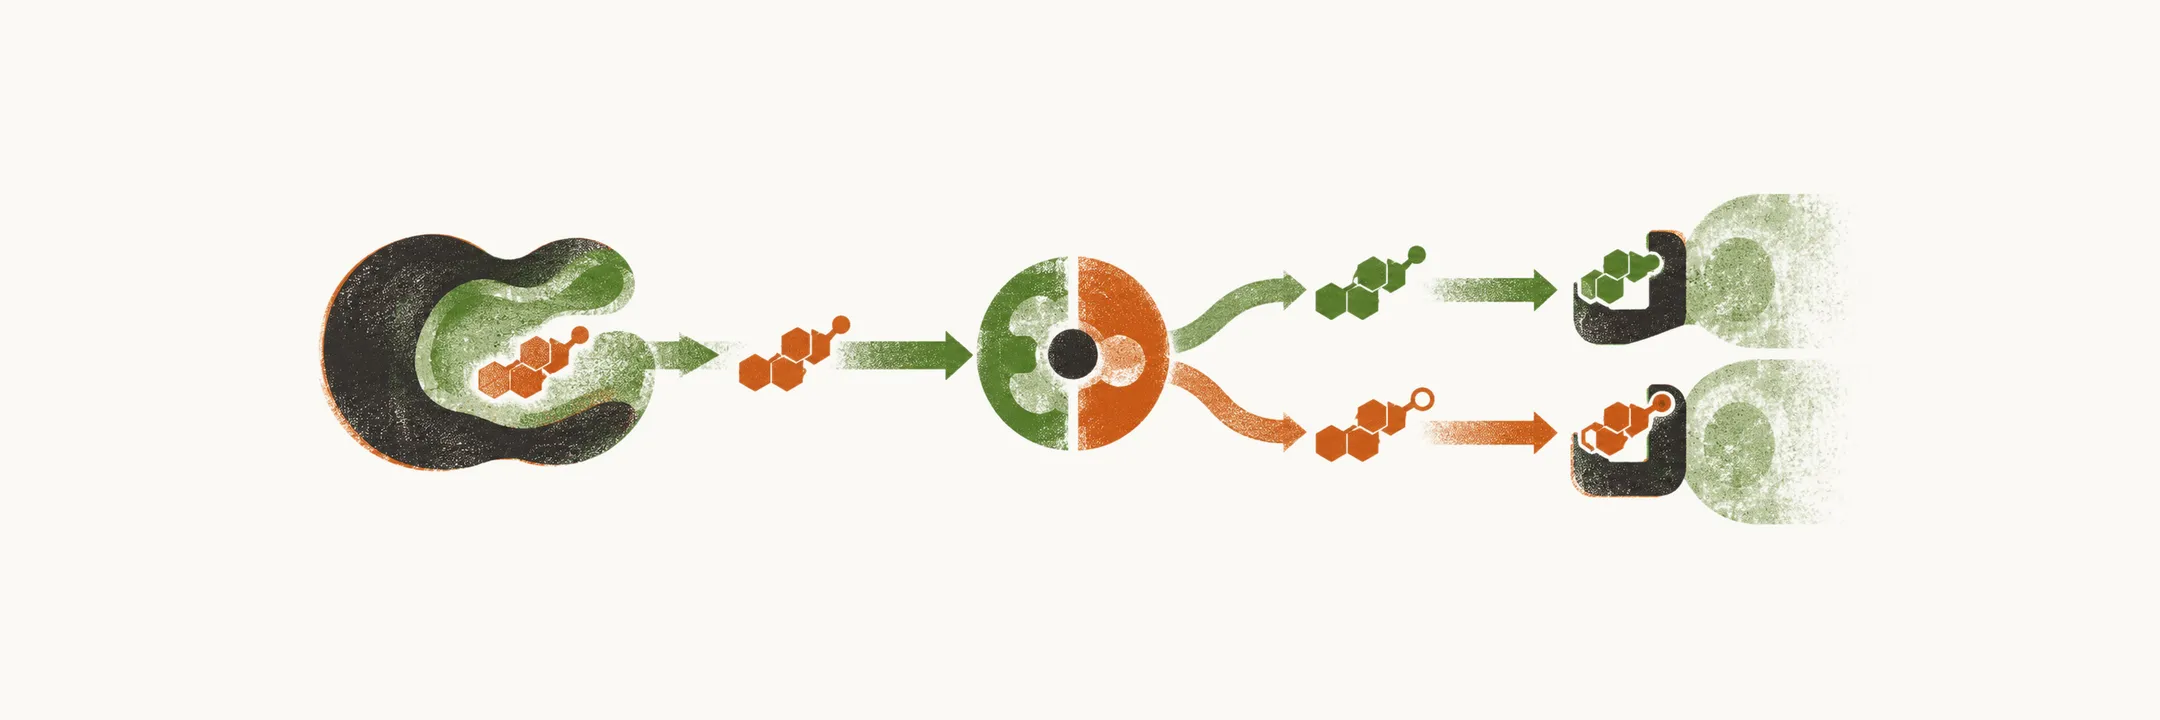
Does the blood level of cortisol tell us how much is acting?
Once the adrenal has made cortisol, the hormone is released into the bloodstream, but the blood level is not the amount that acts. Circulating cortisol is not the same as active cortisol everywhere in the body. Three gates stand between the circulating hormone and its effect: the carrier, the tissue enzymes and the receptor. The first gate is the carrier.
Cortisol is a steroid and dissolves poorly in plasma, so most of it travels bound to a carrier protein. After release it is distributed among three fractions:
- the majority is carried by cortisol-binding globulin (CBG);
- a minority is carried by albumin;
- a very small portion travels as free hormone in the blood.
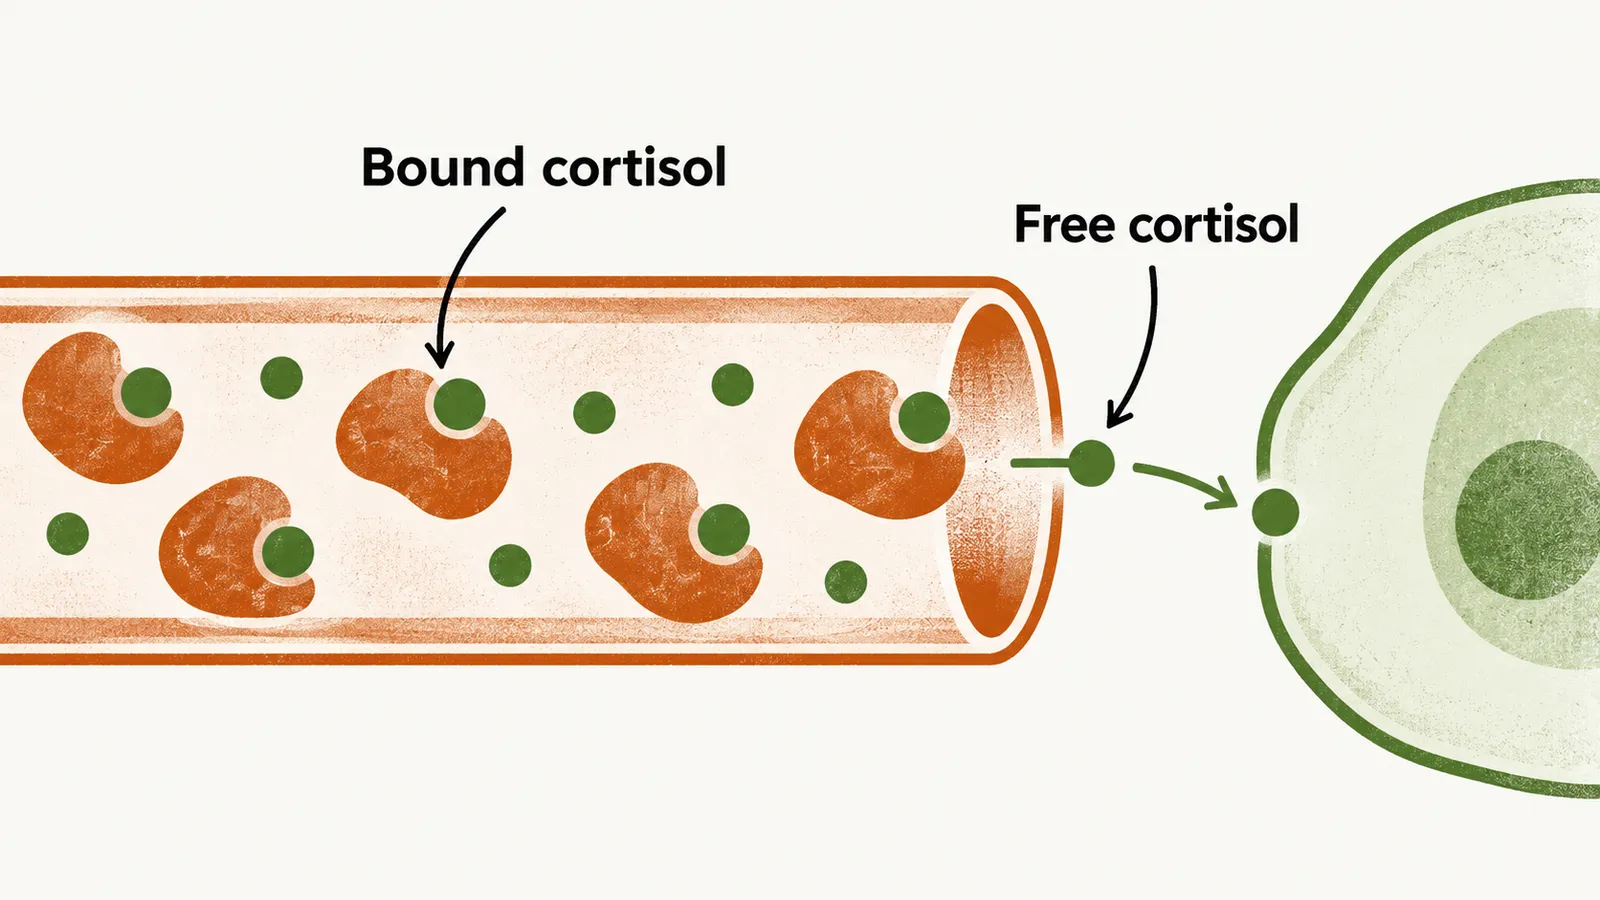
Only the free fraction can leave the vessel and enter cells, because steroids reach their receptors inside the cell by crossing membranes, and hormone that is still bound stays in the vessel. This has a practical consequence. A change in the amount of CBG changes the total measured cortisol without necessarily changing the free, active concentration, so a total value alone can mislead.
Who switches cortisol on and off in the tissues?
Free cortisol that enters a tissue meets the second gate. Individual tissues switch cortisol on or off before it reaches the glucocorticoid receptor. The activated form of the glucocorticoid is cortisol; the inactivated form is cortisone. The two are interconverted in tissues, and which form predominates depends on the enzymes a given tissue carries.
Two enzymes do this work, and they face in opposite directions. Cortisone does not bind the receptors, so a tissue that regenerates cortisol amplifies the local signal, and a tissue that inactivates it mutes the signal.
| Enzyme | Direction | Where it is found |
|---|---|---|
| 11β-hydroxysteroid dehydrogenase type 2 (11β-HSD-2) | inactivates cortisol to cortisone | mainly in the kidney, salivary gland and colon |
| 11β-hydroxysteroid dehydrogenase type 1 (11β-HSD-1) | converts cortisone back to cortisol | other tissues, such as adipose tissue, muscle, brain and liver |
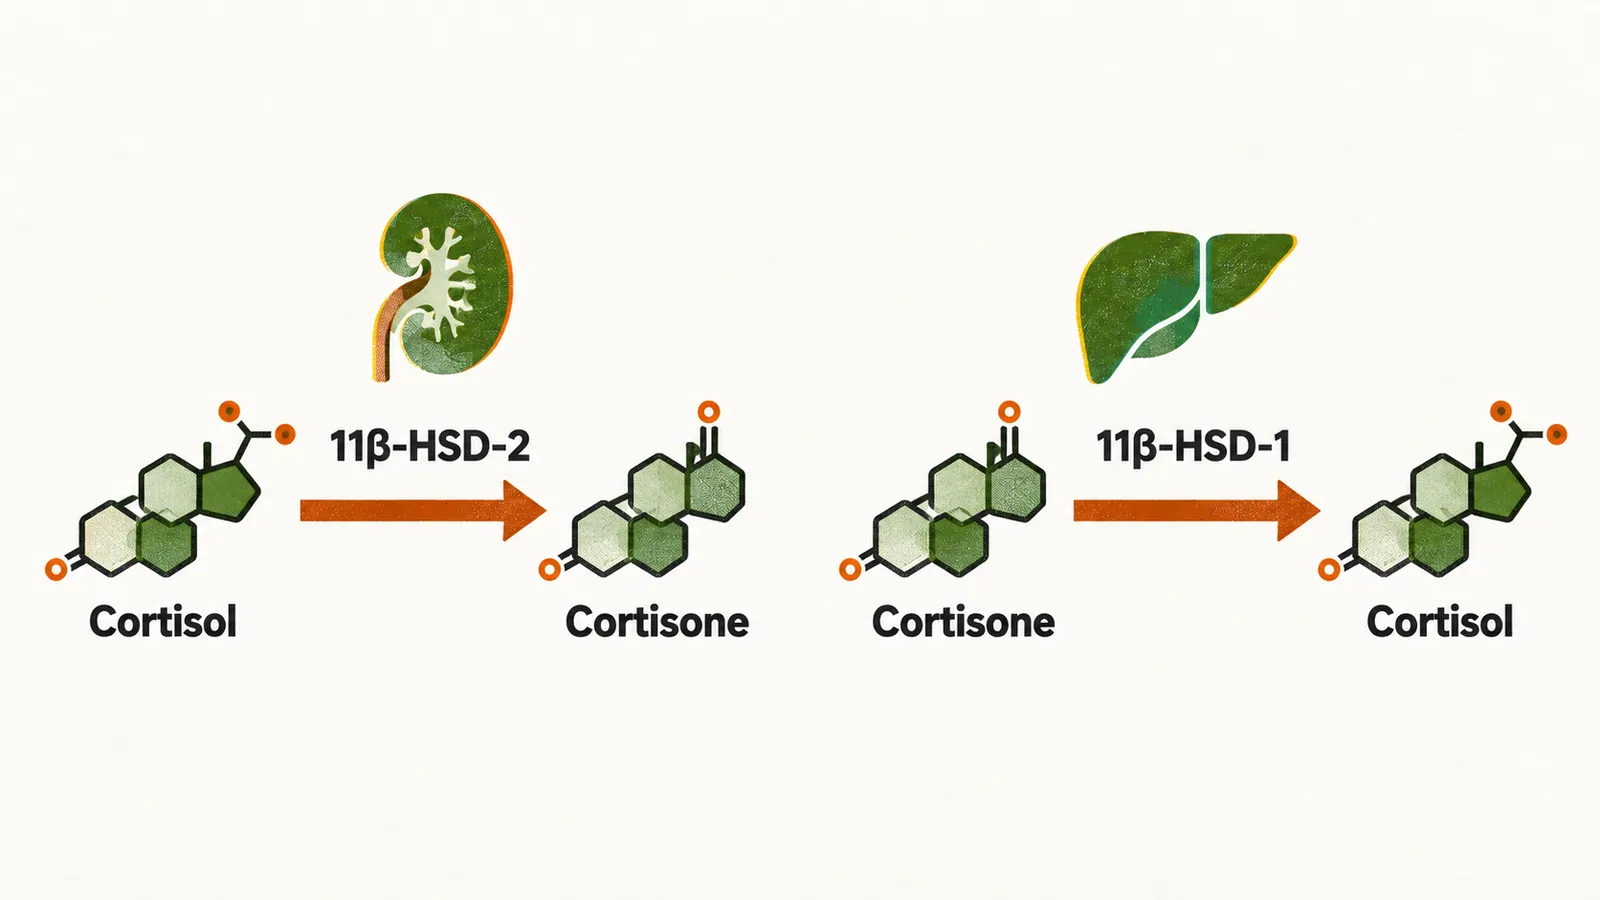
The distribution of the two enzymes therefore decides how much active cortisol each tissue sees. In the kidney this matters especially.
Why does the kidney need the off switch?
The kidney is the clearest case of a tissue controlling its own cortisol. The mineralocorticoid receptor in the kidney binds cortisol as readily as it binds aldosterone, and cortisol circulates at much higher concentration than aldosterone. How does aldosterone then keep control of the site? 11β-HSD-2 inactivates cortisol before it can reach that receptor. Cortisone does not bind the receptor, and aldosterone is not a substrate of the enzyme, so only aldosterone reaches the site. Without 11β-HSD-2, cortisol would act as a mineralocorticoid.
What happens inside the cell once cortisol arrives?
Cortisol that has passed the carrier and the tissue enzymes reaches the third gate. The glucocorticoid receptor (GR) carries out cortisol’s effects. Before the hormone arrives, the receptor sits in the cell in a complex with chaperone proteins. After cortisol enters a target cell, it attaches to the GR, and this causes heat shock proteins to dissociate from the receptor. The receptor and its ligand then dimerise, and the complex enters the nucleus. There it activates or suppresses the synthesis of particular proteins.
Suppression has its own route. If the GR heterodimerises with NF-κB or AP-1, the complex acts as a suppressor of some genes, such as those for pro-inflammatory proteins. In this route the receptor interacts physically with these partners and keeps them from switching on those genes, which fits cortisol’s suppression of inflammation.
What if cortisol cannot be made at all?
All of this assumes that cortisol exists. When its synthesis is blocked, another steroid becomes the nearest glucocorticoid. Corticosterone is the glucocorticoid of the mineralocorticoid pathway, the route in which progesterone is hydroxylated at the 21 position without first being hydroxylated at the 17 position. It also circulates, and it has weak glucocorticoid activity of its own. Its weak activity is why it matters most when cortisol synthesis itself is blocked.
17α-hydroxylase deficiency shows what follows. The enzyme is the doorway into the cortisol route, so cortisol cannot be made. With cortisol low, the brake on the axis is lost and ACTH rises. The precursors that would have led to cortisol are diverted into the mineralocorticoid pathway, and deoxycorticosterone and corticosterone accumulate because of this diversion. Those steroids act on the mineralocorticoid receptor, which, like aldosterone, retains sodium and loses potassium. The result is hypertension and hypokalaemia rather than a glucocorticoid effect.
How can the axis be used to test the adrenal?
The amount of cortisol available depends on the axis that drives its production, and that dependence is what makes adrenal function testable. If cortisol follows the axis, how can the axis be used to find where an abnormality lies?