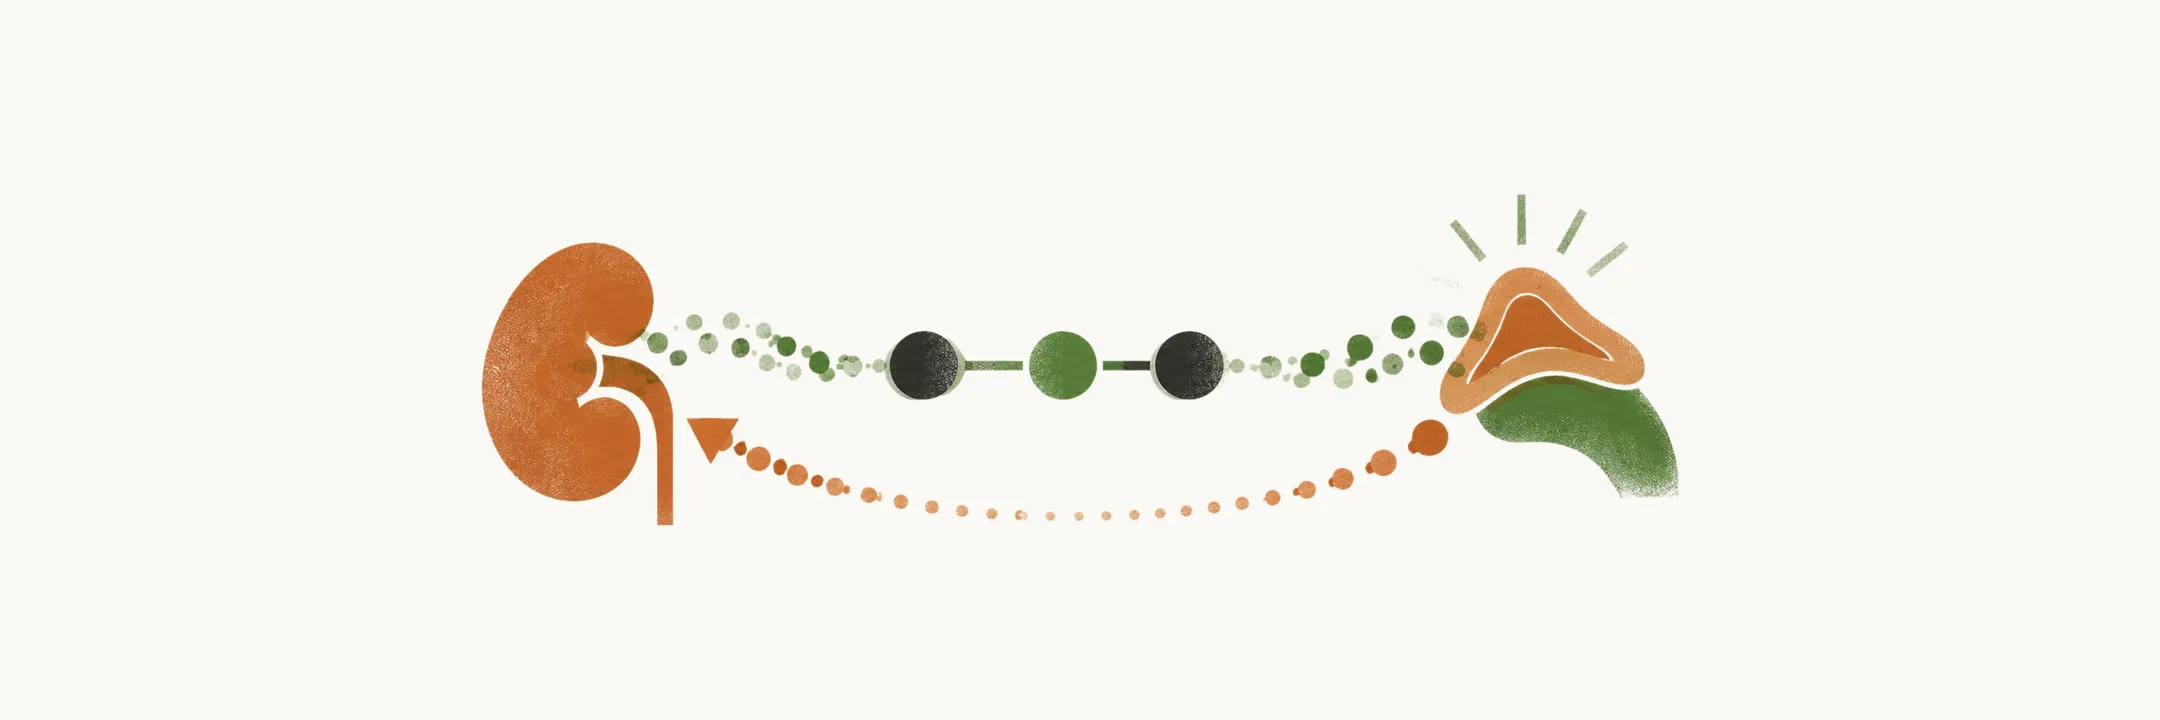
Aldosterone is the mineralocorticoid, made by the zona glomerulosa of the adrenal cortex. It is controlled mainly by the renin-angiotensin-aldosterone system (RAAS), so the kidney, not the pituitary, tells the adrenal what to make. The RAAS links the kidney’s sense of perfusion to sodium retention and blood pressure, and the first question is how the kidney senses perfusion.
How does the kidney sense perfusion and set renin?
The sensor is the macula densa of the kidney. It modulates renin secretion according to the concentration of chloride ion reaching it. When arterial pressure falls, renal perfusion and glomerular filtration fall, and less chloride reaches the macula densa. That drop is the cue: the juxtaglomerular cells, which sit beside the macula densa in the wall of the afferent arteriole, are activated and release renin into the systemic circulation.
The chloride signal therefore tracks perfusion, and the mechanism is a sensor of kidney perfusion. The more the kidney is hypoperfused, the lower the chloride reaching the macula densa. With hyperperfusion or hypertension, more chloride reaches the macula densa and renin release is inhibited. This chloride feedback is how the RAAS adjusts to hypotension physiologically. It also closes the loop: once volume is restored, perfusion and filtration rise and renin falls.
Renin is the major controller of the RAAS, because the rest of the chain follows it. The next question is what renin sets in motion.
How does renin lead to angiotensin II, and what does angiotensin II do?
Renin is only the first step. The liver makes angiotensinogen, and renin converts it to angiotensin I. Angiotensin-converting enzyme (ACE) then converts angiotensin I to angiotensin II. Renin is the gate of this chain: nothing follows without it.
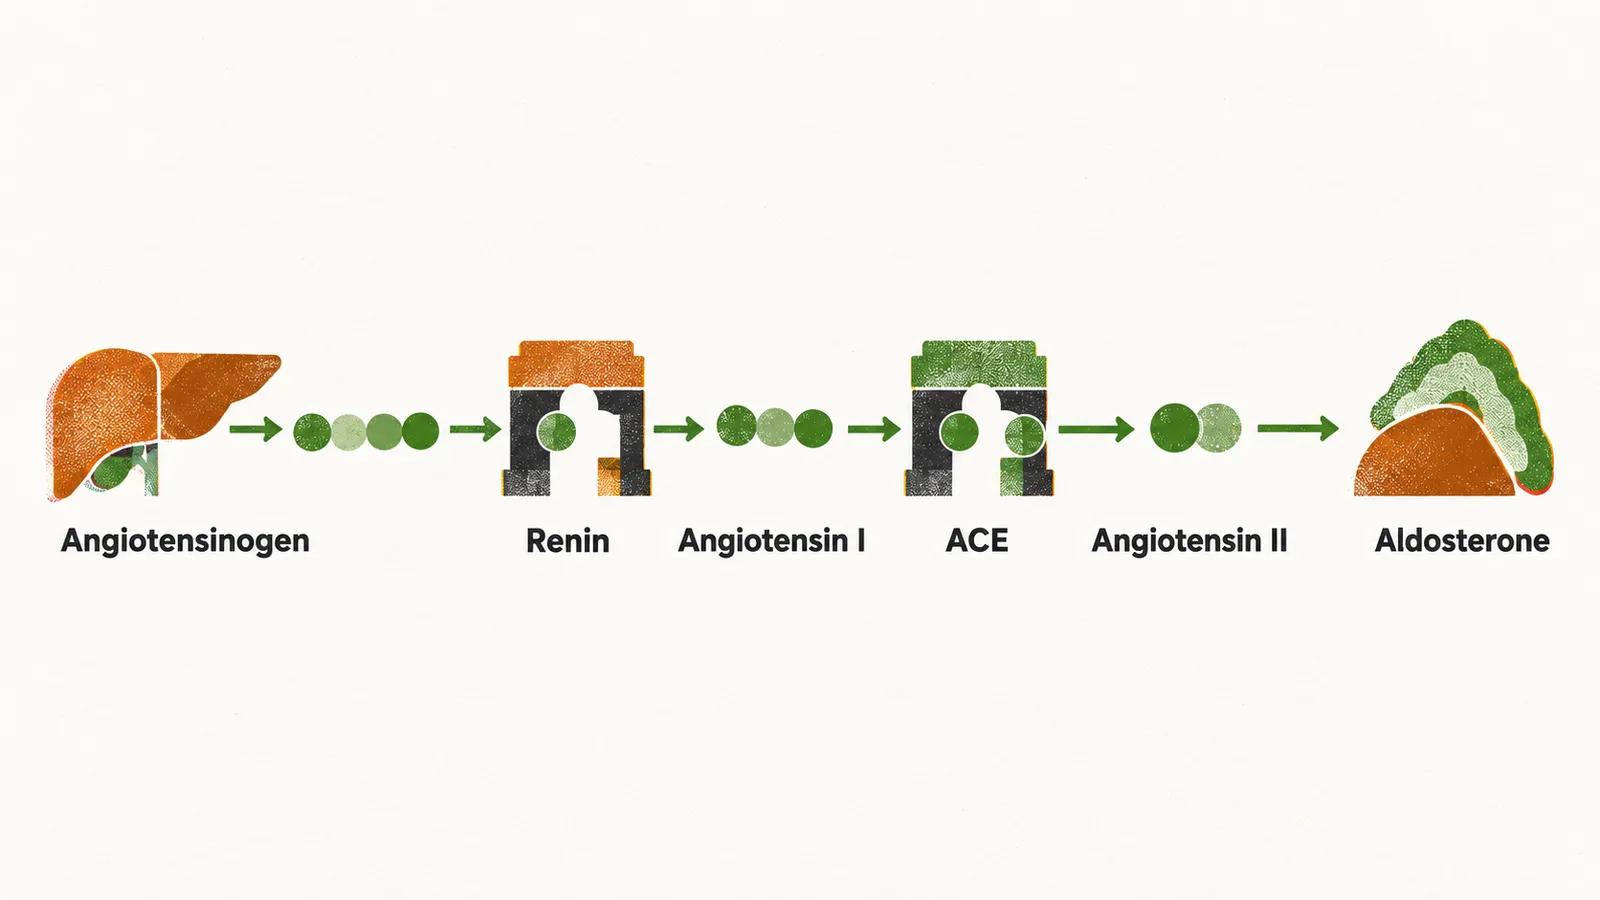
Angiotensin II exerts the final physiological effect, and it does so in four ways, each of which counters the initial low pressure.
- Direct vasoconstriction.
- Release of antidiuretic hormone (ADH). ADH increases water reabsorption, so it increases intravascular volume and pressure.
- Augmented sodium reabsorption by the proximal convoluted tubule (PCT). This increases intravascular water and sodium, so it increases pressure.
- Stimulation of aldosterone production by the zona glomerulosa of the adrenal glands. Aldosterone increases sodium reabsorption by the distal convoluted tubule (DCT), so it too increases pressure.
The first three actions act on vessels, water balance and the proximal tubule. Only the fourth is the link to the adrenal cortex, so it is the one followed here. Renin, through angiotensin II, is one of the most important biological signals for aldosterone secretion. But it is not the only one.
Which signals other than renin reach the zona glomerulosa?
A rise in plasma potassium (hyperkalaemia) stimulates aldosterone release directly. The logic is physiological: aldosterone is what makes the kidney excrete potassium, so this signal couples aldosterone to potassium balance.
ACTH also stimulates aldosterone, but its effect is very low and transient. ACTH does not set the day-to-day level of aldosterone secretion.
Angiotensin II and potassium are therefore the two main controllers. Potassium has no receptor to work through here, and the cell reads it in another way.
How does a zona glomerulosa cell read potassium?
The final step of aldosterone secretion is an electrical event inside the zona glomerulosa cell. The cell is turned on by a change in membrane potential, not by a receptor alone.
The cell senses potassium through its resting membrane potential. At rest, the cell is held hyperpolarised by background potassium channels that let potassium leak out. The leaving potassium carries positive charge out of the cell and leaves the inside negative. When extracellular potassium rises, the gradient driving the leak falls, potassium efflux decreases and the membrane depolarises.
Depolarisation opens voltage-gated calcium channels, chiefly T type. The calcium that enters activates calcium-calmodulin-dependent kinases, and these drive expression of aldosterone synthase (CYP11B2), which is also driven by angiotensin II.
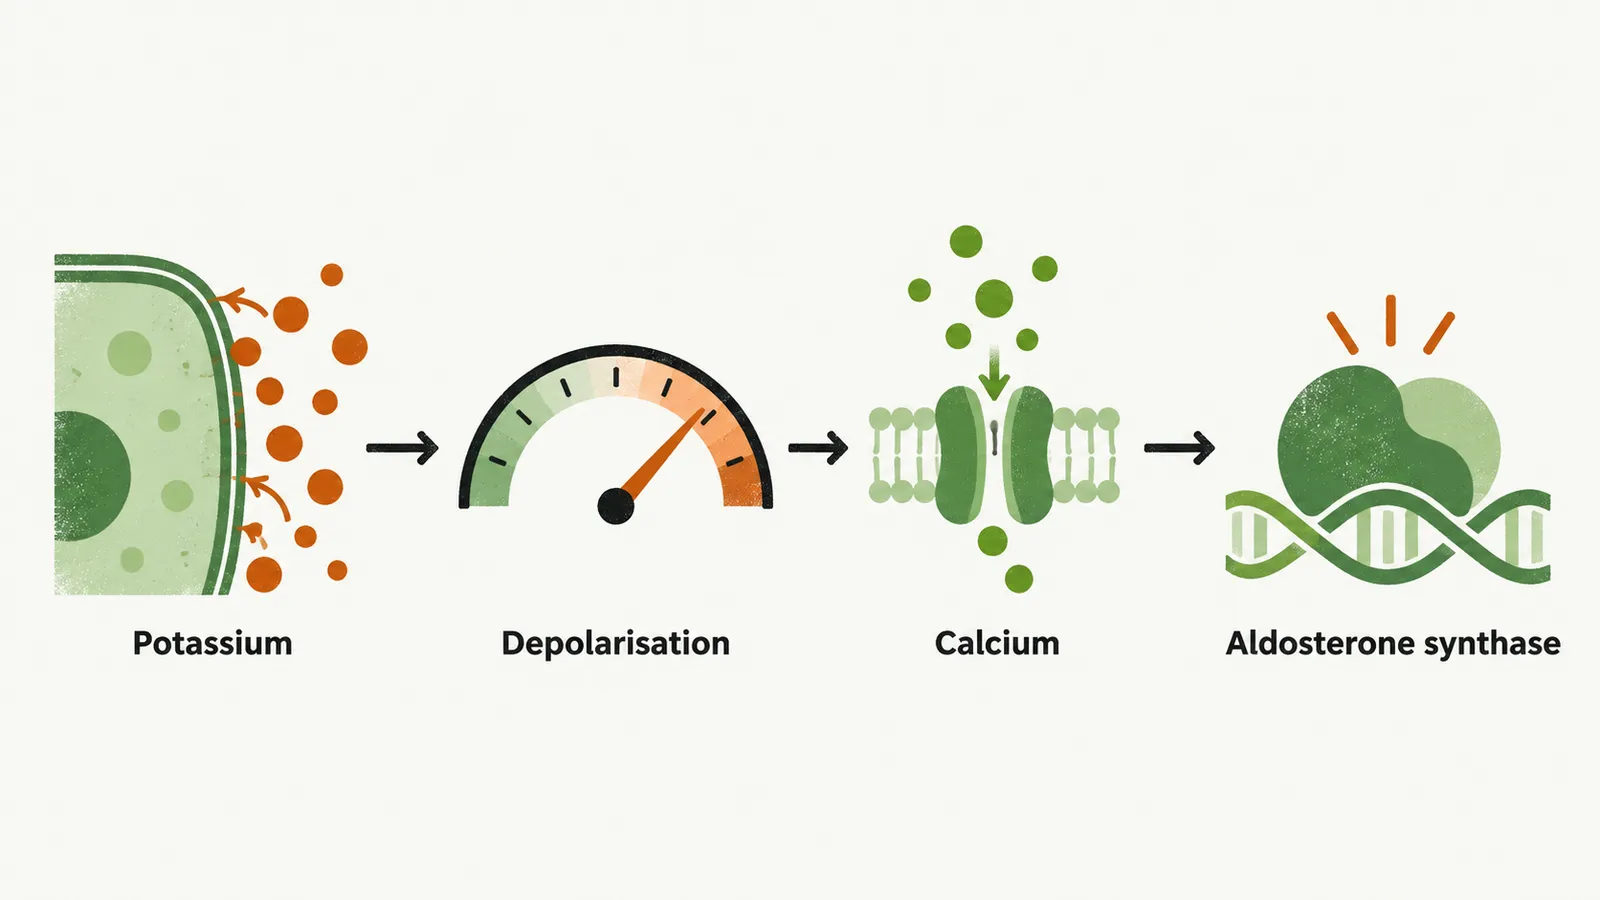
This sequence also shows how a mutation that reduces the potassium current can do the same thing without hyperkalaemia: the cell stays depolarised and aldosterone synthase stays switched on.
Angiotensin II reaches the same endpoint because its receptor also raises intracellular calcium. So the two main controllers of aldosterone, potassium and angiotensin II, both act through calcium and CYP11B2.
Why is aldosterone’s control separate from cortisol’s?
Aldosterone is controlled by renin, potassium and angiotensin II rather than mainly by ACTH. Its control loop is therefore separate from that of cortisol, which is driven by the HPA axis, so one hormone can change without the other.
Cortisol also has a different course after secretion: it is carried in blood and is switched on or off by tissues before it acts. How tissues decide whether cortisol acts is the next question.