What has to work for a period to happen?
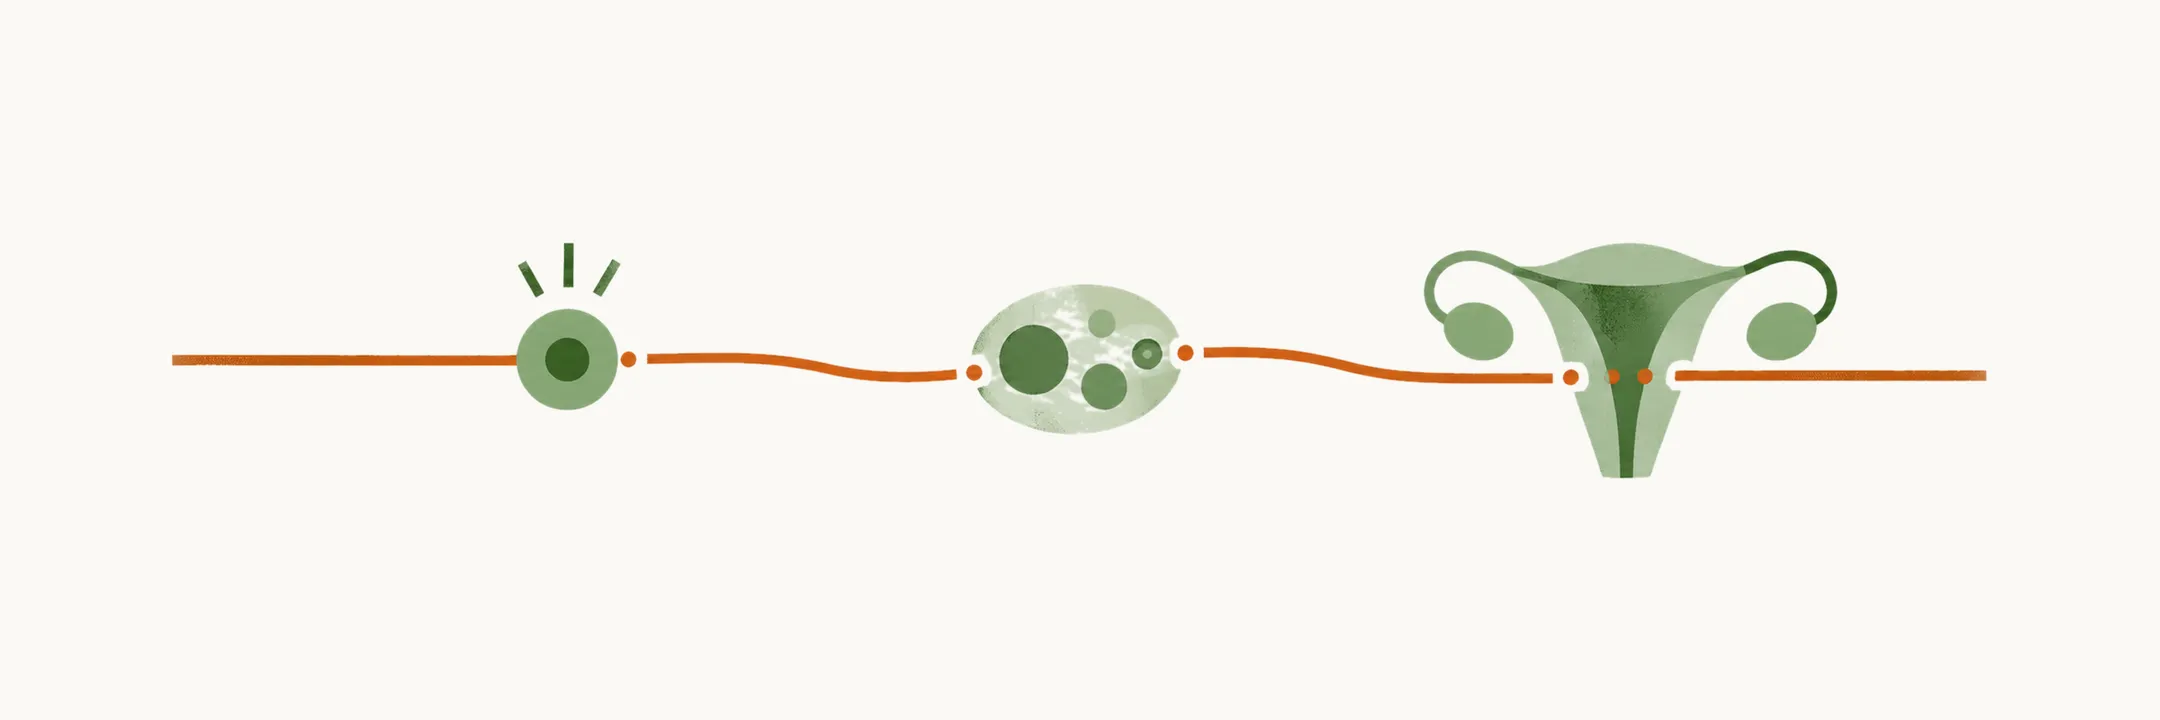
Menstruation is the last step of a four-part relay. The hypothalamus signals the pituitary, and the pituitary releases the gonadotropins, the pituitary hormones follicle-stimulating hormone (FSH) and luteinizing hormone (LH), which drive the ovary. The ovary makes estrogen and follicles. Its estrogen builds the endometrium, and a normal outflow tract (uterus, cervix, vagina) lets the blood leave. The ovary also reports back: its estrogen restrains the pituitary, which is the negative feedback.
If any of the four parts fails, bleeding stops. That is why amenorrhea is a sign, not a diagnosis: the cause can sit at any part of the relay, and evaluation starts with finding which one. Amenorrhea not caused by pregnancy, lactation or menopause affects approximately 3–4% of women of reproductive age.
Where can the relay break?
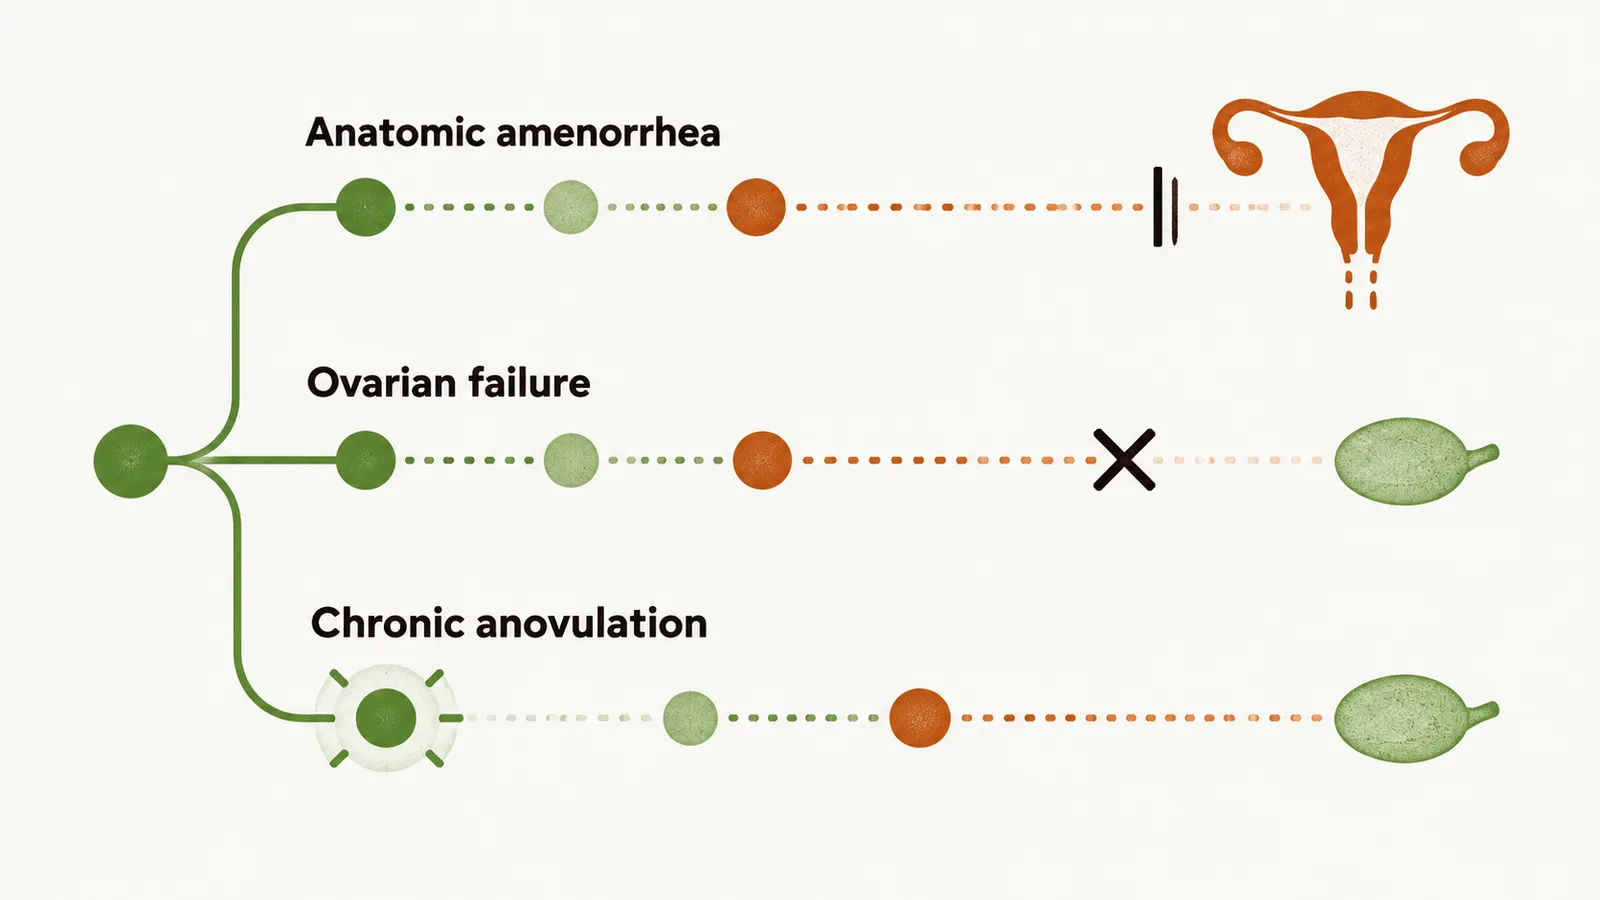
Because the relay has four parts, amenorrhea is grouped by where the fault lies, and three groups point to different parts of the axis.
- Anatomic amenorrhea: the uterus or the genital outflow tract is affected. Either the endometrium cannot respond to hormones or menstrual blood cannot leave the body. The hormones themselves can be normal, because the problem lies in the tissue that should respond or in the exit.
- Ovarian failure: the ovary itself fails and produces little estrogen and few follicles. With no estrogen to restrain it, the pituitary releases more FSH and LH, so the loss of estrogen feedback is what raises the gonadotropins.
- Chronic anovulation: the ovary is intact but ovulation is blocked. Because the ovary is not the fault, the block lies upstream or in the hormonal environment around it: an endocrine disturbance elsewhere in the axis, in the hypothalamus or pituitary, or abnormal steroid feedback. Disorders of the hypothalamus and pituitary lower the signal that drives the ovary, so the ovary lacks stimulation.
What causes each group?
The groups are defined by where the fault is, so each has its own list of causes.
Anatomic causes have one thing in common: the uterus cannot respond or the blood cannot leave. They are pregnancy, Müllerian agenesis or dysgenesis, cervical stenosis, disorders of sexual differentiation, and intrauterine adhesions (Asherman syndrome).
Ovarian failure causes are parallel items that all end in a depleted or damaged ovary:
- menopause
- genetic abnormalities, including X chromosomal causes such as Turner syndrome and pure gonadal dysgenesis, and autosomal causes
- immune dysfunction
- physical insults, such as chemotherapy and radiation
- idiopathic failure
Chronic anovulation is easier to sort by where the signal is disturbed:
- Hypothalamic: psychogenic causes, exercise-associated causes, eating disorders and systemic illness. These make the hypothalamus slow its signal. Neoplasms can also disturb it.
- Pituitary: pituitary tumours and hyperprolactinemia, which can disturb the pituitary’s gonadotropin output.
- Inappropriate steroid feedback: polycystic ovary syndrome (PCOS), adrenal hyperplasia and various neoplasms. Abnormal steroid levels, such as excess androgens, are thought to suppress the axis, so ovulation does not occur.
- Other endocrine disorders: thyroid dysfunction and adrenal hyperfunction, which also disturb ovulation.
What can the history and examination show?
The causes differ in what they leave visible, so the three categories can often be told apart at the bedside. In most patients the history and physical examination suggest the diagnosis before any test is ordered, which makes them the most important step.
Four aspects are examined, and each points toward a different group of causes:
- Body dimension and habitus. Weight loss or low body weight points toward functional hypothalamic causes. Obesity points toward PCOS.
- Androgen-stimulated body hair. Hirsutism, meaning excess androgen-stimulated body hair, points to androgen excess, most often PCOS.
- Breast development and secretions. Breast development shows previous estrogen action, so the ovary has worked before. This helps separate an ovary that never worked from one that has failed. Galactorrhea, milk secretion from the breast, points to hyperprolactinemia, an elevated prolactin level.
- External and internal genitalia. An absent or blind vagina, or an absent uterus, points to an anatomic cause, because the exit or the uterus itself is missing.
Is she pregnant?
Before the relay is tested, the commonest cause is ruled out: the most common cause of secondary amenorrhea is pregnancy. It is evaluated first with a human chorionic gonadotropin (hCG) test. A urinary hCG test can occasionally be falsely negative, so serum hCG is preferred when clinical suspicion is high.
What do the first tests show?
When the examination and the pregnancy test are done, the initial workup consists of four tests, each of which questions one part of the relay: FSH and estradiol (E2) for the ovary, prolactin for the pituitary, and thyroid-stimulating hormone (TSH) for the thyroid.
FSH and E2 are interpreted together because they separate ovarian failure from other causes. FSH shows whether the pituitary is being restrained, and E2 shows whether the ovary is making estrogen. In ovarian failure the ovary no longer produces estrogen, so E2 is low while FSH is high. In most other causes FSH is normal or low, because the signal itself is weak. An elevated FSH in a woman under 40 points toward primary ovarian insufficiency.
Prolactin. Hyperprolactinemia suppresses the gonadotropin signal. It is a common, treatable cause of amenorrhea. Only about one third of women with hyperprolactinemia have galactorrhea, so its absence does not exclude the diagnosis. A mildly elevated prolactin (20–40 ng/mL) should be repeated before the diagnosis is made.
TSH. Both hypothyroidism and hyperthyroidism disturb ovulation. Treating the thyroid disorder usually restores spontaneous menses.
Where does the progestin challenge fit?
An older test asked a similar question about estrogen status. A progestin challenge was traditionally used to separate anovulation from other causes. The endometrium needs estrogen to build, and withdrawing a progestin then makes a primed endometrium bleed. So withdrawal bleeding after progestin means the endometrium has been estrogenised and the problem is anovulation. No bleeding means either low estrogen or an outflow-tract problem. The challenge is less often needed now, because measuring FSH and E2 answers the same question more directly.
What comes after the ovary is shown to have failed?
A high FSH with a low E2 points to ovarian failure. Once the ovary is known to have failed, what has caused the failure?