Why does treatment depend on where the fault is?
Menstruation needs four working links: the hypothalamus, the pituitary, the ovary, and a uterus with a lining that responds and an open outflow. Amenorrhea is a sign that one of them is faulty, so there is no treatment for “no periods” as such. Amenorrhea is treated according to its cause, and management begins only once the cause has been located. The reason is that the same sign needs opposite treatments: surgery for a blocked outflow, hormones for a failed ovary, a change of lifestyle for an energy deficit. Pregnancy and lactation are normal causes and need no treatment, because the axis is working as it should.
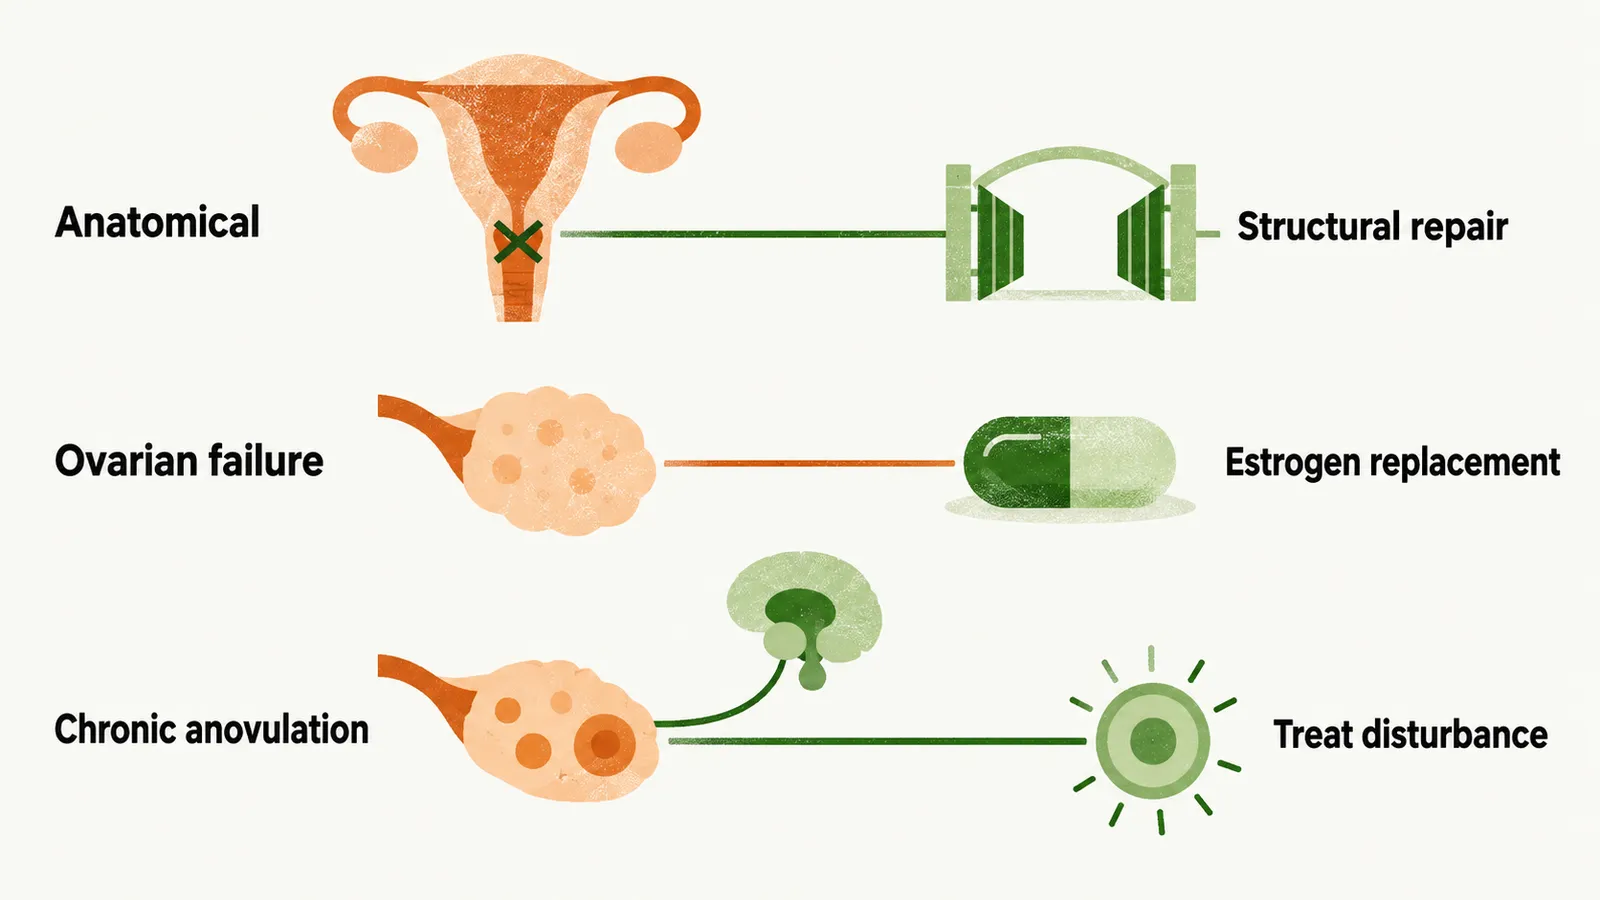
Most cases fall into 3 groups: an anatomical problem of the uterus or outflow tract, ovarian failure, and chronic anovulation. In chronic anovulation the ovary is intact, but ovulation is blocked by an endocrine disturbance elsewhere. It includes functional hypothalamic amenorrhea, polycystic ovary syndrome (PCOS) and hyperprolactinemia, three different disturbances that need three different treatments. Each group breaks a different link, so each has its own kind of treatment.
Once the evaluation has located the fault, the question is what to do about it. The simplest case is a fault in the structure itself.
How is an anatomical cause treated?
If the hormones are working but the structure is not, the repair is structural. Which repair is used depends on which structure is affected.
Müllerian agenesis or dysgenesis
The Müllerian ducts are embryonic structures that form the uterus, the cervix and the upper vagina. When they have not formed normally, the uterus is absent or underdeveloped, a condition called Müllerian agenesis or dysgenesis. With no uterus, menstruation does not occur.
The missing or short vagina is a problem separate from the missing uterus. It can be created or widened with progressive dilators or with surgery. Pregnancy requires a gestational carrier, meaning a woman other than the patient who carries the pregnancy, because the patient has no functioning uterus to carry it herself.
Intrauterine adhesions
Intrauterine adhesions (Asherman syndrome) are scar bands inside the uterine cavity. The scar tissue stops the endometrium from responding. Treatment therefore aims to clear the scar and let the lining regrow. The adhesions are divided hysteroscopically, through a hysteroscope passed into the uterus, which gives a direct view so the bands can be cut under sight. Estrogen is sometimes given afterwards to help the endometrium regrow.
Outflow obstruction
Imperforate hymen, transverse vaginal septum and cervical stenosis are physical barriers on the way out. They block menstrual blood, so removing the barrier fixes the cause. Outflow obstruction is relieved surgically.
If the structure is sound but the ovary no longer answers, what is missing has to be supplied.
What is done when the ovary has failed?
In ovarian failure the ovary can no longer supply estrogen. The causes of primary ovarian insufficiency are covered in Hypergonadotropic Amenorrhea. Management has three tasks, taken in this order: replace what is missing, address fertility, and look for associated disease.
Replacing estrogen
Hormone replacement with estrogen and a progestogen supplies the missing estrogen. The progestogen is added to oppose the estrogen on the endometrium. Replacement should continue until around the average age of natural menopause, 50–51 years. A woman whose ovaries failed early would otherwise go for years without the estrogen she would normally have had, and losing estrogen early raises the long-term risk of osteoporosis and cardiovascular disease.
Fertility
Fertility is a separate question from replacement: replacement supplies hormone, not fertility. Oocyte donation is the only proven treatment for fertility. A small proportion of women with primary ovarian insufficiency, 5–10%, conceive spontaneously, so spontaneous pregnancy is possible but cannot be counted on. When ovarian failure can be anticipated, for example before gonadotoxic treatment, oocyte or ovarian tissue cryopreservation can be offered.
Associated disease and bone
Ovarian failure can accompany other conditions, so these are looked for. Associated autoimmune disease, such as thyroid or adrenal disease, is looked for, because autoimmune disease is among the causes of primary ovarian insufficiency. Estrogen loss also affects the skeleton, so bone density is monitored.
If the ovary is intact, treatment targets the disturbance that blocks it.
How is chronic anovulation treated?
In chronic anovulation the cause is an endocrine disturbance rather than a damaged gonad. Because the ovary itself is not damaged, the condition is usually reversible, and treatment is aimed at the disturbance itself. Each cause has its own treatment: functional hypothalamic amenorrhea, PCOS, hyperprolactinemia and thyroid dysfunction.
Functional hypothalamic amenorrhea
Functional hypothalamic amenorrhea results from an energy deficit. The hypothalamus slows its GnRH output in response to weight loss, stress or excessive exercise; this is thought to be an adaptive response to low energy availability. Treatment therefore corrects the energy imbalance: more calories, less exercise, and often weight gain. It includes psychological support, such as cognitive behavioural therapy.
Combined oral contraceptives are not recommended in functional hypothalamic amenorrhea for the sole purpose of regaining menses or protecting bone, since a pill bleed can give false reassurance while the energy deficit continues. Estrogen replacement may be considered when bone density is low after 6 to 12 months of these measures. The measures come first because correcting the deficit treats the cause.
PCOS
PCOS is managed first with lifestyle change and weight management. Combined oral contraceptives regulate cycles and protect the endometrium, because their progestin component opposes estrogen on the lining. Metformin helps when insulin resistance is present. When pregnancy is desired, ovulation is induced, with letrozole used first.
Hyperprolactinemia
Hyperprolactinemia is an elevated prolactin level. Dopamine from the hypothalamus normally restrains prolactin release by acting on dopamine receptors of the pituitary cells that make it. So hyperprolactinemia is treated with a dopamine agonist such as cabergoline, which acts on those receptors and lowers prolactin secretion. Persistently elevated prolactin should be investigated with pituitary MRI, which looks for an adenoma that may be the source of the excess; a pituitary adenoma is found in 50–60% of persistent cases.
Thyroid dysfunction
Thyroid dysfunction is treated directly. Restoring the euthyroid state usually restores spontaneous menses.
Treating the cause takes time, and in the meantime the endometrium faces a problem of its own.
Why does the endometrium need protection in chronic anovulation?
Consider a woman who still produces estrogen but does not ovulate, as in PCOS. Without ovulation there is no corpus luteum and so no progesterone. Estrogen promotes the growth of endometrial glands, while progesterone restrains that growth and prompts secretory change. The endometrium is therefore exposed to estrogen without the progesterone a normal cycle provides, and unopposed estrogen raises the risk of endometrial hyperplasia and cancer.
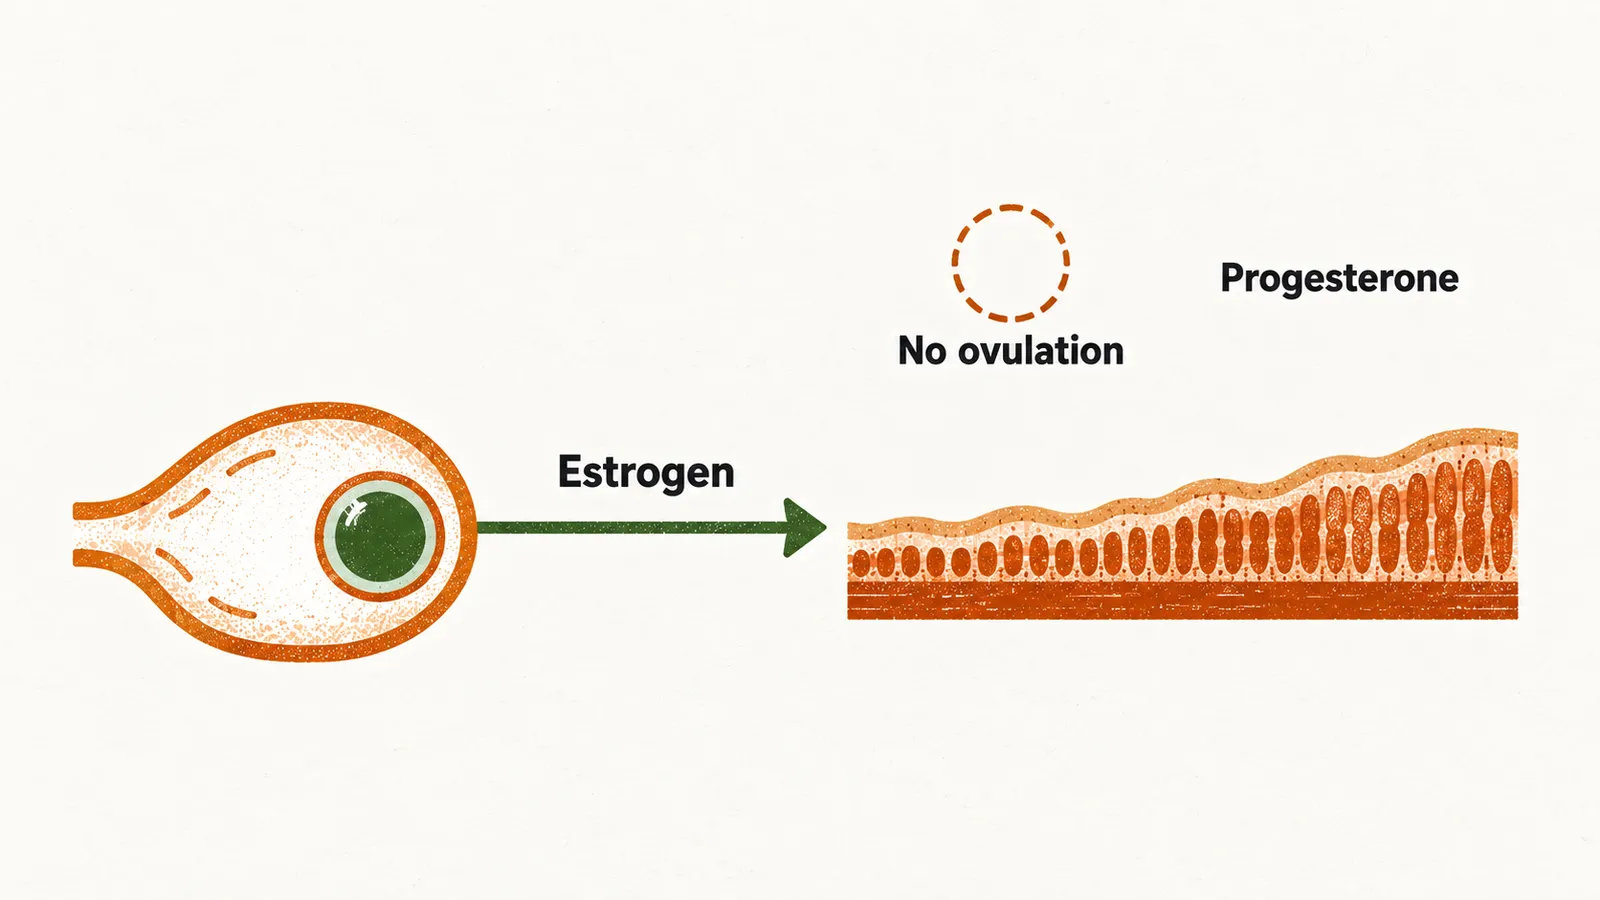
For that reason a withdrawal bleed is induced with a progestogen every 3 to 4 months, or a combined oral contraceptive is used. The progestogen sheds the lining that has built up, as a normal cycle would.
Once the cycle returns, how is ovulation itself followed and fertility pursued?