
Why are the gonadotropins high?
Hypergonadotropic amenorrhea is amenorrhea with high gonadotropins, the pituitary hormones FSH and LH that drive the ovary. The name says where the fault lies: high levels mean the pituitary is working, so the problem is downstream, in the ovary.
A high FSH with a low estradiol points to ovarian failure, as used in Causes and Initial Evaluation of Amenorrhea. Ovarian estrogen normally restrains FSH and LH. When the ovary stops producing estrogen and follicles, that negative feedback is lost and gonadotropin secretion rises. A high FSH is therefore the pituitary’s response to an ovary that no longer answers.
Primary ovarian insufficiency (POI) is one of the main causes of hypergonadotropic amenorrhea. Its triad is amenorrhea, hypergonadotropinism and hypoestrogenism, and the three form one chain: without follicles there is no estrogen, and without estrogen the brake on the pituitary is off.
What is primary ovarian insufficiency?
The triad gives the picture; the diagnosis needs criteria. A few missed cycles are common, so the criteria wait before calling an ovary failed, and 40 years marks the line between insufficiency and ordinary menopause timing. POI is diagnosed when all of these are present:
- disordered menstrual cycles, either spontaneous amenorrhea or irregular cycles, for at least 4 months;
- an FSH above 25 IU/L;
- a woman under 40 years of age.
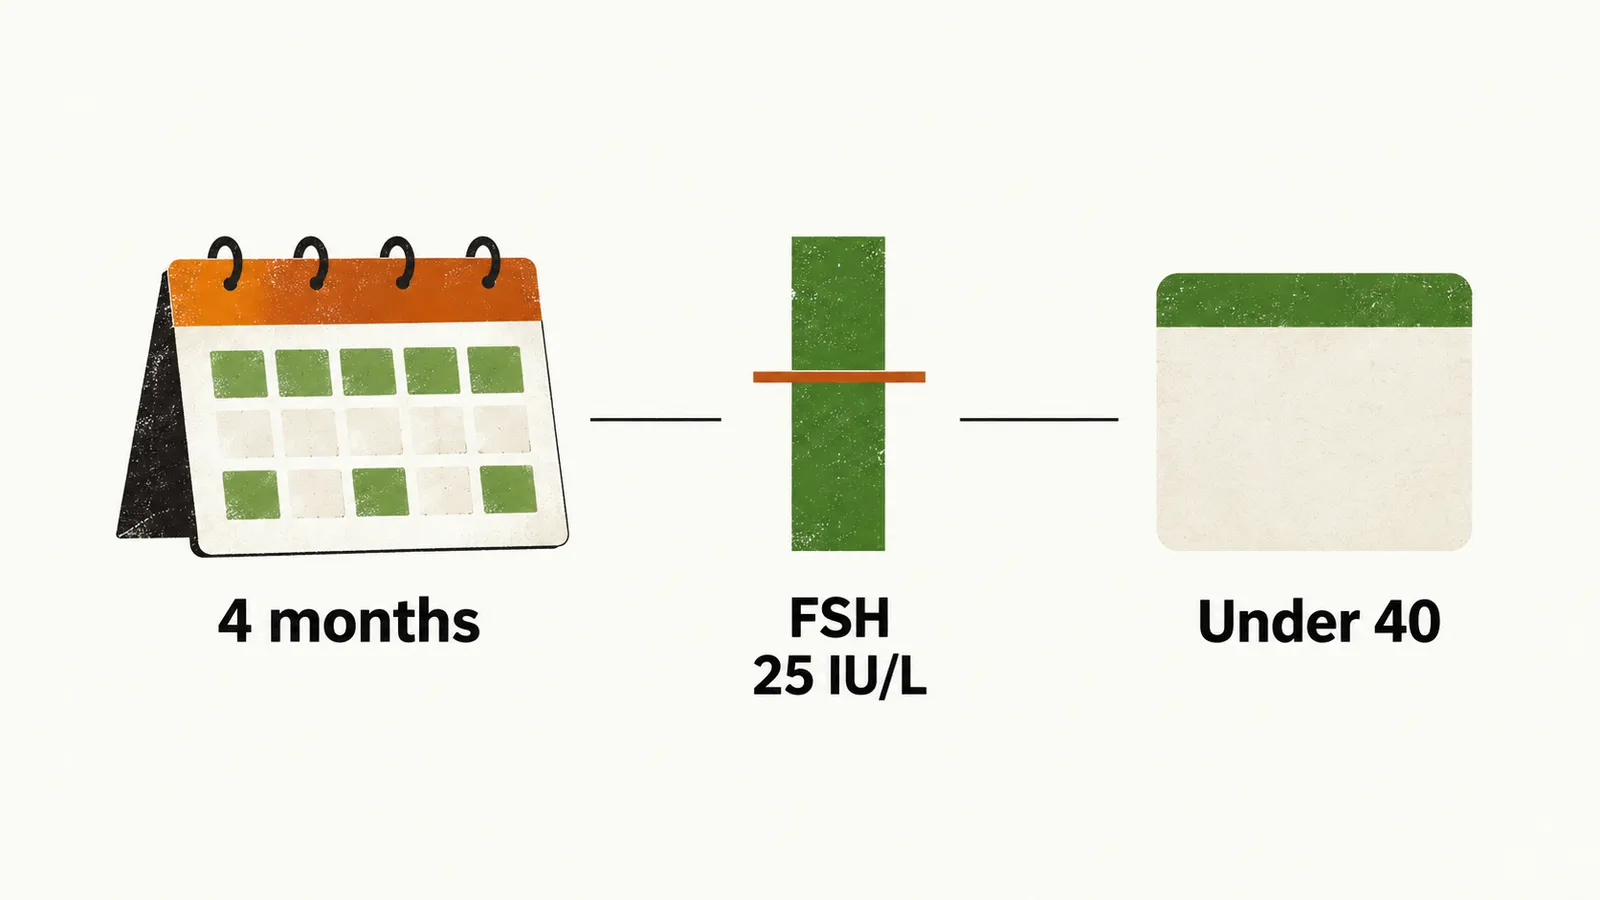
FSH need not be measured on a particular cycle day. A raised FSH should be repeated if there is diagnostic uncertainty. Pregnancy should be excluded first, as it is a common reason for a missed period at this age.
POI can present as primary or secondary amenorrhea. The ovary can fail before puberty or after cycles have begun: a girl whose gonad never formed properly never starts periods, while a woman whose follicles run out stops them.
Why can the cause be so many things?
Criteria say that an ovary has failed, not why. POI is a very heterogeneous condition, and its causes range from a single genetic mutation, cytological chromosomal abnormalities and a single enzymatic mutation or deficiency to environmental causes. An ovary can be built wrongly, can be unable to make hormones or respond to them, or can be damaged later.
Genetic causes are the most important single group of POI, but a specific genetic cause is identified in only a minority of cases. The causes fall into three groups, with the genetic group first:
- Genetic: disorders of gonadal development, single-gene changes such as FMR1, enzymes of steroid synthesis and the FSH receptor.
- Autoimmune.
- Environmental.
Following the ovary’s life, the causes concern how it is built, how it works, and what harms it afterwards.
What if the ovary never forms properly?
The most direct way for an ovary to fail is never to be built. Gonadal dysgenesis means the primary gonad, ovary or testis, does not develop or is under-developed. Several causes of POI involve it, and the gonad lacks follicles from the start.
Gonadal dysgenesis has three forms, depending on how much gonad forms: complete, partial and mixed.
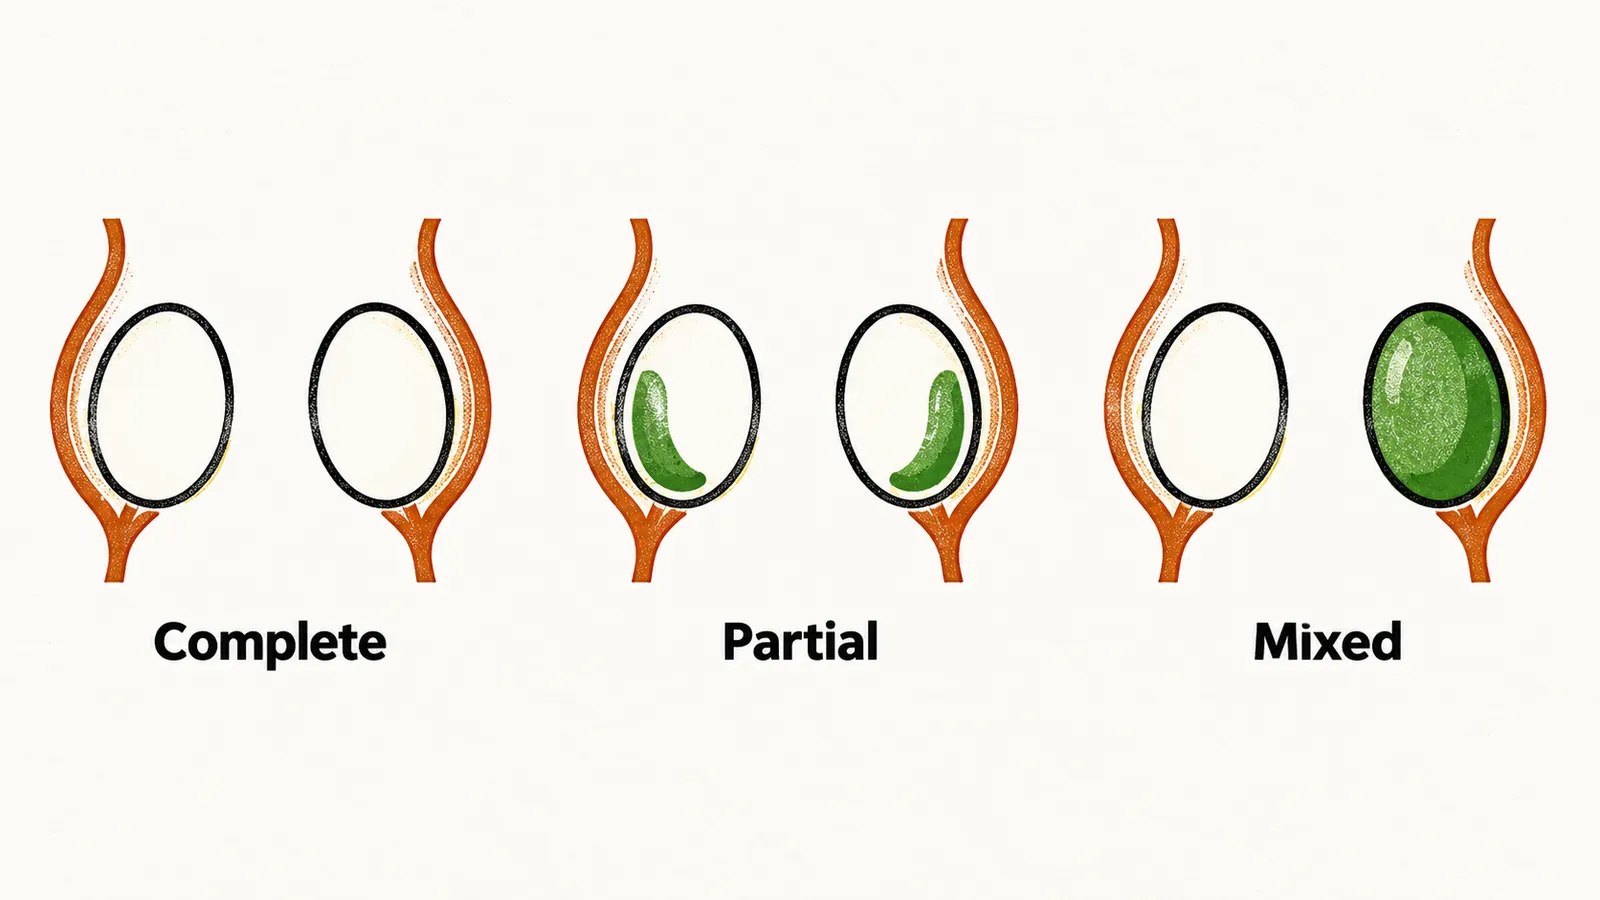
Complete gonadal dysgenesis
Here the gonads are entirely replaced by a streak gonad, a strand of fibrous tissue. Complete gonadal dysgenesis occurs in women in two situations, 46,XX and 46,XY.
In 46,XX dysgenesis the woman has 46,XX genetics and apparently female characteristics, with a uterus and vagina, but she is infantile in form with streak gonads. She carries mutations in genes needed for ovary development, which can be autosomal or X-linked, and these mutations leave the ovaries as fibrous streaks. The uterus and vagina form regardless because they do not depend on the gonad.
In 46,XY dysgenesis the subjects are genetically male. They have a mutation in the SRY gene, or in another gene needed for testis determination, and SRY is the switch that starts testis development. The testes therefore do not develop. Without testes there is no anti-Müllerian hormone, so the Müllerian structures persist, and no testosterone, so the external genitalia stay female. Internal and external genitalia are female, the gonads remain streaks and the person is infertile.
Complete gonadal dysgenesis with streak ovaries must be told apart from Turner syndrome. Turner syndrome has characteristic physical findings, whereas pure gonadal dysgenesis has none of its specific findings: height and weight are normal, the genitalia are normal, and only the ovaries are streaks.
Partial gonadal dysgenesis
Some degree of gonadal development occurs, but it is not complete. A partly developed gonad makes hormones incompletely, and this can lead to ambiguous genitalia.
Mixed gonadal dysgenesis
Mixed gonadal dysgenesis happens because of genetic mosaicism, which means more than one cell line with a different chromosome complement in the same person. Two cell lines let the two gonads develop differently: there is one streak gonad on one side and a partially developed gonad, a testis, on the other. Most patients carry 45,X/46,XY. The vast majority of cases are raised as females.
The dysgenetic gonad
A dysgenetic gonad has high malignant potential, so it should be removed surgically. The risk is thought to be tied to Y-chromosome material in the retained gonads.
Why does the X chromosome matter?
Even a well-built ovary needs two intact X chromosomes. An intact 46,XX karyotype is necessary for ovary development and for oocyte survival, and depletion or mutation of X-chromosomal material can exhaust the ovary and lead to POI. Three X-chromosome loci are associated with POI, and mutations at these loci are among its identified causes:
| Locus | Position | Note |
|---|---|---|
| POF1 | Xq26–q28 | includes the FMR1 gene |
| POF2 | Xq13.3–q21.1 | |
| POF4 | Xp11.2 | BMP15 gene, involved in follicle development |
The FMR1 gene, on the X chromosome, shows how a repeat count turns a gene from harmless to ovary-damaging. The count of CGG repeats decides the state of the gene:
| State | CGG repeats |
|---|---|
| Normal | 5–44 |
| Intermediate expansion | 45–54 |
| Premutation | 55–200 |
| Full mutation | more than 200 |
In the premutation state the gene still produces mRNA. The expanded mRNA is toxic to ovarian cells and accelerates follicular atresia, so carriers are at risk of POI. The premutation is the most common single-gene cause of POI, found in about 2% of women with sporadic POI and about 14% of women with familial POI.
In the full mutation state the gene is silenced and its function is lost, which causes fragile X syndrome. Its presentation is prominent in males and milder in females, because one X chromosome is largely inactivated in a woman, so a normal X can still work in many cells.
A woman with a premutation can pass on more repeats, because the expansion occurs during maternal transmission. It does not occur when a father passes on the premutation.
Which single genes disturb steroid synthesis and FSH signalling?
After the X chromosome, genes elsewhere can block the ovary’s hormone synthesis or its response to FSH.
17-α hydroxylase mutation is a mutation of CYP17A1. The enzyme is needed for steroid synthesis in both the adrenal gland and the ovary, so in girls who survive to their teenage years the block stops cortisol and sex steroid synthesis and can lead to POI. Steps before the block build up: progesterone, deoxycorticosterone and corticosterone rise. FSH and LH rise too, since sex steroids are absent. The excess mineralocorticoid causes hypertension with low potassium, and aldosterone itself is suppressed. Mutations of 17,20-desmolase and 20,22-desmolase affect the same steroid pathways.
Aromatase mutation prevents estrogen synthesis, because aromatase converts androgens to estrogen. The result is severe estrogen deficiency. Patients are virilized by high androstenedione that cannot be converted to estrogen, and this is manifested at birth by clitoromegaly and posterior labioscrotal fusion.
FSH receptor mutation (the gene is on chromosome 2) can lead to failure of folliculogenesis. The receptor is how the ovary hears FSH, so the follicles do not respond even though FSH is high. FSH resistance is fairly rare in many populations.
Other genetic mutations involve the inhibin alpha gene (INHA), the BMP15 gene and the AIRE gene.
What can injure a normal ovary?
A correctly built ovary can still be harmed afterwards, by the immune system or by the environment.
POI can be associated with other endocrinopathies. Autoimmune diseases tend to cluster. The most common autoimmune association in women is thyroiditis. POI can also be seen in poly-endocrine autoimmune conditions presenting with hypoparathyroidism, hypoadrenalism and mucocutaneous candidiasis. In the restricted ovarian autoimmune condition, the immune attack is confined to the ovary.
Among environmental causes, the ovary can be damaged directly by ionizing radiation, chemotherapeutic agents or viral infections.
Once the ovary has failed and the cause is known, what can be done about the missing estrogen and the question of fertility?