
Diabetes insipidus (DI) is hypotonic polyuria: large volumes of dilute urine, caused by too little action of antidiuretic hormone (ADH, also called arginine vasopressin, AVP). Urine is concentrated only when enough ADH arrives and the collecting duct responds to it. That gives three fault lines. In hypothalamic DI (HDI) too little ADH is secreted. In nephrogenic DI (NDI) the kidney is resistant to ADH. In dipsogenic DI (DDI) the fluid intake is so large that it suppresses ADH.
Diagnosis is a way of finding which line has broken, and treatment mends that line.
How do we find out whether polyuria is diabetes insipidus?
The work-up must establish that polyuria is present, show that it is DI, and then tell the forms apart, because treatment differs between them. The order runs from the cheap and common to the specific: each step removes a commoner explanation before the next. The first steps are the physical examination, the history, and laboratory findings that rule DI out. The examination and history are often the most important step in diagnosis and differential diagnosis.
The first question is whether the patient really has polyuria, so diagnosis requires confirmation of it. A complaint of “passing a lot of urine” is often something else. In some cases there is only frequency of urination, caused by a urinary tract infection: many small voids, not a large total volume. This is why the 24-hour urinary volume is measured. If it is less than 3 litres, the total is not in the polyuria range, there is nothing for the ADH system to explain, and osmotic studies are unnecessary.
The second question is whether the urine is dilute. Glycosuria indicates diabetes mellitus, not diabetes insipidus: glucose in the urine drags water out with it, so the polyuria comes from a solute load and the urine is not dilute. Urine osmolality helps answer it. A urine osmolality greater than 700 mosmol/kg indicates proper function of AVP, because a kidney that can make concentrated urine has both the hormone and a response to it, so DI is excluded. Polyuria with a normal urine osmolality is mostly polydipsia. In DI the kidney makes water-like urine because ADH action is missing, so the urine osmolality is very low, mostly close to maximally diluted urine, which is less than 100 mosmol/kg. Almost all DI patients have a urine osmolality less than 300 mosmol/kg.
A dilute urine shows DI but not which fault line has broken. Can the patient’s story already say?
What can the history tell us before any test?
The history can point to a form, and that narrows which test is needed. Daytime polyuria occurs in patients with DDI, since their urine follows their drinking; in HDI and NDI there is nocturia as well, as the earlier note on presentation described.
A history of drug use, especially lithium, is important, because a drug can leave the kidney resistant to ADH. A history of a sellar mass, or current signs and symptoms of a sellar tumour, has important value in differential diagnosis. It is especially relevant for craniopharyngioma and germinoma, two tumours of that region that can damage the ADH pathway and so point to HDI. A sellar mass history also indicates that the mass is most probably not a pituitary adenoma. A strong family history of autoimmune thyroid disease can suggest autoimmune HDI.
When the history leaves the form open, the kidney can be asked directly.
How does the water deprivation test separate the forms?
Confirmation that polyuria is caused by DI comes from the two-step water deprivation test. It asks two questions in turn: does dehydration make the kidney concentrate, and if not, does desmopressin fix it?
In the first step the patient is dehydrated for 8 hours. Dehydration raises plasma osmolality, the normal stimulus for ADH, so the normal response is secretion of AVP and a rise of urine osmolality over 750 mosmol/kg. In DDI the response is similar to normal, with urine osmolality greater than 750 mosmol/kg, because the hormone system and the kidney are intact and the kidney can concentrate once drinking stops. In HDI the urine osmolality does not increase to normal values: there is no hormone to release. In NDI it does not increase either: the hormone is released but cannot act. Dehydration therefore cannot separate HDI from NDI, and a second step is needed.
The second step is the response to intramuscular desmopressin, which distinguishes NDI from HDI. Desmopressin supplies the missing hormone action from outside, so it tests whether the kidney can respond when the hormone is present. In HDI the response is an increase of urine osmolality: the kidney was fine and only the hormone was missing. In NDI the urine osmolality does not increase after desmopressin, because of resistance to AVP.
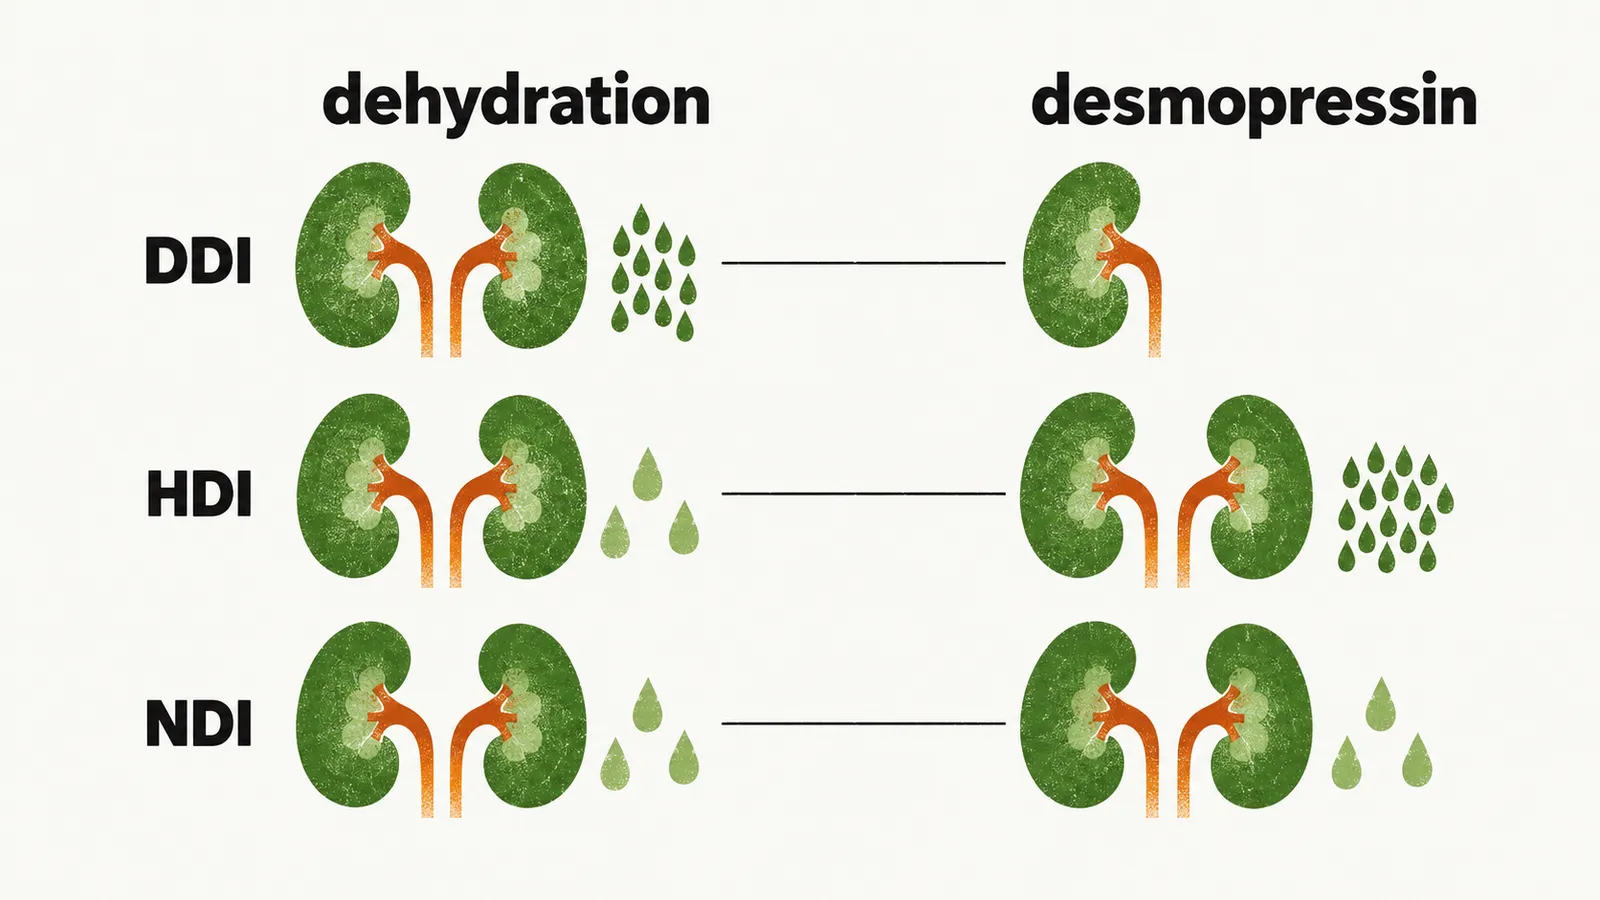
| Form | Step 1: 8 hours of dehydration | Step 2: desmopressin |
|---|---|---|
| DDI | Urine osmolality greater than 750 mosmol/kg, similar to normal | — |
| HDI | Urine osmolality does not rise to normal values | Urine osmolality increases |
| NDI | Urine osmolality does not rise | Urine osmolality does not increase, because of resistance to AVP |
This test infers the hormone from what the urine does. Why not measure the hormone itself?
Can the hormone be measured directly?
It can. The most accurate way to diagnose DI is to stimulate AVP release with a hypertonic saline infusion and measure the hormone in plasma. The salt load raises plasma osmolality directly, without making the patient dehydrate, and the measurement asks the hormone question directly rather than inferring it from urine.
AVP is difficult to measure, because most of it is bound to platelets and the sample must be handled quickly. Copeptin is the stable fragment released from the same precursor in equimolar amounts as AVP, so its level mirrors the hormone. Copeptin is now measured instead of AVP. The response of the AVP system, which copeptin reflects, separates the forms:
- HDI: after hypertonic saline there is no increase of AVP correlated with the increase of plasma osmolality. The neurons that make the hormone are damaged, so a rising osmolality gets no answer.
- NDI: AVP secretion in plasma increases, correlated with blood osmolality, but the patient still has hypotonic polyuria. The hormone system answers the stimulus; the kidney does not.
- DDI: AVP secretion in plasma increases, correlated with blood osmolality, and the kidney responds normally, producing less urine and concentrating it.
All these forms fail inside the patient’s own system. Can ADH be lost in another way?
Is there another way to lose ADH?
Yes: pregnancy-related DI, a less common form. It is caused by placental vasopressinase, an enzyme that degrades ADH in the mother’s circulation. Here the hormone is destroyed in the circulation rather than not being made. Placental vasopressinase rises with placental size, and pregnancy-related DI mostly occurs in the third trimester.
Once the tests have named the failed step, what is done about it?
How is each form treated?
Treatment differs by form because each form fails at a different step.
HDI is treated with desmopressin, the analogue of vasopressin. It replaces the missing hormone, and the kidney responds to it, as step two of the water deprivation test showed. Desmopressin is not degraded by the vasopressinase of pregnancy, so it also treats the pregnancy-related form. The dose is kept to the smallest that controls symptoms. The reason is that desmopressin retains water and can produce hyponatremia if the patient drinks more than the urine output: the drug takes away the kidney’s ability to make dilute urine, so water that is drunk but not excreted dilutes the plasma sodium.
NDI: the hormone itself will not help because the kidney is resistant to it, so treatment acts on the kidney indirectly. Sodium intake is restricted and a thiazide is used. A thiazide is a diuretic, yet it reduces urine volume in NDI by causing mild sodium and volume depletion. That depletion increases water reabsorption in the proximal tubule, so less water reaches the collecting duct. A collecting duct that cannot respond cannot rescue water, so reducing what arrives there reduces the loss. Amiloride is added in lithium-induced disease; it blocks the channel through which lithium enters the principal cells. An NSAID such as indomethacin can be used as well.
DDI: the kidney responds normally, so treatment is directed at the excessive drinking rather than the kidney. Giving desmopressin would add water retention and the risk of hyponatremia described above. The underlying psychiatric condition is treated.
With three different failures and three different treatments, how do the pieces fit together into one view of diabetes insipidus?