
What is hypothalamic diabetes insipidus, and why does it appear late?
Hypothalamic (central) diabetes insipidus (HDI) is diabetes insipidus caused by too little secretion of antidiuretic hormone (ADH, also called arginine vasopressin, AVP). The hormone’s route is one line: the neuron cell bodies sit in the hypothalamus, their long axons run down the pituitary stalk, and their endings in the posterior pituitary release the hormone. HDI is a break anywhere on that line.
ADH lets the kidney concentrate urine. When too little of it is secreted, the kidney cannot concentrate urine, so hypotonic polyuria develops: the patient passes large volumes of dilute urine, and also wakes at night to pass it (nocturia).
Why is the disease not seen at the first sign of damage? The magnocellular neurons that produce AVP are numerous, and many of them share the work, so the system has a large spare capacity. The disease therefore appears only after most of them are lost: more than 80% of the hypothalamic AVP neurons must be destroyed before diabetes insipidus becomes manifest.
Thirst stays intact in most cases. Patients drink enough to replace the water they lose, so plasma osmolality stays normal. For the same reason the disorder is usually found through the polyuria rather than through a raised plasma sodium.
HDI is generally very rare, with a prevalence on the order of 4 in 100,000 of the population. So where is it met most often?
Why is it common after pituitary surgery?
The commonest way to hit the AVP pathway is to operate beside it. The posterior pituitary and the stalk are handled during pituitary surgery, and the posterior pituitary controls water balance, so patients are vulnerable to water and sodium disturbance early after the operation. HDI is fairly common among patients undergoing neurosurgery for pituitary tumours: it occurs in 18-30% of these operations, because the surgery can injure the stalk or its endings.
How long it lasts depends on the extent of the injury. In most cases the natural history is spontaneous resolution over 2-5 days after surgery. In about 1-8% HDI remains permanent. The more neurons are lost, the more likely the deficit is to be permanent.
After surgery, the plasma sodium is a signal. Sodium rises when the water lost in the urine is not matched by water drunk. A plasma sodium above 145 mmol/l after neurosurgery carries a significant risk of HDI, and it has a specificity above 98% for the diagnosis of post-operative HDI.
Some patients do not simply recover or stay ill. What happens when they pass through stages?
What is the triple-phase course?
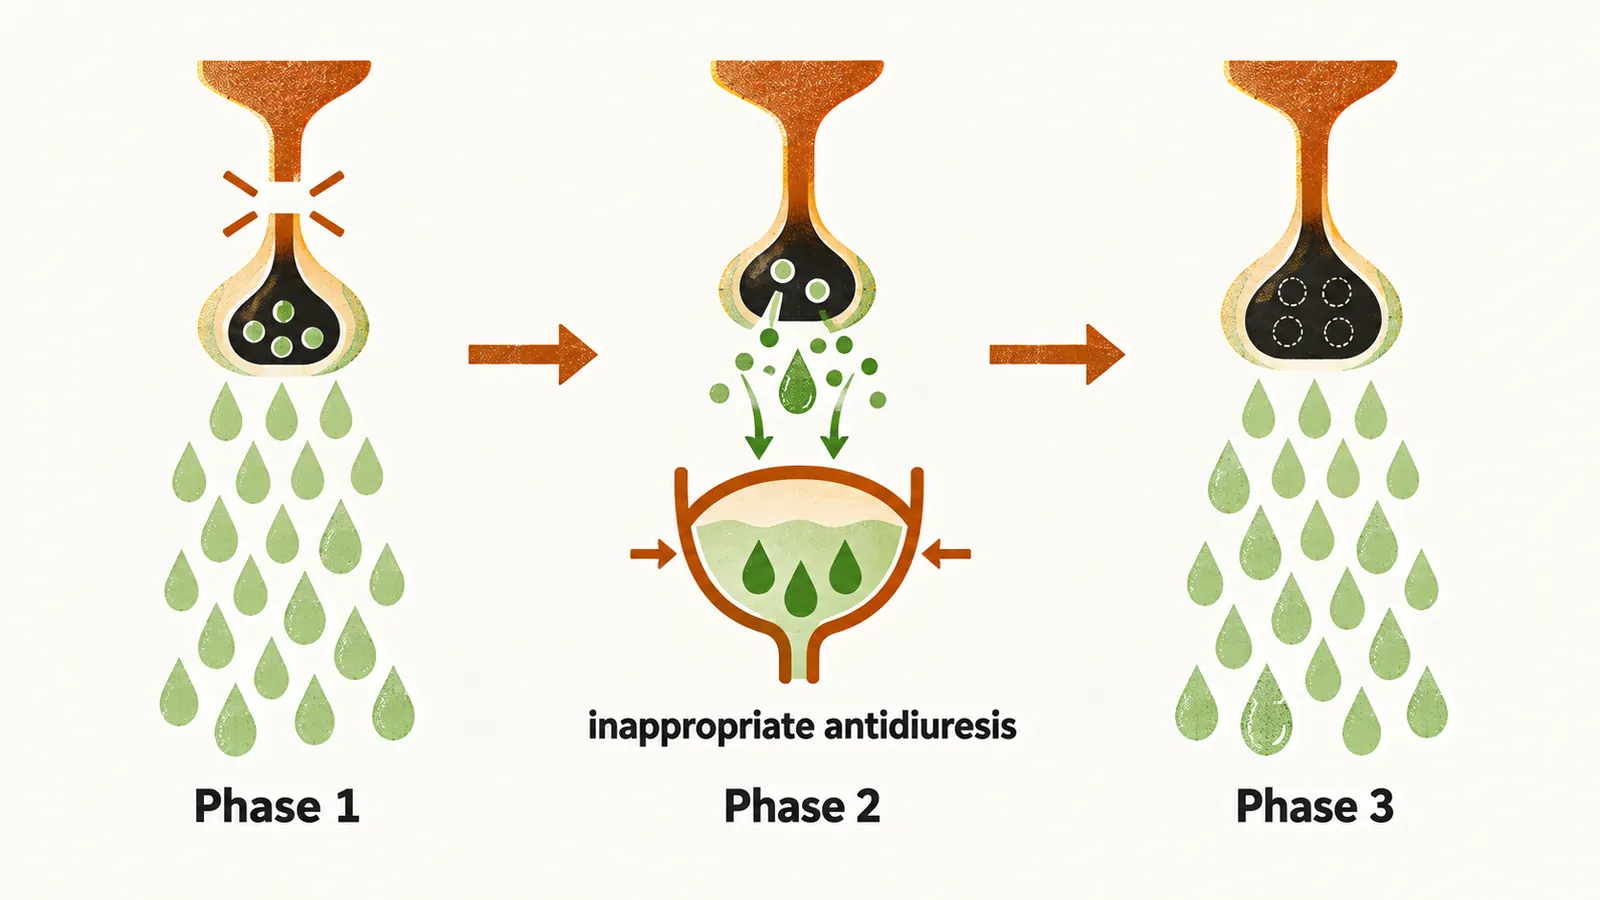
Permanent post-operative HDI often follows a stereotyped sequence called triple-phase HDI. The stages arise because one injury runs through three steps: the connection is interrupted, the damaged endings leak their stored hormone, and finally the neurons are lost.
- Phase 1: polyuria and hypotonic urine for 4-8 days after surgery, with trace amounts of AVP in plasma. The stalk is cut or the connection to the posterior pituitary is interrupted, so the cell bodies cannot release AVP on demand.
- Phase 2: the damaged magnocellular neurons release the AVP they had stored, without normal feedback control. The hormone leaks from damaged endings and is not governed by plasma osmolality, so the kidney retains water and plasma sodium can fall, a picture of inappropriate antidiuresis.
- Phase 3: permanent HDI. Once the stored hormone is used up, nothing replaces it if most AVP neurons are lost, in line with the more than 80% needed for the disease to show.
Surgery is the commonest setting of HDI, but not the only one. What else injures the same pathway?
What else injures the pathway?
Surgery is only one way to injure it. Pituitary masses rarely cause DI by themselves. When they do, the most common pathologies are craniopharyngiomas (tumours of the sellar region, around the pituitary), hypophysitis and granulomas. These sit next to the stalk and hypothalamus, or inflame them, so they can interrupt the same route.
Some cases have no identified cause; these are called idiopathic DI. Idiopathic DI used to be diagnosed more often. With more sophisticated imaging and greater awareness of autoimmune conditions affecting the CNS, especially the hypothalamus and pituitary, most idiopathic cases are now known to have been autoimmune.
Autoimmune DI is characterised by:
- young age of onset;
- circulating autoantibodies against AVP-secreting cells, a proposed link to the loss of the neurons that make the hormone, which is the same loss as before;
- a thickened pituitary stalk on T1-weighted MRI, which shows that the stalk, the route of the neurons, is involved.
Patients with autoimmune DI more commonly have autoimmune conditions of other organs: in about 30% of autoimmune DI cases there is also autoimmune thyroid disease.
And after head injury?
Injury without a surgeon follows the same logic. Diabetes insipidus occurs in 20% of cases of traumatic brain injury, and in nearly all of these the DI is transient. When it is permanent, the course is a triple-phase response similar to permanent DI following surgery, which fits the idea that both are injury to the same pathway.
In all of these forms the hormone is lost. What if the hormone is made normally and the kidney ignores it, or the patient simply drinks too much?