
What else can go wrong besides damaged ADH cells?
Hypothalamic diabetes insipidus comes from damage to the cells that make ADH. Nephrogenic and dipsogenic diabetes insipidus are the two forms that do not. ADH, also called arginine vasopressin (AVP), is present or can be released normally, and the urine is still dilute. Both forms produce hypotonic polyuria, a large volume of dilute urine, but they get there differently:
- In nephrogenic DI the hormone is present and the kidney fails to respond.
- In dipsogenic DI the kidney responds, and the drinking is excessive.
What does resistance to ADH mean?
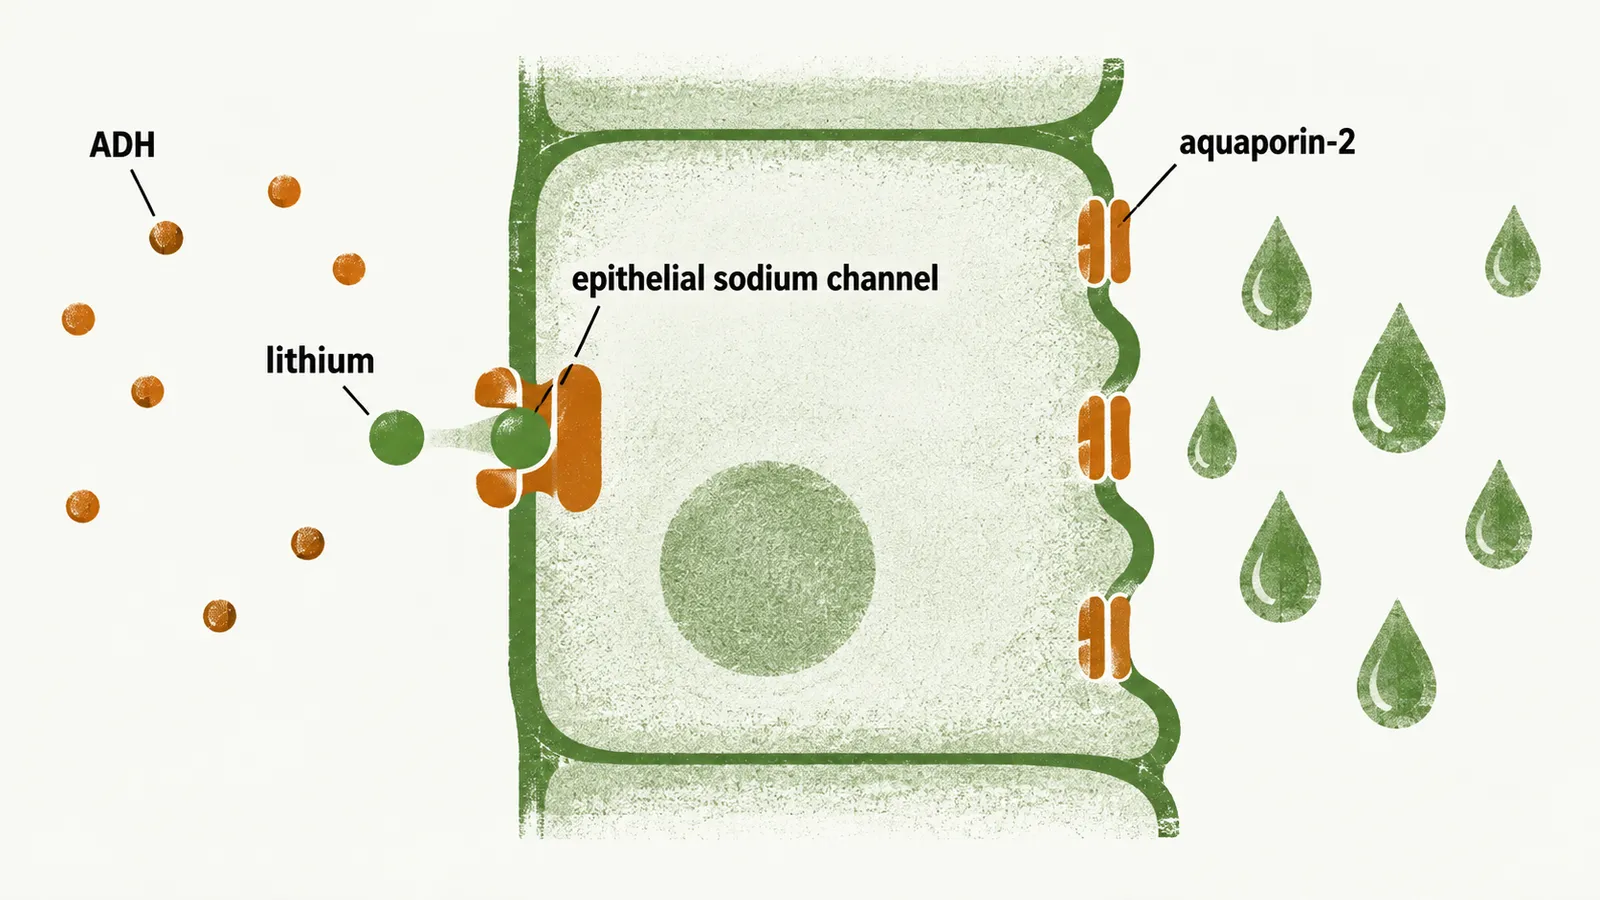
Concentrating urine takes two things: the hormone must arrive, and the collecting duct must respond to it. In nephrogenic DI (NDI), production and secretion of AVP are normal. The fault lies in the kidney’s response: renal resistance to AVP leads to hypotonic polyuria. The step that fails is the one in which ADH opens aquaporin-2, the water channel of the principal cells, so the urine stays dilute although the hormone is there.
Why does lithium cause it?
The most common cause of NDI is lithium use. Lithium produces NDI in about 30% of patients who take it.
The route begins at a door meant for sodium. Lithium enters the collecting duct principal cells through the same epithelial sodium channel that amiloride blocks. The channel lets lithium through more readily than it lets sodium through. Inside the cell, lithium is thought to reduce the expression of aquaporin-2. With fewer water channels, the collecting duct stays impermeable to water even when ADH is present. That is why this form of NDI does not answer to the hormone.
What happens to a patient with lithium NDI over time?
Lithium-induced NDI occurs in two forms: without interstitial damage and with interstitial damage. Lithium is able to cause interstitial kidney injury. In most cases lithium-induced NDI resolves only after the drug is stopped.
Patients with lithium-induced NDI are also more vulnerable to hypernatremia than patients with hypothalamic DI (HDI). Hypernatremia appears when the water lost in the urine is not replaced. The reason for this greater vulnerability is still unknown.
Dipsogenic DI: what if the kidney is fine and the problem is drinking?
Nephrogenic DI fails at the kidney’s response. Dipsogenic DI (DDI) fails at neither the hormone nor the kidney. It differs from the other forms because the primary problem is the amount drunk, so the kidney is not the cause.
Thirst is regulated in parallel with ADH, at a similar threshold. Anything that exaggerates the thirst response, or lowers the threshold at which thirst is triggered, can therefore produce DDI through excessive fluid intake: the person drinks at a plasma osmolality at which a healthy person would not.
How does drinking produce dilute urine?
The link between drinking and dilute urine runs through the osmoreceptors. They are carried by the magnocellular cells of the paraventricular nucleus (PVN) and the supraoptic nucleus (SON), which respond to plasma tonicity. When plasma osmolality falls below about 285 mosmol/kg, AVP release is suppressed.
Drinking a large amount of fluid can push osmolality below that threshold. Then AVP secretion falls, and a large volume of hypo-osmolar urine is produced. The kidney is not at fault: it is doing what it does when ADH is low.
Who gets dipsogenic DI?
A significant proportion of DDI patients have a psychiatric condition. Up to 20% of patients with chronic schizophrenia have DDI.
Same urine, different routes
All three forms of DI produce dilute polyuria by different routes: too little ADH, resistance to ADH, or too much drinking. At the bedside the picture is alike, so telling the forms apart depends on history and on tests that probe the ADH system directly. Which history and which tests separate the three?