What is left to decide once hyperglycemia is confirmed?
Confirming hyperglycemia is the first half of diagnosis. The second half is classification: deciding which category of diabetes the patient has. The same glucose value can come from different failures, so the result alone does not say which one. The category matters because it decides treatment. The categories overlap, and in some patients the type is unclear at first presentation and becomes obvious only as the disease evolves. Type 2 starts slowly, with insulin resistance compensated at first, and some adult type 1 also starts slowly, so early on the picture can be unclear.
Why does the category matter, and what are the categories?
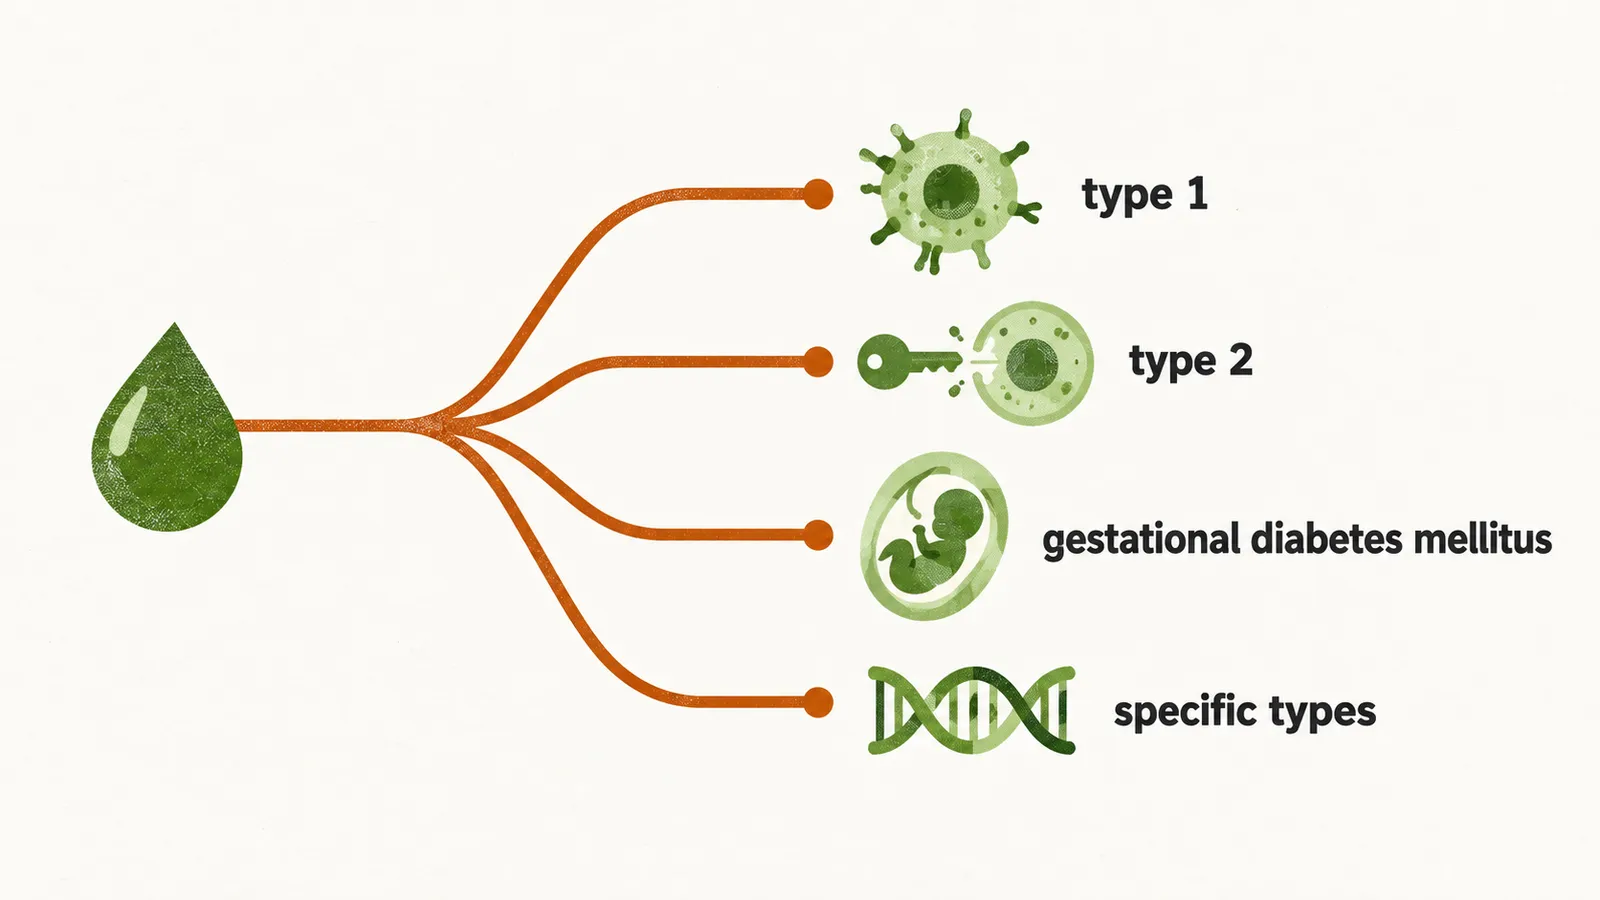
The ADA divides diabetes into four clinical categories: type 1, type 2, gestational diabetes mellitus (GDM) and specific types from other causes. The categories differ in the underlying cause of the hyperglycemia, that is, in which step of insulin production or action fails. Insulin is made by the β-cells, so to see what separates the categories, start with what fails in each.
What goes wrong in type 1?
Type 1 diabetes is immune-mediated destruction of the pancreatic β-cells. Autoimmune, T-cell-mediated destruction of the β-cells is the main process. When they are gone, no insulin is made, so type 1 usually leads to absolute insulin deficiency. People with type 1 therefore need insulin from outside the body to survive. Type 1 accounts for 5-10% of all diabetes.
What goes wrong in type 2?
Type 2 diabetes is non-autoimmune. It is a progressive loss of adequate β-cell insulin secretion, and it frequently occurs against a background of insulin resistance. The tissues respond poorly to insulin first and the β-cells compensate by secreting more. The loss of secretion shows when they can no longer keep up. Type 2 accounts for 90-95% of all diabetes.
Type 1 and type 2 are the two common categories, so how are they told apart? First, the other two.
What are gestational diabetes and the specific types?
GDM is diabetes first recognized in the second or third trimester of pregnancy, in someone who did not clearly have diabetes before pregnancy. Pregnancy changes how the body handles glucose, which is why diabetes can first appear then.
The specific types from other causes are other routes to the same raised glucose:
- monogenic diabetes syndromes, where a single faulty gene disturbs β-cell function;
- diseases of the exocrine pancreas, which can damage the pancreatic tissue that holds the islets, so insulin production can fail;
- drug- or chemical-induced diabetes, since some drugs and chemicals can raise glucose or impair insulin action.
That leaves two large groups to separate in practice.
Can age and weight tell type 1 from type 2?
Type 1 and type 2 are both heterogeneous: more than one pathway leads to each, so their features overlap. Both occur at every age. Type 1 can develop at any age, and type 2 is increasingly seen in children, adolescents and younger adults alongside obesity and inactivity. The old rule “type 1 of children, type 2 of adults” is therefore not reliable.
Some features most support type 1, because they fit an abrupt, near-total loss of insulin:
- younger age at diagnosis (under 35 years), since the immune destruction is often rapid in the young;
- lower BMI (under 25 kg/m²), since people with type 1 are generally not obese, whereas type 2 usually comes with excess body fat that promotes insulin resistance;
- unintentional weight loss, which reflects insulin lack;
- ketoacidosis, which type 1 can present with as its first manifestation;
- plasma glucose above 360 mg/dl (20 mmol/L) at presentation.
Other features are classically linked to type 1 but weak on their own. Ketosis without acidosis does not decide the type. Osmotic symptoms follow from the glucose level itself, so they do not say which type. A family history of diabetes is common in both types, since type 2 is familial too. A personal history of autoimmune disease is weak alone, but type 1 is associated with other autoimmune diseases, and that is why it is used as a prompt.
So which features should be checked?
Which features should prompt a look at type 1?
The AABBCC approach gathers the features worth checking:
- Age: younger age at diagnosis, as in the features just listed.
- Autoimmunity: personal or family history of autoimmune disease or polyglandular autoimmune syndromes.
- Body habitus: BMI under 25 kg/m².
- Background: family history of type 1 diabetes.
- Control: failure to reach glycemic goals on non-insulin therapy.
- Co-morbidities, such as treatment with immune checkpoint inhibitors for cancer, which can cause an acute autoimmune type 1 diabetes.
Features suggest the diagnosis, and tests can help.
What do islet antibodies and C-peptide add?
Islet autoantibodies support the diagnosis of type 1 diabetes. They are markers of the autoimmune process against the β-cells. GAD (glutamic acid decarboxylase) antibody is the first to measure. IA-2 (islet antigen 2) and ZnT8 (zinc transporter 8) antibodies are measured if GAD is negative. In someone not yet treated with insulin, antibodies against insulin can also help.
The antibodies mark the process but are not the process itself, since T-cell-mediated β-cell injury is the main pathologic process. So the absence of islet antibodies does not exclude type 1: 5-10% of people with type 1 diabetes have no islet antibodies.
C-peptide reflects how much insulin the pancreas still makes. It is useful when the question is whether insulin therapy can be reduced or stopped.
No test is perfect, so how often is the type wrong at first?
How often is the type wrong at first?
Misclassification is common. About 40% of adults with new type 1 diabetes are first diagnosed as having type 2. Adults are not the age group expected for type 1, and adult type 1 can come on slowly, with a slower course, which can help explain this. The distinction matters because it changes whether insulin is needed from the start. A patient who does not fit the expected picture deserves a second look, and sometimes the explanation is a single-gene defect.
When is diabetes caused by a single gene?
Monogenic diabetes is caused by a mutation in a single gene. Unlike the multi-factor type 1 and type 2, a single gene alters β-cell insulin secretion in response to glucose. It is rare, present in under 5% of people with diabetes. Recognizing it changes treatment, because treatment follows the gene.
Neonatal diabetes. Diabetes diagnosed within the first 6 months of life should prompt genetic testing for neonatal diabetes. Neonatal diabetes is associated with mutations in the KATP-channel genes or the insulin gene. The β-cell KATP channel controls insulin release, coupling the β-cell’s glucose sensing to it. In 30-50% of cases caused by mutations in this channel, high-dose oral sulfonylureas work instead of insulin. Sulfonylureas stimulate insulin release by closing the channel, which is why some of these cases can respond to them.
MODY. MODY (maturity-onset diabetes of the young) is a group of monogenic, non-syndromic forms. It is inherited in an autosomal dominant pattern: a single heterozygous mutation can be passed on, so the diabetes runs through generations. MODY is suggested by:
- diabetes without the typical features of type 1 or type 2, which is why it is mistaken for either;
- a family history of diabetes across successive generations;
- stable, mild fasting hyperglycemia.
The most common MODY forms differ in treatment, because different genes affect different steps of insulin secretion. HNF1A and HNF4A MODY are sensitive to sulfonylureas: the β-cell dysfunction is progressive, but the β-cells still respond when sulfonylureas bind their receptors. GCK MODY causes stable, non-progressive fasting hyperglycemia. GCK is an enzyme that lets the β-cells sense glucose, and the mutation resets the glucose threshold for insulin secretion upward, so fasting glucose is mildly and stably higher. With mild, non-progressive hyperglycemia and a low complication risk, GCK MODY usually needs no treatment.
What changes in pregnancy?
Gestational diabetes is diagnosed with thresholds of its own, because pregnancy changes what counts as an abnormal glucose result. What glucose values count as abnormal in pregnancy?