Why does diabetes need a laboratory definition?
Blood glucose is not one fixed number. It moves with meals, stress and illness, and a single sample cannot show what the average has been. So the ADA criteria for diagnosing diabetes mellitus are built on a set of laboratory tests, not on one value.
Four tests are used. Three measure plasma glucose at a moment: fasting plasma glucose (FPG), random plasma glucose (RPG), and the plasma glucose 2 hours after an oral glucose load, the oral glucose tolerance test (OGTT). The fourth, HbA1c, measures glucose bound to hemoglobin.
Each test looks at a different aspect of glucose metabolism, so each has its own threshold and the tests are not interchangeable. Values above normal but below the diabetes threshold define prediabetes, and each test has its own band for it.
What does each plasma glucose test show?
Fasting plasma glucose is measured on venous plasma after at least 8 hours without food. Because no meal is adding glucose, it reflects the glucose level in the fasting state. A value of 126 mg/dl (7.0 mmol/L) or more is diagnostic of diabetes. A normal FPG is below 100 mg/dl (5.6 mmol/L), and 100-125 mg/dl (5.6-6.9 mmol/L) defines prediabetes, also called impaired fasting glucose (IFG).
Random plasma glucose is measured at any time of day, without regard to the last meal. A random sample cannot be separated from the effect of a recent meal, so it is used on its own when the picture is already clear. A value of 200 mg/dl (11.1 mmol/L) or more is diagnostic of diabetes when it comes with classic hyperglycemic symptoms, which arise because glucose spills into the urine, or with a hyperglycemic crisis. In someone without those symptoms or a crisis, an FPG or OGTT value is used instead.
The OGTT is a test of how well glucose is handled after a load. The 2-hour plasma glucose is measured after the person drinks a solution equivalent to 75 grams of glucose. Because it asks the body to clear a load, it can show a problem that a fasting value does not. Two preparations make the result valid. The person must have taken at least 150 grams of carbohydrate in the preceding 3 days, because cutting carbohydrate beforehand can falsely raise the post-load glucose. The person must also be tested after a night of fasting, so that the starting value is the baseline.
The 2-hour result is read in three bands:
- below 140 mg/dl (7.8 mmol/L): normal;
- 140-199 mg/dl (7.8-11.0 mmol/L): impaired glucose tolerance (IGT), which is prediabetes;
- 200 mg/dl (11.1 mmol/L) or more: diabetes mellitus.
These three tests all sample glucose at one moment. What does the fourth, which looks at an average, show?
What does HbA1c show, and why does it need no fasting?
As blood circulates, glucose slowly attaches to the hemoglobin inside red cells. The amount attached builds up over the lifespan of the red cell, so HbA1c is a chronic measure: it reflects the average glucose of the preceding 2-3 months. Because it is an average, one meal does not change it, and it needs no fasting.
An HbA1c of 6.5% or more is diagnostic. A value of 5.7 to 6.4% marks very high risk of progression to diabetes mellitus, which is the prediabetes band for this test.
Because the tests look through different windows, they do not always agree.
Why can the tests disagree, and what is done about it?
The tests measure different aspects of glucose metabolism, so they detect slightly different groups of people, and they can disagree in the same patient. That is why the choice of test matters, and why so does the number of abnormal results needed.
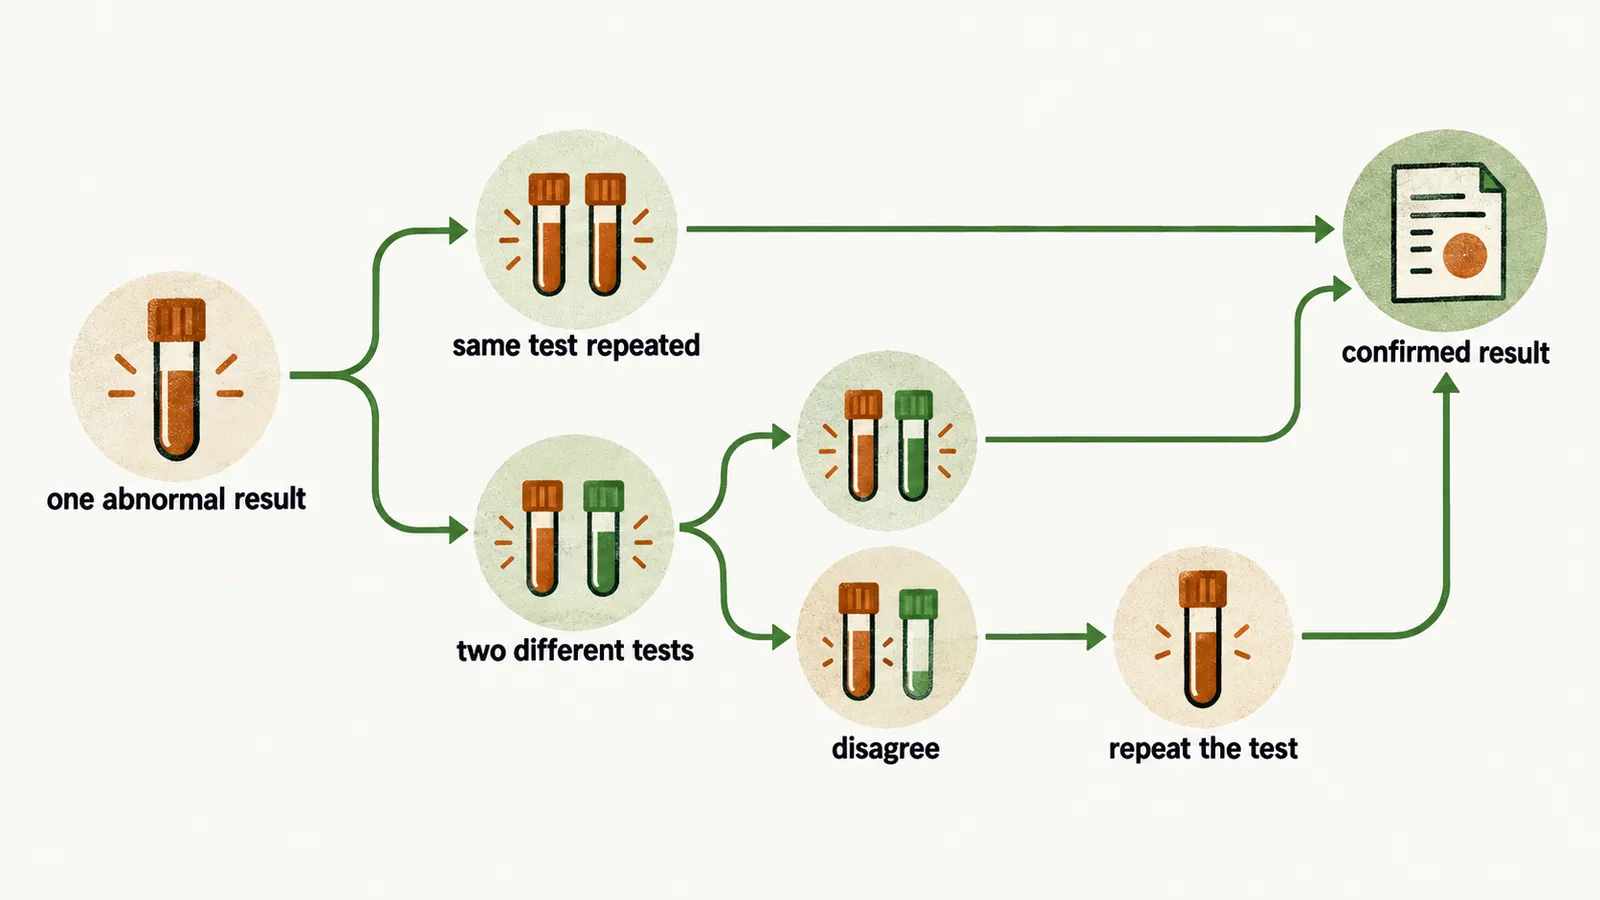
A single abnormal result is not enough on its own, unless there is unequivocal hyperglycemia: classic symptoms of hyperglycemia or a hyperglycemic crisis, together with a random plasma glucose of 200 mg/dl or more. A sample can give an abnormal value for reasons unrelated to diabetes, for example a recent meal, stress, an illness or the handling of the sample, so otherwise the diagnosis is confirmed by two abnormal results.
The two results can be two different tests on the same sample, for example FPG and HbA1c drawn together. Or they can be the same test repeated at a second time point. If two different tests disagree, the test with the abnormal value is repeated, and the diagnosis follows the confirmed result.
The averaging that makes HbA1c useful also makes it fragile. When can its number mislead?
When is HbA1c misleading?
HbA1c depends on how long red blood cells survive and on the hemoglobin they carry. Anything that alters red-cell turnover or hemoglobin can therefore make the value misleading, shifting it without a matching change in glucose. In these situations the plasma glucose criteria should be used instead of HbA1c to diagnose diabetes:
- some hemoglobin variants, which interfere with the assay;
- pregnancy, in the second and third trimesters and postpartum (pregnancy has its own glucose thresholds, set for pregnancy outcomes);
- glucose-6-phosphate dehydrogenase (G6PD) deficiency;
- HIV infection;
- hemodialysis;
- recent blood loss or transfusion, or ongoing hemolysis;
- erythropoietin therapy.
Two further situations follow the same logic.
Two further settings concern the choice of test. HbA1c is not used to screen for cystic fibrosis-related diabetes because it is insensitive. After organ transplantation the OGTT is preferred for diagnosing post-transplantation diabetes.
Once the tests confirm hyperglycemia, what kind of diabetes does the patient have?