When is a girl’s puberty late, and what is it a sign of?
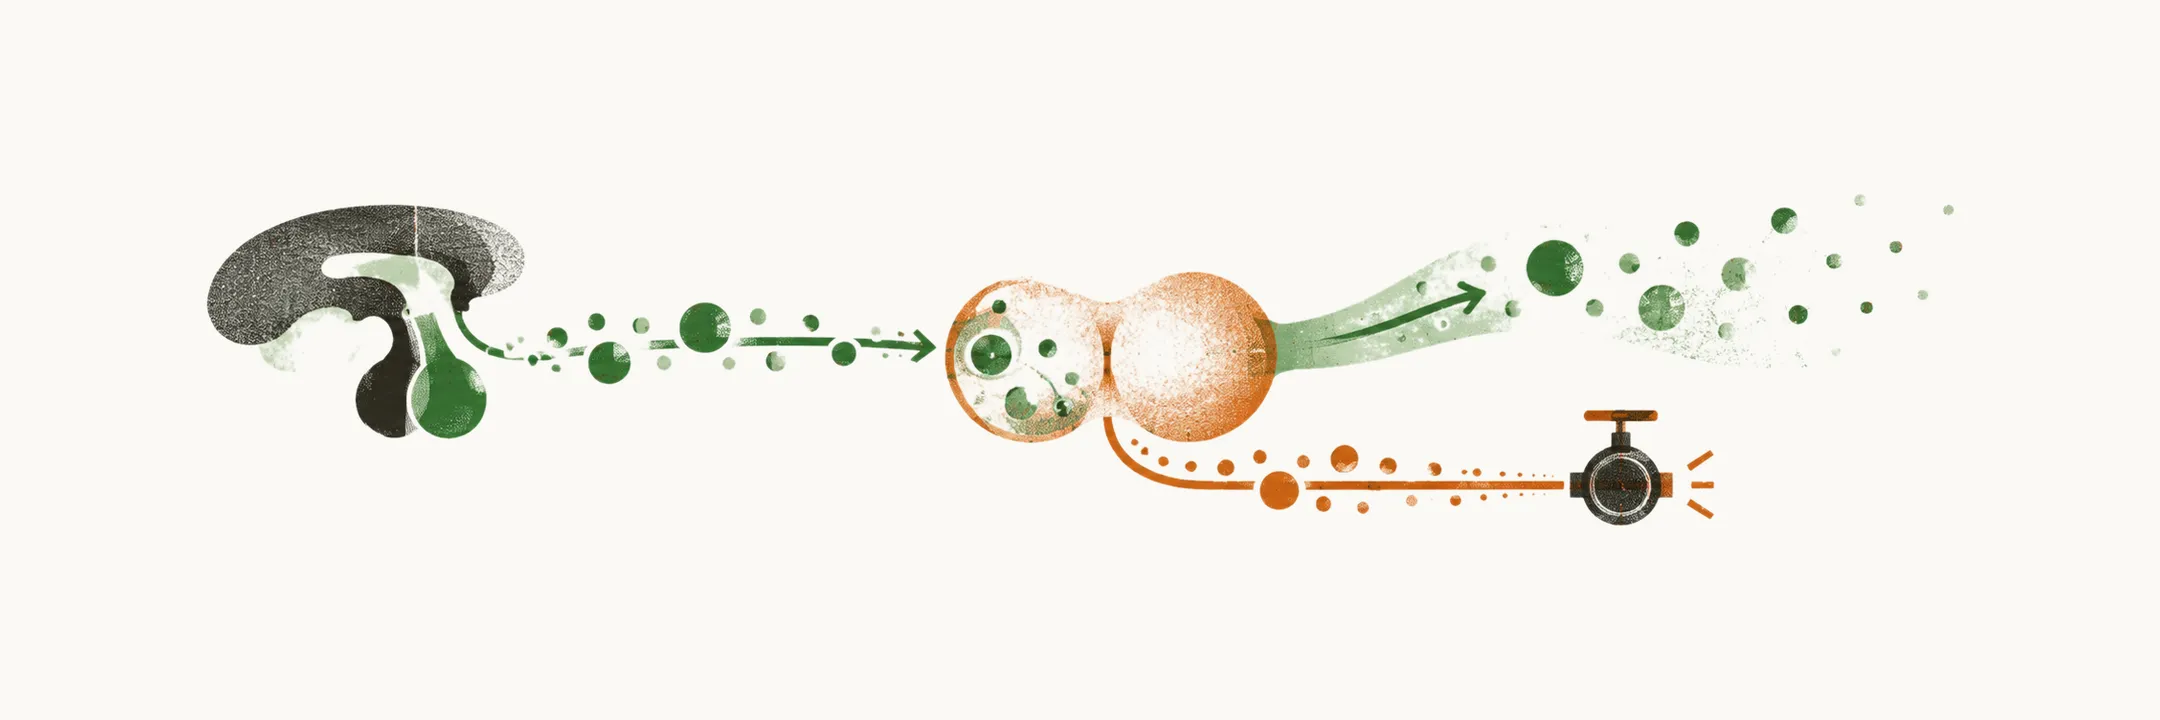
Puberty works as a relay. The hypothalamus releases GnRH, the pituitary answers with LH and FSH, the ovary answers with estrogen, and estrogen builds the breast and the lining of the uterus. Menstrual blood then needs an open uterus, cervix and vagina to leave. Late puberty is the visible sign that some link of this relay, or that exit, is not working.
Delayed puberty in girls is the absence of thelarche, the start of breast development, after age 13. Delayed menarche, the first menstruation, is the absence of menarche by age 15 or 16. Both terms describe timing, not a diagnosis. As the definitions note showed, these ages are statistical cut-offs, so they mark the point at which the clinician should look for a cause, not what the cause is. Breast development normally comes first and menarche follows about 3 years later, as described in Normal Physiology of Puberty in Girls.
The guideline recommends evaluation of girls with:
- absence of thelarche after age 13;
- absence of menarche after age 15 or 16;
- absence of menarche by age 14 plus hirsutism, meaning excess male-pattern hair growth;
- absence of menarche by age 14 plus a history or examination suggestive of an eating disorder or excessive exercise, which are associated with low body fat and low energy availability; a proposed route is that reduced intake lowers leptin, leading to less gonadotropin output, so the axis is not activated;
- absence of menarche by age 14 plus an outflow abnormality, meaning an anatomical block to menstrual flow. If the passage is blocked, hormones can be normal and still no period appears.
The guideline also suggests starting the diagnostic procedure if there is no menarche 3 years after thelarche. Because menarche normally follows thelarche after about 3 years, a longer gap suggests the sequence is stalling even before the age cut-off.
Which causes are the commonest?
Knowing when to look, what is most often found? Three causes account for more than two thirds of girls presenting with delayed puberty or absent menarche:
- ovarian insufficiency, 42%;
- congenital absence of the uterus or vagina, 14%;
- constitutional delay of puberty, 10%.
One of the three is temporary and two are fixed. In constitutional delay a healthy child simply matures later than average, and it resolves with time. Ovarian insufficiency and the absent uterus or vagina are permanent.
How does the relay show where it has failed?
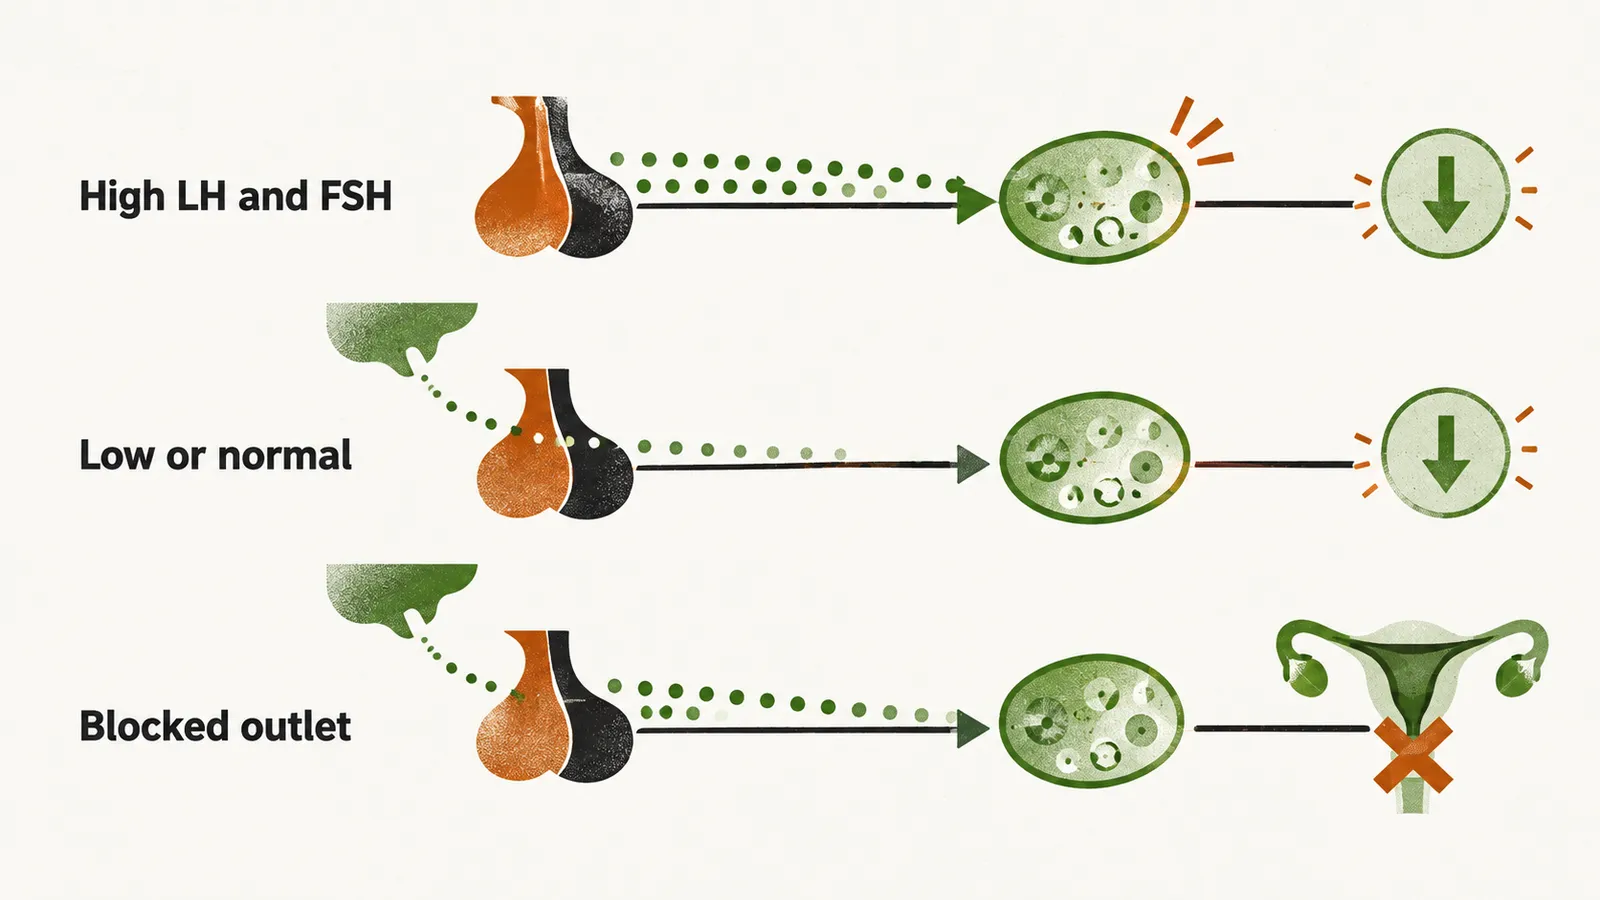
The remaining third separates by where the axis has failed. Hypogonadism means underactive gonads, the ovaries in a girl, and the three patterns differ in what the pituitary is doing and whether the gonads can respond. Estrogen feeds back to the brain, so the pituitary’s own output is the best clue. If the ovary has failed, the pituitary pushes harder. If the drive from above is missing, the ovary is never asked. If the chain works but menstruation is blocked, the hormones are normal and the problem lies downstream.
When the ovary fails
In hypergonadotropic hypogonadism the gonads fail, so the pituitary compensates and gonadotropins are high. Gonadotropins are LH and FSH, the pituitary hormones that command the gonads. Failing gonads mean low estrogen, and low estrogen removes the brake on GnRH, LH and FSH, so their secretion rises.
The best-known example is Turner syndrome, in which an X chromosome is partly or completely absent and the ovaries fail. The same picture can arise with a normal karyotype, in 46,XX or 46,XY gonadal dysgenesis.
If the ovary is not the problem, what is the pituitary doing?
When the drive from above is missing
In hypogonadotropic (or eugonadotropic) hypogonadism gonadotropins are low or normal because the fault is in the hypothalamus or pituitary. Deficient GnRH leads to reduced LH and FSH, so the ovary is not driven; a normal level can still be inappropriate when estrogen is low.
Its causes divide by whether correcting them restores the axis. In the reversible group, the axis is switched off by a condition outside it, and treating that condition brings it back. Constitutional delay is a late start of a normal axis, and systemic illness and eating disorders suppress the axis through low energy availability. The reversible causes, treated by correcting them, are:
- constitutional delay;
- systemic illness;
- eating disorders;
- primary hypothyroidism;
- congenital adrenal hyperplasia;
- Cushing syndrome;
- pseudopseudohypoparathyroidism;
- hyperprolactinemia.
In the irreversible group, the drive itself is missing or destroyed, so correcting nothing restores it and hormones have to be replaced. These causes are:
- congenital deficiency syndromes;
- isolated GnRH deficiency;
- forms of hypopituitarism;
- congenital CNS defects;
- acquired anatomical lesions.
Irreversible causes also include tumours near the hypothalamus and pituitary that can damage the drive: unclassified pituitary adenoma, craniopharyngioma and malignant tumour.
What if the drive works and the ovary answers, yet no period comes?
When the axis works but no period appears
In eugonadism the axis itself works, and the ovary makes estrogen, so breasts develop; what is missing is the menstruation, because it is blocked. The anatomic causes are Müllerian aplasia and outlet obstruction. The Müllerian ducts form the uterus, cervix and upper vagina, so Müllerian aplasia, the congenital absence of the uterus or vagina, leaves no menstrual outlet.
Outlet obstruction can come from a transverse vaginal septum, an imperforate hymen or cervical atresia. A transverse septum is a failure of canalisation where the Müllerian ducts meet the urogenital sinus, and an imperforate hymen is a failure of the hymen to perforate; menstrual blood then accumulates behind the block. Inappropriate feedback, intersex disorders, androgen insensitivity and 17-ketoreductase deficiency complete the eugonadism group.
Three patterns, then: which tests separate them?
How is the break located?
Evaluation begins with history and examination, which look for the broken link: features of Turner syndrome, signs of chronic illness or an eating disorder, and evidence of androgen excess. Bone age is obtained; it is skeletal maturity read from a radiograph.
Gonadotropin levels are the most useful initial test, because they show what the pituitary is doing in response to estrogen. High LH and FSH identify gonadal failure. Low or normal LH and FSH point to a hypothalamic-pituitary cause.
Hypogonadism in a girl raises the possibility of Turner syndrome, so karyotype, the analysis of the chromosomes, is checked early. Any Y-chromosome material found means the gonads have to be removed because of their tumour risk. Prolactin and thyroid function are measured, since they are reversible endocrine causes. Brain MRI looks for a hypothalamic-pituitary lesion when the cause appears central.
Once the cause is known, what is done about it?
How is puberty induced, and who needs it for life?
Treatment follows the cause. Constitutional delay of puberty resolves with time, because the axis is normal and starts late, so reassurance may be enough. When low body fat or an eating disorder is responsible, restoring weight can restart the axis on its own.
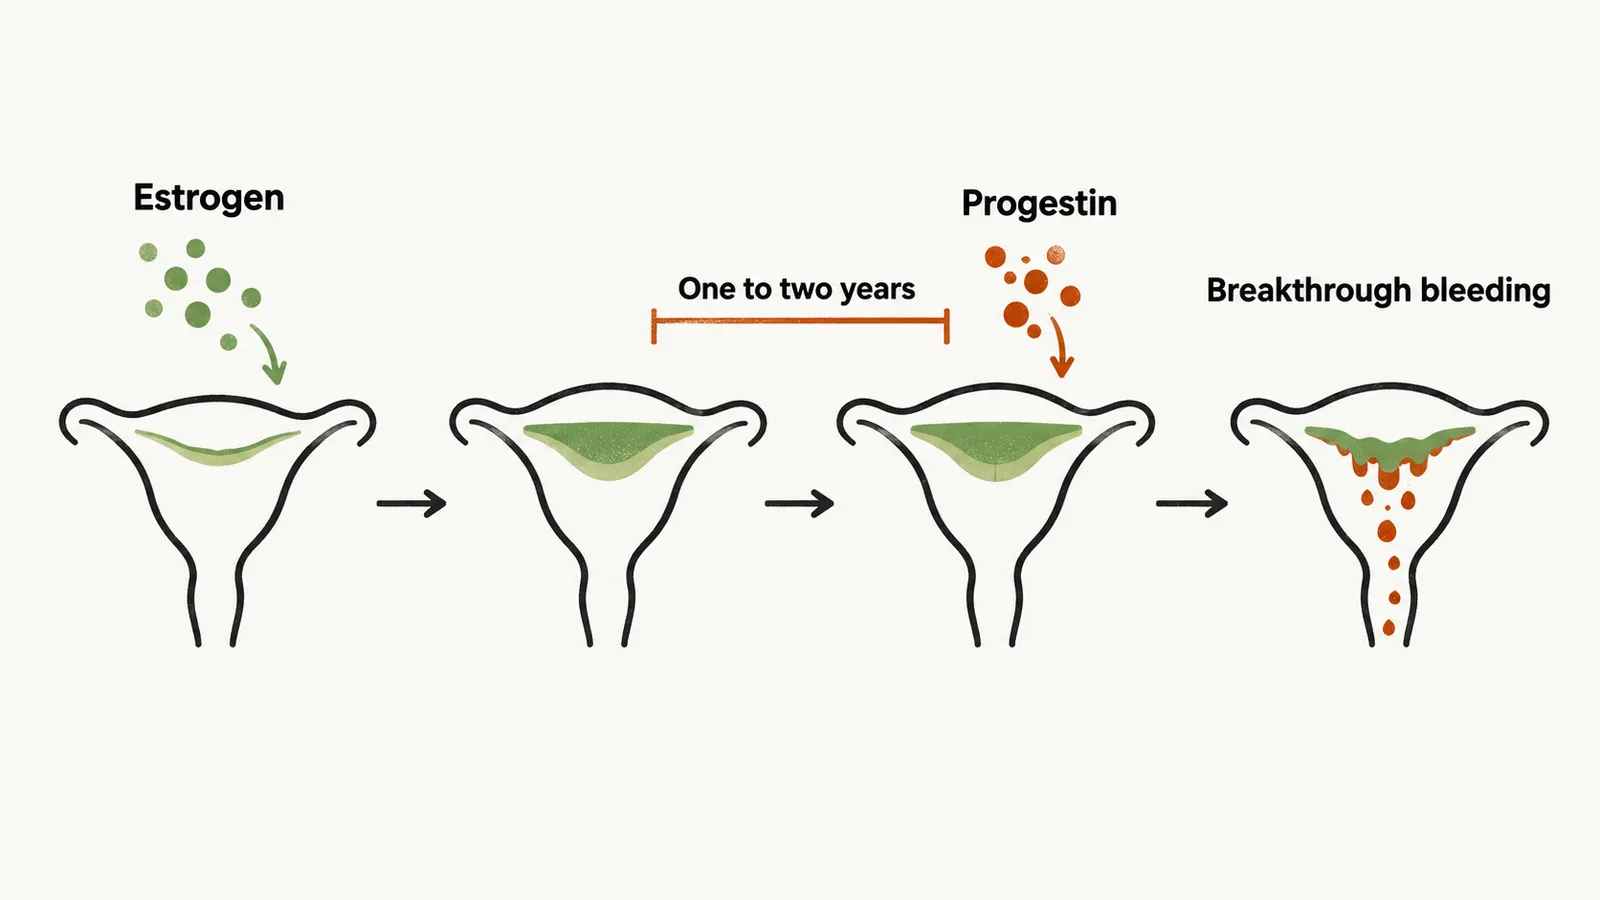
When the delay causes distress, or the deficiency is permanent, puberty is induced with estrogen, the hormone the ovary would have made. It is given gradually, with a low starting dose increased slowly to mimic the tempo of natural puberty. Estrogen alone stimulates the endometrium, the lining of the uterus, which grows without ever being shed. A progestin, a synthetic form of progesterone, is therefore added after one to two years, or once breakthrough bleeding appears, so that the endometrium is shed.
Girls with primary ovarian insufficiency or permanent gonadotropin deficiency do not recover, so they need long-term estrogen replacement rather than a short course.
Now that the determinants, the normal sequence and the early and late abnormal directions have all been laid out, how do they fit together, and which should a reader open first?