
What does precocious puberty mean, and what do its signs share?
Precocious puberty means secondary sexual traits appearing before the age cutoffs for normal pubertal timing: before age 6 in African-American girls and before age 7 in Caucasian girls. Many endocrinologists still evaluate a girl who shows secondary sexual traits before age 8. The estimated incidence is about 1 in 5,000 to 1 in 10,000 children, and prevalence in females is about 10 times that in males.
A girl’s puberty runs as a chain. The hypothalamus releases GnRH, the pituitary answers with the gonadotropins, LH and FSH, the two pituitary hormones that command the gonads, and the ovaries answer with estrogen. Estrogen builds the breast, enlarges the uterus and ovaries, speeds growth and matures the skeleton. So in precocious puberty all the signs come from one thing, an increase in sex steroids, and the real question is where the extra steroid comes from. The increase can derive from central disorders of the hypothalamus, disorders of the gonads, or disorders of the adrenal glands: these are the places where the chain can switch on early, or be bypassed by a source that makes steroid on its own. Precocious puberty is sex-steroid action arriving too early.
How is it classified, and what causes each type?
Which of these origins operates decides everything that follows. Precocious puberty is classified by the sequence of pubertal events into two main groups.
- Complete precocious puberty is the gonadotropin-dependent form. All stages of normal puberty appear before the age cutoff: thelarche (start of breast development), adrenarche (start of adrenal androgen production) and menarche (start of menstruation). The whole sequence appears because the whole chain is on.
- Incomplete precocious puberty is the gonadotropin-independent form. One stage appears on its own, as one source acts alone. It is sub-classified by which stage appears: isolated precocious thelarche, isolated precocious adrenarche or isolated precocious menarche.
A second distinction is by sex of the features. Isosexual precocity means features of the child’s own sex, such as feminization of a female. Heterosexual (contrasexual) precocity means features of the opposite sex, such as virilization of a female.
Together these give three groups of causes. In the first, the early axis drives a complete, isosexual picture; in the second, steroid comes from the ovary or adrenal without pituitary drive and feminizes; in the third, androgen from the adrenal or a tumour virilizes.
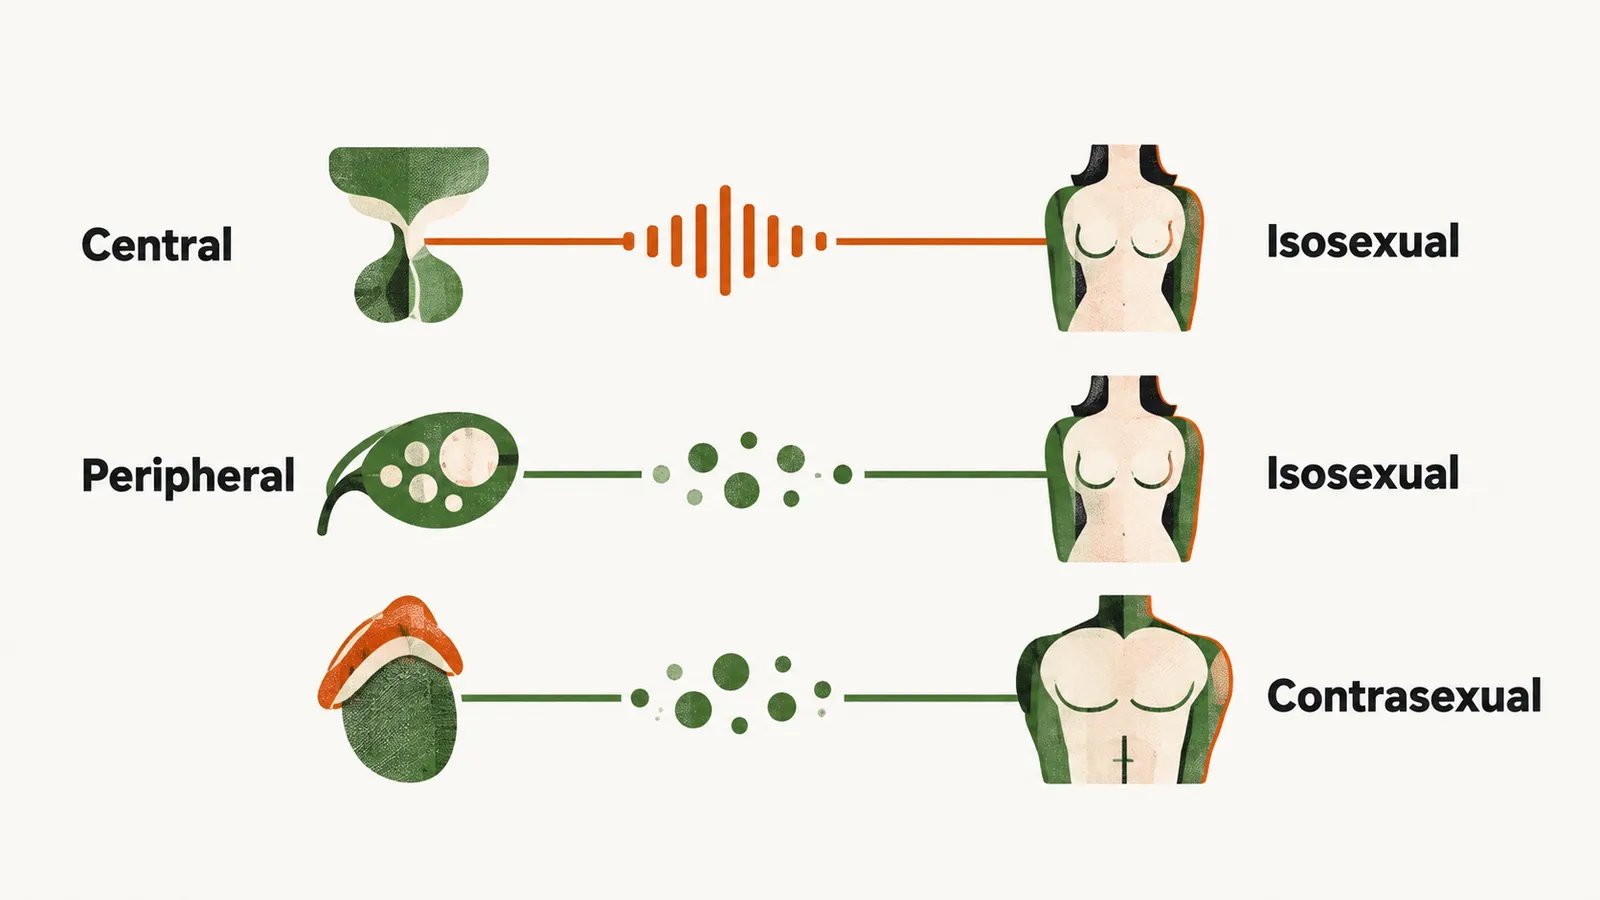
I. Complete isosexual precocity (gonadotropin dependent)
- idiopathic
- CNS lesions (hamartomas, craniopharyngioma, etc.)
- primary hypothyroidism
- post treatment for CAH
- genetic
II. Incomplete isosexual precocity (GnRH independent)
- isolated precocious thelarche
- isolated precocious menarche
- estrogen-secreting tumors (ovary/adrenals)
- ovarian cysts
- McCune-Albright syndrome
- Peutz-Jeghers syndrome
- iatrogenic
III. Contrasexual precocity (isolated virilization)
- isolated precocious adrenarche
- congenital adrenal hyperplasia
- androgen-secreting neoplasm
- iatrogenic
The gonadotropin-dependent form is central precocious puberty (CPP), and it accounts for 97.7% of cases. Gonadotropin-independent precocious puberty (GIPP) accounts for about 2.3%. The commoner form comes first.
Why does the axis switch on early in central precocious puberty?
Central precocious puberty is the first group of causes seen from the inside. Puberty normally begins when the hypothalamic GnRH pulse generator reactivates after a quiet childhood. In CPP this reactivation comes too early: the hypothalamic-pituitary-ovarian axis matures earlier, so the whole axis switches on prematurely rather than being driven from outside it.
Because the axis is simply running at its normal pubertal setting, its numbers look like those of an ordinary pubertal girl. Gonadotropin, GnRH and GnRH pulsatility are all in the normal range, similar to the post-pubertal level. GnRH pulsatility is the rhythmic pattern in which GnRH is released, and pulsatile GnRH is what normally drives pulsatile LH and FSH.
The most common cause of CPP is idiopathic: no lesion is found and the axis simply matures early. The early switch-on is itself the finding, not a hidden lesion, and some of these cases turn out to have a genetic cause, which appears below.
When a lesion is responsible, it usually sits in the CNS. The hypothalamus is where the switch sits, and a lesion there can upset the balance of excitatory and inhibitory inputs to the GnRH neurons; for acquired lesions the mechanisms are poorly established. The most common neoplasm in CPP is the hypothalamic hamartoma, a benign mass of the tuber cinereum, part of the hypothalamus. Proposed mechanisms are its anatomical connection to the anterior hypothalamus, autonomous GnRH-neuron activity within the lesion, trophic factors secreted by it, and mechanical pressure on the hypothalamus. Other CNS causes are trauma, hydrocephalus, congenital brain defects and post-infectious damage, and acquired insults like these can disrupt the regulation of GnRH release by poorly established mechanisms.
Some rare genetic conditions also cause CPP. The timing of the switch is held by an accelerator and a brake, and a gene change in either can move it earlier.
- The accelerator. Kisspeptin is the primary stimulatory signal of puberty: kisspeptin neurons push the GnRH neurons to fire. A gain-of-function mutation of KISS1 or its receptor therefore makes the axis switch on early.
- The brake. A loss-of-function mutation of MKRN3 has the same effect. MKRN3 is an E3 ubiquitin ligase, an enzyme that tags proteins for degradation. It is expressed in childhood and falls before puberty, and it inhibits the production of kisspeptin before puberty; its site of action is not fully understood. Losing MKRN3 removes a brake.
Not every cause is the pituitary being switched on. What happens when steroid rises without it?
How can sex steroids rise without the pituitary driving them?
In GIPP the steroid comes from a source that makes it on its own, so the pituitary is not the origin. Gonadotropin-independent precocious puberty accounts for about 2.3% of cases.
An estrogen-secreting tumour or an ovarian cyst makes estrogen on its own, and a high estradiol with a blunted LH and FSH response suggests such a source. In McCune-Albright syndrome, an activating GNAS mutation drives autonomous ovarian activation while gonadotropins stay at prepubertal levels or are suppressed. Peutz-Jeghers syndrome and iatrogenic causes also appear in the classification above.
Severe primary hypothyroidism can also lead to precocious puberty, because very high TSH, the pituitary hormone that drives the thyroid, cross-reacts with and activates FSH receptors on the ovary. TSH and FSH share the same alpha-subunit and bind related receptors, and in a reported case the picture was a GnRH-independent, FSH-dominated response. This cause is listed among the complete, gonadotropin-dependent causes, yet the mechanism acts on the ovary directly rather than through the pituitary’s own LH surge, so it behaves differently from the other causes on that list.
The link between the two kinds runs both ways: CAH appears among the peripheral causes, but after treatment for CAH the long-standing androgen excess may switch the central axis on, which is why it also appears in the first group.
How does a child present, and what can look like it but is not?
What the child shows follows from the steroids. Precocious puberty usually announces itself with breast development, because estrogen acts on breast tissue. Breast development may begin on one side before the other. Pubic and axillary hair may appear before, at about the same time as, or well after breast tissue, because the adrenal androgen rise is a separate process, not locked to breast timing.
The child often shows a growth spurt and advanced bone age, because estrogen speeds growth and also matures the skeleton, so bone age runs ahead of age. This growth acceleration is deceptive. The same sex steroids that speed growth also mature the growth plates, so without treatment the child may be tall for age but end up short as an adult.
Two benign variants resemble precocious puberty and must be separated from it.
- Premature thelarche is the isolated appearance of breast development, usually in girls younger than 3 years.
- Premature adrenarche is the appearance of pubic hair without other signs of puberty, usually before 7 to 8 years.
Both progress slowly or not at all, so the axis is not being pushed forward, and that is why they must be told apart from true precocious puberty.
Telling the types apart takes a few tests, each answering one question.
How is the diagnosis confirmed?
Evaluation starts from history and examination. The growth chart is reviewed against population norms, which shows whether growth has accelerated.
A radiograph of the left hand and wrist gives the bone age. Estrogen exposure matures the skeleton ahead of age, and the longer the process has run, the further ahead it is, so bone age is advanced by more than a year if the process has been running for a while.
An ultrasensitive basal LH is measured. In childhood LH is very low, so a pubertal level signals that the pituitary has been switched on, and the assay must be sensitive enough for low values. If LH stays low although clinical suspicion is high, a GnRH stimulation test settles whether the axis has truly switched on. A basal sample can miss a pituitary that is only starting to work, because LH release is uneven, so the test asks whether the pituitary now answers a GnRH stimulus like a pubertal one. A pubertal peak of LH after the stimulus confirms CPP, and a flat response points to a gonadotropin-independent cause.
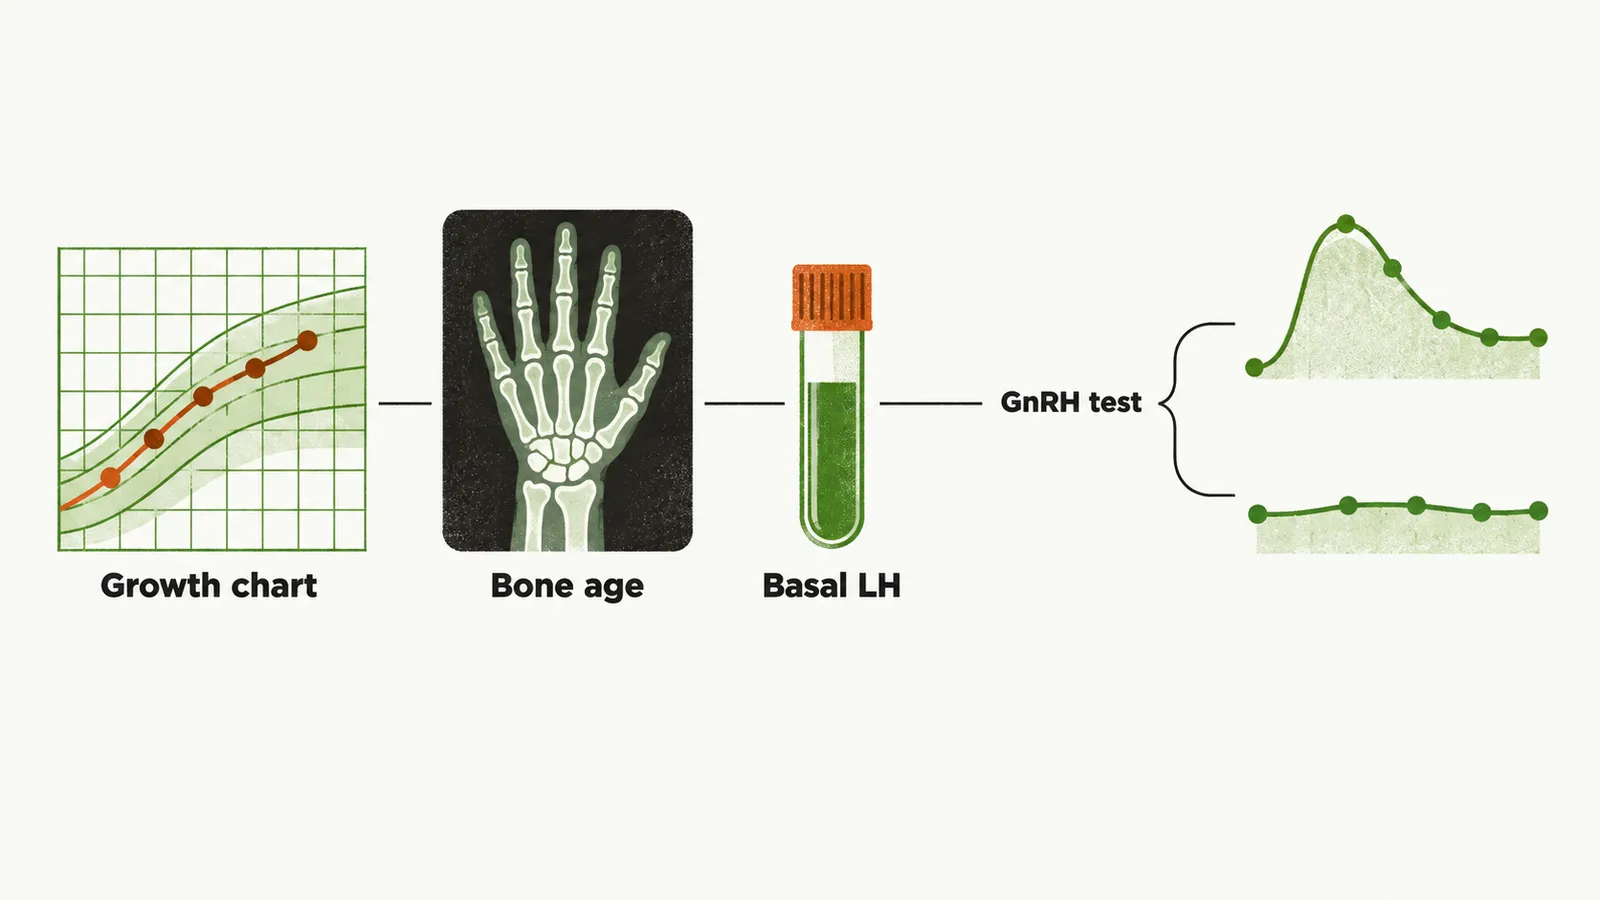
Pelvic ultrasound assesses ovarian and uterine size; estrogen enlarges both, so size shows how much estrogen has acted.
Brain MRI is used selectively, not routinely in every girl aged 6 to 8. It is indicated in girls younger than 6 years, in boys, and in any child with central symptoms such as headache or visual change. A lesion is the reason to image, so MRI is kept for children in whom a lesion is more likely, or in whom a mass could press on the hypothalamus. In boys, CPP is more likely to have a pathological source.
Once the origin is known, treatment is chosen to match.
How is the axis suppressed, and who is treated?
Treatment is directed at the cause, since the cause decides which step of the chain to act on.
For CPP, the treatment of choice is a GnRH agonist such as leuprolide. Normal GnRH is pulsatile and the pituitary responds to pulses. Given continuously, the agonist first overstimulates, then down-regulates the pituitary GnRH receptors, so gonadotropin secretion stops and gonadal hormones fall. This suppresses the reproductive axis and halts or slows pubertal progression. With estrogen removed, the skeleton stops maturing early, so the treatment delays fusion of the growth plates (epiphyseal closure) and adult height is preserved. Treatment is usually continued to the normal age of puberty, and the axis recovers afterwards, since the receptor changes reverse once the stimulus stops.
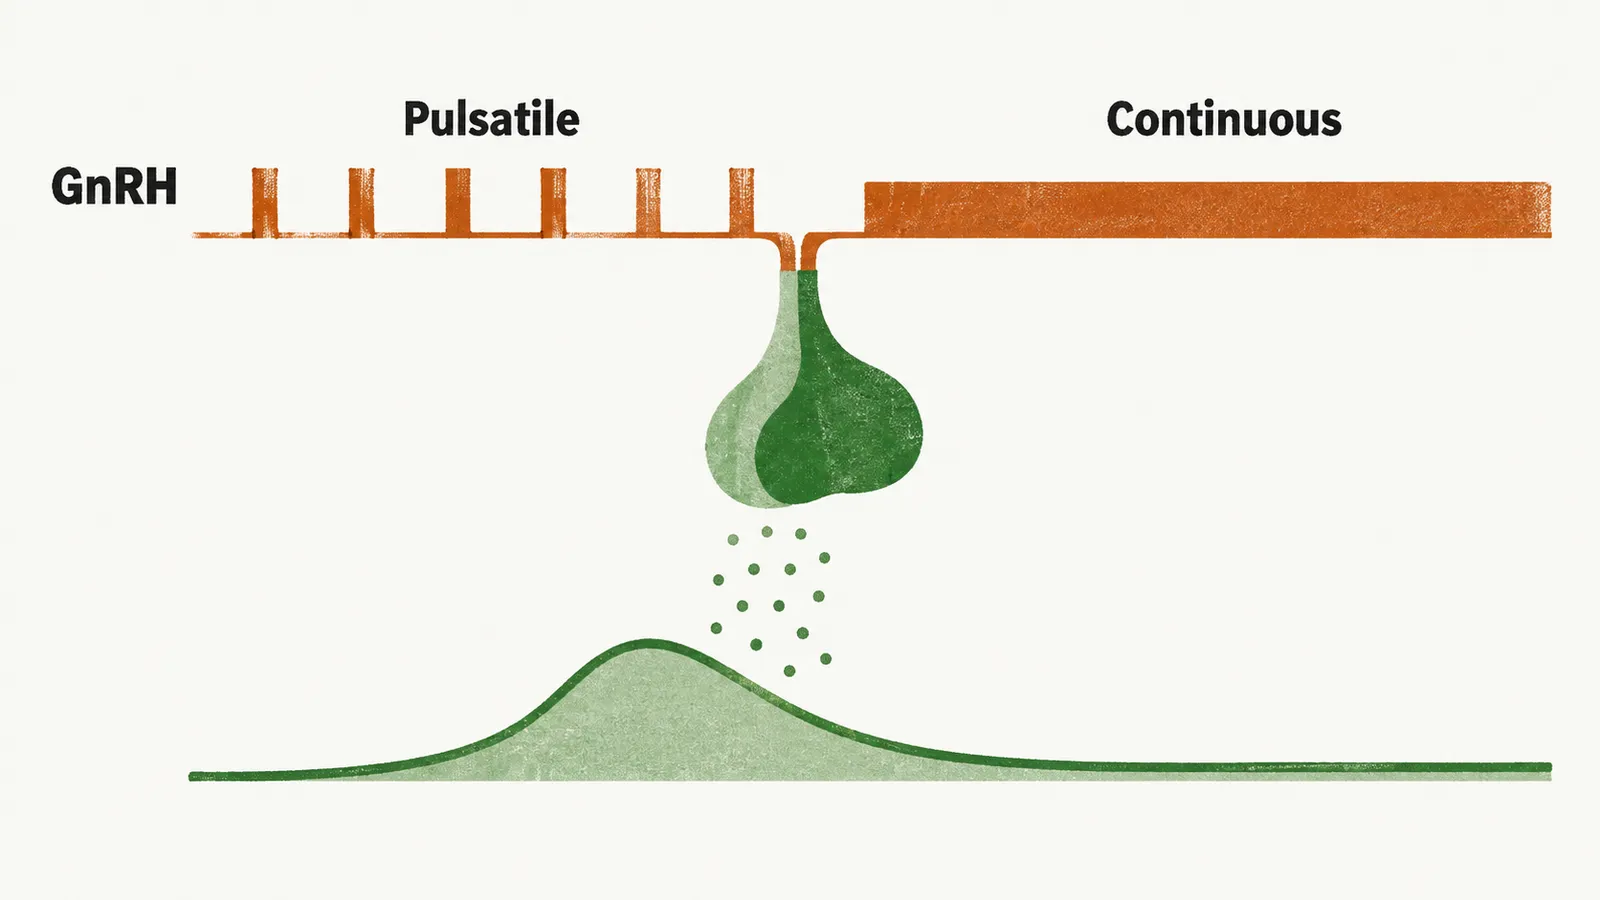
Not every child with CPP needs treatment. The aim is adult height, so a slowly progressive form that does not compromise adult height can be followed without treatment, because there is nothing for treatment to protect.
For GIPP the axis is not the problem, so GnRH agonists do not work: an agonist acts on the pituitary, and there is nothing there for it to suppress. The underlying source has to be treated instead: an estrogen-secreting tumour, an ovarian cyst, the autonomous ovarian estrogen production of McCune-Albright syndrome, or congenital adrenal hyperplasia.
Precocious puberty is sex-steroid action arriving too early. If puberty can arrive too soon, what keeps it from coming at all, and why?