
Diagnosing hypocalcemia takes two steps: confirm that the calcium is genuinely low, then identify the cause that produced it. The steps are linked, because the same low calcium means different things depending on whether the parathyroid glands are answering it.
The picture is this. Calcium in the blood travels in three parts: a free ionised fraction, a part bound to albumin, and a part bound to other anions. Only the ionised calcium is the fraction tissues respond to, and the parathyroid glands sense it. When it falls, the glands release PTH. So the PTH level is the glands’ answer to the calcium, and the diagnosis asks two questions: is the free calcium really low, and are the glands answering?
Is the calcium really low?
The first step is to confirm the result and to rule out an artefactually low calcium. The first question is whether the calcium is really low at all.
Why can total calcium mislead?
Before anything is corrected, the total has to be understood as the sum of its parts. About 40% of serum calcium is bound to albumin, and a further fraction is bound to other anions. The measured total counts all of these, and the ionised part is only one share of it. A low total is therefore not always a low ionised calcium.
This matters when albumin is low. Albumin carries a large share of the calcium, so in hypoalbuminemia the total falls with it, while the ionised calcium, the fraction that tissues respond to and the glands sense, may not be low. A low total calcium with hypoalbuminemia may not represent low ionised calcium, and the total can overstate the hypocalcemia.
How is the albumin error corrected, and when is it not enough?
Because albumin carries the calcium, there are two ways to get back to the free share. In hypoalbuminemia, measure the ionised calcium directly, or correct the total calcium for albumin:
corrected calcium = measured calcium + 0.8 × (4.0 − serum albumin)
An ionised calcium below about 1.17 mmol/L (4.7 mg/dL) is low.
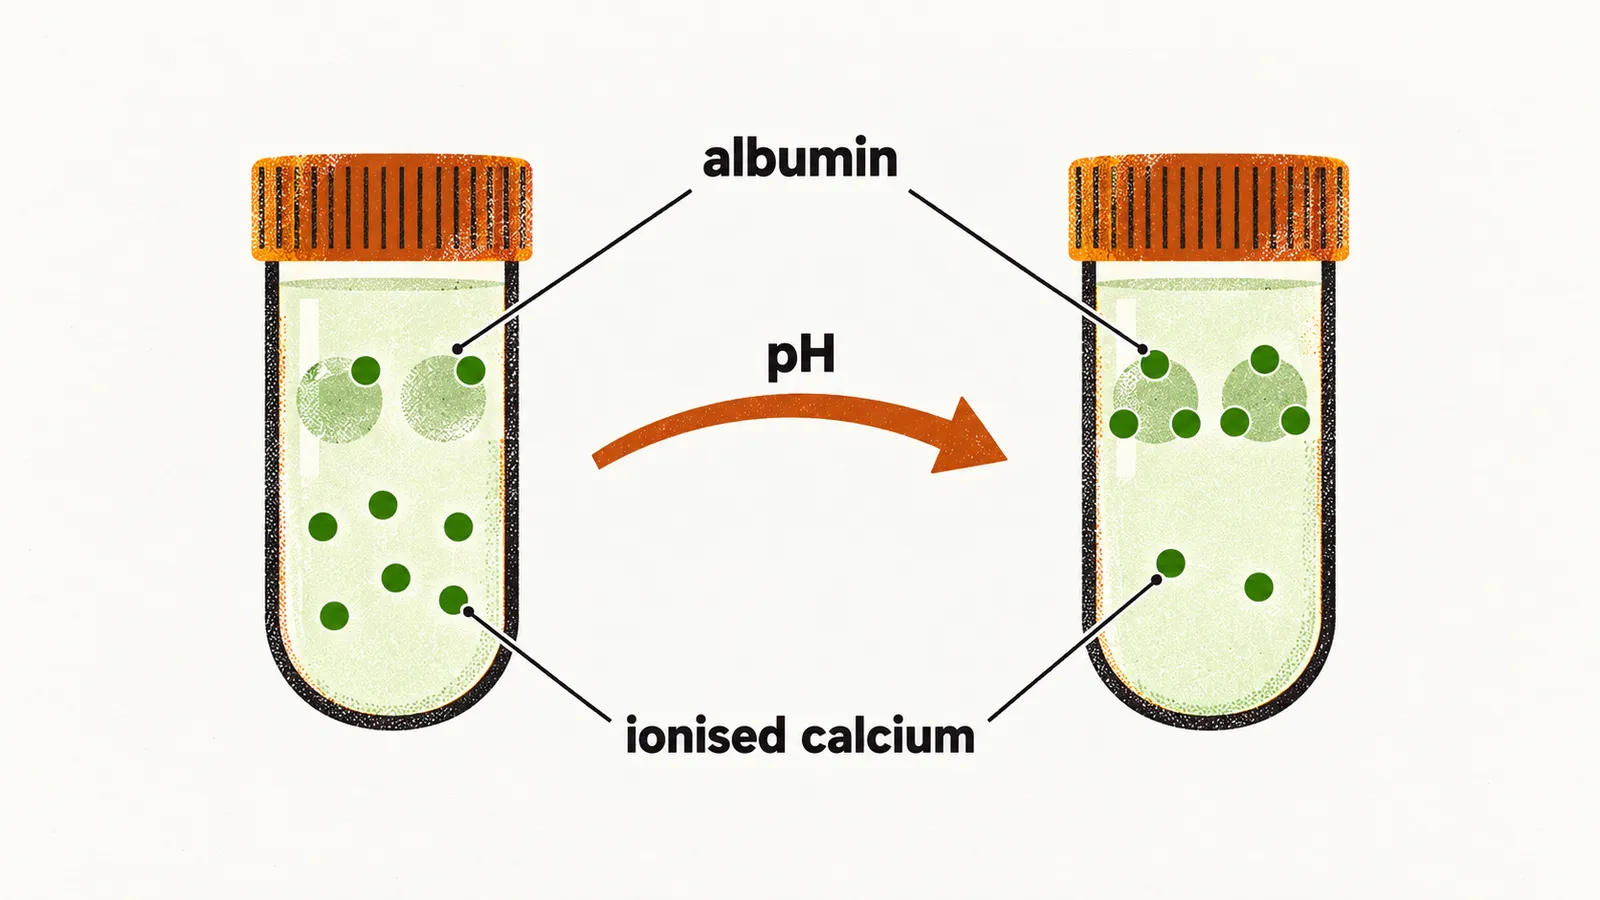
In critically ill patients with acid-base disturbances, ionised calcium is preferable. The reason is that the binding of calcium to albumin changes with pH. The free fraction can therefore move with pH while the total may not, so a correction based on albumin alone can mislead.
Is the gland answering?
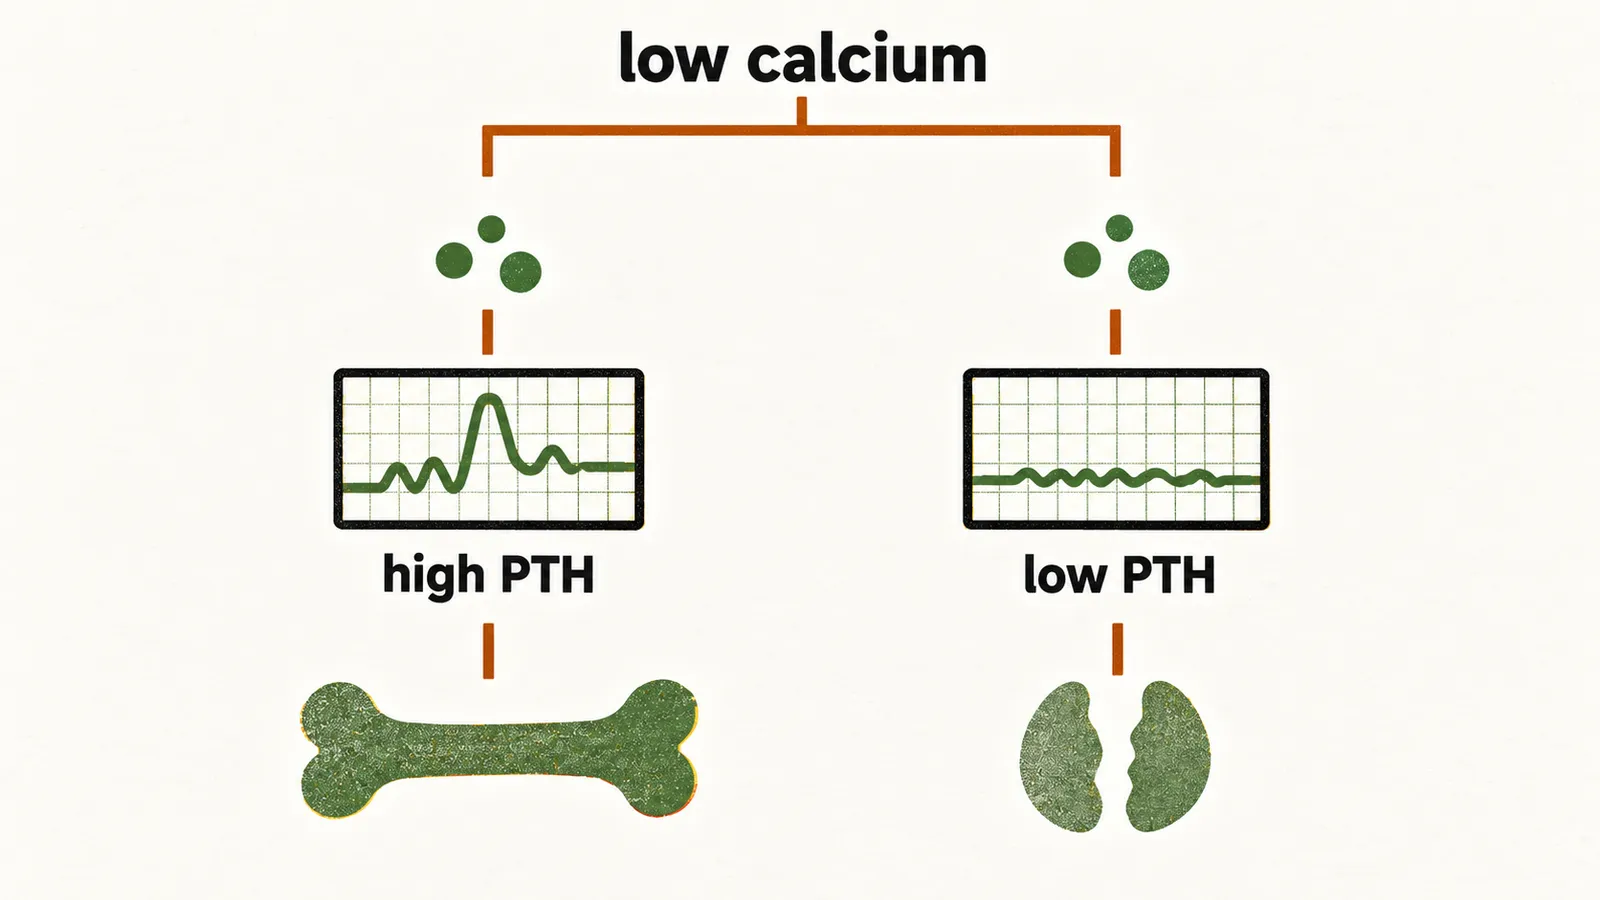
Once the free calcium is known to be low, the question is whether the glands answer it. Serum PTH is the most useful test. The same low calcium means different things depending on whether the glands are answering, and a gland that is answering raises PTH.
For this reason PTH is read in the context of the calcium level, not on its own. PTH rises as calcium falls, so a value is read against the calcium that produced it. When calcium is low, PTH should be high, because the glands sense the falling ionised calcium and secrete PTH in response.
Two readings follow. A low or inappropriately normal intact PTH means the glands are not responding, which is hypoparathyroidism: the glands are both the sensor and the source of PTH. A high PTH means the glands are responding, so the fault lies outside them. The assay should be an intact PTH assay with reliable performance at the low end of the normal range.
If PTH is high, where is the fault?
A high PTH moves the search outside the glands. PTH acts through the kidney and active vitamin D, so a high PTH with low calcium points to a fault in the supply or activation of vitamin D, in absorption, or in the response of the tissues. The causes outside the glands with high PTH are vitamin D deficiency, chronic kidney disease, malabsorption and PTH resistance.
Which tests separate the causes?
Measuring serum phosphate, creatinine and 25-hydroxyvitamin D alongside PTH usually identifies the cause. Phosphate, creatinine and vitamin D point to which outside cause is at work.
Phosphate reads the effect of PTH on the kidney, which excretes phosphate under PTH’s drive. When PTH is absent or ineffective, phosphate tends to be high. When PTH is high, it pulls phosphate out through the kidney, so phosphate tends to be low.
This is why phosphate helps separate hypoparathyroidism and pseudohypoparathyroidism from vitamin D deficiency. In hypoparathyroidism and pseudohypoparathyroidism the missing or ineffective PTH leaves phosphate high. In vitamin D deficiency the rise in PTH keeps phosphate low, through the same phosphate-losing action.
Why must magnesium always be checked?
Magnesium sits upstream of PTH, so it should always be checked. Magnesium depletion impairs PTH secretion, and it also blunts the action of PTH on the kidney.
This has a practical consequence. Hypocalcemia from magnesium deficiency does not correct adequately with calcium and vitamin D until the magnesium is replaced. In this state PTH secretion is impaired.
What else is checked, and why?
Further tests are added according to the presentation.
- Lipase, for pancreatitis. Acute pancreatitis can lower calcium.
- ACTH, cortisol and TSH, for polyendocrine failure. An autoimmune attack can involve several endocrine glands, so the adrenal and thyroid are checked along with the parathyroid, as in APS-1 from Etiologies of hypocalcemia.
- 1,25-dihydroxyvitamin D, for deficiency states. Measuring it checks the step the kidney supplies.
When is pseudohypoparathyroidism suspected?
A high PTH with low calcium and the right signs turns the search to tissue resistance. Signs and symptoms of hypocalcemia with a high serum PTH should raise suspicion of pseudohypoparathyroidism, in which the gland answers but the tissue does not. The signs of neuromuscular irritability are described in Clinical manifestations of hypocalcemia.
Albright hereditary osteodystrophy (AHO) is typically manifested as short stature, brachydactyly, subcutaneous calcification and obesity. Pseudohypoparathyroidism: PTH resistance and AHO explains how these features follow from the loss of one working copy of the gene.
In a patient with AHO, the diagnosis to consider is pseudohypoparathyroidism 1a or pseudopseudohypoparathyroidism. A patient with only AHO and no biochemical alteration related to PTH resistance has PPHP, with a normal serum calcium and a normal serum phosphate.
How is the kidney’s response tested?
The test checks whether the kidney answers an injected PTH. The classical test for pseudohypoparathyroidism measures the kidney response to an injection of PTH. PTH normally raises cAMP in the kidney and makes the kidney excrete more phosphate in the urine, so the test reads the response through urinary cAMP excretion and the urinary phosphate level.
The normal physiological response, and the response in hypoparathyroidism, is a 10- to 20-fold increase of urinary cAMP. A missing rise is therefore abnormal. In PHP 1a and PHP 1b there is no increase of urinary cAMP, because the chain that carries the PTH signal is interrupted.
What confirms the diagnosis?
The kidney test points to the gene, which is where the definitive answer sits. The definitive diagnosis of PHP 1 is genetic analysis of the GNAS gene.
How low is the calcium, and does it cause symptoms?
Once the cause is identified, the next question is how far the calcium has fallen and whether it causes symptoms, because this decides how quickly it must be replaced. So how quickly must it be replaced?