Hypocalcemia has a limited set of causes.
What lever has failed?
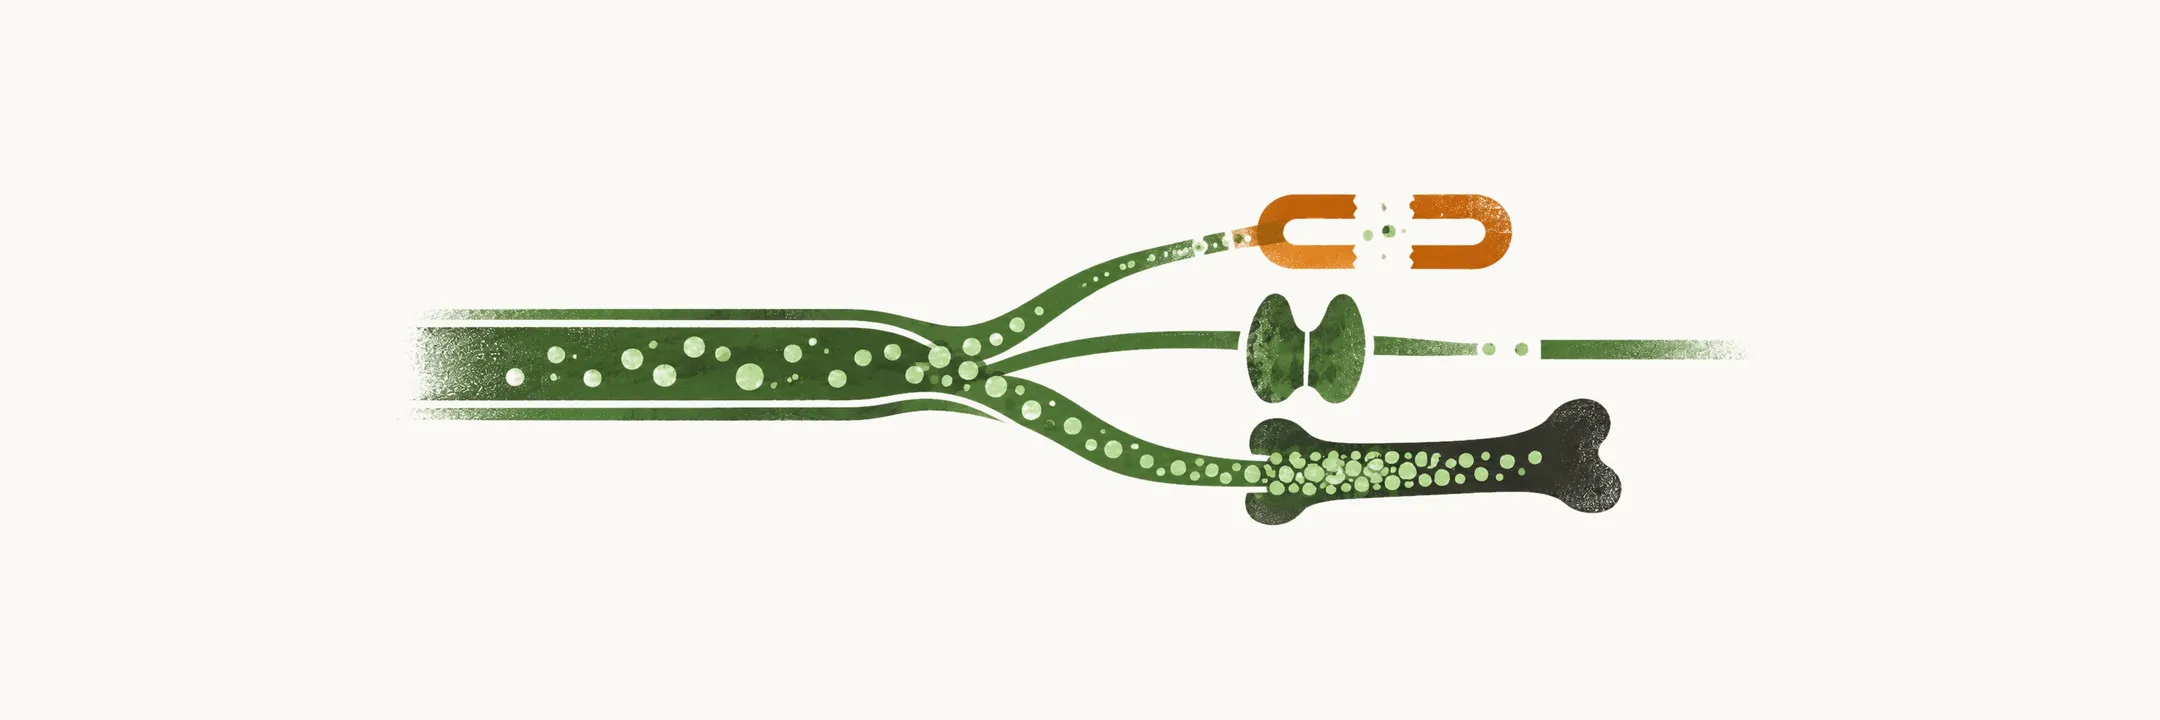
Blood calcium is kept in a narrow range by three levers. The parathyroid glands make parathyroid hormone (PTH), which raises calcium by stimulating bone to release it. Vitamin D is inactive when it is eaten or made in the skin. It has to be hydroxylated twice, and the first step happens in the liver. The third lever is movement: calcium can be pulled out of the blood into bone or damaged tissue, and the level falls when that happens.
So the causes can be grouped by which part of calcium control has failed: the vitamin D pathway, the parathyroid response (PTH release), or the traffic of calcium out of the blood into bone or damaged tissue. The mechanism behind each cause explains the resulting calcium level and points to the treatment it needs.
How does vitamin D fail?
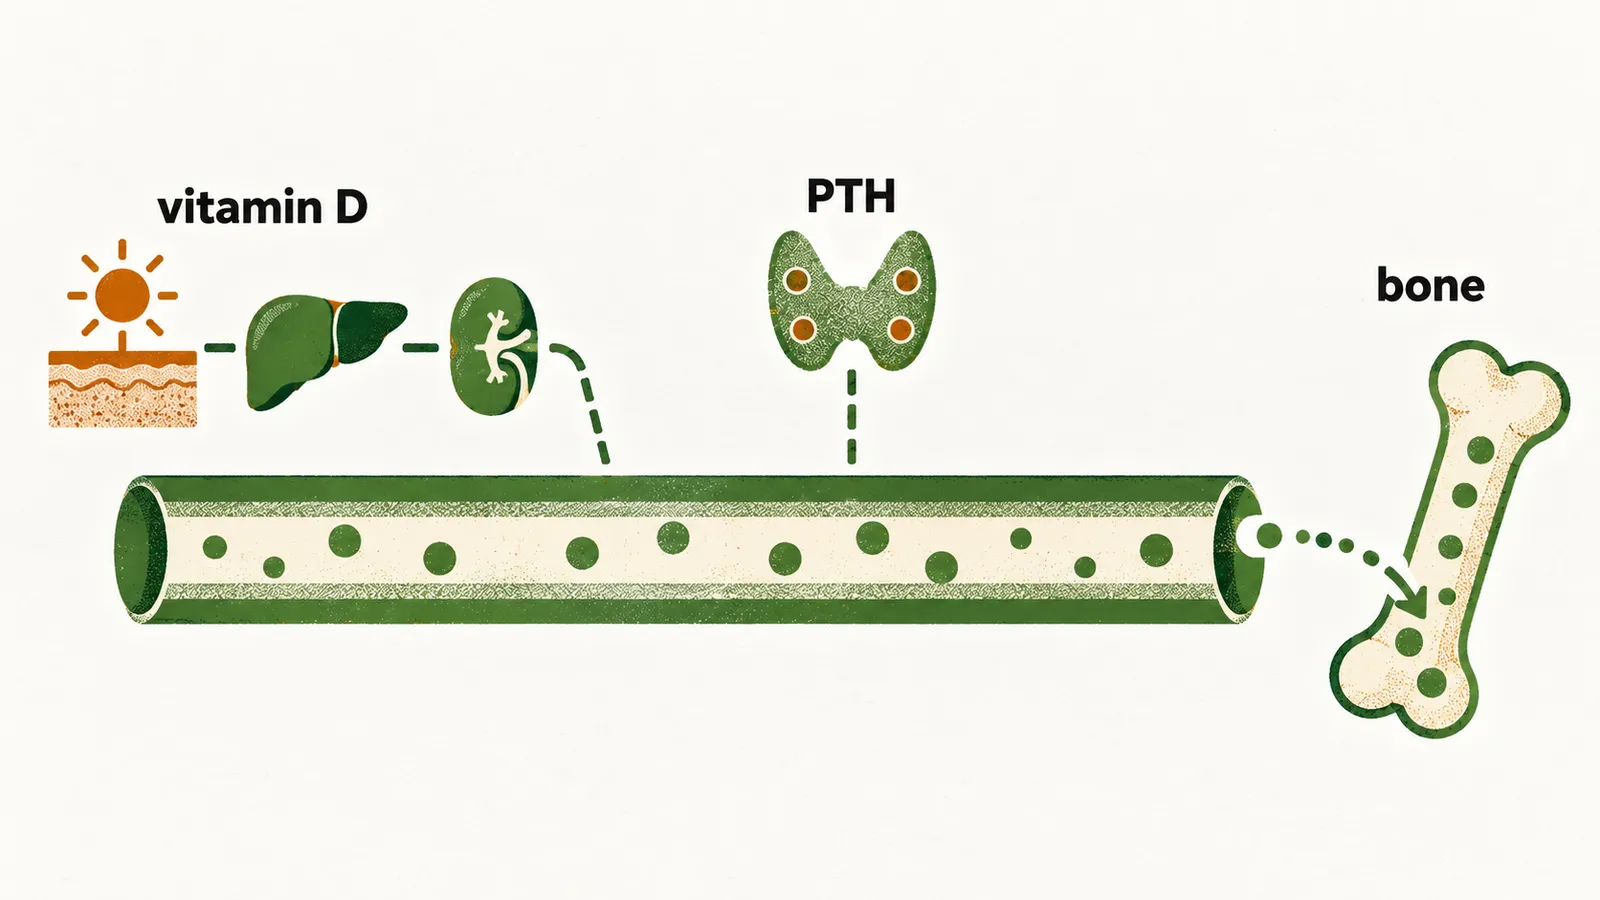
Vitamin D is inactive until it is hydroxylated twice. If the supply is too small, or the chain breaks at any step, less active vitamin D is made. Acquired or inherited vitamin D disease is one of the most common causes of hypocalcemia.
Vitamin D deficiency is defined as a 25-hydroxyvitamin D level below 20 ng/ml, and the estimated prevalence of true vitamin D deficiency is about 40%. The acquired causes are:
- low intake of vitamin D-fortified food, or a restricted diet;
- cultures in which clothes cover most of the body;
- malabsorption;
- liver and renal disease.
The causes of inadequate vitamin D production and action are: nutritional deficiency, lack of sunlight exposure, malabsorption, post-gastric bypass surgery, end-stage liver disease and cirrhosis, chronic kidney disease, and vitamin D-dependent rickets types 1 and 2.
Which organs does the vitamin D chain depend on?
The chain runs through the liver and the kidney, so organ disease can break it. Liver disease is not a common cause of vitamin D deficiency. At least 90% liver damage is needed to directly affect the production of 25-hydroxyvitamin D. In the early stages of liver disease, intestinal vitamin D absorption is nevertheless abnormal, because fat absorption is abnormal.
In chronic renal failure, hyperphosphatemia reduces the production and activation of vitamin D. Vitamin D travels in the blood on a carrier protein, and in nephrotic syndrome vitamin D falls, possibly because these carrier proteins are lost from the serum.
What do inherited vitamin D disorders do to bone?
Rickets is a spectrum of disorders in which growing bone is not mineralised normally, so bones stay soft and deform. Rickets can be caused by deficiency of vitamin D, calcium or phosphate.
The inherited causes are rickets and the vitamin D-dependent rickets (VDDR) disorders. VDDR is very uncommon and occurs in two forms. VDDR type 1 results from a defect in the renal production of 1,25-dihydroxyvitamin D. VDDR type 2 results from a mutation in the vitamin D receptor.
When do the parathyroid glands stop making PTH?
The second lever is PTH. Hypoparathyroidism means inadequate PTH production. PTH raises calcium by stimulating bone resorption, so when the glands make too little, less calcium is released from bone and the level falls.
The most common cause of hypoparathyroidism is post-surgical damage. Autoimmune hypoparathyroidism is the second most common cause in adults.
Why does neck surgery damage the glands?
The most common route to lost PTH is the operation itself. Post-surgical damage can happen during surgery on the parathyroid or thyroid gland. Postoperative parathyroid failure is the most common adverse effect of total thyroidectomy.
Permanent post-operative hypoparathyroidism is diagnosed when hypoparathyroidism is still present at least 6 months after surgery. In some cases, therefore, hypoparathyroidism resolves spontaneously.
Transient hypocalcemia after thyroidectomy is the pattern encountered most often. The proportion of patients affected differs between studies. In one study the figure is estimated at around 35%, with the permanent form in about 2% of cases.
Some studies suggest a cutoff for predicting symptomatic hypocalcemia after total or near-total thyroidectomy. The test is the 1-hour post-operative intact PTH. A low value means a higher chance of hypocalcemia, and with an intact PTH above 10 pg/ml these patients do not develop symptomatic hypocalcemia.
What about removing an adenoma?
A removed adenoma leaves the other glands to recover. Hypocalcemia after parathyroidectomy for an adenoma follows a different route. The remaining normal parathyroid glands were suppressed by the adenomatous gland that has been removed, and they need time to regain their function.
Can the glands fail as part of a syndrome?
Some glands fail because they never formed properly. Hypoparathyroidism can be one part of a genetic syndrome.
DiGeorge syndrome is the most common gene deletion syndrome in humans and occurs in 1 in every 4000 newborns. A microdeletion of part of chromosome 22 disrupts the development of the third and fourth pharyngeal pouches during embryonic life. The results are:
- aplasia or hypoplasia of the thymus gland, so immunodeficiency and recurrent respiratory infections are common;
- aplasia or hypoplasia of the parathyroid glands, so PTH is lacking;
- cardiac outflow malformations.
What is APS-1?
Another inherited cause is driven by the immune system. Hypoparathyroidism can occur in an autoimmune context: autoimmune polyendocrine syndrome type 1 (APS-1). Because the immune system attacks more than one endocrine organ in this syndrome, the parathyroid is one of several targets. APS-1 is caused by a mutation in the AIRE gene.
At least two of three conditions are needed for the diagnosis: autoimmune parathyroid disease, autoimmune adrenal disease, and mucocutaneous candidiasis. The classic triad is hypoparathyroidism, candidiasis and adrenal insufficiency (Addison’s disease).
Two or three of the following are also associated:
- type 1 diabetes mellitus;
- primary hypogonadism, especially ovarian failure;
- autoimmune thyroid disease;
- chronic active hepatitis;
- alopecia (totalis or areata);
- vitiligo.
Why can calcium fall after surgery when the glands are fine?
The glands are not always the problem; bone can take calcium out of the blood. Hungry bone syndrome is a recognised postoperative complication, so hypocalcemia after thyroidectomy or parathyroidectomy does not always come from a failing parathyroid gland.
After either operation in a patient with hyperparathyroidism, bone can mineralise rapidly. Hungry bone syndrome is thought to happen because the sudden loss of the stimulus to bone resorption (PTH or thyroid hormone) leaves bone formation running ahead of resorption. Mineral is then drawn out of the blood after the operation. The rapid mineralisation of bone causes bone pain, and the resulting hypocalcemia causes tetany.
What else takes calcium down?
Several further causes do not belong to the groups above. They are the miscellaneous etiologies:
- neonatal hypocalcemia;
- hyperphosphatemia, from phosphate retention in acute or chronic renal failure, from excess phosphate absorption caused by enemas or oral supplements, or from massive phosphate release in tumour lysis or crush injury;
- drugs, particularly intravenous bisphosphonate or denosumab therapy in patients with vitamin D insufficiency or deficiency, and foscarnet;
- rapid transfusion of large volumes of citrate-containing blood;
- acute critical illness;
- hungry bone syndrome after thyroidectomy for Graves’ disease or after parathyroidectomy;
- osteoblastic metastases;
- acute pancreatitis;
- rhabdomyolysis;
- mitochondrial gene defects.
Can low magnesium stop the glands?
Magnesium depletion lowers calcium by interfering with the end-organ actions of PTH and by inhibiting its secretion. This is functional hypoparathyroidism, and it also arises with magnesium excess.
What if the gland makes PTH and the tissue still ignores it?
One last failure remains: PTH resistance, called pseudohypoparathyroidism, in which the parathyroid gland makes PTH but the tissues do not respond to it. The gland is working, but the tissue does not respond to the PTH; how can that be, and why does calcium stay low?