Pseudohypoparathyroidism is a state of biological resistance to parathyroid hormone. The parathyroid gland is present and can make PTH, but the tissues do not answer it. So serum calcium stays low while the PTH level is high.
This raises a question: why does a gland that can make PTH fail to produce a response?
Who described it
Dr. Albright introduced the condition in 1942. The classical demonstration is an injection of PTH: it produces no rise in serum calcium and no fall in serum phosphate.
Hypocalcemia: etiologies covers the other causes of low calcium; pseudohypoparathyroidism is the one where PTH is present but not heard. What does a cell need in order to hear PTH?
How PTH signals
The PTH receptor, mainly PTH1R, is a G protein-coupled receptor. It is coupled to a Gs subunit that activates protein kinase A and so increases cAMP formation inside the cell. Resistance arises when this signalling chain is interrupted.
The interruption is most often a defect in the GNAS gene, which encodes the Gs alpha subunit, rather than a defect in the receptor itself.
Gs alpha also carries the signal of other hormones. Patients with PHP 1a can show resistance to other hormones, which may appear as hypothyroidism, short stature, hypogonadism or intellectual disability.
What happens when the GNAS copy is faulty?
Imprinting
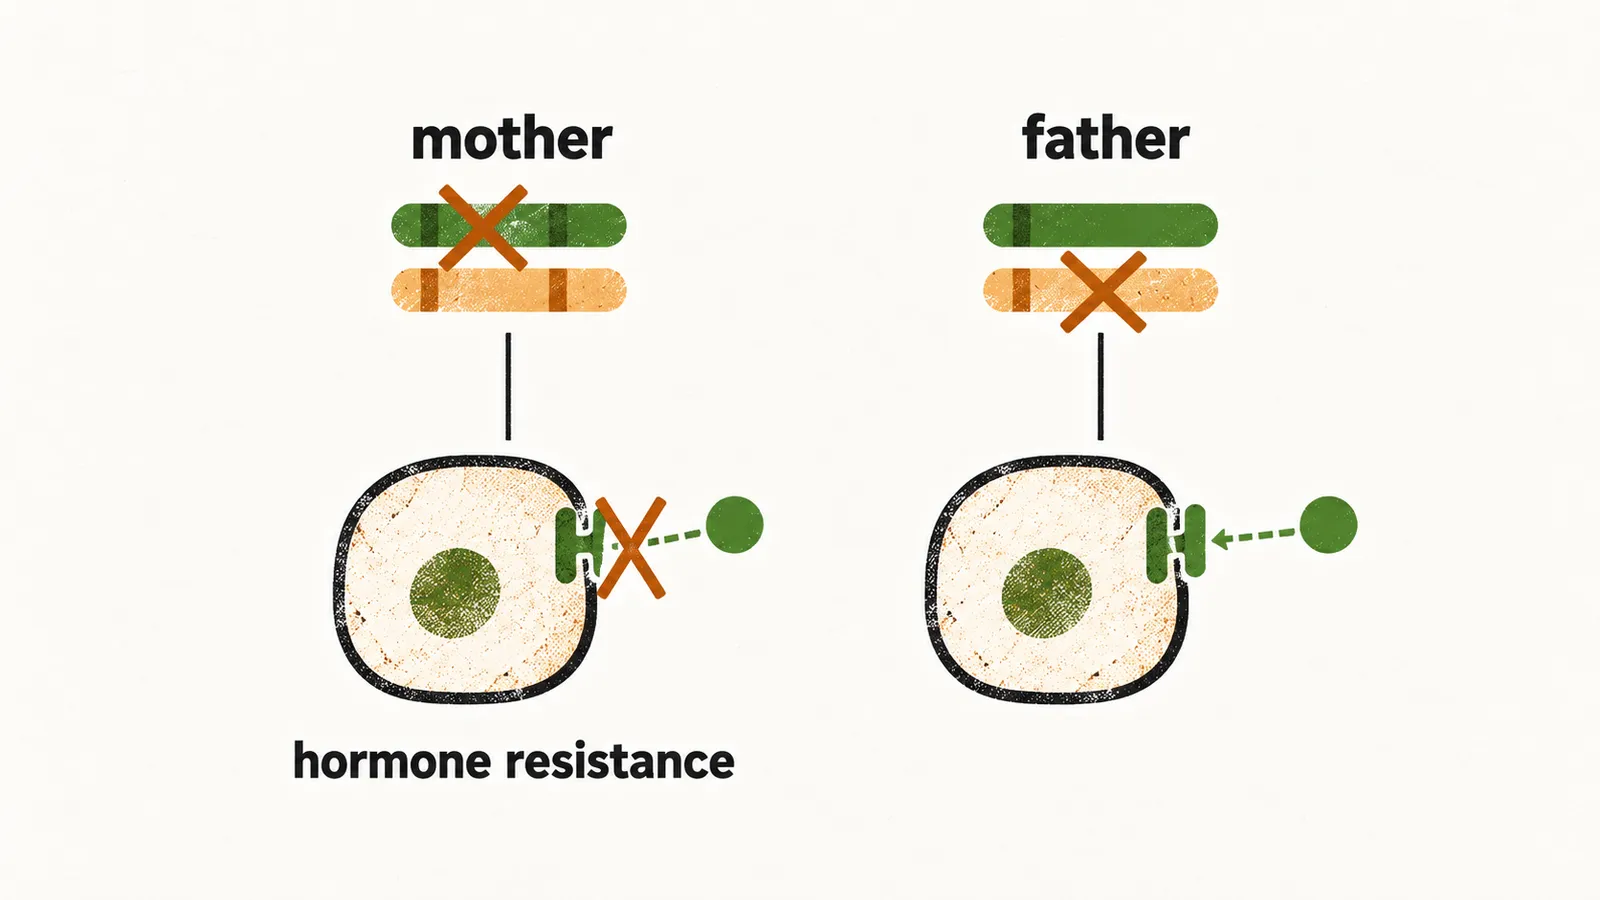
GNAS is an imprinted gene, so its expression depends on which parent the copy came from. In most tissues GNAS is expressed from both alleles. In a few tissues, including the proximal renal tubule, thyroid, gonads and pituitary, paternal Gs alpha expression is silenced, so only the maternal copy is read.
This decides what a mutation does. A mutation inherited from the mother removes the only working copy in those tissues and produces hormone resistance. The same mutation inherited from the father leaves the maternal copy active and produces no resistance.
The physical features of Albright hereditary osteodystrophy follow from having only one working copy of Gs alpha in tissues that express both alleles. So these features appear whichever parent transmitted the mutation.
Inactivating GNAS mutations are transmitted in an autosomal dominant pattern, but which parent transmits the mutation decides the phenotype. That is why the forms of pseudohypoparathyroidism have different biochemistry despite sharing the same gene.
If the mother’s copy is the faulty one, which form appears?
PHP 1a
In PHP 1a the mutation comes from the mother. Resistance is present in every tissue that depends on the maternal copy. Serum calcium is low, serum phosphate is high and serum PTH is high.
Patients with PHP 1a also show the features of Albright hereditary osteodystrophy (AHO). What are those features?
Albright hereditary osteodystrophy
AHO is a constellation of developmental and somatic defects. It is characterised by short stature, round facies, brachydactyly, obesity and subcutaneous calcification.
AHO arises because loss of one working copy acts in the tissues that do not imprint. So a patient can have AHO without the hormone resistance that comes from loss of the maternal copy in imprinted tissues.
What if the faulty copy comes from the father?
Pseudopseudohypoparathyroidism
When the same mutation is inherited from the father, the normal maternal copy is still expressed in the kidney and other imprinted tissues. In pseudopseudohypoparathyroidism serum calcium and serum phosphate remain normal. The patient nevertheless has AHO.
Pseudopseudohypoparathyroidism (PPHP) is therefore AHO without hormone resistance.
What changes when the defect is an epigenetic one?
PHP 1b
The defect in PHP 1b is epigenetic. The methylation of the GNAS locus is lost and the gene is not transcribed normally. PHP 1b patients have hypocalcemia, hyperphosphatemia and a high PTH level. They do not have the features of AHO.
How do the other forms differ in their cAMP response?
PHP 2
The exact pathophysiology of PHP 2 is not yet known. In PHP 1a and PHP 1b the cAMP response to PTH is reduced; unlike them, the cAMP response is normal in PHP 2. The defining feature of PHP 2 is a lack of phosphaturic response even though cAMP increases normally after exogenous PTH. So the PHP 2 defect lies downstream of cAMP generation.
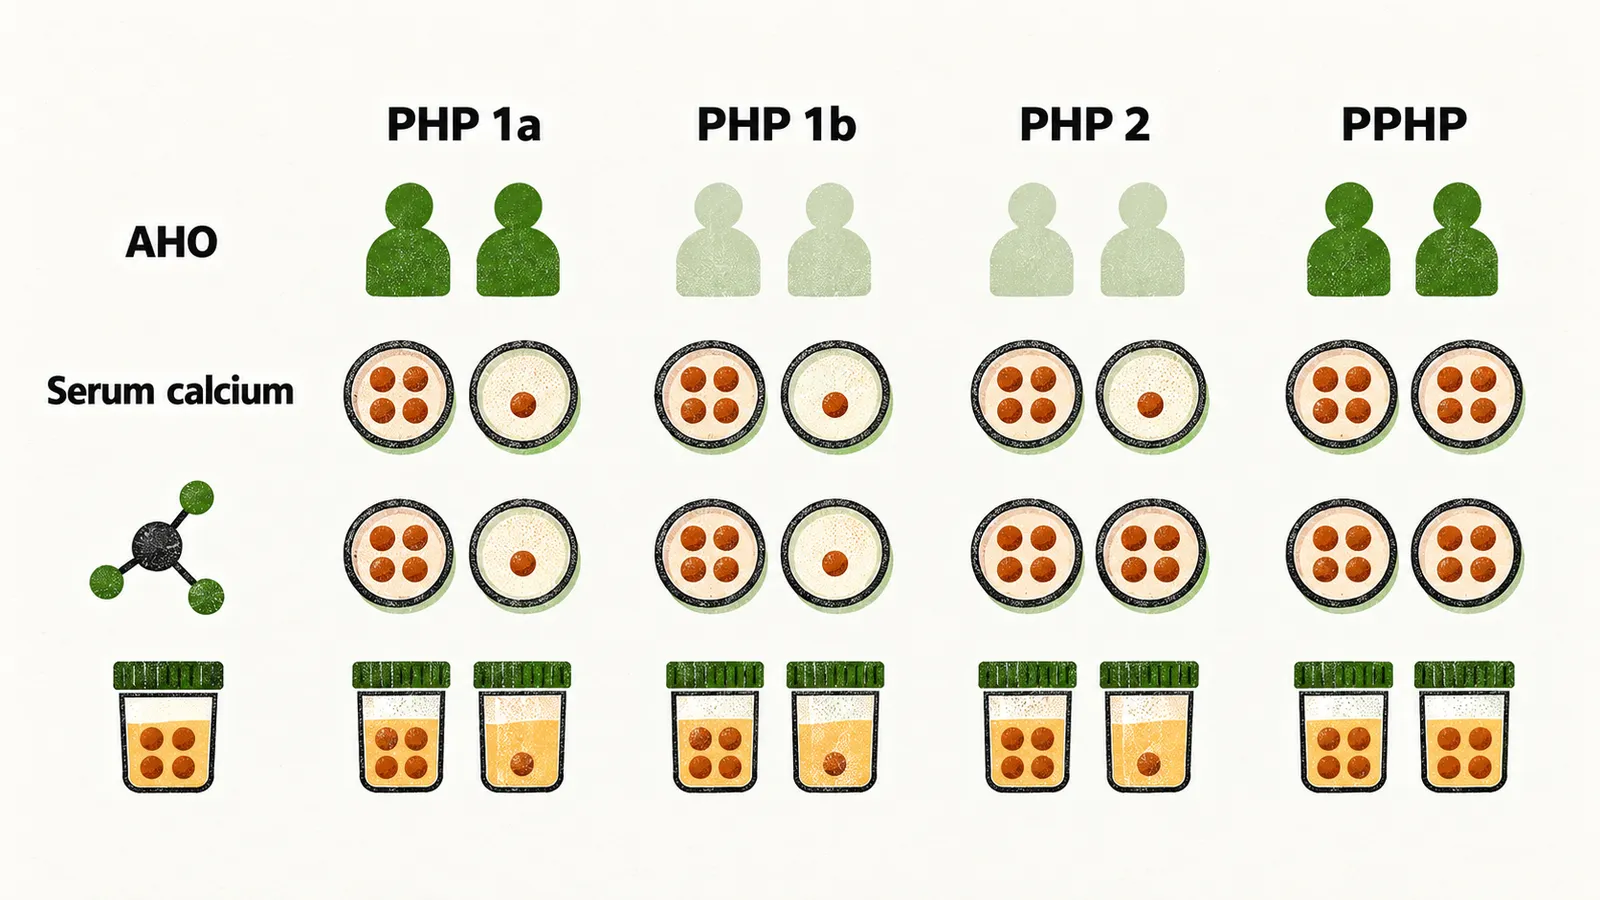
The forms can be told apart by whether AHO is present, by serum calcium, and by the cAMP and phosphate response to PTH. How do the forms look side by side?
Comparing the forms
In the table, NL means normal.
| PHP 1a | PHP 1b | PHP 2 | PPHP | |
|---|---|---|---|---|
| AHO | Present | Absent | Absent | Present |
| Serum calcium | Low | Low | Low | NL |
| cAMP response to PTH | Reduced | Reduced | NL | NL |
| Urinary phosphate | Low | Low | Low or NL | NL |
| Hormone resistance | PTH, TSH and other Gs-alpha coupled hormones | PTH target tissues only | PTH target tissues only | None |
| Molecular defect | Reduced functional Gs-alpha levels, mutation on the maternal allele | Abnormalities in Gs-alpha gene transcription (loss of methylation) | Unknown | Reduced functional Gs-alpha levels, mutation on the paternal allele |
What pattern do we look for in a patient?
Diagnostic pattern
These patterns are what is looked for when a patient with hypocalcemia and a high PTH level is investigated for PTH resistance.