
Group A streptococcus lives on the surface of the throat, on the tonsils and on the posterior pharyngeal wall. A sore throat caused by a virus looks the same to the eye, so nothing at the bedside shows whether the organism is there. The way to find out is to collect material from where the organism lives and test it. That is why GAS pharyngitis is diagnosed with a swab, and why the quality of the specimen matters as much as the test that reads it.
Why can the examination not make the diagnosis?
The signs of GAS overlap with those of adenovirus and EBV to the point of being indistinguishable. Exudate and tender nodes can therefore shift how likely GAS is. They cannot show that it is present.
This gives clinical scores a limited job, and the job is not the same at both ends of the scale. At the bottom of the range a score can end the reasoning. At the top it cannot establish the diagnosis. The rule that organises everything below is: the score decides whether to test, and the test decides whether to treat.
How is the swab taken so that it means something?
A swab is a procedure with a measurable failure rate. Almost all of that failure comes from two errors: the wrong site and the wrong pressure.
The first requirement is access to the back of the throat.
- Immobilise the child. An unheld child closes the mouth as the swab approaches, and a swab pushed against a moving child hurts.
- Always use a tongue depressor. Without it the mouth closes before the posterior pharynx is reached.
The second requirement is firm contact with the right places. The organism sits on the tonsils and the posterior pharyngeal wall, so the swab must be rubbed firmly over both tonsils and the posterior pharyngeal wall. A gentle swab that touches only the soft palate is the classic false negative. Firm contact with the two areas where GAS sits is what makes the test work.
The sites to avoid follow from the same reasoning: saliva, the base of the tongue, the sublingual area and the buccal mucosa. The organism is not what lives there. In children with culture-proven GAS, swabs from those sites were frequently negative in the same child whose tonsillar swab grew the organism. The site, not the test, decides the result.
What can a rapid antigen test deliver?
The swab goes to a test. The rapid antigen detection test (RADT) is the point-of-care test that made GAS diagnosis practical in primary care.
It works on a simple principle. An extraction reagent breaks down the bacterial cell wall and exposes the group A-specific carbohydrate antigen. The antigen binds a labelled antibody on a strip and produces a visible line in 5 to 10 minutes. The format is the same idea as a rapid SARS-CoV-2 test, and it carries the same lesson about sampling: the test is only as good as the specimen.
How good is it? Pooled estimates in children give a sensitivity of about 86% and a specificity of about 95%. There is substantial variation between test types and between studies, so these are central figures, not guarantees.
The two numbers are read differently.
- A positive RADT needs no confirmation. The specificity is high enough that a positive result in a child with a compatible illness justifies treatment. A culture after a positive RADT adds nothing but delay.
- A negative RADT is not a rule-out in children. With a pooled sensitivity around 86%, roughly one child in seven with true GAS tests negative.
This is why the CDC and the 2012 IDSA guideline advise a back-up throat culture when the RADT is negative in a child or adolescent. The culture needs a mechanism for contacting the family and starting antibiotics if it grows GAS.
Do all guidelines agree on the back-up culture?
They do not, and a negative rapid test is exactly where the disagreement shows. Practice varies. Some national guidelines, including the UK NICE guideline on acute sore throat, do not rely on microbiological testing at all in most patients. They use clinical scoring alone to choose between immediate antibiotics, back-up antibiotics and no antibiotic. Others, particularly in North America, treat back-up culture as standard in children. The local protocol governs.
One position is not defensible: treating a negative rapid test in a child with a classic picture as proof that the illness is viral.
What does a culture add, and why is the wait acceptable?
Throat culture remains the reference standard. Its disadvantages are timing and process. Results take 18 to 24 hours. Some GAS strains grow slowly, so a negative plate should be re-incubated overnight, because 48-hour cultures detect a further proportion of true positives that a 24-hour reading misses.
Susceptibility testing is unnecessary. GAS has never developed resistance to penicillin, so the culture result will not change the antibiotic choice.
Is the delay dangerous? Acute rheumatic fever is one reason a sore throat is investigated, and antibiotics started within about nine days of symptom onset still prevent it. A culture returning on day 2 therefore changes neither the rheumatic outcome nor the safety of the child. It does change how the child feels over those two days. That is why a rapid test matters when it is available.
Where do clinical scores help?
Before any swab there is the decision to swab. The McIsaac score is a modification of the Centor score, and it is the scoring system taught in primary care. It has five items, one point each except the age item:
- fever (or history of fever): +1
- tonsillar exudate: +1
- tender anterior cervical lymphadenopathy: +1
- absence of cough: +1
- age 3-14 years: +1; age 15-44 years: 0; age 45 years or older: -1
The maximum score is 5.
The two ends of the scale are not mirror images, and this asymmetry is the reason the score and the swab can be taught together.
The low end (0 or 1). A child with none or one of the independent predictors has a low probability of GAS. The guideline wording accepts the low band as valid to rule the diagnosis out, with two caveats: there is no ongoing GAS epidemic, and the setting has a low prevalence of rheumatic heart disease, as in Italy. Under those conditions a low band can close the visit without a swab.
The high end (4 or 5). Here the score has not earned the same authority. Fever, exudate, tender nodes and absent cough do raise the probability of GAS, but they raise it in a way that cannot distinguish GAS from adenovirus or EBV, which produce the same exudative tonsillitis with the same nodes. The score measures the shape and severity of the pharyngitis, not the presence of Streptococcus pyogenes. So a high score justifies a swab. In some guidelines it also justifies starting antibiotics in the same encounter while awaiting the swab. It never justifies believing that GAS is established.
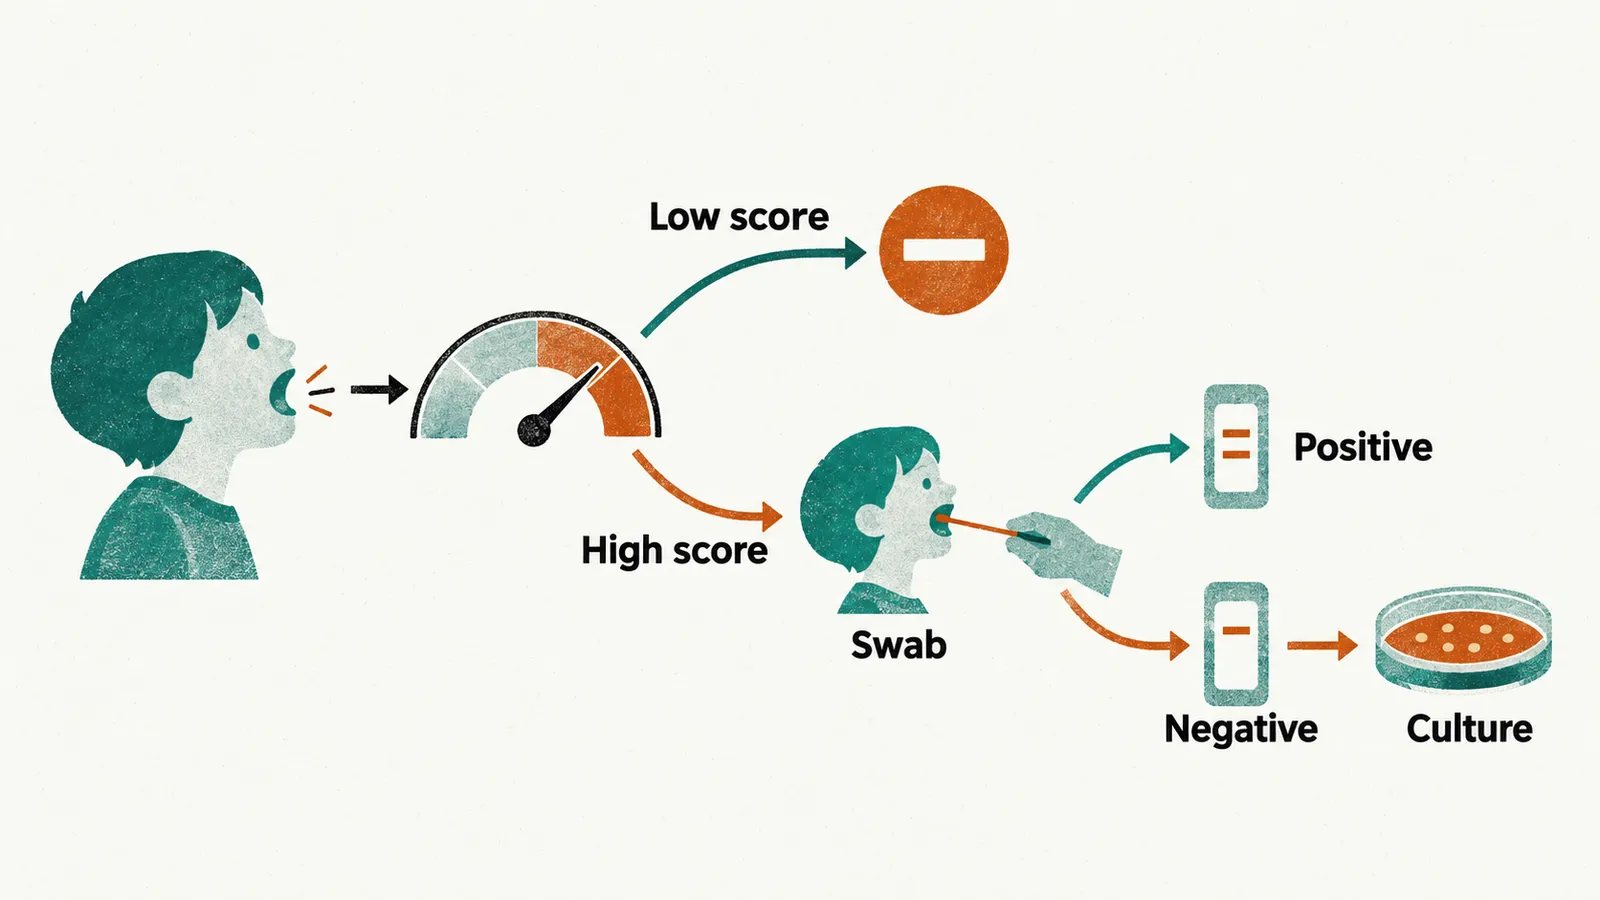
The IDSA published a focused update in 2025 that revisits the use of clinical scoring systems for risk assessment in children and adults. The practical position remains that scoring is a triage step. The rule is short: a low score can end the visit, and a high score cannot. A high score only moves the decision.
Which children should not be swabbed, and what does a positive swab mean?
A low score is one way of deciding not to swab. The other is the kind of child.
Most acute pharyngitis is not GAS pharyngitis. Guidelines differ about how much testing is worthwhile, but two situations are reasonably consistent for not testing.
- Infants under 12 months. Pharyngitis is viral in the great majority of cases and GAS is uncommon, so the pre-test probability is low and a swab rarely changes management. Under 12 months is the only age band in which this old logic survives. The previous rule that children under 3 years are viral by default has been abandoned.
- A clearly viral illness. A child with prominent cough, coryza, hoarseness, or oral ulcers with no fever has a low probability of GAS even if an exudate is present, because the exudate cannot tell the organisms apart.
And when the swab is taken and is positive, what does it show? Between 10% and 21% of children with microbiological evidence of GAS are chronic carriers. A carrier has the organism sitting in the pharynx without causing the illness that brought the child to the clinic. A carrier who contracts a viral pharyngitis will test positive, because the swab finds the organism wherever it sits and says nothing about what is causing the illness. Neither does it measure the antibody markers antistreptolysin O and anti-DNase B.
A positive test is evidence of the organism, not proof that it is the cause. This is why a second positive test after treatment most often means carriage rather than failed treatment, especially if the child is asymptomatic or the illness does not behave like GAS pharyngitis. The clinical picture still matters at the margin.
A well child with recurrent positive tests who is treated again and again should prompt a question, not another antibiotic: is it carriage, non-adherence, or reinfection from a household contact?
Can carriage be removed, and what about contacts?
Repeated positives in a well child raise the question of eradication. It is possible: combined intramuscular penicillin plus four days of oral rifampicin, or a ten-day clindamycin course, have been studied. The evidence base is small and old, and routine treatment of carriers is not recommended.
Household and classroom contacts of a case of invasive GAS disease are a separate situation. Their management follows public-health guidance, and chemoprophylaxis is included only in defined situations.
For the child whose positive test does reflect acute infection, the remaining questions are practical ones: which antibiotic, what dose, and how long?