Group A Streptococcus (GAS) pharyngitis is difficult to treat almost entirely because of restraint. GAS has never developed resistance to penicillin anywhere in the world, and the penicillin that worked in the 1950s still works. So nothing about the organism demands a strong or broad drug. The antibiotics that fail, or that are unnecessary, are the broad-spectrum ones prescribed when the prescriber is unsure what else to do. The practical rule is the narrowest agent that reliably works for the individual child, held steady for the good of the next one. This discipline is called antibiotic stewardship.
The picture for the whole note is this. The antibiotic does two jobs: it shortens a mild illness a little, and, more importantly, it removes the organism before it can cause its complications. The second job takes longer than the first, and that gap between feeling well and being cured runs through the rules that follow.
What do antibiotics actually buy?
If the drug works so reliably, what does it achieve for the child? Four reasons justify antibiotics in confirmed GAS pharyngitis, and the evidence for each is uneven:
- relief of symptoms;
- fewer suppurative complications;
- prevention of acute rheumatic fever;
- reduced transmission.
Most of the evidence comes from pooled trials, expressed as a risk ratio or an odds ratio. A value below 1 means the outcome is less common with antibiotics. When the 95% CI includes 1, the difference is not statistically significant. The number needed to treat is the number of patients who must receive the antibiotic for one to benefit.
Symptoms. Compared with placebo or no treatment, antibiotics reduce the proportion of children with a sore throat at day 3: risk ratio 0.70, 95% CI 0.60–0.80. The number needed to treat to prevent one sore throat at day 3 is fewer than 6. Antibiotics also reduce headache at day 3 (risk ratio 0.49, 95% CI 0.34–0.70). They do not significantly reduce fever at day 3 (risk ratio 0.75, 95% CI 0.53–1.07). The benefit shrinks with time: 82% of patients given placebo or no treatment are symptom-free by one week.
Suppurative complications. They are described in Pediatric Group A Streptococcus: Virulence and Complications. Treatment lowers them. Acute otitis media within 14 days is reduced (Peto odds ratio 0.21, 95% CI 0.11–0.40), and so is peritonsillar abscess (quinsy) within two months (Peto odds ratio 0.16, 95% CI 0.07–0.35).
Acute rheumatic fever. A pooled analysis of 18 studies with 12,249 participants found that acute rheumatic fever within two months was reduced (Peto odds ratio 0.36, 95% CI 0.26–0.50). Most of these trials date from the 1950s, when rheumatic fever was far more common than in most settings today. Even so, this outcome makes treatment non-negotiable in settings where rheumatic heart disease still occurs.
Transmission. The pharyngeal bacterial load falls sharply within the first 24 hours of effective therapy, so the child becomes less able to pass the organism on.
One complication is missing from this list. Antibiotics have not been shown to prevent acute post-streptococcal glomerulonephritis. A pooled analysis of 10 studies with 5,147 participants had too few cases to show an effect either way. The evidence is therefore insufficient rather than negative, and glomerulonephritis is not a reason to prescribe.
Which penicillin, and at what dose?
Amoxicillin is the first-choice antibiotic for GAS pharyngotonsillitis where oral penicillin V is not available. In Italy, pediatric penicillin V formulations were withdrawn in the early 1980s. In the United States and Denmark oral penicillin V remains first-line and is equally effective.
The regimens are these:
- Amoxicillin (first choice in Italy): 50 mg/kg/day in 2 divided doses (25 mg/kg per dose, maximum 500 mg per dose) for 10 days, according to European product labelling and the 2024 Italian intersociety consensus. An accepted alternative is 50 mg/kg once daily, maximum 1 g/day, for 10 days.
- Penicillin V (first choice where available): 250 mg two to three times daily for 10 days in children, and four times daily in adolescents and adults.
- Benzathine penicillin G (intramuscular): a single dose, 600,000 units if the child weighs 27 kg or less and 1.2 million units if more.
The drug is chosen, so why does this dose differ from the one used for ear infections? Amoxicillin for GAS is 40–50 mg/kg/day, whereas amoxicillin for pneumococcus is 80–90 mg/kg/day. Amoxicillin, like other penicillins and cephalosporins, is a β-lactam. It acts by binding the bacterial penicillin-binding proteins, which build the cell wall, so the wall fails. In Streptococcus pneumoniae, altered penicillin-binding proteins reduce susceptibility to penicillin. The higher pneumococcal dose exists to overcome that. GAS has no such resistance to overcome.
Published practice for pharyngitis spans 40–90 mg/kg/day, not exceeding 3 g/day, so the indication has to be attached to the number. For GAS pharyngitis the dose is 40–50 mg/kg/day: there is no resistance, and the smallest effective exposure is the stewardship-correct one. For pneumococcal acute otitis media it is 80–90 mg/kg/day, because the altered penicillin-binding proteins reduce susceptibility in some strains and higher tissue concentrations are needed.
The schedule also matters. A twice-daily regimen is as effective as the same daily dose divided three times, and it is better tolerated. Adherence is the real threat to the ten-day course, rather than the drug. Once-daily dosing is effective in children older than 3 years.
Intramuscular benzathine penicillin is the alternative where adherence is genuinely impossible: impaired intestinal absorption, inability to take oral medication, or repeatedly missed doses in a child at high risk of suppurative complications, for example an immunodeficient child. It has a cost: the injection is painful and must be given by a trained professional.
Why ten days?
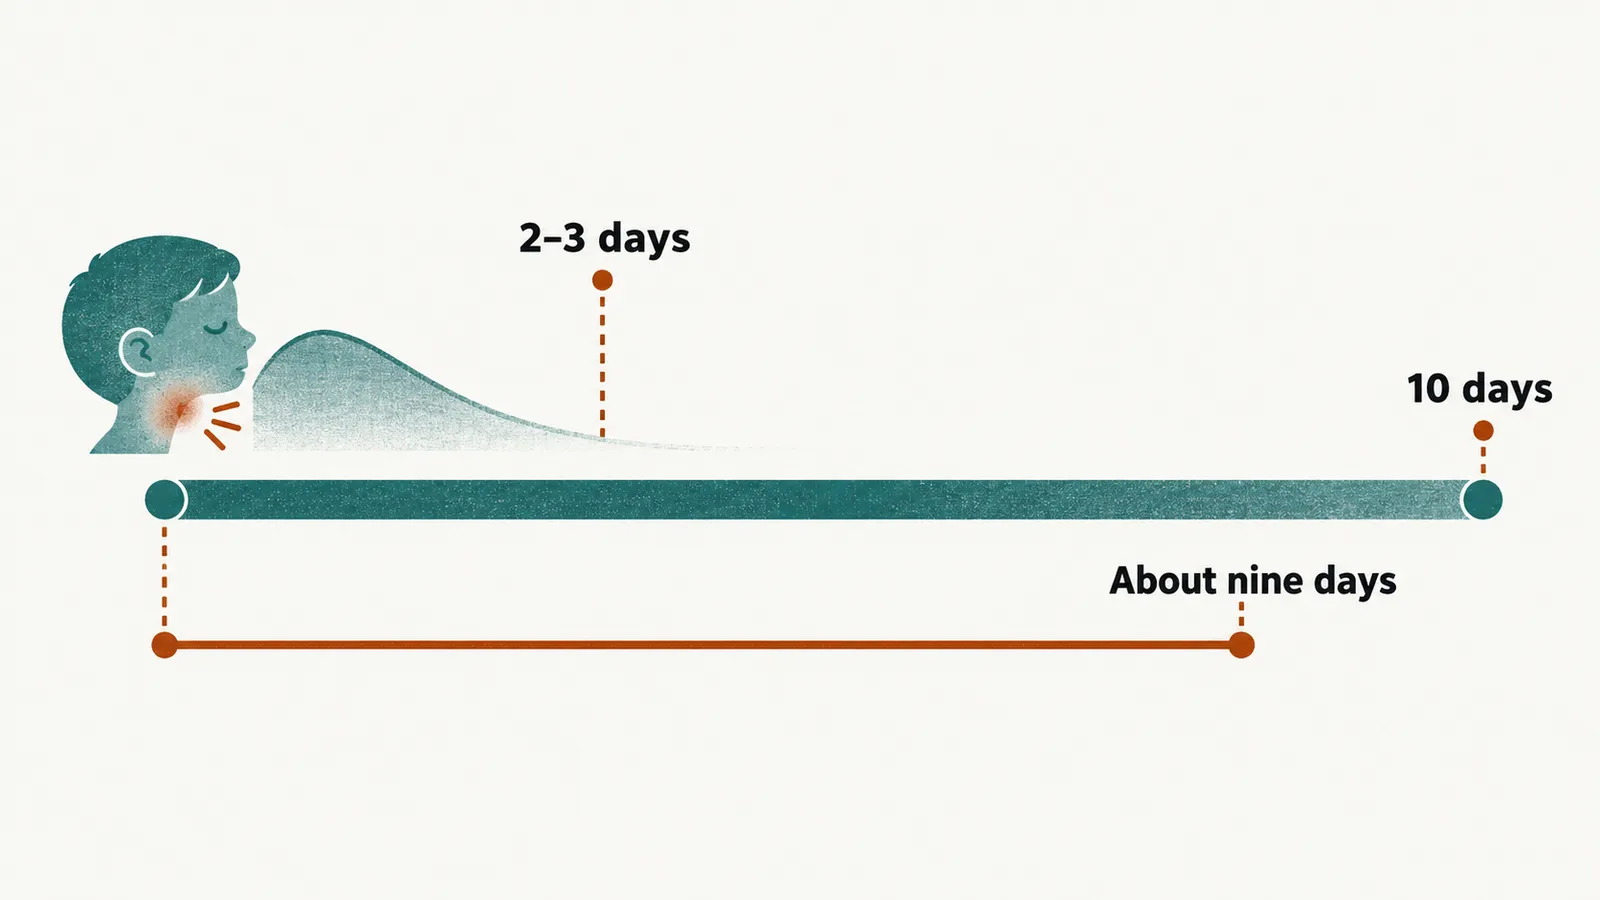
The child is better on day 3, so why not stop? Symptoms resolve after two to three days of treatment, but the organism has not yet gone. The remaining days are the eradication phase, and they are not for the sore throat. Eradication is what prevents rheumatic fever.
There is also a window. Antibiotic treatment started within about nine days of symptom onset still prevents acute rheumatic fever. Treatment started later does not. This one fact explains several habits:
- GAS pharyngitis is treated at all in settings where rheumatic fever is rare.
- The full ten-day course is completed although the child feels well on day 3.
- A two-day wait for a culture result is acceptable when no rapid test is available, as Pediatric GAS Pharyngitis: Diagnosis describes.
- A positive rapid test should be acted on in the same encounter rather than deferred.
Could a shorter course do the same? A six-day amoxicillin regimen performed similarly to ten days of penicillin V in one trial. The evidence on complications for shorter courses is too weak to generalise, because the studies were in populations with a low incidence of rheumatic fever and followed for only about a month. Some guidelines accept shorter courses: NICE five to ten days, the German guideline five to seven days. The 2024 Italian intersociety consensus deliberately retains 10 days for children, including in low-incidence regions, because critical outcomes have not been studied adequately.
The clinical work here is communicative, not pharmacological. Families stop treatment when the child feels well. The reasons include multiple drugs, frequent dosing, duration, disappearance of symptoms, side effects, taste and cost. Explaining that the last seven days prevent a heart complication years later keeps the course going.
Which drugs should not be used?
If penicillin works, what goes wrong when other drugs are used? Restraint applies to the choice of drug as well as the course. Because GAS remains susceptible to penicillin, a broader agent adds nothing against the target and exposes the rest of the child’s flora for no gain.
Amoxicillin-clavulanate shows this well. Clavulanate inhibits β-lactamases, bacterial enzymes that inactivate β-lactam antibiotics. GAS does not produce β-lactamases, so the inhibitor adds nothing against the target. What clavulanate does is broaden the spectrum to cover β-lactamase-producing oral anaerobes, Haemophilus influenzae, Moraxella catarrhalis, methicillin-sensitive Staphylococcus aureus and Escherichia coli. So amoxicillin-clavulanate works against GAS, but it should not be used because of what it does to the rest of the flora. Even so, in a 2023 nationwide Italian survey of 107 pediatric emergency units, about 25% of units prescribed it for GAS pharyngitis.
Third-generation cephalosporins as a routine choice follow the same logic. They were prescribed in roughly 28% of pharyngitis cases in Italian pediatric primary care. Their spectrum resembles that of amoxicillin-clavulanate, which is unnecessarily broad for a penicillin-susceptible organism.
Macrolides differ, because macrolide-resistant GAS exists. Its prevalence varies by region and period. Recent Italian estimates put macrolide resistance at up to about 18%, and earlier Italian surveys reported rates as high as 30% to 40% in some periods and centres. A macrolide is therefore a weaker choice than penicillin, reserved for children who cannot safely receive a β-lactam.
A last group is considered separately. Antibiotics for non-streptococcal bacterial pharyngotonsillitis, meaning a swab growing Fusobacterium, other anaerobes or Staphylococcus aureus, are not recommended in previously healthy children. In that group the illness is self-limiting, and antibiotics do not meaningfully change symptoms or complications. A child with an underlying condition in whom such a decision is considered is a case for specialist advice.
What if the child is still febrile, or the infection returns?
When treatment seems to fail, resistance is the wrong first thought. Suppose a child was given a broad β-lactam, typically amoxicillin-clavulanate, and is still febrile after three days. The question is not which resistant GAS strain this is, because GAS does not resist amoxicillin. The differential is:
- the illness was never bacterial, since most pharyngitis is viral and antibiotics do not treat it;
- intracellular and atypical bacteria: β-lactams act on the bacterial cell wall, which Mycoplasma does not have, and they penetrate cells poorly, so Mycoplasma pneumoniae and Chlamydia species are not covered. In children these are treated with macrolides; tetracyclines are age-restricted and fluoroquinolones are not routine pediatric drugs;
- methicillin-resistant Staphylococcus aureus, which amoxicillin-clavulanate does not cover;
- Pseudomonas aeruginosa and, rarely, fungal infection, particularly in an immunocompromised child.
The reasoning step is the same each time: when a cell-wall antibiotic fails, think of organisms with no cell wall to attack, or that sit where the drug does not reach.
The same logic applies to apparent recurrences of GAS pharyngitis after amoxicillin. Most are not resistant GAS. Three explanations should be considered first: non-adherence to the ten-day course; reinfection from a household contact; and carriage, rather than true relapse, in a child with an unrelated viral illness. A proposed explanation, called indirect pathogenicity, is that the throat is co-colonised by Staphylococcus aureus or Haemophilus influenzae producing β-lactamases in the immediate environment. These would inactivate amoxicillin before it reaches GAS in the tonsillar crypts. The organism was never resistant; the drug was destroyed around it. The three explanations above are at least as common in practice as indirect pathogenicity.
If a relapse needs treatment, the options are those that survive β-lactamase activity: the β-lactamase-stable oral cephalosporins cefaclor and cefprozil, with cefuroxime axetil a further alternative. A five-day course of cefaclor was compared with ten days of amoxicillin, with comparable clinical results, in a single small trial. A first-generation cephalosporin such as cephalexin is active against GAS and is among the alternatives for penicillin-allergic patients. It is broader than penicillin, so it is not the first choice in a child who can take amoxicillin.
A Cochrane review of antibiotic choices for recurrent pharyngotonsillitis could reach no conclusion, because no trial met its inclusion criteria. The Italian consensus recommends antibiotic therapy in relapsing disease only for children being considered for tonsillectomy. The regimens are amoxicillin-clavulanate, clindamycin, or amoxicillin plus rifampicin during the final four days, to try to avoid surgery. Tonsillectomy remains the only intervention proven to reduce the frequency of episodes, and it carries its own risks.
What about penicillin allergy?
When a β-lactam seems to be off the table, how is the alternative chosen? First, how often is the allergy real? Proven penicillin allergy is uncommon, with a prevalence on the order of 0.7% to 1%, and anaphylaxis is far rarer still. Most children labelled penicillin-allergic are not allergic. Maculopapular rashes, urticaria and vomiting are common features of the viral infections for which the antibiotic was prescribed.
The decision should therefore be made by risk stratification rather than reflex.
- Low risk of a severe reaction (for example a delayed maculopapular rash): a third-generation cephalosporin for 5 days, the recommended alternative in the Italian consensus. Cross-reactivity between penicillins and cephalosporins is low when the original reaction was not immediate.
- High risk (immediate type I features such as anaphylaxis, angioedema or urticaria within an hour): a macrolide, accepting that a proportion of strains will be macrolide-resistant.
The macrolide and the other options are dosed as follows:
- azithromycin 12 mg/kg once daily for 5 days, or 20 mg/kg once daily for 3 days, maximum 500 mg per day;
- clarithromycin 15 mg/kg/day in divided doses for 10 days;
- clindamycin 7 mg/kg/dose three times daily for 10 days.
An allergy work-up is the definitive answer. A child given an alternative for years without a work-up may be taking a worse antibiotic forever for a reaction that never happened.
Supportive care, contagion and follow-up
The drug is chosen and the course is run. What else does the child need? Only paracetamol or ibuprofen is recommended for the pain and fever of acute pharyngitis in children, with adequate fluids. Systemic corticosteroids and topical anaesthetics are not recommended for uncomplicated GAS pharyngitis, because they do not alter the course and add adverse effects. Topical anaesthetics also carry a risk of toxicity in young children.
The bacterial load in the pharynx drops substantially within the first 24 hours of treatment, but children are most contagious in the days before and immediately after the illness becomes apparent. Rules on how long a child stays at home or away from school are administrative rather than microbiological, and they differ between countries and between regions of the same country. Many services ask for at least 24 to 48 hours of effective antibiotic therapy and clinical improvement before return, and the local rule should be followed.
A test of cure is not recommended. A routine follow-up swab after adequate treatment adds cost and confusion without changing management.
There is no licensed vaccine against group A Streptococcus. Pharyngitis therefore remains an antibiotic-stewardship problem rather than a vaccination problem, and streptococcal pharyngitis, scarlet fever and their complications are still prevented by diagnosis and a correctly chosen antibiotic. For many other serious childhood infections, prevention comes first, through a routine schedule of vaccines matched to each pathogen’s biology. If no vaccine can prevent GAS, how is a vaccine built for the infections that can be prevented, and why does each pathogen need a different kind?