What does GAS need to do to make a child ill?
Streptococcus pyogenes, or group A Streptococcus (GAS), is a Gram-positive coccus growing in chains. Most sore throats in children are viral, but GAS accounts for roughly 90% of bacterial pharyngitis, so it is the bacterium that dominates the bacterial differential.
Its importance is out of proportion to its share, because it causes two kinds of complication, and antibiotics remove only one of them. Why only one? The answer comes from the organism’s equipment, so the equipment comes first.
GAS colonises the throat or the skin, defends itself against innate and adaptive immunity, and then spreads. It carries one set of tools for each job, and the virulence factors fall into three groups: surface defences, toxins and spreading enzymes. The same organism, using these tools at different sites, produces very different illnesses: pharyngitis, scarlet fever, impetigo, cellulitis, necrotising fasciitis, toxic shock and puerperal sepsis. Most GAS disease, however, is mucosal and self-limiting.
Both kinds of complication make sense from this equipment: from what lets the organism colonise the throat, evade the immune system and spread, and from which of its products leave an antibody response.
How does it avoid being eaten?
Phagocytes have to recognise a bacterium and then engulf it. The surface defences attack exactly those steps: they keep the organism from being recognised and engulfed.
The first is the capsule, made of hyaluronic acid. This polymer resembles host connective tissue, so the immune system recognises it poorly. Together with the M protein, the capsule gives GAS an antiphagocytic surface.
The M protein is encoded at the emm locus and is type-specific. It is made of two polypeptide chains in an α-helix. Its C-terminal end is conserved and anchored to the cytoplasmic membrane, while its N-terminal end is variable. The M protein is a protective antigen, but only for its own type. Re-infection with the same M type gives type-specific immunity, and another M type does not. This explains why immunity is type-specific: the N-terminal sequence varies so much between strains that GAS is classified into more than 200 emm types.
C5a peptidase degrades C5a, which recruits and activates phagocytes. With the call removed, the local inflammatory response is blunted.
What do its toxins do?
Surviving is not enough; the organism also damages host cells and drives inflammation. Toxins do both.
The streptococcal pyrogenic exotoxins (SPE), also called erythrogenic toxins, are best known as SPE-A and SPE-C. They are encoded by bacteriophages carried by lysogenic strains.
The SPEs act as superantigens. They bypass normal antigen presentation and trigger mass cytokine release. This cytokine surge reaches the skin as the erythema of scarlet fever, the same organism presenting with a rash. When the surge is systemic, it contributes to shock and organ failure.
The streptolysins are the other toxins, and they differ in one way that matters later.
- Streptolysin S is oxygen-stable and serum-soluble. It lyses red cells, leucocytes and platelets, and it stimulates the release of lysosomal enzymes. It is not immunogenic, so it leaves no antibody trace.
- Streptolysin O is oxygen-labile. It is cytolytic for leucocytes, platelets and erythrocytes. It is immunogenic, and the antibodies against it are what the antistreptolysin O titer (ASO, also called TAS) measures.
How does it move through tissue?
The toxins damage, but the organism also has to get through clots, pus and tissue. Spreading enzymes break these down so it can move through them.
- Streptokinase exists in two forms that lyse blood clots, and it contributes to the rapid tissue spread of the organism.
- The deoxyribonucleases (DNase A–D) are not cytolytic. They depolymerise free DNA in pus, which promotes spread. They also induce antibody production.
- Hyaluronidase degrades the hyaluronic acid of the extracellular matrix, which enables spread.
What traces does it leave, and why does serology work?
Serology follows from the differences in immunogenicity. Only products that stimulate antibodies can be measured afterwards.
Antistreptolysin O rises after pharyngitis and is the classic marker of recent streptococcal infection. The anti-DNase B titer and anti-streptokinase are alternatives. They are particularly useful after skin infection, where the ASO response is weaker. And streptolysin S, the tissue-damaging toxin, leaves no antibody at all. Serology therefore measures the footprint of the infection, not the harm.
Why do the complications split into two kinds?
The antibody trace that can be measured can also do harm, and this is the key to the split. GAS complications divide by mechanism into suppurative and non-suppurative.
Suppurative complications come from the organism itself, by direct spread or by seeding through the bloodstream. They are:
- peritonsillar cellulitis or abscess
- retropharyngeal abscess
- cervical lymphadenitis
- otitis media
- sinusitis
- meningitis
- brain abscess
Non-suppurative complications come from the antibody response to the organism, so they appear weeks later. They are acute rheumatic fever and acute post-streptococcal glomerulonephritis. This is why antibiotics remove only one kind: the first comes from the organism, which can be killed, and the second from the antibody response to the organism.
Why do the two non-suppurative complications arrive weeks later?
Antibodies take time to form, so the damage appears after the throat may already look well. Acute rheumatic fever appears roughly 1–5 weeks after the sore throat. Acute post-streptococcal glomerulonephritis appears roughly 10 days after pharyngitis, and up to 3 weeks after a skin infection.
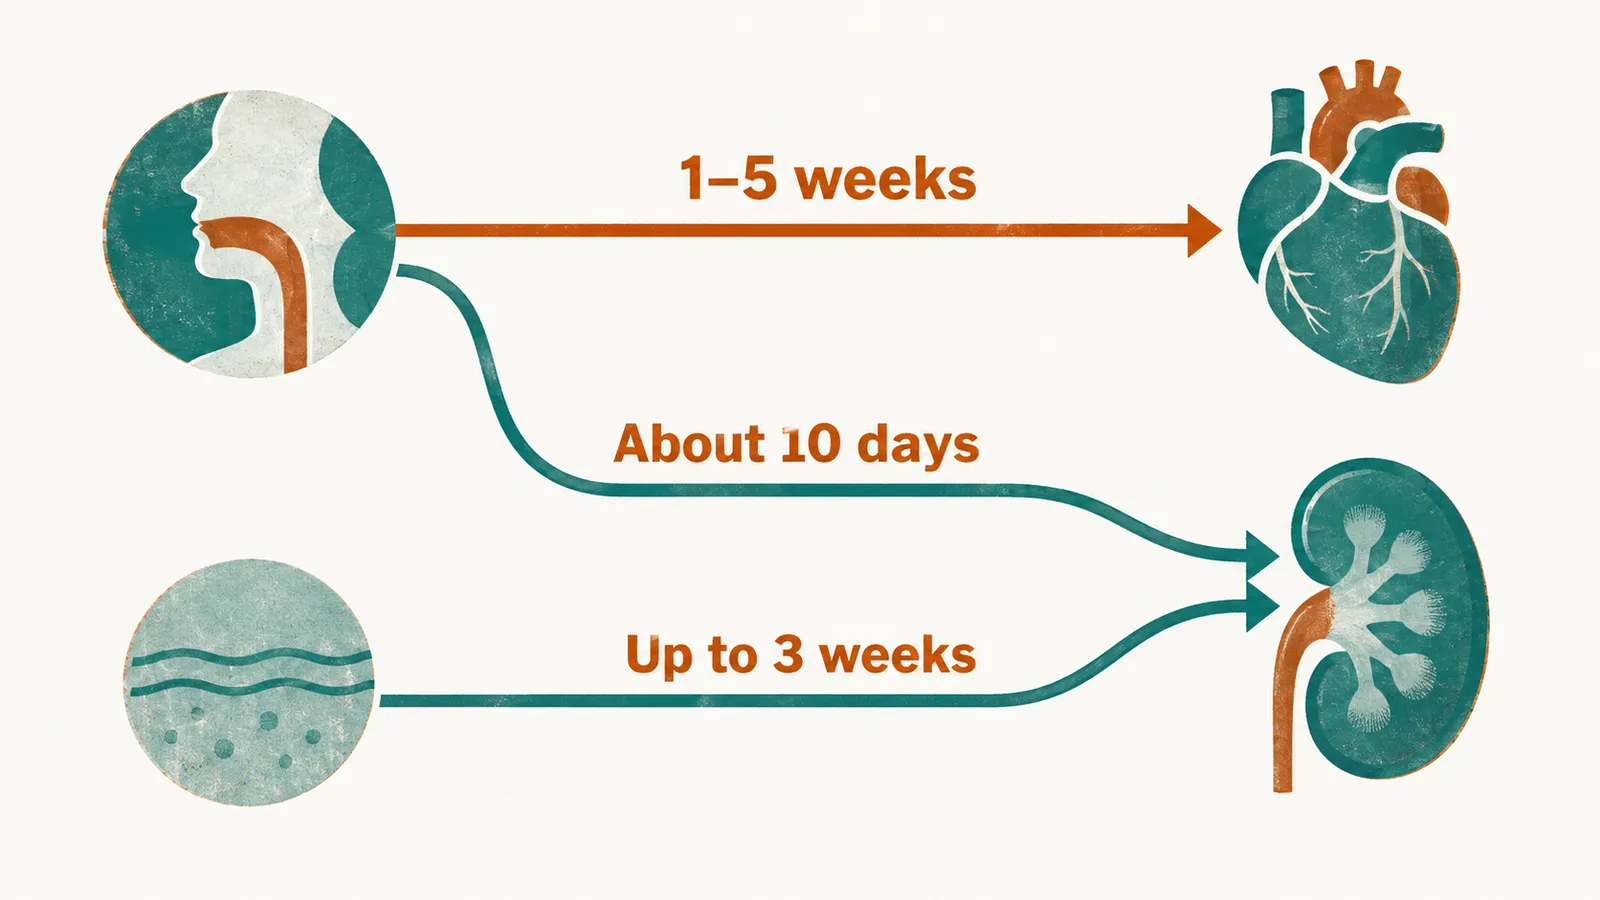
Both rest on molecular mimicry, a widely accepted hypothesis. Streptococcal antigens resemble proteins of the human heart and kidney, so antibodies raised against the bacterium also recognise the patient’s own tissue.
The rheumatic consequence is the reason a sore throat is treated at all in a high-income setting, where the disease looks trivial. It is also the reason the ten-day course exists. The Complications and Pitfalls of Childhood Exanthems note follows rheumatic fever and glomerulonephritis in more detail.
What does the invasive form look like?
Most GAS disease stays on the mucosa. The organism can invade and produce sepsis, necrotising fasciitis or streptococcal toxic shock syndrome, which carries a high mortality. The superantigen exotoxins contribute to the shock and organ failure.
In 2022 WHO and ECDC reported an unseasonal increase in invasive GAS disease and scarlet fever in children under 10 years. It was reported across several European countries, including France, Ireland, the Netherlands, Sweden and the United Kingdom, with a number of deaths. The increase followed a period of unusually low transmission. The organisms involved have remained susceptible to penicillin. Surveillance of circulating emm types continues, because the emm type identifies the strain.
What can the bedside tell us?
Virulence factors, antibody responses and emm types are invisible at the bedside. The signs of GAS pharyngitis overlap with those of adenovirus and Epstein–Barr virus, so establishing that the organism is present is a microbiological question, and a throat swab is what answers it. How, then, is the swab taken, and how far can a swab and a rapid test be trusted?