
Acromegaly causes harm in two ways. The tumor that secretes GH produces local effects of its own, and chronic high GH and IGF-1 (insulin-like growth factor 1) affect many organs. The clinical picture is therefore broad, and that is why early diagnosis matters.
The pituitary sits in the sella, a small bony cup. The optic nerves cross above it, cranial nerves III, IV and VI run at its sides, and normal pituitary tissue and the stalk lie inside it. A GH-secreting adenoma is a tumor in that cup. The local effects appear once the tumor is big. The body-wide effects build slowly over years, because GH and IGF-1 keep stimulating growth of soft tissue, cartilage, bone, skin and some organs. The metabolic changes come from a different action, GH opposing insulin.
The tumor comes first, because it sits in a small space.
What does the tumor do to what lies around it?
In most cases a macroadenoma is present at diagnosis, meaning an adenoma greater than 10 mm. A tumor of that size growing in a fixed bony cup presses on what lies around it, so local mass effects are common. They can include:
- headache
- visual disturbances, which fit the optic nerves lying above the sella
- hydrocephalus
- ophthalmoplegia
- cranial nerve palsies, which fit cranial nerves III, IV and VI running beside the sella
The tumor also squeezes the normal gland, so the same lesions can cause insufficiency of other anterior pituitary hormones: hypothyroidism in 40% of cases, adrenal insufficiency and hypogonadism. Hypogonadism can occur due to either hyperprolactinemia or gonadotropin deficiency. Raised prolactin can come from compression of the stalk or from a tumor that also secretes prolactin. Hypogonadism presents with oligo/amenorrhea, decreased libido and infertility.
The hormone’s own effects begin with how the patient looks.
Why do the face, hands and feet change?
Soft tissue and skeletal changes that alter the appearance are the most characteristic changes of acromegaly, and they are the ones that mostly lead to diagnosis. They develop slowly, so the patient and those around them tend to adapt to them.
In the face there is coarsening of the features, with frontal bossing, broadening of the nose, thickening of the lips and prominence of the superior ridge of the orbits. The jaw also overgrows and lengthens (prognathism), so the teeth spread apart, giving interdental separation, and the temporomandibular joint can become painful. Macroglossia can extend to the vocal cords; vocal cord involvement makes the voice hollow and deep, although the sources describe voice change as debated.
The hands and feet enlarge. Patients notice a change in ring size or shoe size, which gives an objective measure of the growth.
The skin changes in the same way.
What happens to the skin?
Skin manifestations are due to increased GAG (glycosaminoglycan) deposition in dermal tissue and increased proliferation of fibroblasts, both caused by high GH and IGF-1. The extra matrix is accompanied by oedema.
The manifestations are oily skin, hypertrichosis and psoriasis. Oily skin is one of the most sensitive signs of GH excess. In severe cases, acanthosis nigricans and cutis verticis gyrata appear; acanthosis nigricans in severe cases is thought to come from extra extracellular matrix with oedema. Skin tags are another reported change, and it is unclear whether GH and IGF-1 cause them directly or whether they follow insulin resistance and dyslipidemia.
Bone and joints respond to GH and IGF-1 too.
What happens to bone and joints?
Skeletal changes are not made only by the direct effect of GH and IGF-1. Diabetes caused by acromegaly also contributes, and hypogonadism can even contribute to bone changes.
The effect of GH on bone is mediated by IGF-1. The main effect of GH on bone is bone resorption, so reduction of bone density is common. It is most commonly seen as vertebral fracture, which occurs in as many as 60% of cases. The effect on bone health is described as complex, and results vary by skeletal site.
Arthropathy (joint disease) is an important complaint, and it can be arthralgia or arthritis. It changes chronologically over the disease course. GH and IGF-1 stimulate growth of articular cartilage and the ligaments around the joints. Chronic GH excess and the local effect of IGF-1 on articular spaces first lead to joint limitation caused by soft tissue expansion, and this is followed by joint damage, with narrowing of the joint space and osteophytes.
All of this is the adult picture; the age at which the excess starts changes it.
What if the excess begins in childhood?
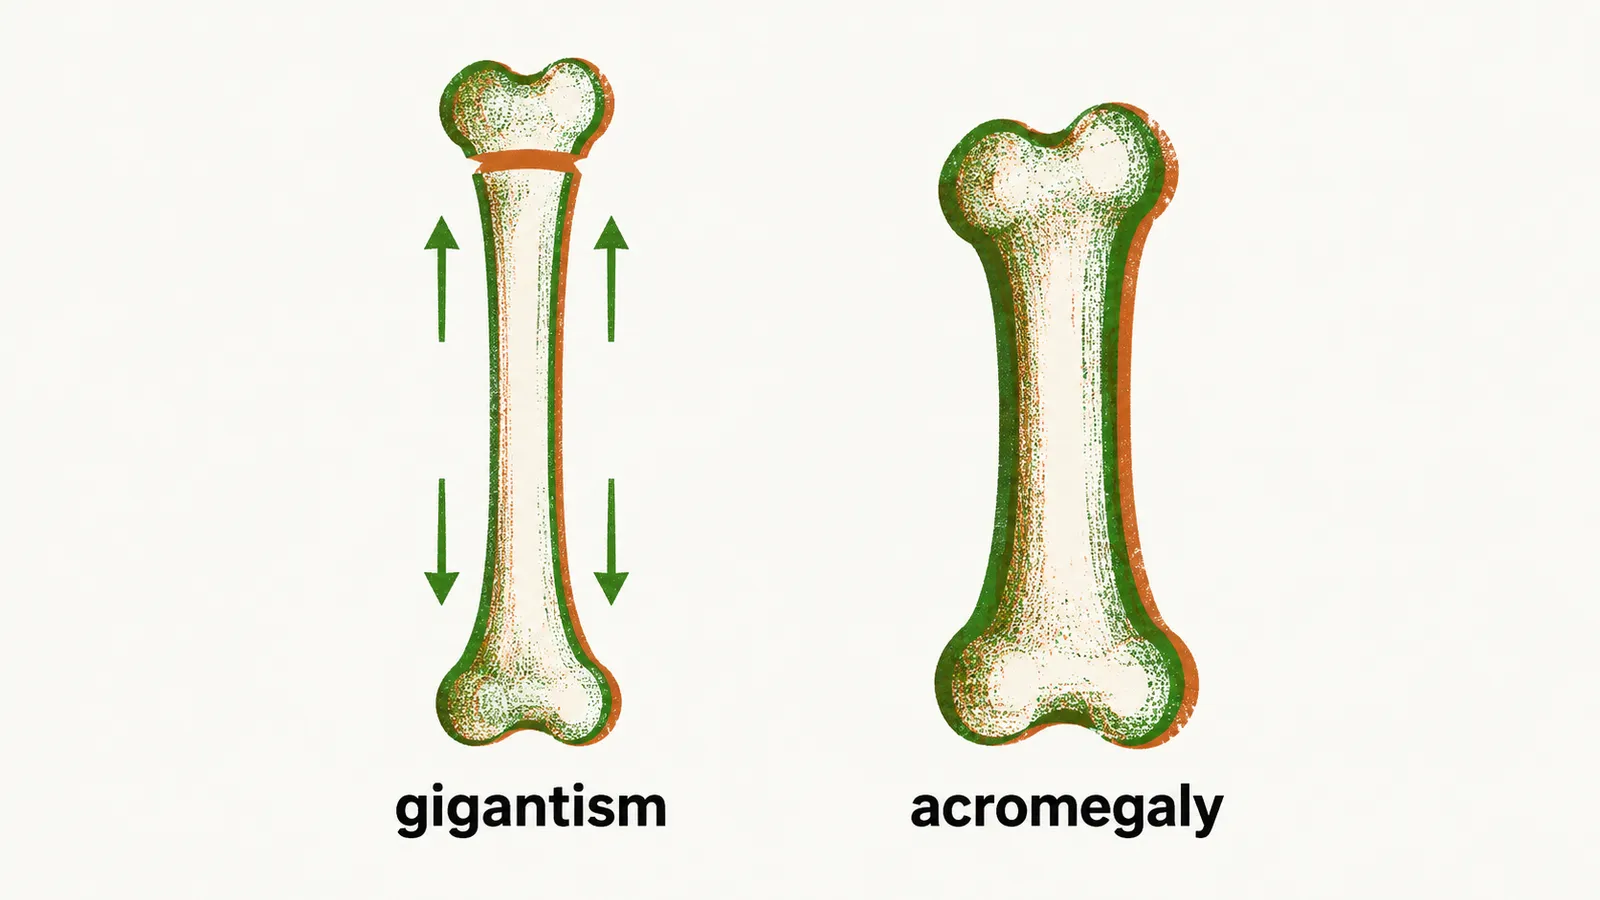
The skeletal changes above are those of adult acromegaly. When the excess begins earlier, the result depends on the growth plates. In children, GH or IGF-1 hypersecretion before closure of the epiphyseal plates can lead to gigantism, because the long bones can still lengthen. In adults the same excess is called acromegaly.
Studies show microduplications in Xq26 chromosome related to gigantism with early onset before age 5 years. GPR101 is a gene, and it is a G protein-coupled receptor (GPCR) encoded in GH-secreting cells of the pituitary gland. Some mutations identified in GPR101 increase GH production in patients with acromegaly. The genetic work is taught in Pathophysiology of Growth Hormone Hypersecretion.
The same tissue overgrowth narrows the airway.
Why does sleep apnea occur?
Sleep apnea syndrome (SAS) is very common in acromegaly, with a prevalence of about 40–80% of these patients. Pathological changes of the craniofacial skeleton play a role, and so does thickening of the soft tissues of the pharynx, which narrow the upper airway. The main cause of SAS is soft tissue thickening. SAS persisting after treatment has been reported in more than 40% of cases, which fits a cause with several contributors.
The hormone also reaches muscle and nerve.
What happens to muscle, nerves and sensation?
In more than 90% of patients, muscle pain is reported during the course of acromegaly as a dominant symptom. Studies show that GH excess mainly causes hypertrophy of type 1 (slow-twitching) muscle fibers, with a variable effect on type 2 fibers. Patients have faster muscle fatigue, especially during fast movements, which is thought to relate to the predominance of type 1 changes. Old studies report proximal muscle weakness in acromegaly; a recent study reported otherwise, and pain may interfere with the assessment.
There is no evidence of CNS involvement, but the peripheral nervous system (PNS) is involved. Carpal tunnel syndrome is reported in more than 60% of cases. In acromegaly it is caused by swelling of the nerve itself, not by compression from other contents of the carpal tunnel, and more than 80% of acromegaly patients suffer median nerve neuropathy. Altered cardiac autonomic function has been described. Restless leg syndrome has also been described, in 20% of cases.
GH does not only cause growth; it also opposes insulin.
What does GH do to glucose and lipids?
GH is a potent antagonist of insulin, and excess GH also increases resistance to insulin in cells. Frank diabetes is present in 50% of acromegaly cases.
GH also affects the lipid profile: it decreases HDL and increases LDL and triglycerides. These lipid abnormalities may accompany insulin resistance.
Growth also reaches the organs.
Which organs enlarge, and does cancer risk rise?
Several organs enlarge in acromegaly, from the same growth stimulus. The thyroid is most commonly affected. Multinodular goiter (enlarged thyroid with several nodules) has been reported in some studies in up to 80% of cases, potentially as a result of the stimulating effect of IGF-1 on thyroid cell growth. The goiter is mostly non-toxic; it is toxic in only 15% of cases. The nodules are mostly benign; carcinoma occurs in only 3% of cases. The duration of acromegaly correlates with both the incidence and the volume of the goiter. The prostate, salivary glands, heart, liver and spleen can also enlarge. Renal cyst formation can occur, and so can polycystic ovaries.
An increased incidence of neoplastic tumors has been observed in acromegalic patients, but the findings are conflicting. It is not proved whether this follows the same trend as neoplastic disorders in general or is due to GH hypersecretion. A proposed mechanism is that IGF-1 promotes proliferation and inhibits apoptosis. The trend of increase is very similar to the increase of cancer in the general population with increasing age.
Colon polyps and cancer are the most discussed. Colon adenoma in acromegaly differs from that in the general population: the adenomas tend to be more in the ascending colon and have more dysplasia. Patients with acromegaly are considered a high-risk population for colon cancer, and frequent colonoscopy screening is suggested. Gastrointestinal tumors include colon polyps, colon adenocarcinoma and gastric adenocarcinoma. Breast cancer, bronchial tumors, multiple myeloma, thyroid cancer and renal cancer have also been described.
The reported findings, system by system.
Summary by system
| System | Reported manifestations |
|---|---|
| Tumor-related local effects | headache; visual field defects; cranial nerve abnormalities; hydrocephalus; temporal lobe epilepsy; hyperprolactinemia; hypopituitarism |
| Skin | hyperhidrosis; oily skin; skin tags; hypertrichosis; acanthosis; cutis verticis gyrata |
| Soft tissue | acral enlargement; change in voice quality (larynx hypertrophy); visceromegaly (thyroid, prostate, liver, salivary glands) |
| Orofacial | prognathism; frontal prominence; dental malocclusion (interdental diathesis); TMJ (temporomandibular joint) pain; gingival enlargement; macroglossia; parotid hypertrophy |
| Musculoskeletal | vertebral deformities; kyphosis; arthralgia and arthritis; myopathy; degenerative arthropathy; calcific discopathy; hypermobility |
| Endocrine and metabolic | hypogonadism; PCOS (polycystic ovary syndrome); DM (diabetes mellitus), insulin resistance; hypertriglyceridemia; erectile dysfunction |
| Hematological | increased thrombosis risk |
| Ocular | increased risk of diabetic retinopathy; extraocular myopathy; glaucoma; epiphora |
| Cardiac | HT (hypertension); cardiomyopathy; valvular heart disease; arrhythmia; heart failure |
| Neurological | peripheral nerve abnormalities; autonomic dysregulation; lumbar canal stenosis; narcolepsy; restless leg syndrome |
| Pulmonary | sleep apnea; restrictive lung disease; subclinical hypoxemia |
| Neoplastic | colon polyps; thyroid cancer; breast cancer |
| Renal | increased GFR (glomerular filtration rate); hypercalciuria; glomerulosclerosis |
| Psychiatric | depression |
The cardiac group belongs to the system where GH hypersecretion has the most significant clinical impact. The heart is where GH excess matters most, so what do GH and IGF-1 do to the heart and vessels? Cardiovascular Complications of Acromegaly answers that.