
Acromegaly is suspected from clinical features, confirmed biochemically with IGF-1 and the oral glucose tolerance test (OGTT), and followed by imaging of the pituitary. Treatment is mainly surgical resection of the adenoma, and radiotherapy and drug therapy are further options. The diagnosis works in two steps. The first asks whether the body is exposed to too much GH. The second asks where the excess comes from and what it has already done. Treatment follows the same logic: the adenoma is the source, so it is removed first, and what is left is controlled by other means.
When should acromegaly be suspected?
The diagnostic panel is started in two main clinical scenarios.
In the first, the clinical manifestations are evident and overt: acral facial features, enlargement of the hands and feet, and dental diastema, meaning interdental separation. These features are common in overt acromegaly.
In the second, the changes are intermediate and could be associated with acromegaly. The disease is still in an early stage here, and a clinical diagnosis at this stage would prevent many future complications. A disease that creeps in slowly may first show as a common complaint, so the clinician has to think of it. Patients in this scenario mostly manifest one or more of these:
- hypertension
- carpal tunnel syndrome
- sleep apnea
- hyperhidrosis
- debilitating arthralgia
- refractory headache
- amenorrhea
The change is slow, so neither the patient nor the family may notice it from day to day. The patient can therefore be asked to bring photographs from different years. The chronic, long-term effect of GH on the body may show as an obvious change in face shape.
Suspicion is clinical, but proof is biochemical. The diagnosis combines clinical examination with biochemical tests.
Why is GH alone not enough, and what does IGF-1 add?
GH is released in pulses, so a single level is a snapshot: a sample taken in a trough or a peak tells little. For this reason GH cannot be used by itself to diagnose GH hypersecretion disorders. The GH level is also not correlated with disease severity.
The guideline recommends screening with IGF-1 and confirmation with the OGTT. A single IGF-1 level is the first-line biochemical test for diagnosis. IGF-1 is made continuously downstream of GH, so it is steadier than GH, tracks the average GH, and can be sampled at any time of day without fasting.
The result has to be read against norms. Plasma IGF-1 depends on physiological factors, age and gender, and on pathological factors: liver dysfunction, renal dysfunction, nutrition and diabetes mellitus (DM).
One way to get around the pulses is the GH day curve, a serial sampling for assessing GH hypersecretion. It takes 5 samples over 12 hours, and the 5 samples for mean GH are taken from an indwelling venous cannula. Averaging smooths the pulses, and the cannula prevents the effect of puncture stress during sampling.
Stress matters because GH secretion is extremely sensitive to physiological stressors such as exercise. A random GH sample can therefore be useless: normal subjects under physiological stress overlap with acromegalic patients. IGF-1 is not affected by physiological stress, so it is a better option for evaluating acromegalic patients. In acromegaly the GH level fluctuates, but IGF-1 is constantly high.
A random GH sample is useful for excluding acromegaly in only one condition: GH < 0.4 ng/ml together with a normal IGF-1 for age and sex.
IGF-1 shows that there is excess. How does one show that GH is out of control?
How does the glucose test confirm it?
Physiologically, serum GH is suppressed after glucose ingestion, most likely because glucose inhibits GHRH release and/or stimulates somatostatin. In GH hypersecretion this suppression can fail, which is consistent with an adenoma that no longer responds to the normal brake. That makes the OGTT the gold-standard diagnostic test for GH hypersecretion diseases.
The protocol runs in order:
- Give 75 g of oral glucose at 9 a.m. to a fasted patient.
- Sample GH at baseline, then 30, 60, 90 and 120 minutes after ingestion.
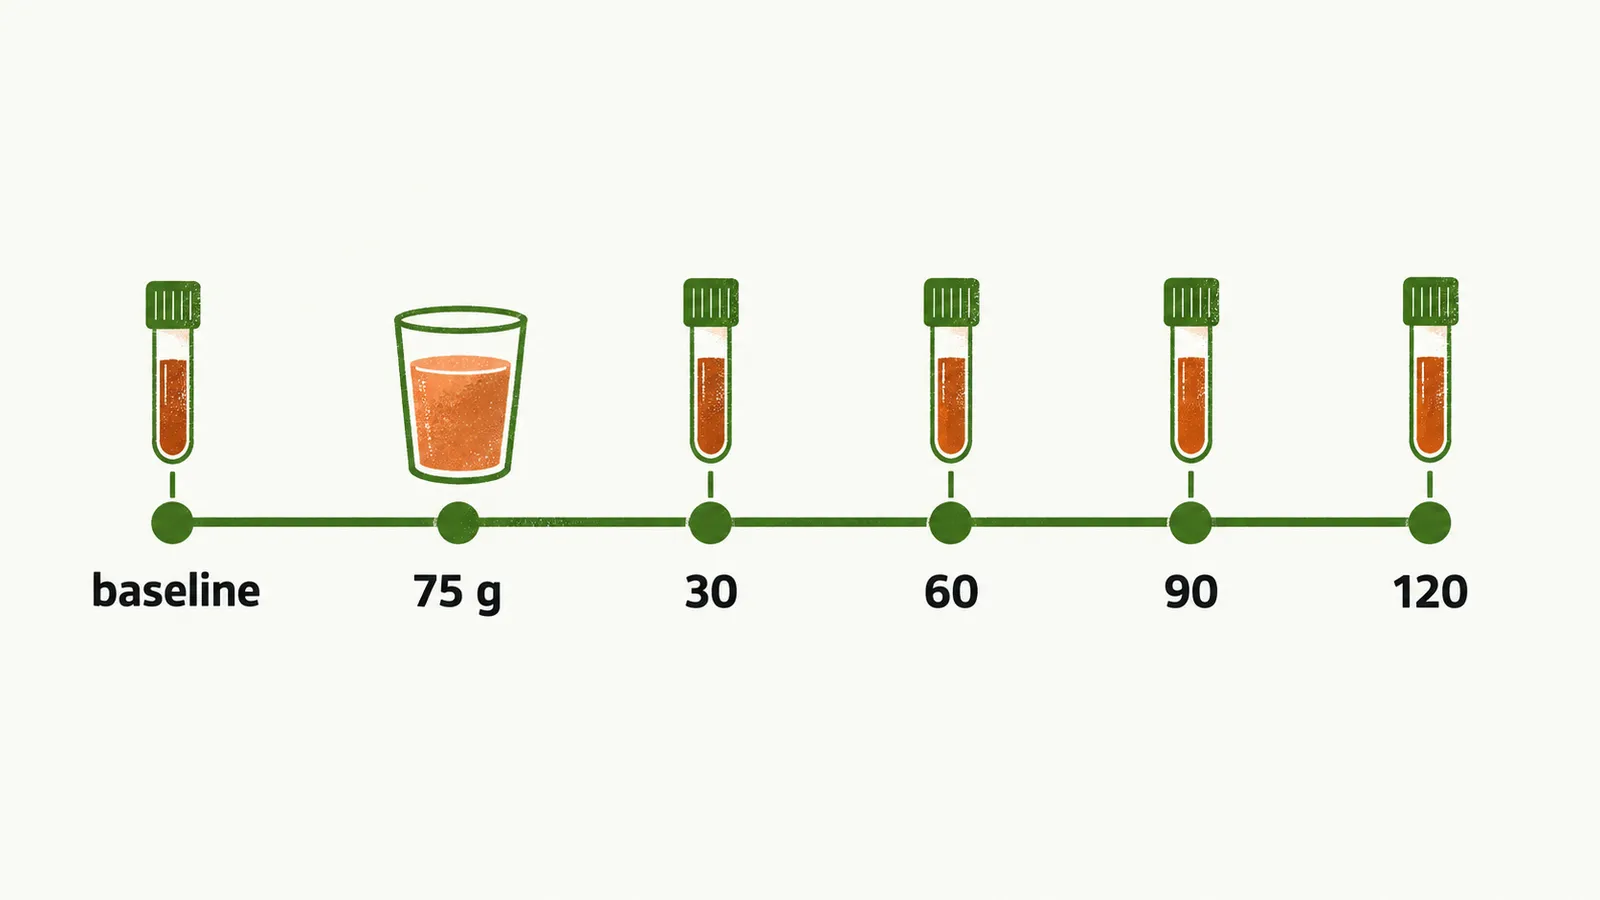
In normal subjects GH after the OGTT is undetectable, or < 0.1 ng/ml. In acromegaly patients GH remains detectable. In about 30% of cases there is a paradoxical GH increase after the OGTT. Failure to suppress GH to < 0.4 ng/ml supports the diagnosis of acromegaly.
That cut-off depends on the assay. A more sensitive assay measures lower GH, so the threshold fell. With older assays the guideline threshold for normal suppression was a GH nadir (lowest value) < 1 ng/ml, and the lower 0.4 ng/ml cutoff applies to modern, more sensitive assays. Assays are the laboratory methods used to measure GH.
The OGTT can give false positives. In these states GH can fail to suppress without acromegaly:
- stressful conditions
- DM
- cirrhosis
- adolescence
- chronic renal failure
- use of L-dopa and estrogen
- heroin addiction
IGF-1 is usually not raised in these conditions, which helps tell them from acromegaly. When the picture is still borderline, further tests exist.
Which other tests help?
Injection of TRH (thyrotrophin-releasing hormone) physiologically inhibits GH release. The TRH test uses 200 μg of intravenous TRH, with sampling at baseline, 20 and 60 minutes after the injection. It is suggested in mild acromegaly with low circulating GH, and its purpose is to confirm the diagnosis.
IGFBP3 (insulin-like growth factor binding protein 3), GHRH (growth hormone-releasing hormone) and prolactin may also be measured. GHRH measurement is useful when an ectopic source of GHRH is suspected, for example when imaging shows no pituitary adenoma.
Biochemistry says that there is excess, but not where it comes from.
What does imaging show?
Once the excess is established, imaging localises it. The optimal pituitary imaging in suspected acromegaly is MRI with gadolinium enhancement. MRI defines the tumor size and characteristics, and it defines possible invasion of surrounding structures, such as cavernous sinus invasion and suprasellar extension. The cranial nerves run beside the sella and the optic pathway lies above it, so these findings matter.
A tumor that touches the optic pathway can damage vision before the patient notices. Neuro-ophthalmological assessment is therefore done in all patients with radiological evidence of macroadenoma, especially when the tumor contacts the optic nerve. Its purpose is to assess visual complications such as optic atrophy, retinal vein engorgement and papilloedema due to compression.
The tumor that is later removed can add further information.
What does histology add?
Histology on somatotrope tumors can look at several things:
- distinguishing sparsely from densely granulated tumors by keratin staining
- the Ki-67 index
- immunohistochemistry of Pit-1, SF-1 and Tpit
- tumor response to somatostatin analogue therapy, by means of somatostatin receptors (SSTR)
The granulation pattern and the somatostatin receptors are two features that can link a tumor’s histology to its response to somatostatin analogue therapy. The normal gland also has to be checked.
What else is assessed at diagnosis?
Pituitary function is the other follow-up that matters once the diagnosis is made. A macroadenoma compresses the normal gland, so other hormones can fall. Secondary hypopituitarism mostly occurs in macroadenomatous acromegaly, in 15–20% of cases. Its forms are secondary central hypothyroidism, secondary central hypogonadism and secondary central hypoadrenalism.
Tall stature raises suspicion of acromegaly in most cases. When soft tissue and biochemical evidence are absent, the differential diagnosis is:
- Marfan syndrome
- homocystinuria
- familial trait
Complications. Acromegaly is associated with quite a lot of important comorbidities that are already present at diagnosis, because the diagnosis comes late. Therefore assessment of complications is suggested at the time the diagnosis is confirmed. Each screen looks for a complication of GH and IGF-1 excess. In the table, BP is blood pressure, OSA is obstructive sleep apnea, HbA1c is glycated hemoglobin, FBG is fasting blood glucose, US is ultrasound, DEXA is dual-energy X-ray absorptiometry, and QOL is quality of life, assessed by ACROQOL.
| Condition | Assessment | Timing |
|---|---|---|
| Hypertension | Measure BP; ambulatory BP monitoring in selected cases | 6 monthly |
| DM | HbA1c, FBG; OGTT in selected cases | At diagnosis, and 6 monthly if normal |
| OSA | Clinical evaluation and Epworth scale; polysomnography for confirmation | At diagnosis and annually |
| Cardiomyopathy | ECG; echocardiography | At diagnosis, and 3–5 yearly if normal |
| Dyslipidemia | Lipid profile | At diagnosis and 6 monthly |
| Colon polyps | Colonoscopy | At diagnosis in patients >40 years of age; then 10 yearly if normal; 3–5 yearly if a polyp is noted and IGF-1 is elevated |
| Thyroid nodules | Clinical evaluation; thyroid US guided by examination | Annually |
| Vertebral disease | Bone morphometric study using thoracic x-ray, thoracic and lumbar spine x-ray; DEXA | At diagnosis and yearly, guided by symptoms |
| Cerebral aneurysm | Cerebral MR angiography | Infrequently |
| QOL | ACROQOL | Annually |
With the problem found and mapped, how is it treated?
How is it treated?
Treatment is mainly based on surgical resection of the adenoma as first line. The second line of treatment is radiotherapy. The aim is to normalize IGF-1 and suppress GH. Uncontrolled disease drives the excess mortality of acromegaly.
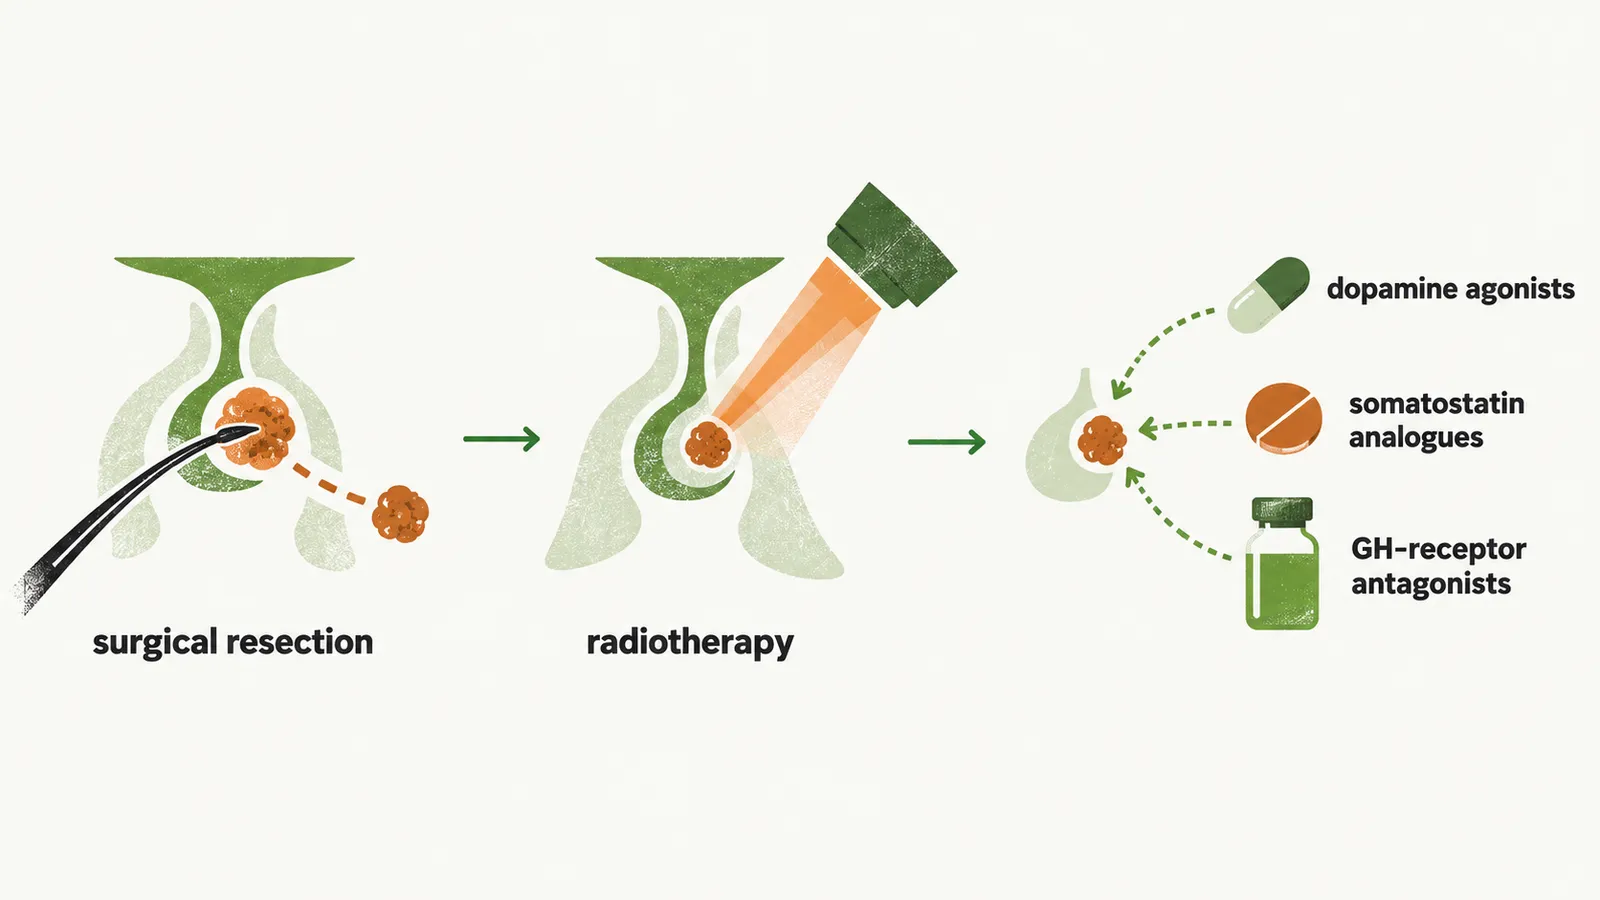
Surgery is usually done by the transsphenoidal route. The chance of remission depends on tumor size and invasiveness: the average cure rate is about 78% for microadenomas (< 1 cm) and 50% or less for macroadenomas (≥ 1 cm).
Radiotherapy has a slow effect, often taking years to bring GH and IGF-1 under control. It also carries a risk of hypopituitarism, since radiation can reach the normal gland too.
When surgery does not cure, medicine continues. The pharmacological options are:
- dopamine agonists
- somatostatin analogues
- GH-receptor antagonists
Somatostatin analogues, such as octreotide and lanreotide, imitate somatostatin and act mainly on somatostatin receptor type 2. They are the first-line medical option when surgery is not curative or not possible. As monotherapy they normalize IGF-1 in only about 40% of patients.
Pegvisomant is a GH-receptor antagonist: it blocks the receptor, so GH cannot signal and IGF-1 production falls. It is used as a second-line agent or combined with a somatostatin analogue, and the combination can normalize IGF-1 in most patients.
Dopamine agonists such as cabergoline can be used, particularly when IGF-1 is only modestly elevated.
Until IGF-1 is normal and GH suppressed, the excess continues to act on the body. What does uncontrolled excess do to a person’s health over the years?