What is growth hormone and who makes it?
Growth hormone (GH) is a 191 amino-acid hormone with two disulfide bonds, a single-chain protein hormone. It is made by the somatotrope cells of the pituitary gland. The somatotrope is the anterior pituitary cell type that makes GH.
GH has very high homology with prolactin. The two are similar proteins, and human GH can bind and activate the prolactin receptor, whereas prolactin does not do the reverse.
Somatotropes do not release GH steadily. So when is it released?
When is GH released, and why is one measurement hard to read?
GH secretion is pulsatile: it comes in bursts, 4–11 times a day, and the bursts mostly occur during the night. Between bursts, plasma GH reaches its nadir (lowest level).
This has a direct consequence. A sample taken in a trough and a sample taken on a peak can give very different numbers for the same person, so because of the bursts and nadirs a single GH measurement is difficult to interpret. That is why GH concentration is not usually used on its own as a diagnostic tool.
A hormone released in bursts needs a controller that can switch it up and down. Who controls the somatotropes?
What switches the somatotrope on and off?
Somatotropes are controlled by a balance of stimulatory and inhibitory signals, and some of these signals reach them through hypothalamic neurons. The net balance decides how much GH is released.
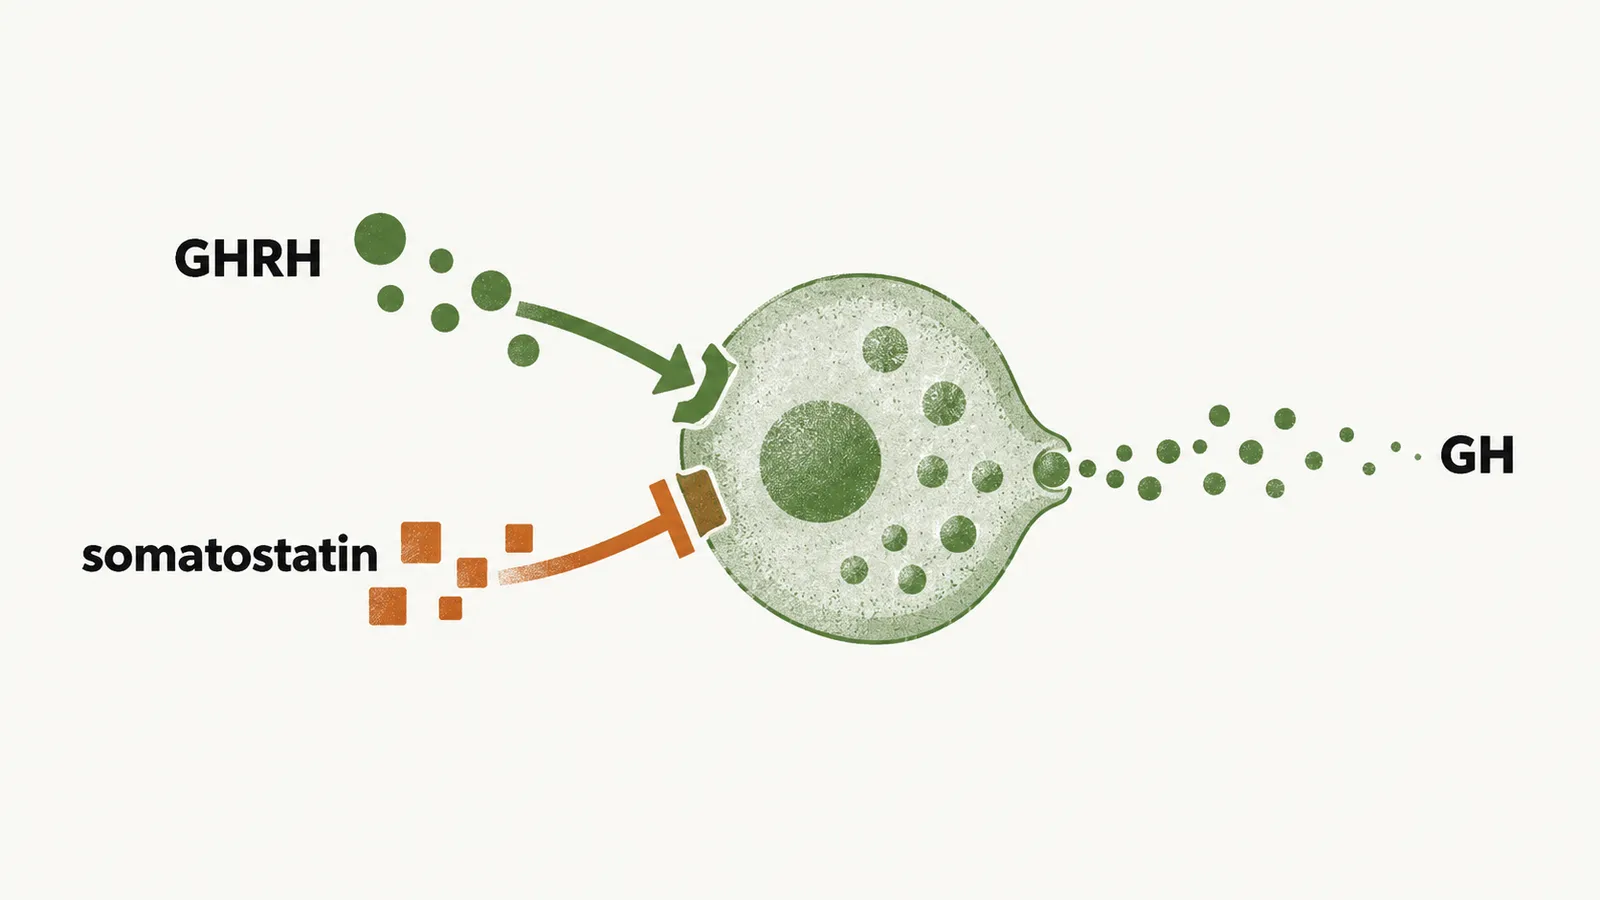
The main stimulus is growth hormone-releasing hormone (GHRH). The GHRH-secreting neurons are mostly in the arcuate nucleus and the ventromedial nucleus of the hypothalamus. The inhibitory signal is the hypothalamic peptide somatostatin, which opposes GHRH.
Other signals act on this same pair of control neurons. Dopamine, serotonin, neuropeptide Y and norepinephrine change GH release by acting on GHRH-secreting and somatostatin-secreting neurons, rather than on the pituitary directly. Their effect on GH therefore runs through the hypothalamic control.
Stimulatory signals also come from elsewhere. Ghrelin is a peptide with a potent effect on GH secretion. It is expressed mainly by the gastrointestinal tract and the central nervous system, and it is released largely in response to hunger and hypoglycemia. A hormone of the gut and brain tied to hunger thus also drives GH, which links feeding state to GH. Klotho is a further stimulatory mediator.
These signals respond to what the body is doing. So what does the body do to them?
How do energy and other hormones tune GH?
Energy state and hormonal state both have an important effect on GH secretion.
Fasting. GH rises during fasting, a rise attributed to neuropeptide Y.
Thyroid hormone. Children with hypothyroidism have lower GH and IGF-1 levels. GH supports the growth of almost all tissues, in part through IGF-1, so less of both can contribute to short stature.
Glucocorticoids. High glucocorticoids suppress GH secretion. The same growth logic applies: children with Cushing disease grow poorly because of GH suppression by high glucocorticoids.
Glucose. Blood glucose acts in both directions on GH.
- Insulin-induced hypoglycemia potently provokes GH secretion. The increase is caused by inhibition of somatostatin release from the hypothalamus. This fits with the fact that GH raises blood glucose by acting on the liver and by mobilising fat, so a rise in GH counters low glucose. That reading is an inference, not a stated mechanism.
- Acute hyperglycemia produces a delayed GH increase. A healthy person can respond to hyperglycemia in two ways: inhibition of GH secretion from the pituitary, and an increase in GHRH release from the hypothalamus. The increase in GHRH release is the likely cause of the delayed GH rise.
Amino acids. High amino acids induce GH secretion. One way to frame this is that GH increases amino acid uptake and is anabolic, and a high-protein state is when building is possible. This is a framing, not a proven mechanism.
Free fatty acids. High non-esterified free fatty acids (FFA) suppress GH secretion. GH stimulates lipolysis, so free fatty acids are a product of GH action. This fits a loop in which a metabolic product of GH dampens GH, but it is a reading, not the established mechanism.
The factors that raise or lower GH, physiological and pathological, are gathered here as they tune the same hypothalamic control.
| Increase GH secretion | Reduce GH levels | |
|---|---|---|
| Physiological | Sleep, fasting, stress, exercise, hypoglycemia, dopamine, increased amino acids (i.e., a high-protein meal), reduced free fatty acids, glucagon, testosterone and estradiol | Overeating, obesity, aging, increased IGF-1 |
| Pathological | Acute glucocorticoid excess, type 1 DM, renal failure, acute use of opioids, anorexia, depression, cirrhosis | Chronic excess cortisol/glucocorticoids, hyperthyroidism, type 2 DM |
Once GH is out, how does a cell hear it?
How does a cell sense GH?
GH acts through the growth hormone receptor (GHR), which is widely expressed in the body. That fits a hormone that acts on almost all tissues.
In plasma, GH is carried by a specific protein, GHBP (growth hormone-binding protein). GHBP comprises the extracellular portion of the GHR. This matches how it arises: the soluble binding protein is made when the outer domain of the receptor is cleaved off.
GHR is a tyrosine kinase receptor, with a refinement: the receptor itself has no kinase domain in its tail, and a kinase partner, JAK2, does the phosphorylating.
GHR signals only after dimerization. For activation, GH has to attach at the same time to two GHR molecules, forming a dimerized molecule. One GH molecule has two binding sites and bridges two receptor molecules, and the dimer is the signalling unit. That is why one GH must meet two receptors.
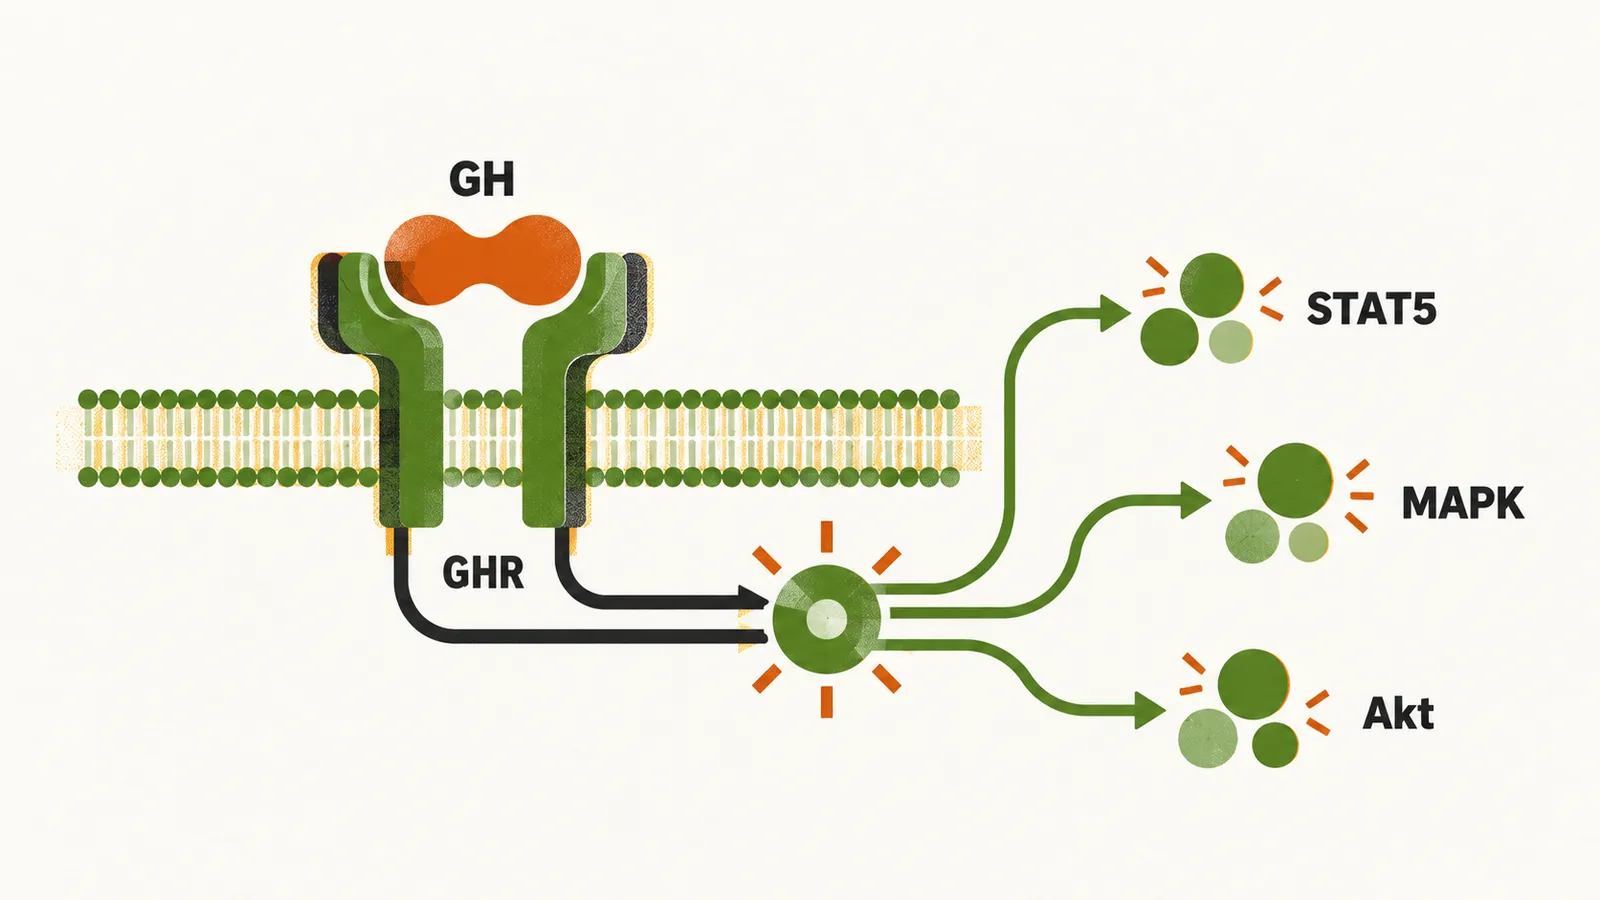
Once GHR has dimerized, several intracellular messengers are activated:
- STAT5, STAT3 and STAT1
- SRC, which activates MAPK
- IRS, which leads to PI3K and Akt
STAT5 is a key GH signal transducer, and STAT5B is a key mediator of GH-induced IGF-1 expression.
What does this signal produce?
What does GH make, and how does that come back to the pituitary?
IGF-1 is one of the major cell products made because of the effect of GH on target cells. IGF-1 was classically believed to be made by the liver: GH induces the liver to release IGF-1, which then acts as a hormone on bone, muscle and other tissues. IGF-1 is now known to be made in paracrine and autocrine ways as well. Even so, IGF-1 in the body is mainly made by the liver. Liver IGF-1 production depends on age, nutritional status, insulin level and the GH level.
IGF-1 acts through its specific receptor, which is very similar to the insulin tyrosine kinase receptor. IGF-1 has several physiological effects, most importantly induction of proliferation and inhibition of apoptosis. This is the link from one hormone to tissue growth.
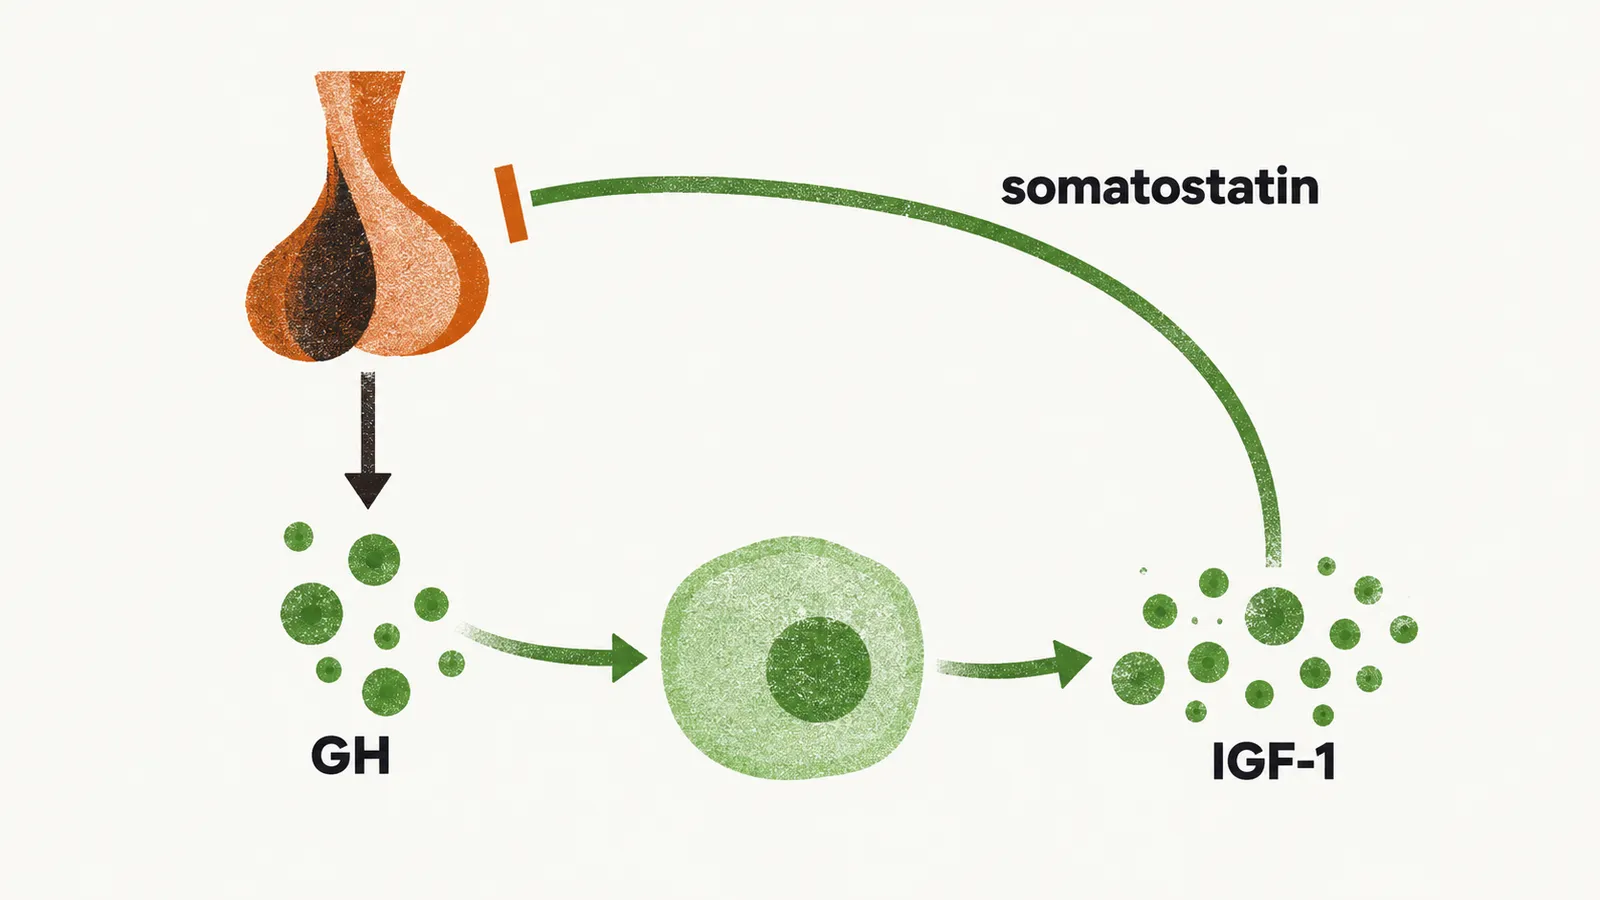
IGF-1 also has an important negative feedback on GH secretion: a rising IGF-1 restrains further GH release. In healthy men, infusing IGF-1 suppressed GH, and the pattern is most compatible with IGF-1 stimulating hypothalamic somatostatin, which is a proposed explanation. So the axis is a loop: GH makes IGF-1, and IGF-1 restrains GH.
If a signal that restrains GH is built into the axis, what makes GH and IGF-1 stay high without letting up?