Where does the excess growth hormone come from?
The somatotrope is the pituitary cell that makes GH. Normally GHRH pushes it and somatostatin holds it back. Acromegaly is what happens when GH output escapes those controls and the cell secretes too much.
Usually the escape is a tumor of the somatotrope itself. Acromegaly is usually caused by an adenoma of the somatotrope cells, the GH-producing cells of the anterior pituitary, and these GH-producing adenomas are benign lesions. They arise from cells of the Pit-1 lineage, the family of pituitary cells defined by the transcription factor Pit-1. In more than 99% of cases the excess GH comes from a benign pituitary adenoma. Acromegaly may also arise from other extra-pituitary lesions, but these are rare.
The source of the GH, the adenoma type and the molecular changes inside the adenoma explain how the disease behaves. The somatotrope adenoma is the usual cause, and the next question is what kind of cell it is.
Which pituitary cell does the tumor come from?
An adenoma is a clone of one cell, so it keeps that cell’s hormone programme. Pituitary adenomas are benign tumors derived from one of five cell types of the anterior pituitary, and the five main forms of adenoma are named after the cell of origin. Acromegaly belongs to the somatotrope lineage, the GH-producing cells.
| Cell type | Hormone |
|---|---|
| Somatotrope | GH |
| Lactotrope | Prolactin |
| Thyrotrope | TSH |
| Corticotrope | ACTH |
| Gonadotrope | FSH and LH |
Somatotrope adenomas make up about 10–15% of pituitary adenomas. Lactotrope adenomas are the most common functioning form, with a prevalence of 50–60% of all functioning pituitary adenomas. A further 15–35% of pituitary adenomas are non-functioning.
Pathologists separate the adenomas by lineage, transcription factors, hormones produced and cytokeratin pattern. The transcription factor tells which lineage a tumor belongs to, so it, rather than the symptoms, defines the family. In the table, PRL is prolactin, ER is estrogen receptor, a-SU is the alpha subunit, NOS is not otherwise specified, and b-TSH, b-FSH and b-LH are the beta subunits of TSH, FSH and LH.
| Adenoma | Transcription factors | Hormones | Cytokeratin |
|---|---|---|---|
| Densely granulated somatotroph | Pit-1 | GH, a-SU | Diffuse |
| Sparsely granulated somatotroph | Pit-1 | GH | Dot-like |
| Mammosomatotroph | Pit-1, ER | GH, PRL, a-SU | Diffuse |
| Mixed somatotroph and lactotroph | Pit-1, ER | GH, PRL, a-SU | Diffuse |
| Sparsely granulated lactotroph | Pit-1, ER | PRL (Golgi) | Diffuse |
| Densely granulated lactotroph | Pit-1, ER | PRL (diffuse) | Diffuse |
| Acidophil stem-cell | Pit-1, ER | PRL (diffuse), GH | Rare dot-like |
| Thyrotroph (TSH-producing) | Pit-1, GATA-2 | b-TSH, a-SU | Diffuse |
| Densely granulated corticotroph (ACTH-producing) | Tpit | ACTH | Diffuse |
| Sparsely granulated corticotroph | Tpit | ACTH | Diffuse |
| Crooke’s cell | Tpit | ACTH | Ring-like |
| Gonadotroph (gonadotropin-producing) | SF-1, GATA-2, ER | b-FSH, b-LH, a-SU | Diffuse |
| Plurihormonal, silent type III | Pit-1 (?), ER | Multiple hormones | Diffuse |
| Plurihormonal, unusual (NOS) | Multiple transcription factors | Multiple hormones | Not applicable |
| Hormone-negative null cell | None | None | Diffuse |
Most of the rows that make GH carry Pit-1. Which of them are associated with acromegaly?
Which kinds of somatotrope adenoma are there, and how do they differ?
Within the Pit-1 lineage the tumors still differ. The pituitary adenoma pathologies associated with acromegaly are:
- densely granulated somatotroph adenoma
- sparsely granulated somatotroph adenoma
- mixed cell somatotroph and lactotroph adenoma
- mammosomatotroph (monohormonal Pit-1 lineage) adenoma
- acidophil stem cell adenoma
- plurihormonal adenoma
- poorly differentiated Pit-1 lineage tumor
- pituitary hyperplasia
- pituitary carcinoma
Most are Pit-1 lineage tumors; hyperplasia and carcinoma are the exceptions.
Somatotrope adenomas are divided microscopically by how densely the cells are granulated. The granulation pattern predicts hormone output and the response to treatment. The reason is that the subtypes differ in what they make and in the receptors they carry.
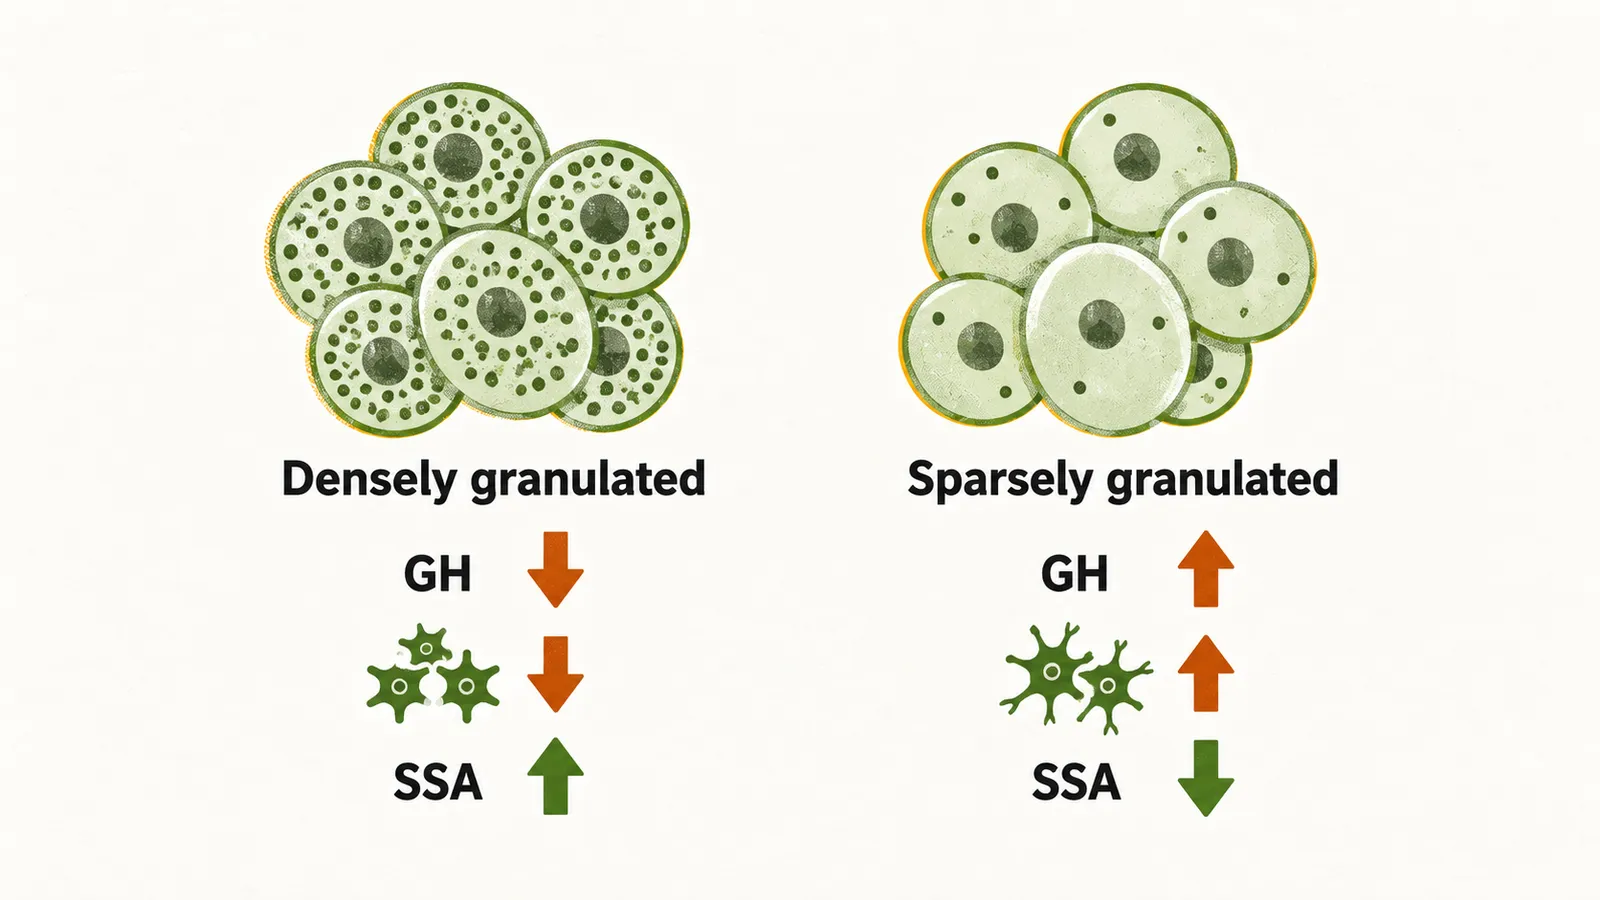
| Feature | Densely granulated (DGSA) | Sparsely granulated (SGSA) |
|---|---|---|
| Frequency | Most common form | Second most common form |
| Age and sex | More common at older ages | More prevalent in younger adults and in females |
| GH secretion | High | Lower |
| GH positivity on staining | Not stated | Lesser amount |
| Proliferation and invasiveness | Low | More |
| Most common molecular change | GNAS mutation | Not stated |
| Response to somatostatin analogue (SSA) treatment | High responsiveness | Lesser responsiveness |
A mixed-pattern adenoma made up of both SGSA and DGSA is also possible.
Two further adenomas make both GH and prolactin, and they differ in how they do it. The mammosomatotrope adenoma arises from a single Pit-1 lineage yet is positive for both GH and prolactin, because one lineage can make both hormones. It is more common in younger adults. The prolactin it produces brings patients to medical attention earlier, so it is usually diagnosed while still small, and it is highly responsive to SSA treatment. The mixed somatotrope and lactotrope adenoma contains two cell populations and produces both hormones.
When an adenoma secretes both GH and prolactin, the clinical manifestation is sometimes dominated by prolactin excess. The louder syndrome hides the quieter one, so acromegaly is then not that evident to detect.
Subtypes differ in output and response, and the genes and receptors of the cell say why.
What changes inside the adenoma make it secrete and grow?
Several genes are altered in somatotrope adenomas. Some bear on tumor behavior, and others on the response to SSA treatment.
GNAS is the only recurrent genetic alteration in somatotrope adenomas. It is mutated in 15–58% of them. GNAS encodes the Gsα portion of a G protein-coupled receptor (GPCR). The pathway normally switches on only when a signal arrives. The mutation leads to constitutive activation of adenylate cyclase (AC), which leaves it on, so cAMP stays high. The cell then secretes GH, and the same signal promotes its growth, without being asked.
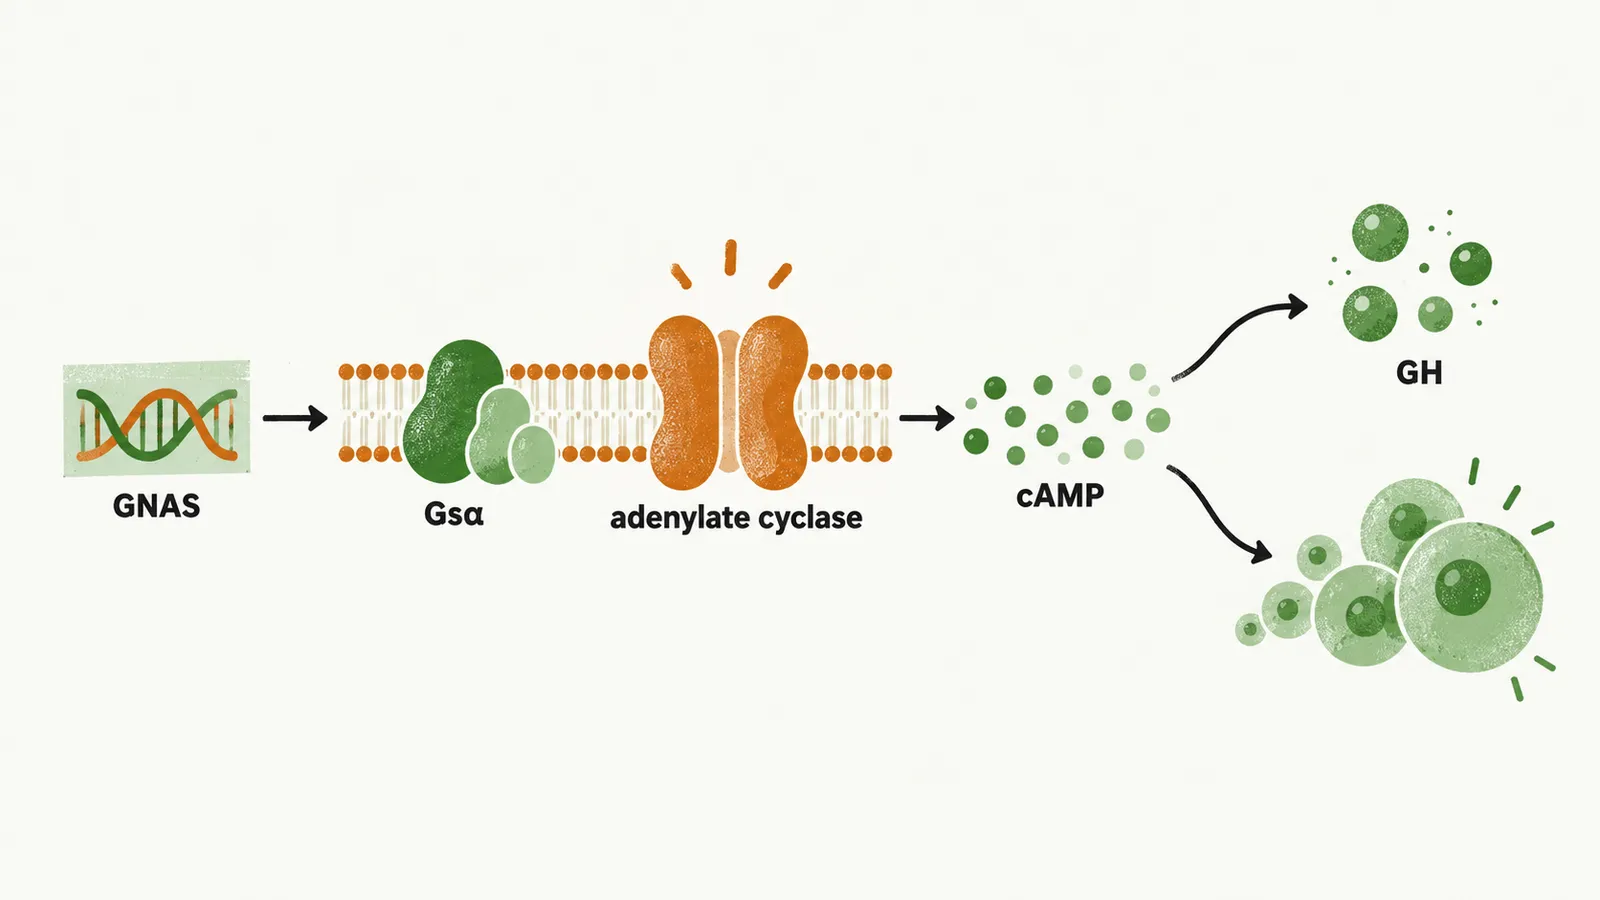
GPR101 acts on the same pathway. It is a receptor predicted to couple to Gsα, a stimulator of adenylate cyclase. In early-onset gigantism with GH hypersecretion, a heritable microduplication of the X chromosome at Xq26.3, called X-linked acrogigantism (X-LAG), is found. GH excess before the growth plates fuse gives gigantism rather than acromegaly. In these patients expression of Gpr101 mRNA is increased 1000-fold. Gpr101 is an orphan GPCR bound to Gsα that increases the activity of AC. A gene-dose effect, with extra copies of the gene giving more receptor, is a proposed explanation.
Two further groups of genes relate to the signals that control the somatotrope, GHRH, ghrelin and somatostatin, which the earlier note on GH physiology covers.
- Ghrelin. Ghrelin is a growth factor acting on the pituitary gland, and GHSR is the gene responsible for expression of the ghrelin receptor. Ghrelin stimulates GH secretion, so its receptor matters in the tumor.
- Somatostatin receptors. The expression pattern of the somatostatin receptor genes differs between somatotrope adenoma subtypes, and it is highly influenced by SSA treatment. An SSA acts by binding somatostatin receptors on the tumor cell, so the more suitable the receptor, the more the drug can brake secretion. DGSA express more SSTR2 (somatostatin receptor type 2), and SGSA express mainly SSTR5. The higher the SSTR2 expression, the higher the responsiveness to SSA treatment. That is why granulation pattern and receptor profile predict how a tumor will answer an SSA, the subject of the diagnosis and treatment note.
The aryl hydrocarbon interacting protein (AIP) gene stands apart. AIP mutations are mostly associated with somatotrope adenomas, and the mutation is a non-sense mutation. AIP products are believed to be onco-suppressor products, although information is still very limited. A proposed explanation is that AIP is a co-chaperone linked with PDE4A5, a cAMP-degrading enzyme, and that mutations are thought to reduce PDE4A5 inhibition and raise cAMP, so the pathway is on through a lost brake.
The picture that results is an early, aggressive tumor that is relatively resistant to treatment. A germline AIP mutation is relatively common among young adults with acromegaly (5–14%). It is associated with larger, more invasive adenomas with more potential for recurrence, and patients with an AIP mutation are relatively resistant to SSA treatment. In patients without an AIP mutation, SSA treatment leads to upregulation of AIP expression.
GNAS and GPR101 act on the cAMP pathway, and AIP is thought to reach it too, so one switch is seen from three sides. All of this assumed an adenoma in the pituitary. Can GH excess arise without one?
Can GH excess happen without a pituitary adenoma?
Not every picture of GH excess comes from a somatotrope adenoma, and not every picture of acral enlargement comes from GH excess at all.
Very rare causes of excess GH are:
- pituitary carcinomas
- ectopic GH secretion by neuroendocrine tumors, namely lung, pancreatic and ovarian NETs
- excessive hypothalamic GHRH secretion, most often from chest and abdominal carcinoids
- iatrogenic injection of GH
GHRH is the main stimulus of the somatotrope, so a tumor that makes it can drive GH output from outside the pituitary. Ectopic hormone secretion is described as central or peripheral. Central sources are hypothalamic tumors and ganglioneuroma. Peripheral sources are bronchial carcinoid, small cell lung cancer, adrenal tumor and pancreatic neuroendocrine tumor. Rarely, ectopic pituitary adenomas are identified in the sphenoid sinus or parapharyngeal tissue.
GH given from outside gives the same picture with no tumor. Exogenous GH replacement or abuse is a cause.
Pseudoacromegaly looks like acromegaly without GH excess. Its causes include pachydermoperiostosis, diseases of the IGF signaling pathway and severe insulin resistance.
Which inherited syndromes include acromegaly?
Several genes met above also appear in families or in very young children. The gene is the same as in the tumor itself; what is new is the family or the age. Acromegaly can occur in some genetic and familial conditions: GPR101 in X-LAG, AIP in familial isolated pituitary adenoma and GNAS in McCune–Albright syndrome. Others are the multiple endocrine neoplasia syndromes (MEN1 and MEN4), Carney complex, SDH (succinate dehydrogenase) mutations and neurofibromatosis.
| Condition | Gene and inheritance | Features |
|---|---|---|
| X-LAG | GPR101; X-linked dominant or sporadic | Mostly females; age <5 years; hyperprolactinemia at diagnosis |
| Familial isolated pituitary adenoma | AIP; autosomal dominant or sporadic | Younger males; higher GH levels; poor response to SSA therapy |
| MEN1 | MEN1; autosomal dominant or sporadic | Primary hyperparathyroidism, pancreatic disease along with pituitary adenoma |
| MEN4 | CDKN1B; autosomal dominant | Pituitary and parathyroid neoplasms with pheochromocytomas, thyroid and other tumors |
| Carney complex | PRKAR1A; autosomal dominant | Skin pigmentation, atrial myxoma, GH or PRL excess; Cushing’s due to primary pigmented nodular adrenocortical disease; somatotroph hyperplasia or multifocal adenoma |
| McCune–Albright syndrome | GNAS; somatic mosaicism, not inherited | Average age of diagnosis 23 years; acromegaly in 20–30% of cases; hyperprolactinemia at diagnosis; café-au-lait spots; peripheral precocious puberty; somatotroph hyperplasia |
| SDH mutation | SDHx; autosomal dominant or sporadic | Phaeochromocytoma, paraganglioma and primary hyperparathyroidism |
| Neurofibromatosis | NF1; autosomal dominant | Few case reports of children and adolescents with optic glioma; adenoma rarely reported |
Some of these fit what the pathway predicts. X-LAG can be de novo, so a family history may be absent. Its hyperprolactinemia fits tumors that contain GH- and prolactin-producing cells. MEN1 encodes menin, a tumor suppressor, so its loss lets several endocrine tissues form tumors. MEN4 is a loss of function of a cell-cycle regulator, with a MEN1-like phenotype. In Carney complex, inactivating PRKAR1A mutations let cAMP-dependent kinase activity run uncontrolled, the same pathway, and several tissues are involved. In McCune–Albright syndrome an activating GNAS mutation arising in only some cells after conception explains why it is not inherited and why only some tissues are involved. It is the pathway of the GNAS mutation described above.
In neurofibromatosis the mechanisms are unclear. One proposed explanation is an optic glioma disrupting hypothalamic somatostatin neurons; another is unknown mechanisms that raise GPR101 expression.
With causes this varied, most of them one tumor of the pituitary, how common is acromegaly, who gets it, and why is it so often found years late?