
What is PTH, and where does it fit?
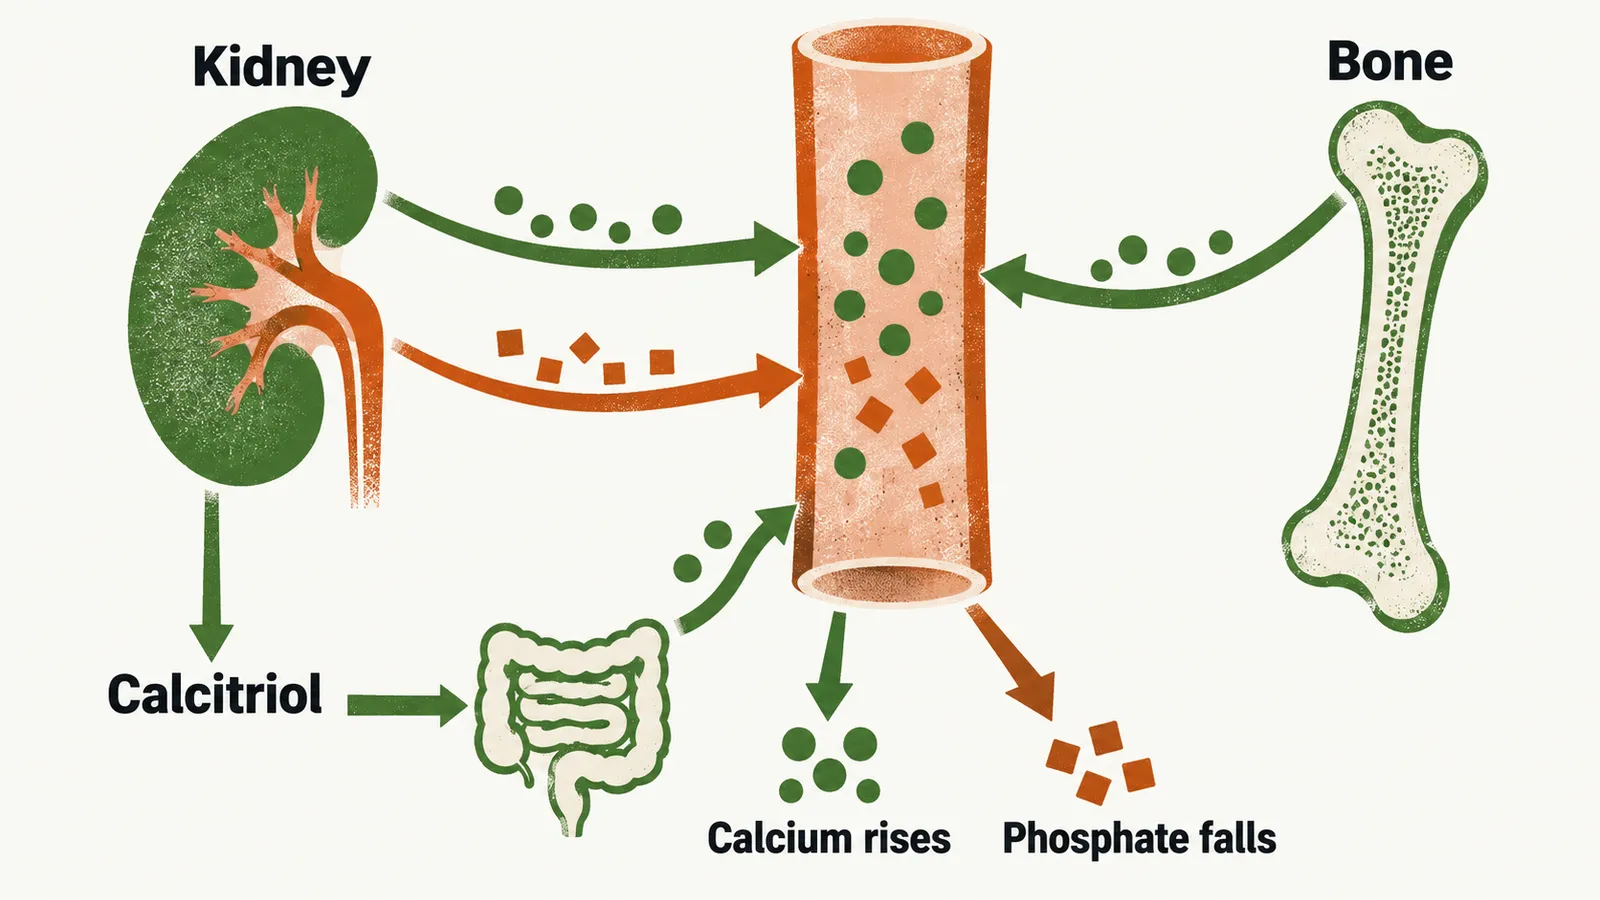
The parathyroid glands work like a thermostat for calcium. PTH is their hormone, and it is the principal regulator of plasma calcium. When calcium is low, PTH is released. When calcium is high, its release stops. PTH then acts on bone, on the kidney and, through calcitriol, on the intestine, so that calcium rises and phosphate falls.
Three hormonal factors control calcium and phosphate ion homeostasis: PTH, FGF23 (fibroblast growth factor 23) and calcitriol, the active form of vitamin D. All three act on the same main organs: bone, kidney and intestine. PTH is the one that responds to calcium within minutes, so it handles the minute-to-minute defence of calcium while the other two work on a longer timescale. FGF23 and calcitriol have their own notes.
How does the parathyroid cell know the calcium level?
A thermostat needs a sensor and a feedback rule. The sensor is a plasma membrane calcium-sensing receptor, called CaSR, which lets the parathyroid cell read the calcium level of the plasma directly. The rule is negative feedback: the sensed variable is plasma calcium itself, so the response removes its own stimulus. When plasma calcium rises, PTH release falls. When plasma calcium falls, PTH is released.
CaSR is a G-protein-coupled receptor (GPCR) bound to the G proteins Gi and Gq, and both limbs reduce PTH release. In hypocalcemia the receptor is not occupied by calcium, so Gi and Gq are not activated to inhibit PTH release, and PTH is released.
When calcium occupies CaSR, two routes inhibit PTH release:
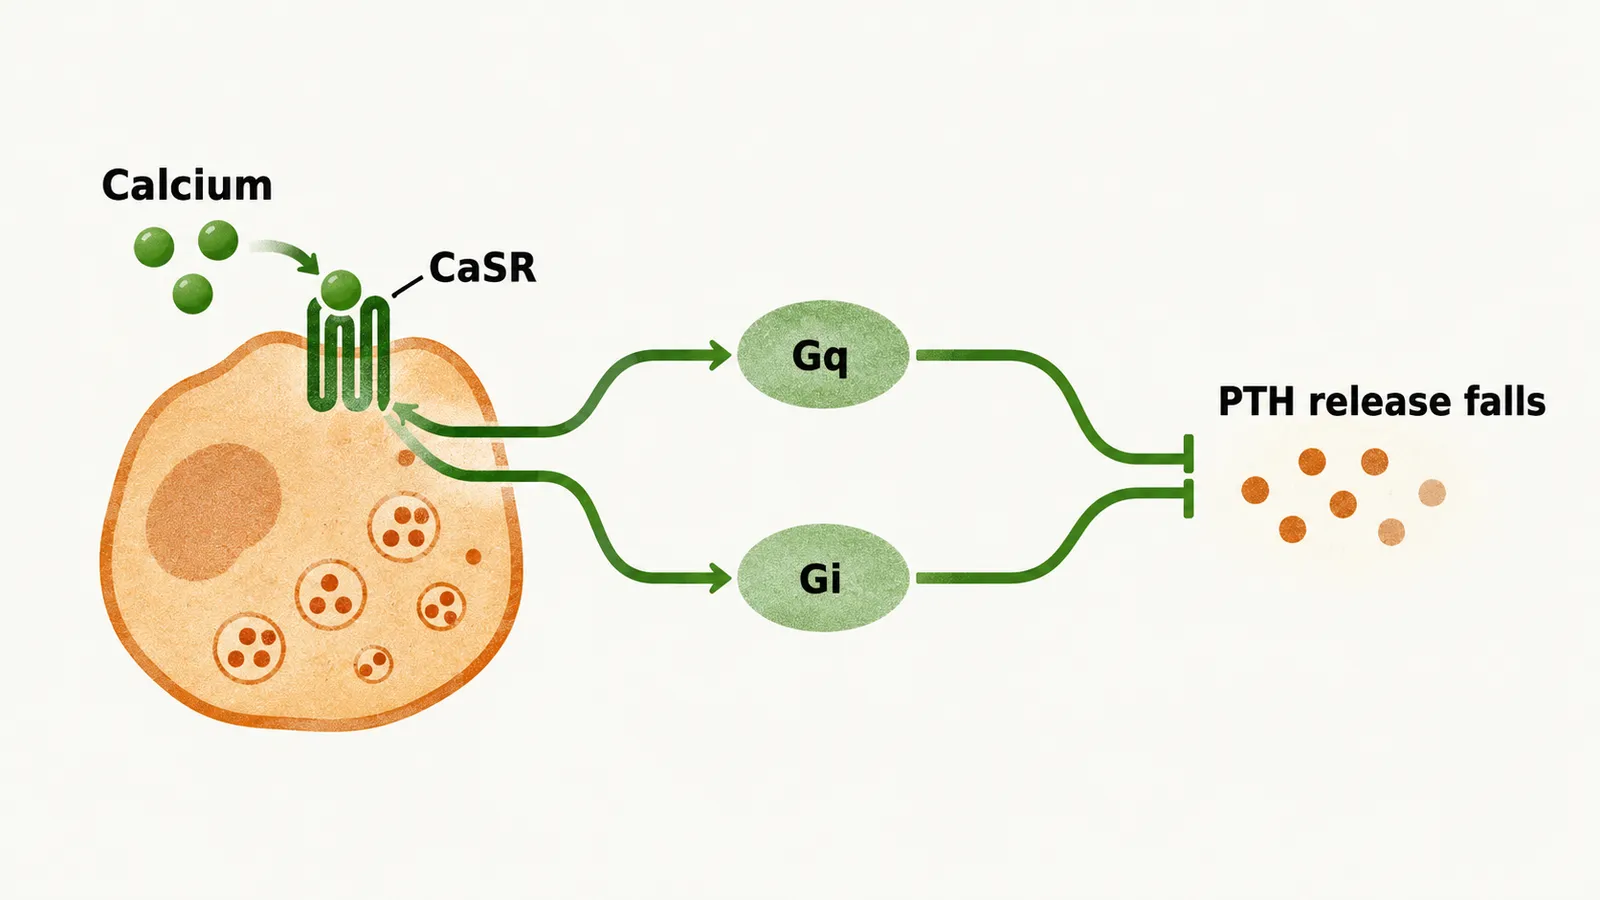
- Via Gq: calcium occupation of CaSR activates Gq and increases PKC activity. The increase of intracellular calcium concentration then leads to reduction of PTH release.
- Via Gi: Gi reduces cAMP inside the parathyroid cells, and reduced cAMP inhibits PTH release.
Because cAMP is what Gi lowers, agents that increase intracellular cAMP of parathyroid cells push release the other way and increase PTH secretion, such as beta agonists and dopamine.
Why does calcium turn PTH off, when it turns most cells on?
Both routes make high calcium a stop signal, and that is unusual. In most cells of the body, increased intracellular calcium is a stimulatory signal for secretion or expression. The Gq route is a physiological exception, because in two cell types increased intracellular calcium inhibits secretion of a target product:
- Granular cells of the juxtaglomerular apparatus, where increased intracellular calcium reduces renin secretion.
- Parathyroid cells, where increased intracellular calcium, promoted by occupation of CaSR by calcium ion, reduces PTH release.
This inverted signal is what lets high calcium act as a stop signal for PTH. It also shows what happens when the sensor fails. A loss-of-function mutation of the CaSR gene leads to familial hypocalciuric hypercalcemia type 1 (FHH-1). The receptor-as-brake picture explains the link: if the receptor cannot work, the cell reads calcium as lower than it is, so PTH is not switched off appropriately.
What else adjusts PTH release?
Calcium is the main input to the loop, but other, less important regulatory mechanisms of PTH secretion exist. Active vitamin D reduces PTH secretion. Hypermagnesemia inhibits PTH secretion, and hypomagnesemia also impairs it, so both extremes of magnesium disturb the axis.
What does PTH look like, and what does it bind?
Once PTH is released, which part of the molecule carries the message, and which receptors read it?
PTH is produced as a 115-amino-acid molecule, preproparathyroid hormone. The ER cleaves it to the 90-amino-acid proparathyroid hormone, and removal of 6 amino acids in the Golgi produces PTH. PTH is a single polypeptide chain of 84 amino acids.
The receptor engages the amino-terminal end of PTH, so the biological activity sits in the first 34 amino acids from the N-terminal side. PTH(1-34) is the shortest fragment that retains essentially complete activity and behaves like the whole hormone. Changes at the two ends of the chain alter PTH activity. The very start of the chain is what switches the receptor on, and the rest helps it hold on. That explains why derivatives lacking the first and second amino acids attach to the receptor but do not activate it, and why derivatives lacking the first six amino acids inhibit PTH action. Studies also show that oxidation of the 8th and 18th methionine reduces physiological activity.
PTH is short-lived. Its half-life in the body is about 4 minutes, and it is mostly cleared by the liver and kidney.
PTH acts through more than one receptor, at least three:
- The type 1 PTH receptor (PTH1R) is responsible for the homeostatic and skeletal effects of PTH. It can also bind PTH-related protein (PTHrP), which has its own note.
- The type 2 PTHR is expressed on organs such as cardiac tissue, pancreas, brain and placenta. It is activated only by PTH, not by PTHrP.
- cPTHR binds the C-terminal end of the shortened PTH and is expressed on osteocytes.
What does PTH do in kidney, bone and calcitriol?
The receptor sits in bone and kidney, so what happens at each? The physiological effects of PTH are calcium reabsorption in the kidney, phosphorus excretion in the kidney, calcium mobilization from bone and stimulation of calcitriol production.
Kidney. In the distal tubule, where calcium reabsorption is regulated, PTH opens up calcium reabsorption through the calcium channel there, so more calcium is removed from the filtrate. In the proximal tubule, which reabsorbs most of the filtered phosphate, PTH takes the sodium-phosphate transporters off the brush border. Less phosphate is reabsorbed and more is excreted, so PTH acts on the step that sets phosphate balance.
Bone. PTH does not directly activate osteoclasts. The primary target cell of PTH in bone is the osteoblast, and the osteoblast then drives resorption by the osteoclast. Through the osteoblast (and osteocyte), PTH raises RANKL and lowers its decoy OPG, so osteoclasts are recruited and activated and mobilise calcium.
Calcitriol. PTH stimulates conversion of inactive to active calcitriol in the kidney, through direct activation of 1α-hydroxylase of tubular cells. Calcitriol then raises intestinal calcium and phosphate absorption. PTH also increases calcitriol production indirectly, through the hypophosphatemia caused by a high PTH level, and hypophosphatemia itself increases calcitriol production.
Net effect. PTH raises plasma calcium and lowers plasma phosphate, because PTH increases phosphate excretion in the kidney while it brings calcium in. The fall in phosphate keeps calcium phosphate from precipitating in the tissues as calcium is mobilized.
Does PTH build bone or break it down?
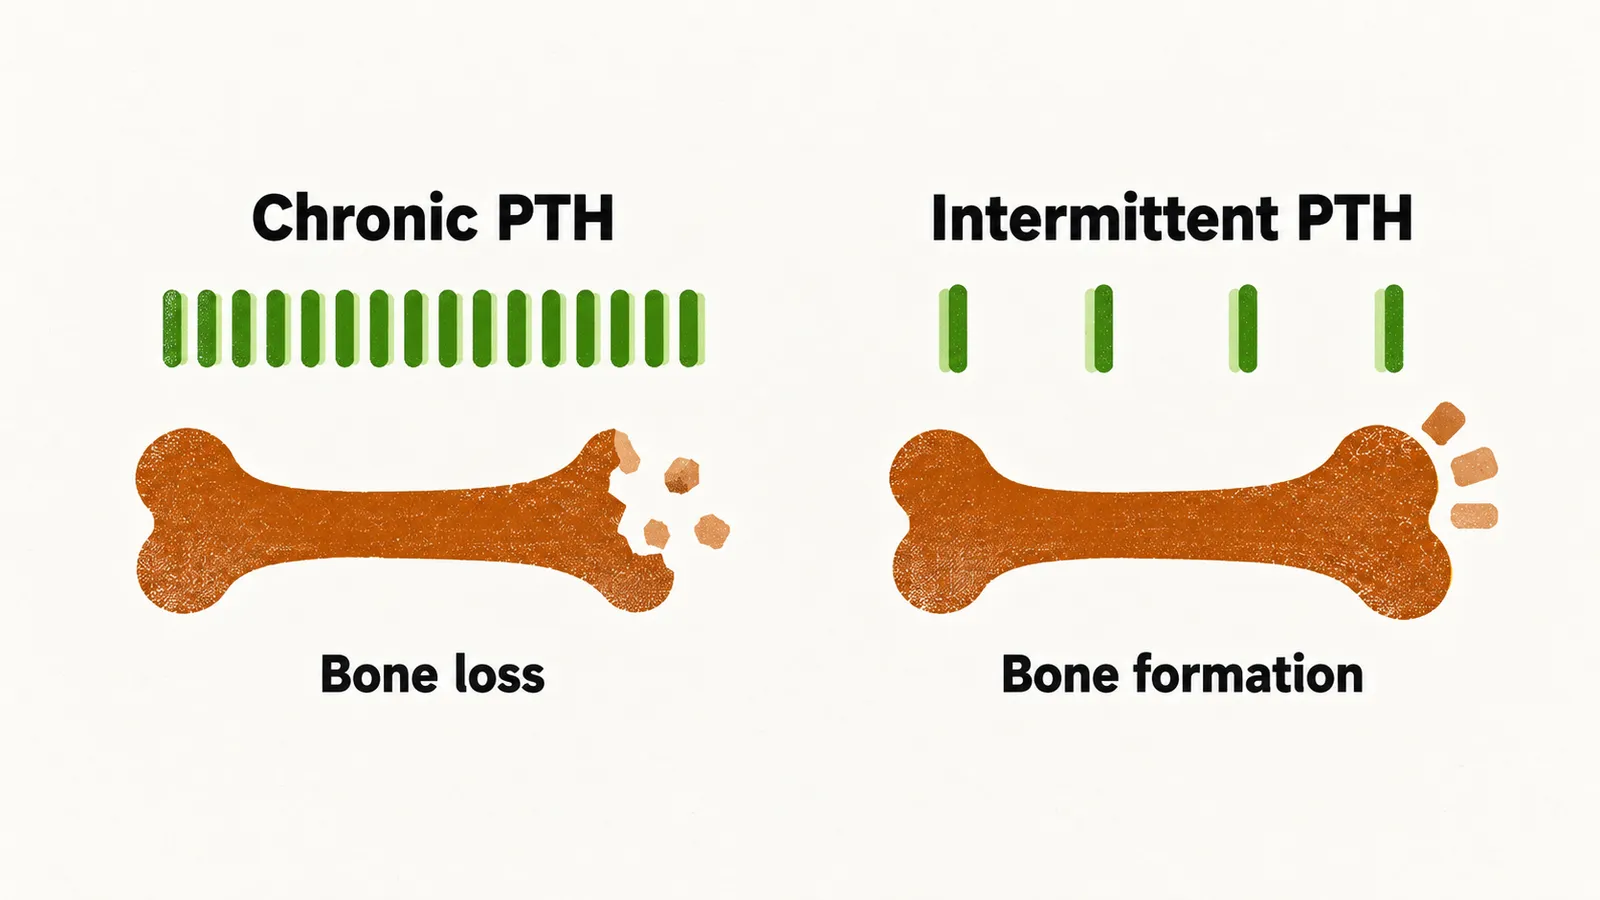
Bone is the organ where the answer depends on the pattern. PTH has both catabolic and anabolic effects on bone. Chronic PTH release is catabolic, causing bone loss: sustained exposure keeps the RANKL-over-OPG balance tilted toward resorption. Intermittent PTH release has an anabolic effect. Intermittent exposure is brief, and this is thought to let bone-forming signals act, so that formation exceeds resorption. A proposed explanation is that PTH lowers sclerostin in osteocytes, at least in part, releasing a bone-forming pathway.
Does the response change with the length of the fall in calcium?
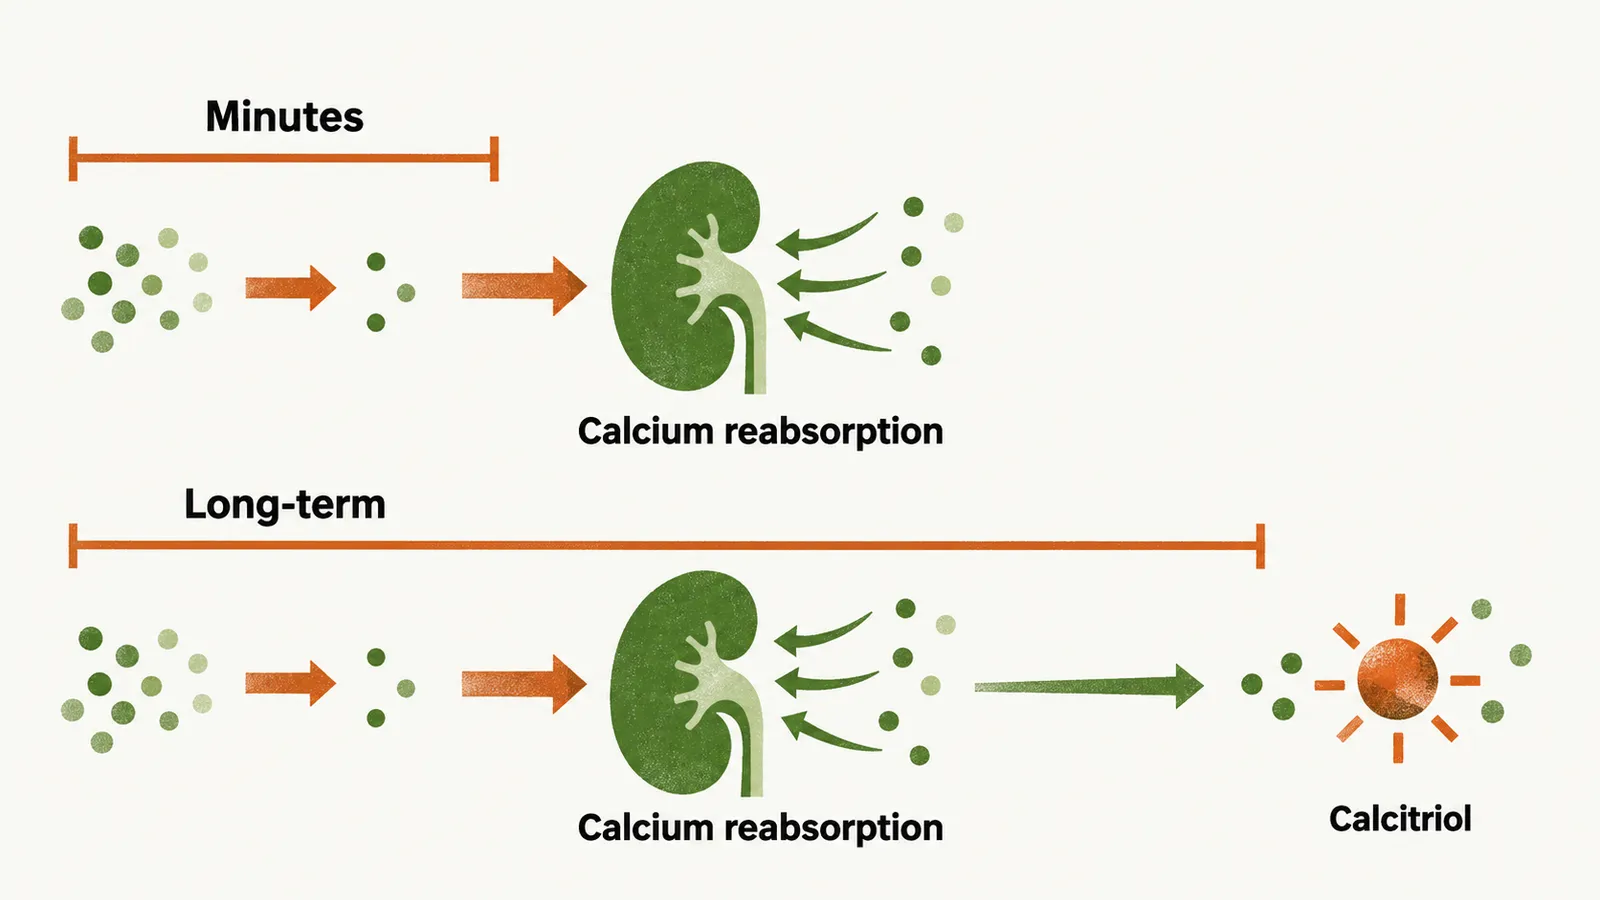
With all the actions in view, how do they combine over time? In hypocalcemia, the changes in calcium, phosphate, calcitriol and PTH depend on the time course of the hypocalcemia.
If the fall in calcium lasts only minutes, PTH only increases calcium reabsorption, which suffices for compensation. In minute-to-minute hypocalcemia calcitriol does not need to increase. A likely reading is that the kidney acts quickly: reabsorption of calcium that has already been filtered can be changed in minutes, so a brief dip needs nothing else. In long-term hypocalcemia, calcium reabsorption increases and calcitriol also increases. Calcitriol is thought to act through changes in gene expression, which takes longer. In summary, PTH lowers phosphate and raises calcitriol.
What pulls phosphate down while holding calcitriol back?
FGF23 also lowers phosphate, but it restrains calcitriol, and FGF23 release is itself driven by high PTH. If PTH pushes phosphate down and calcitriol up, which hormone made in bone pulls phosphate down while holding calcitriol back, and why is PTH itself what drives its release?