
A raised prolactin level is one number, and several routes can push it up: more drive to the lactotrophs, less dopamine brake on them, or less prolactin cleared from the blood. Each route has its own causes, so a high number does not name a disease by itself. The diagnosis is therefore built by excluding the common causes first. Then the prolactin level and the imaging are used together to decide whether a tumour is present. Each of these two pieces of information can mislead on its own: a very high prolactin can be read as low by the assay, and the blood can hold a large complex that does not act. That is why they are read against each other.
What is ruled out before any scan?
In hyperprolactinemia it is mandatory first to rule out other causes. These causes are common and reversible, and they come before any imaging. They are:
- pregnancy
- lactation
- hypothyroidism
- drug-induced hyperprolactinemia
- renal failure
- liver failure
- hypothalamic defects
Pregnancy and lactation are normal physiological states that raise prolactin. Dopamine from the hypothalamus holds the lactotrophs down through D2 receptors, so drugs that block those receptors let prolactin rise; the drugs remove part of the dopaminergic brake. A mass on the pituitary stalk blocks dopamine on its way to the lactotrophs, so hypothalamic and stalk defects raise prolactin too.
Why does hypothyroidism raise prolactin? In hypothyroidism, TRH is raised. TRH is also one of the signals that drive prolactin release, so its increase stimulates the lactotrophs and the prolactin level rises.
Why do renal and liver failure raise it? Prolactin is cleared from the blood through the liver and the kidneys. When either organ fails, less prolactin is cleared, and the level rises.
So the first step is to take out the causes that are common and reversible.
What is left when those causes are gone?
Once none of those causes explains the level, three possibilities are left.
- A microadenoma, which is 4 to 5 folds more prevalent than a macroadenoma.
- A macroadenoma.
- No visible tumour. At this stage these patients are considered to have idiopathic hyperprolactinemia.
Idiopathic hyperprolactinemia may simply be a microadenoma too small to be seen. It usually remains stable on follow-up.
How does imaging look for the tumour?
MRI is the modality of choice when a prolactinoma is suspected, because MRI is the primary imaging modality for the pituitary gland. It uses T2-weighted coronal sections, and T1-weighted coronal sections before and after gadolinium.
On T1-weighted MRI, a prolactinoma is usually hypo-intense or iso-intense. It is rarely hyper-intense, and T1 hyper-intensity happens in haemorrhagic complications of a prolactinoma. On T2-weighted MRI, usually 80% of prolactinomas are hyper-intense.
CT scan is helpful in a macroprolactinoma when invasion of bony structures is suspected. Bony invasion can present with CSF rhinorrhea. This happens mostly in men with a macroprolactinoma, after the mass has shrunk under dopamine agonist therapy.
How is the size read against the level?
Once imaging finds an adenoma, its size is read against the level. The earlier note set the groups at a diameter of 10 mm: an adenoma smaller than 10 mm is considered a microadenoma, and one bigger than 10 mm a macroadenoma.
Usually in a microadenoma the serum prolactin is below 200 ng/ml. In a macroadenoma it is mostly greater than 200 ng/ml, and mostly more than 500 ng/ml. Sometimes, however, the level is not correlated with the size of a tumour that imaging shows to be a macroprolactinoma. An example is a macroprolactinoma with a prolactin of 100-200 ng/ml.
When do the size and the level disagree?
Size and level are read together, and sometimes they do not agree. Two different conditions have to be differentiated during the diagnostic work-up.
- Condition A: a macroprolactinoma whose hyperprolactinemia is correlated with tumour size.
- Condition B: a macroprolactinoma whose hyperprolactinemia is not correlated with tumour size.
In condition B the tumour is not a functioning tumour that releases prolactin into the blood. A mass on the pituitary stalk blocks dopamine on its way to the lactotrophs, so prolactin rises although the mass does not make prolactin. The only cause of the hyperprolactinemia is then compression of the pituitary stalk.
The two scenarios should always be differentiated, because the treatment differs. In condition A, pharmacological treatment has to be used. In condition B, the patient has to be operated on.
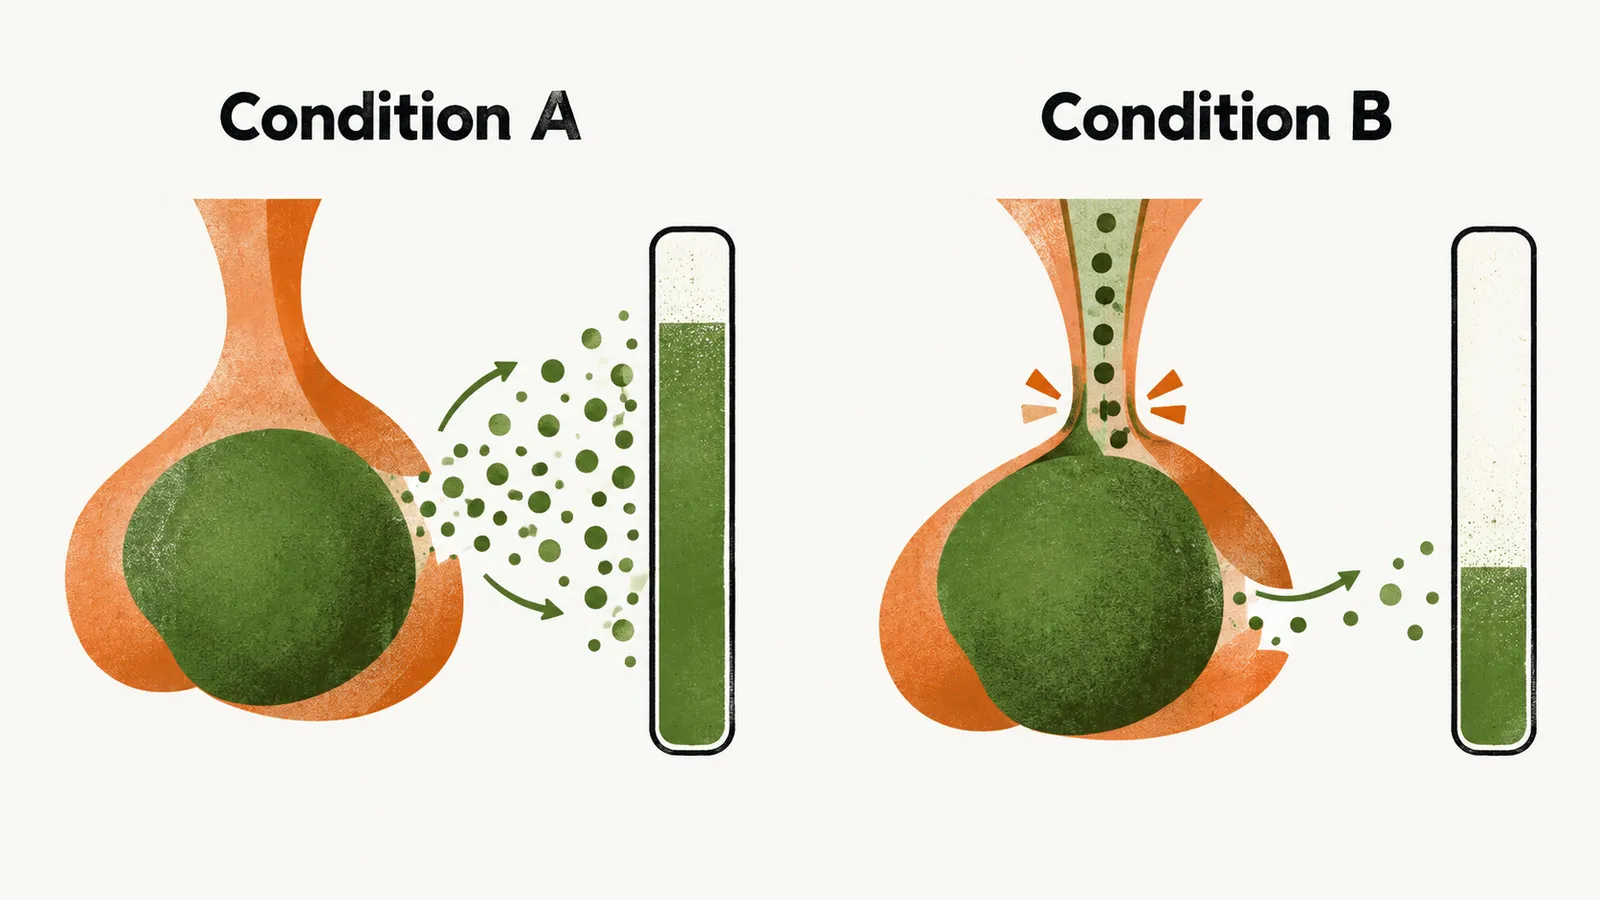
Suppose the scan shows a macroadenoma and the serum prolactin is less than 200 ng/ml. If the laboratory measurement of prolactin is reliable, it can be a pseudo-prolactinoma. If the measurement is not reliable, it could still be a macroadenoma. Also, if more than 50% of a prolactinoma is a cystic sellar mass, the size of the prolactinoma is usually not correlated with the serum prolactin, which is low.
So the reliability of the laboratory measurement decides how a low level is read, and that reliability can fail in several ways.
Why can one measurement mislead?
Even the level itself can be wrong before it is read against the size. Similar to GH, prolactin secretion is affected by stress, so a reading taken in a stressful moment can be high without disease. That is why the laboratory test for prolactin is better done in serial form: repeated measurements separate true from stress-induced hyperprolactinemia. Serial sampling also prevents the effect of stress-induced prolactin secretion in response to venipuncture.
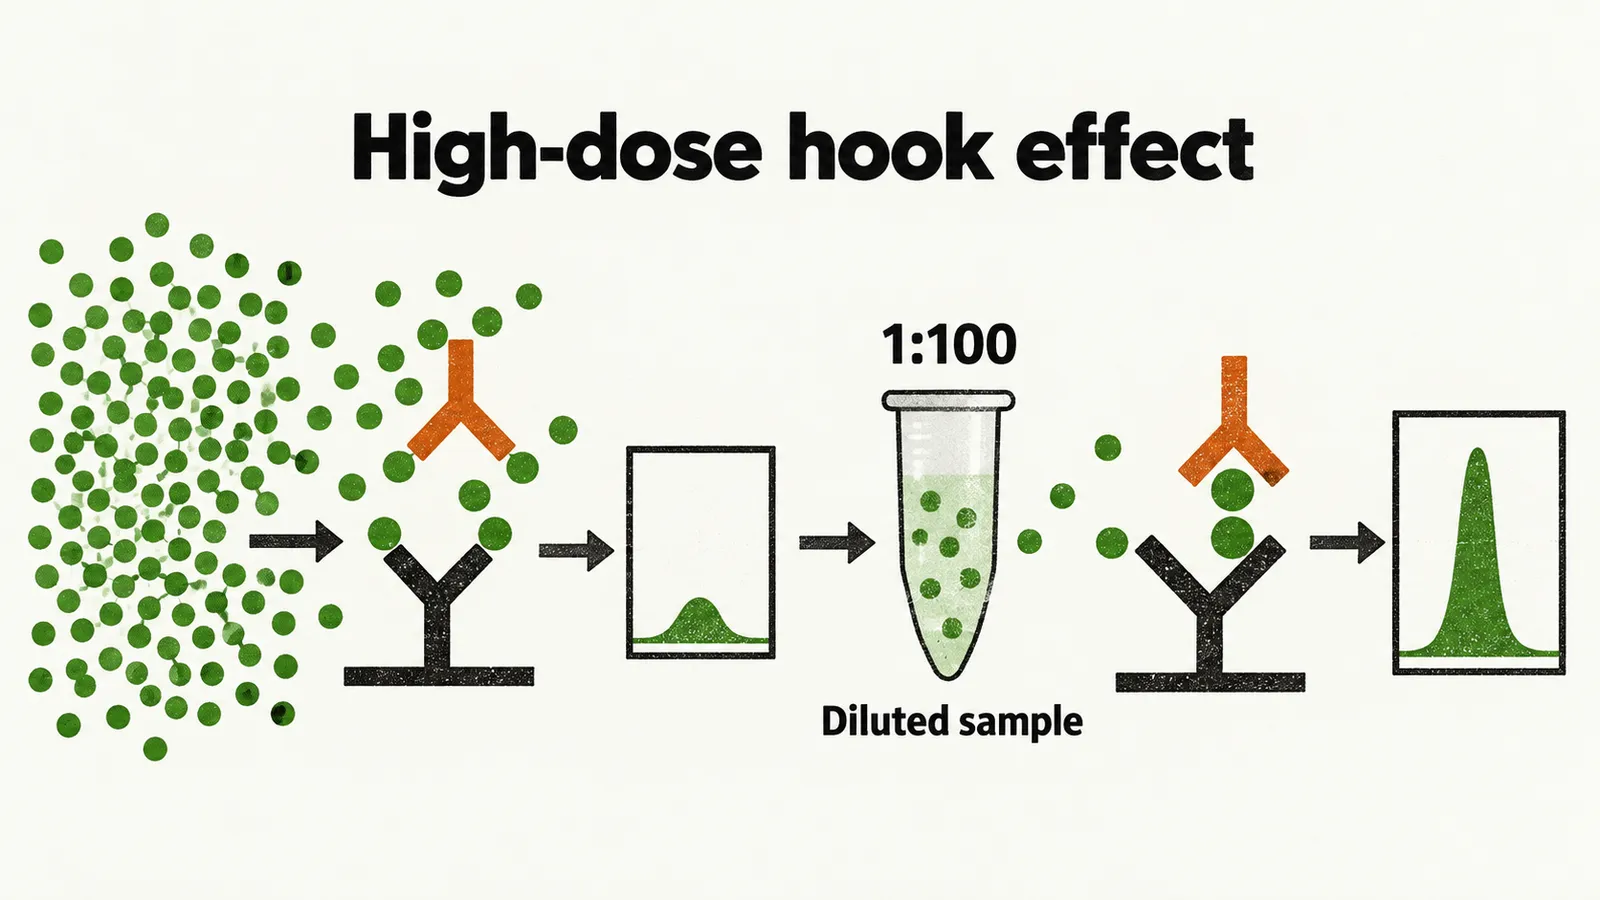
The result can also be incorrect because of the assay itself. In some laboratory techniques, a very high prolactin concentration in the serum saturates both the signal and the capture antibodies. The result from the signal antibodies is then not correct, and the serum prolactin level is under-estimated. This effect is called the high-dose hook effect. When it is suspected, the test can be repeated with the patient’s serum diluted at 1:100.
Why can a high reading be harmless?
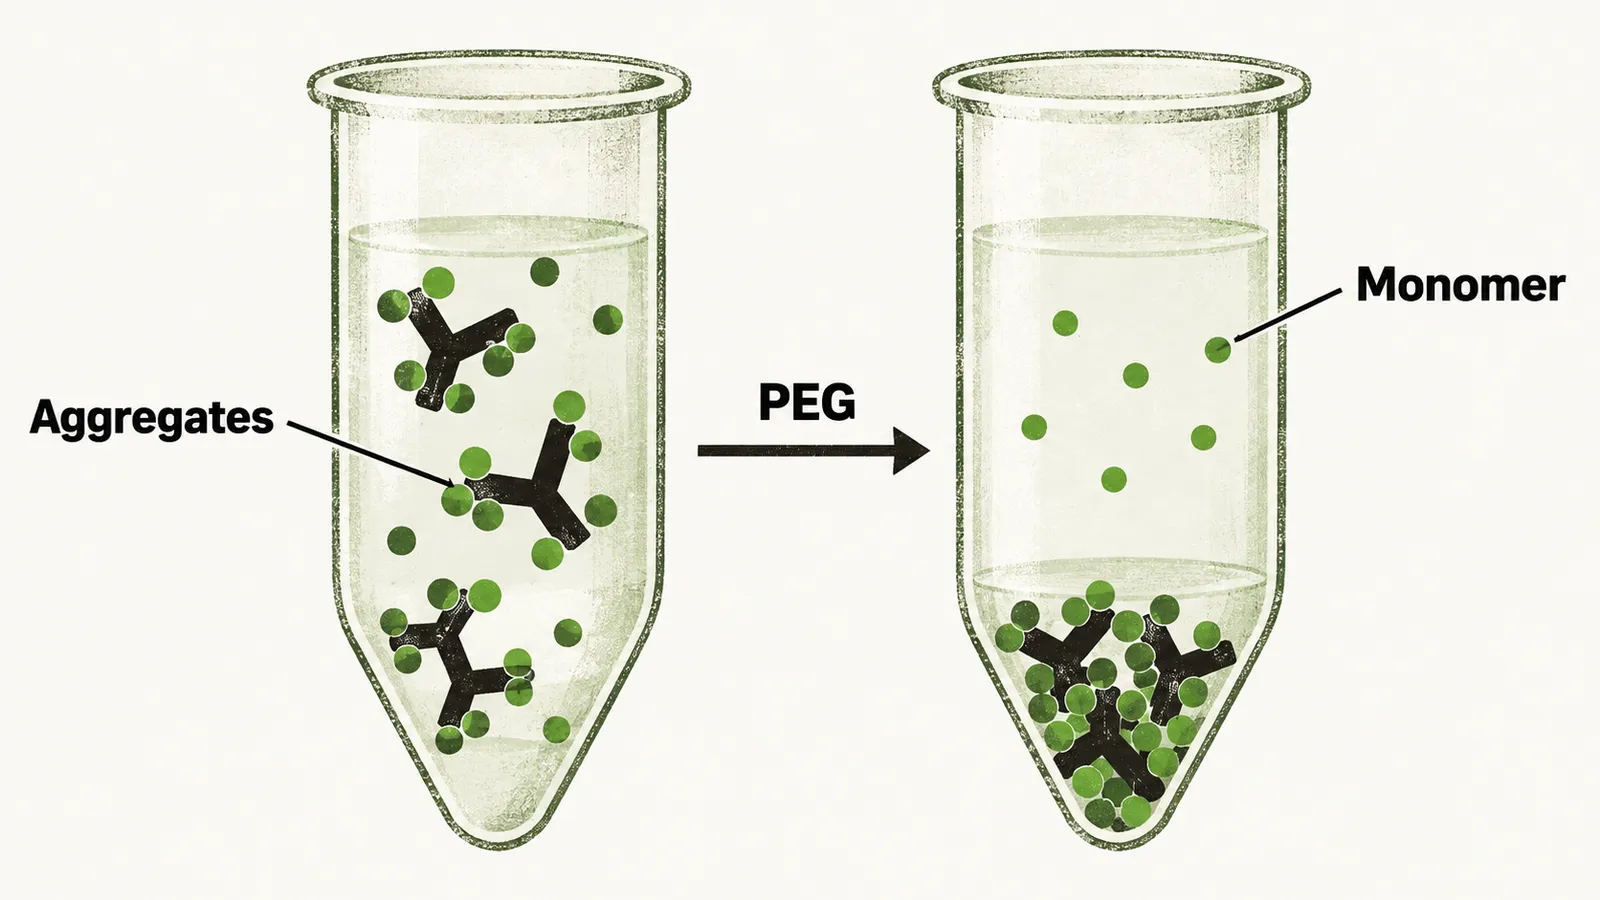
Some of the wrong readings come from the blood itself, not from the assay. Some patients have no clinical signs and symptoms of hyperprolactinemia, yet the laboratory results show significant hyperprolactinemia. Studies of these patients show that the hyperprolactinemia is caused by a big-big prolactin aggregate. The biological activity of prolactin is exerted by the monomeric form, not by aggregate molecules, so a large complex that does not act can give a high number with no symptoms. These patients are called macroprolactinemia.
How do the aggregates form? Big-big prolactin is a complex of prolactin with immunoglobulin. The aggregates found in serum are due to complex formation between IgG, or IgA, and circulating prolactin. They have a high molecular weight in comparison with the monomeric form, which is the active form of the hormone. The antibodies are autoantibodies against different epitopes of prolactin. The epitopes can differ in different individuals, with different association rates with the antigen, which is prolactin. Macroprolactinemia is defined as the presence of big-big prolactin in the serum, which predominates over the other forms by 30-60%.
In a patient without clinical signs and symptoms but with laboratory results showing macroprolactinemia, a precipitation test of the serum with PEG has to be performed. PEG precipitates the large complex out of the serum, and it is the routine test for identifying macroprolactin when the level is above the reference interval. PEG positivity shows that the high prolactin level is made by the big-big prolactin aggregate, which is not biologically active, because the active form is the monomer. It also shows that there is no adenoma in these patients.
Why is PCOS a trap in women?
The same harmless complex turns up in women with PCOS. PCOS is a very important differential diagnosis in women with hyperprolactinemia, because PCOS and hyperprolactinemia are the two most common causes of anovulation in women. In about 15% of women with PCOS the laboratory result shows hyperprolactinemia. Much of this reflects macroprolactinemia, the biologically inactive big-big aggregate, rather than a true excess of active hormone. Prolactinoma explains a minority of these elevations.
When does a high level point to a tumour?
When true hyperprolactinemia persists after artefact is excluded, a prolactinoma is looked for. Once a tumour is confirmed as the cause, what treatment is needed?