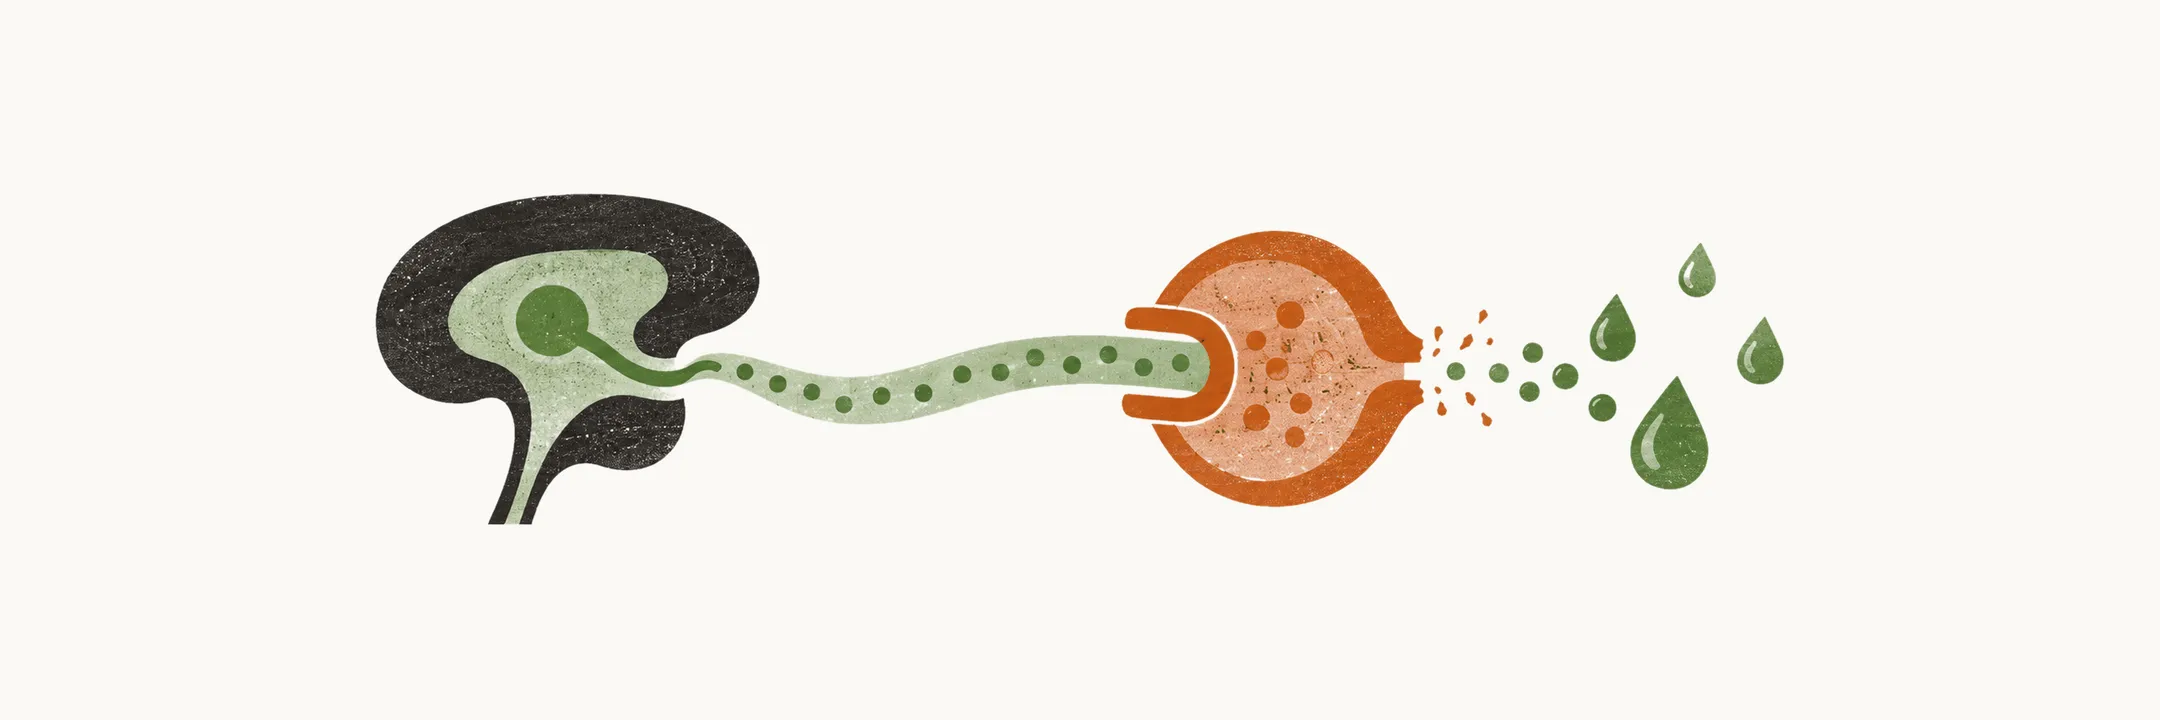
Prolactin is a hormone of the anterior pituitary, made by cells called lactotrophs. Hyperprolactinemia is the most common pituitary hypersecretion syndrome in both men and women. To see how it arises, start with how prolactin is controlled.
What keeps prolactin down?
Most anterior pituitary hormones are driven mainly by releasing factors from the hypothalamus. Prolactin is the reverse. Its release is held back by the hypothalamus rather than driven by it, and dominance of inhibition is what separates prolactin from the other anterior pituitary hormones. Dopamine is the main signal that holds prolactin release down. So the resting state of a lactotroph is suppressed.
How does the brake reach the cells?
The hypothalamus releases dopamine into the portal blood, which carries it down to the anterior pituitary. The brake travels in this portal blood. There dopamine acts on D2 receptors of the lactotrophs. It suppresses both prolactin secretion and prolactin synthesis, and it also holds down the number of lactotrophs. GABA adds a minor inhibitory effect alongside dopamine.
What happens when the brake fails?
Because the resting state is suppressed, taking the brake away lets release rise with nothing else added. Anything that reduces dopamine delivery to lactotrophs will raise prolactin. That is why a raised prolactin level usually means a brake or a pathway has been interrupted.
What pushes prolactin up?
The brake is not the only control. A smaller set of signals stimulates prolactin release: TRH, estrogen, VIP, serotonin and oxytocin. Estrogen matters most clinically. It stimulates prolactin release and it also increases the number of lactotrophs, so it both pushes release and adds cells. The high estrogen of pregnancy drives prolactin very high.
Is every raised level a disease?
Estrogen in pregnancy is one of the normal states that raise prolactin, so not every raised level signals disease. Some causes are physiological states, and they have to be recognised before a pathological cause is pursued:
- pregnancy and lactation;
- sleep-associated hyperprolactinemia;
- nipple stimulation and sexual orgasm;
- chest wall stimulation and trauma.
How does size narrow the causes?
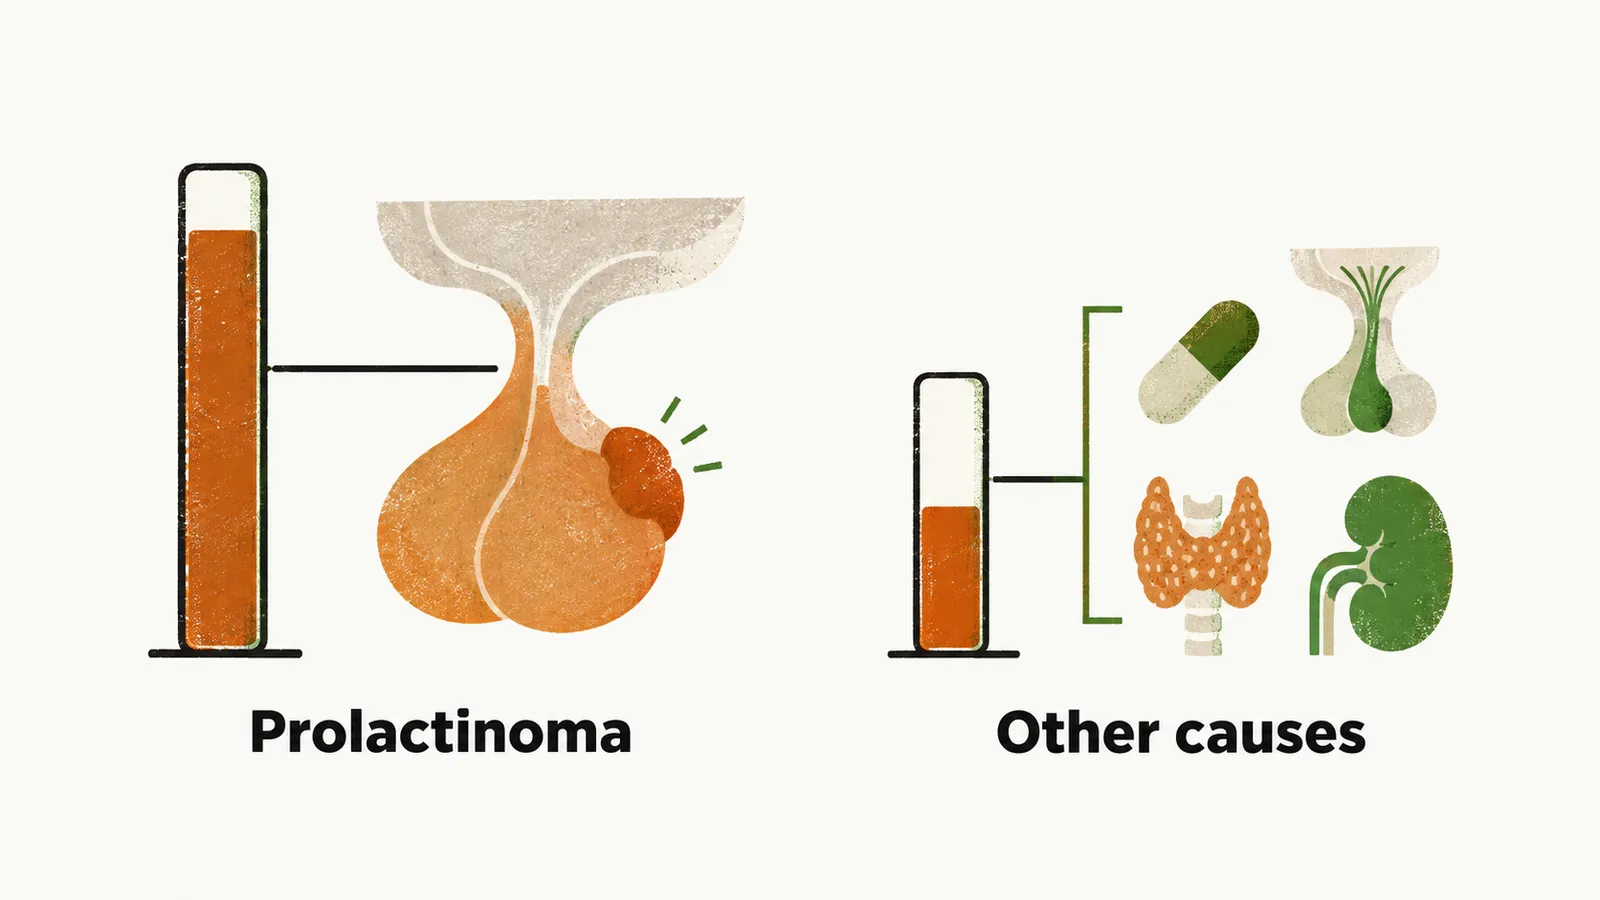
Once the physiological states are set aside, the size of the prolactin level helps narrow the pathological causes. Prolactinoma is the most common cause of a level greater than 200 microgram/L. Less pronounced hyperprolactinemia is mostly due to drugs, pituitary stalk compression, hypothyroidism, or renal failure. The dividing line is useful because these other causes rarely push the level to the very high values a prolactinoma can produce.
How can a lesion cut the brake?
A lesion in the hypothalamic-pituitary region can cut the brake in two ways. It can disrupt the dopaminergic cells that supply the brake, or it can affect the portal system that carries dopamine to the lactotrophs.
The usual mechanism is stalk compression. The pituitary stalk carries the portal blood. A mass resting on the stalk therefore blocks dopamine on its way to the lactotrophs. Prolactin rises even though the mass itself does not secrete prolactin, because the loss of the brake is enough. A newer proposal suggests that stalk compression may not be the whole explanation for some suprasellar tumours.
The lesions can be:
- tumours, mainly by compression of the pituitary stalk;
- cysts;
- infiltrative disorders, such as sarcoidosis;
- radiotherapy-induced damage.
Which drugs cut the brake?
A drug can cut the same brake, and many of the drugs that do so act on dopamine. Anti-dopaminergic drugs such as antipsychotics or antidepressants can cause hyperprolactinemia. Blocking D2 receptors releases lactotrophs from their normal inhibition. Many antipsychotics and antidepressants act on dopamine, so these drugs are best read as a group, and the list below gathers them by class, including those that do not raise prolactin.
- Typical antipsychotics that raise prolactin: haloperidol, chlorpromazine, thioridazine, thiothixene.
- Atypical antipsychotics that raise prolactin: risperidone, quetiapine, olanzapine.
- Atypical antipsychotics that do not raise prolactin: clozapine, aripiprazole, ziprasidone.
- Tricyclic antidepressant that raises prolactin: clomipramine.
- Monoamine oxidase inhibitors that raise prolactin: pargyline, clorgyline.
- Selective serotonin reuptake inhibitors that raise prolactin: sertraline, fluoxetine, paroxetine.
- Other psychotropics that raise prolactin: buspirone, alprazolam.
- Opiates and cocaine raise prolactin.
- Antihypertensive medications that raise prolactin: verapamil, methyldopa.
- Gastrointestinal medications that raise prolactin: metoclopramide, domperidone.
- Sexual steroids that raise prolactin: estrogens.
Other drugs act by different routes and should also be taken into account. Methyldopa inhibits dopamine production, and verapamil inhibits the release of dopamine. Estrogen is a drug that raises prolactin by the effect described above.
So what does a prolactin-secreting tumour do to the patient, beyond the level itself?