How much fat does a person carry? Fat cannot be read off the outside of the body, because it lies under the skin and around the organs inside the abdomen. So a measurement has to take one of two routes. It can look at the body itself, which is a direct method. Or it can measure some other property that changes with how much fat there is, which is an indirect method. Body fat is therefore measurable directly or estimable indirectly, and there are several ways to do either.
Which measures are easy, and which are accurate?
The two routes differ in cost and accuracy. Some methods are easy to use and cost-effective. Other methods are neither easy nor cost-effective, but they are the most accurate. Because the accurate methods need costly equipment, neither direct nor indirect methods are commonly used in practice.
How do direct methods see the fat?
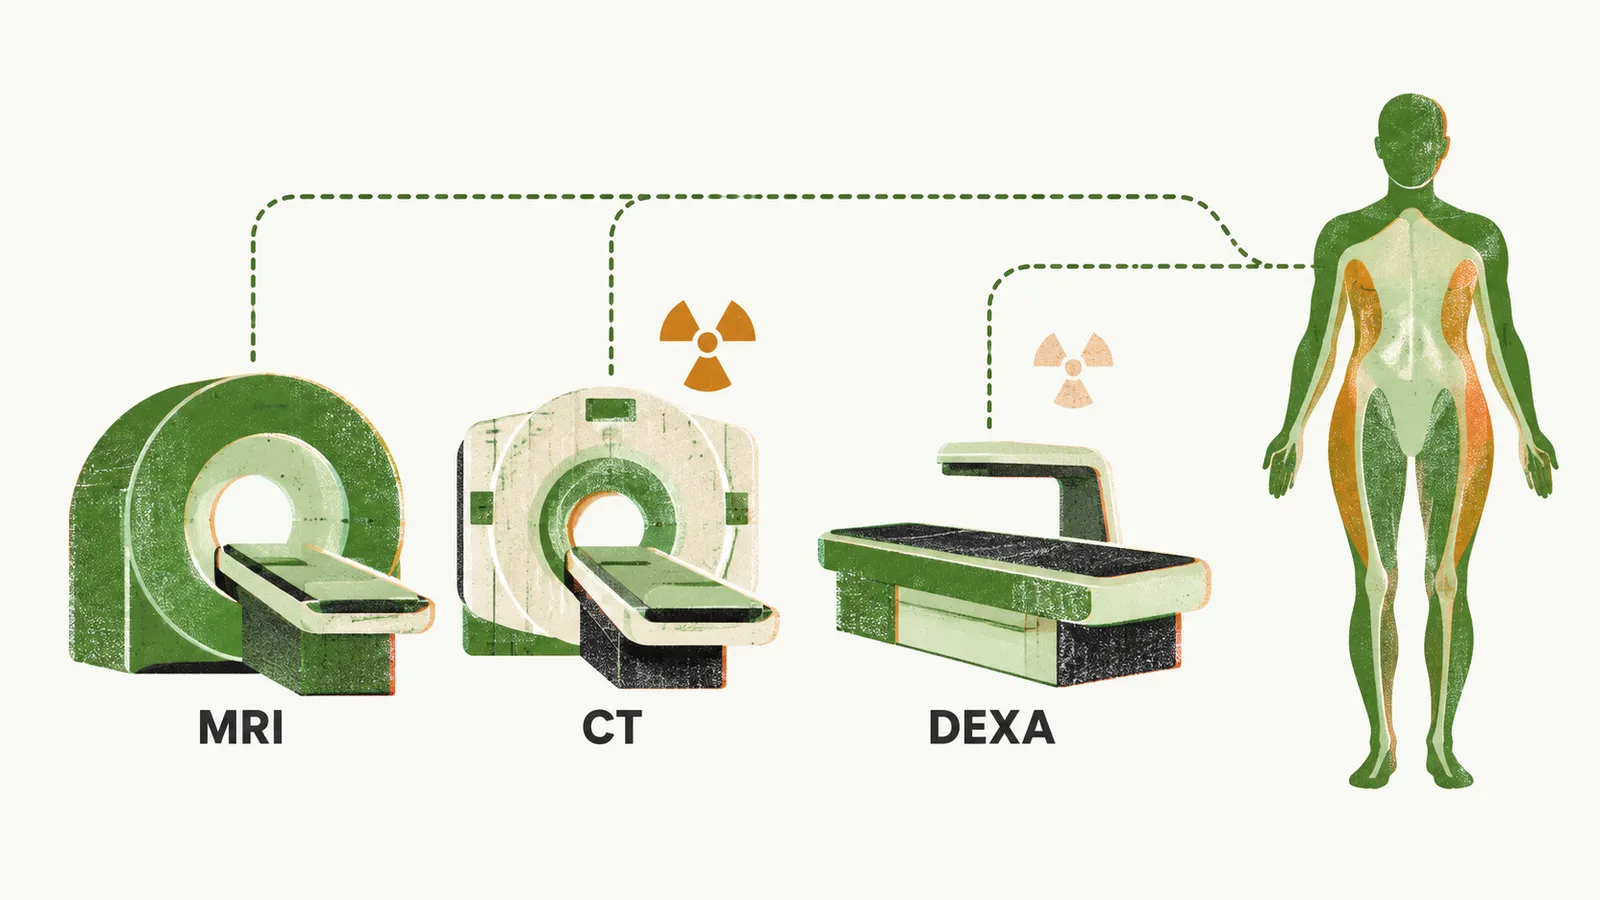
The accurate methods are the direct ones, so the next question is how they see fat. The direct methods are MRI, CT and DEXA (dual-energy X-ray absorptiometry). They measure fat mass by imaging or modelling the body itself. DEXA is a standard method for measuring body fat in clinical research.
What do MRI and CT separate?
MRI and CT quantify fat, and they can separate visceral from subcutaneous fat. An image can sort them by where they lie. That raises a cost question.
How much radiation does each scan give, and what does CT cost?
CT carries a substantial dose of ionising radiation, and it is costly. DEXA involves much less radiation.
How can fat be estimated from body density?
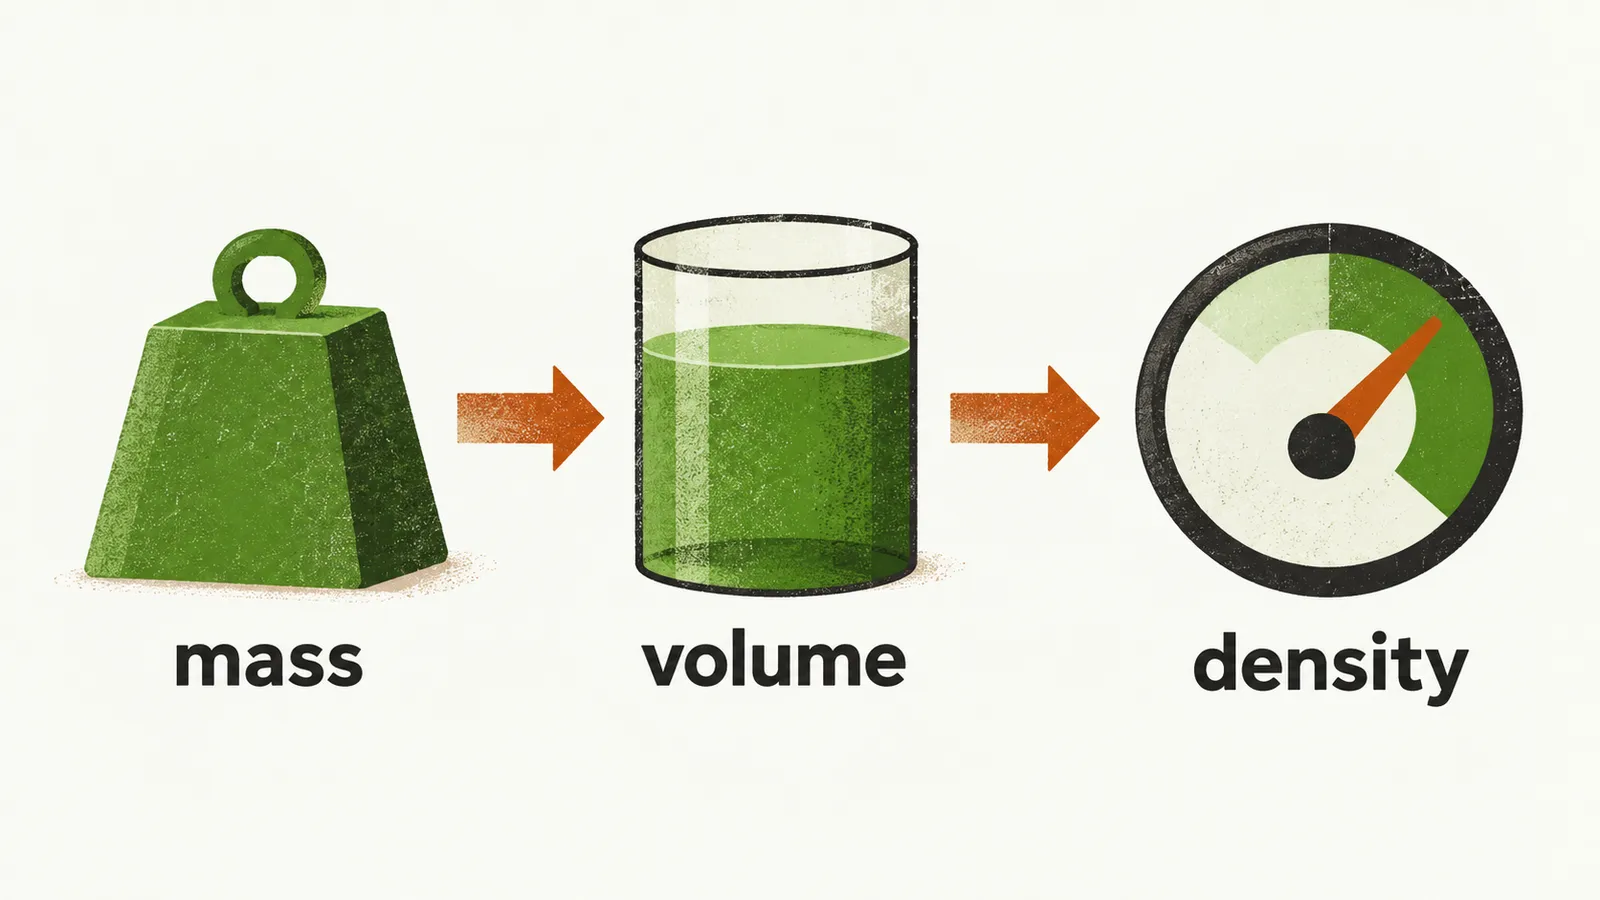
A method that cannot see fat must estimate it from another property. Indirect methods estimate fat from some other measurable property, such as density. Underwater weighing and air displacement (BODPOD) work from body density. Both assess the body’s mass and volume, and density follows from them.
How does electrical resistance give a fat estimate?
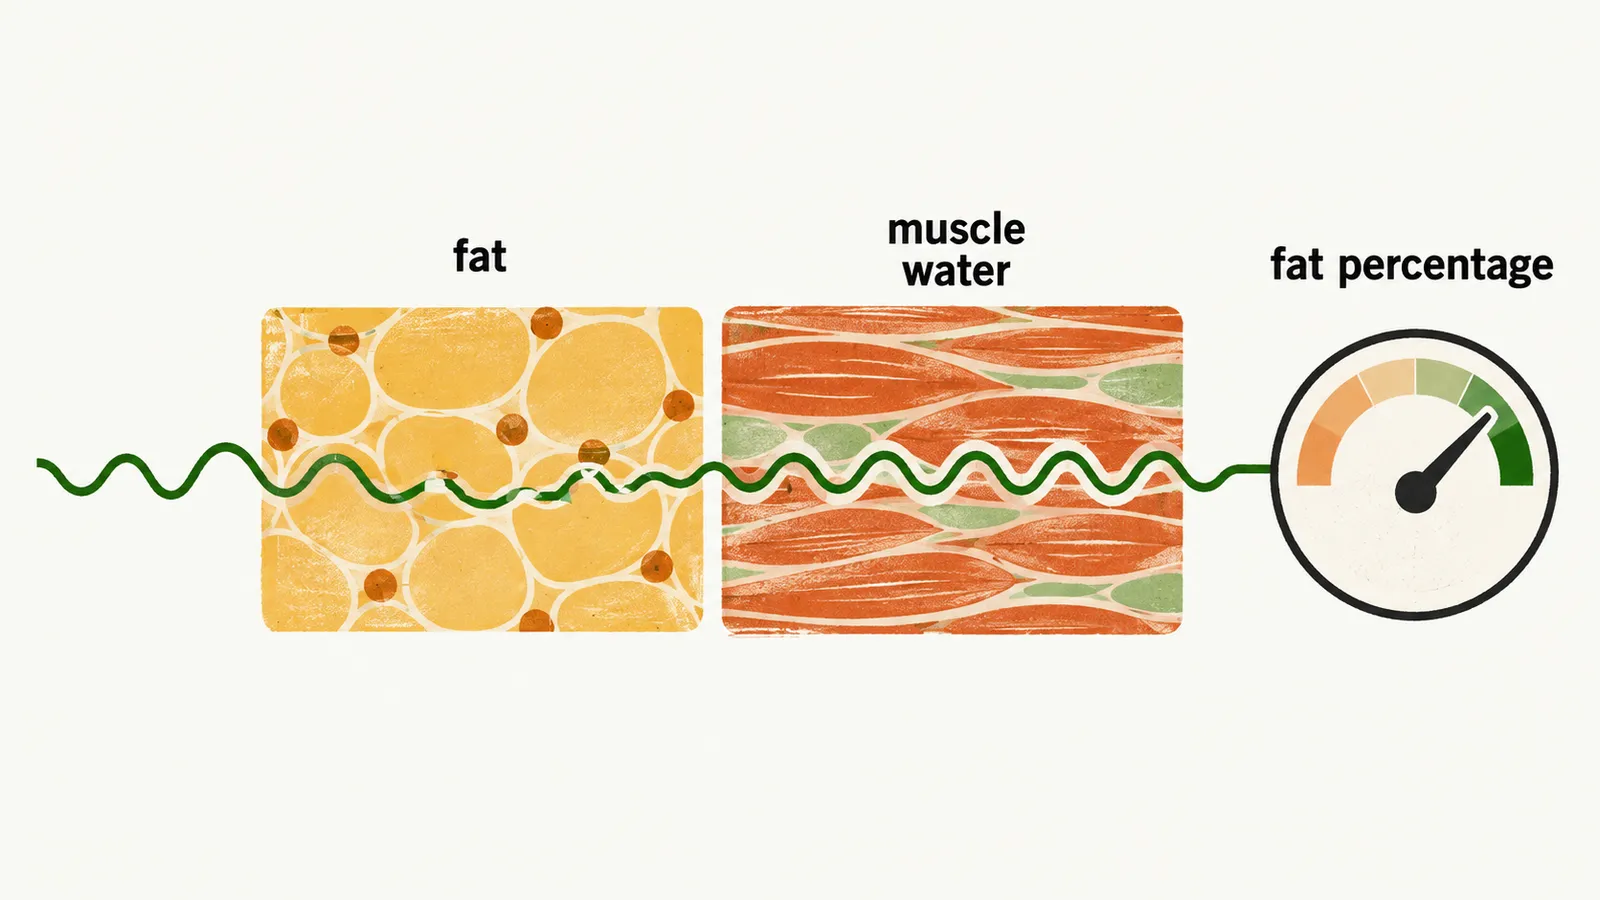
The next indirect route is electrical. Bioimpedance works from electrical resistance. BIA (bioimpedance analysis) sends a low-amplitude electrical current between two electrodes and measures the body’s resistance to it. Fat tissue is highly resistant to the signal, while muscle and water are highly conductive. The measured resistance can then be converted into an estimate of fat percentage.
What spoils the reading?
Because water conducts the current, the reading depends on body water content. Recent exercise and recent hydration interfere with the measurement. BIA estimates are also less accurate than those from DEXA, MRI or CT.
How does gas exchange reveal energy use?
The electrical route reads resistance, so the next indirect route measures energy use itself. Indirect calorimetry works from energy use. It estimates the calories used by measuring oxygen consumption (VO2) and carbon dioxide production (VCO2), rather than measuring fat directly.
What does the Weir equation convert?
The gas measurements give volumes, and the Weir formula turns them into energy expenditure: EE = [3.941 × VO2 + 1.106 × VCO2] × 1.44.
What does the respiratory quotient reveal?
The respiratory quotient (respiratory exchange ratio) is the VCO2/VO2 ratio, and it reflects the main fuel being used. It is close to 0.7 when fat dominates and close to 1 when carbohydrate dominates.
What does urinary nitrogen add?
Protein use is estimated from urinary nitrogen content, and the amount of urinary nitrogen is proportional to the amount of protein used for energy expenditure.
How much energy does the body use at rest?
The gas measurements give energy use, and much of it is spent at rest. BMR is the energy the body uses at rest.
How much of the day’s energy is spent at rest?
In a sedentary person, resting metabolic rate accounts for most of daily energy expenditure. Physical activity makes up the remainder.
How does body size change resting use?
Studies based on indirect calorimetry show that a higher BMI is associated with a higher BMR. The reverse also holds: weight loss means less energy is needed at rest. That is why a weight-loss diet must be modified after some weight is lost. The amount of food is reduced, to keep the loss going as BMR falls.
Why are BMI and waist used in everyday practice?
The accurate methods need costly equipment, so routine practice turns to simple measures. Everyday risk classification relies on BMI and waist circumference. The most commonly used index is BMI, which relates body weight to height. BMI is a measure of body weight in relation to height, as the earlier note Obesity: Epidemiology and Prevalence said.
How does BMI track fat, and where does it fail?
BMI is the most used index, and it works as a proxy for fat. It does not measure fat directly, because it relies on body weight alone. It correlates well with body fat percentage, except in individuals such as bodybuilders, whose weight includes a great deal of muscle. Its relation to fat percentage also depends on age, gender and race. So interpreting BMI as fat percentage depends on race, sex and age.
Do BMI cut-offs change between groups?
A proxy read against one set of cut-offs may not fit every group. As the earlier note on Obesity: Epidemiology and Prevalence said, BMI cut-offs are not the same for every population. BMI thresholds differ between countries and ethnicities. In the USA, men aged 20 to 29 with a BMI of 27.8 or more are considered overweight, and so are women aged 20 to 29 with a BMI of 27.3 or more. The WHO classification and risk assessment for hypertension and cardiovascular disease are mainly applicable to individuals of European ancestry. Thresholds are lower for Southern Asian countries, because central obesity and a higher fat percentage are more prevalent there.
What do the risk bands say?
The cut-offs set the bands. Risk is normal at a BMI of 18.5 to 23 kg/m2, slightly increased at 23 to 27.5 kg/m2, and highly increased at more than 27.5 kg/m2.
Why does waist add to BMI?
BMI cannot see where the fat sits, so the other important value for risk stratification is waist circumference. Central obesity is fat concentrated in the abdomen and trunk, as the earlier note on Obesity: Epidemiology and Prevalence said. Fat in the abdomen and trunk carries a higher risk of comorbidities than fat elsewhere. A patient with a normal BMI but a waist circumference outside the normal range is still considered obese.
What are the waist cut-offs?
The waist is read against its own cut-offs. Risk rises above these waist circumferences:
- Americans: more than 102 cm in men, more than 88 cm in women.
- Europeans: more than 94 cm in men, more than 80 cm in women.
- South Asians: more than 90 cm in men, more than 80 cm in women.
What do these measures leave out?
These measures describe how much fat a person carries and where it sits. They do not explain why some people accumulate fat and keep it. That depends in part on how the brain regulates hunger and satiety, so what in the brain controls hunger and fullness, and with it how much fat is kept?