
Appetite is set in the brain. The brain weighs hunger and satiety signals coming from the body, and that is why obesity is not just a metabolic disorder. Obesity progression and pathogenesis may also have a neuropsychological basis.
How does the brain decide to eat?
If appetite is set in the brain, we must ask what signals reach it. Eating is controlled by anorexigenic (satiety) and orexigenic (hunger) signals. They push in opposite directions, one lowering appetite and one raising it, so eating depends on which one wins.
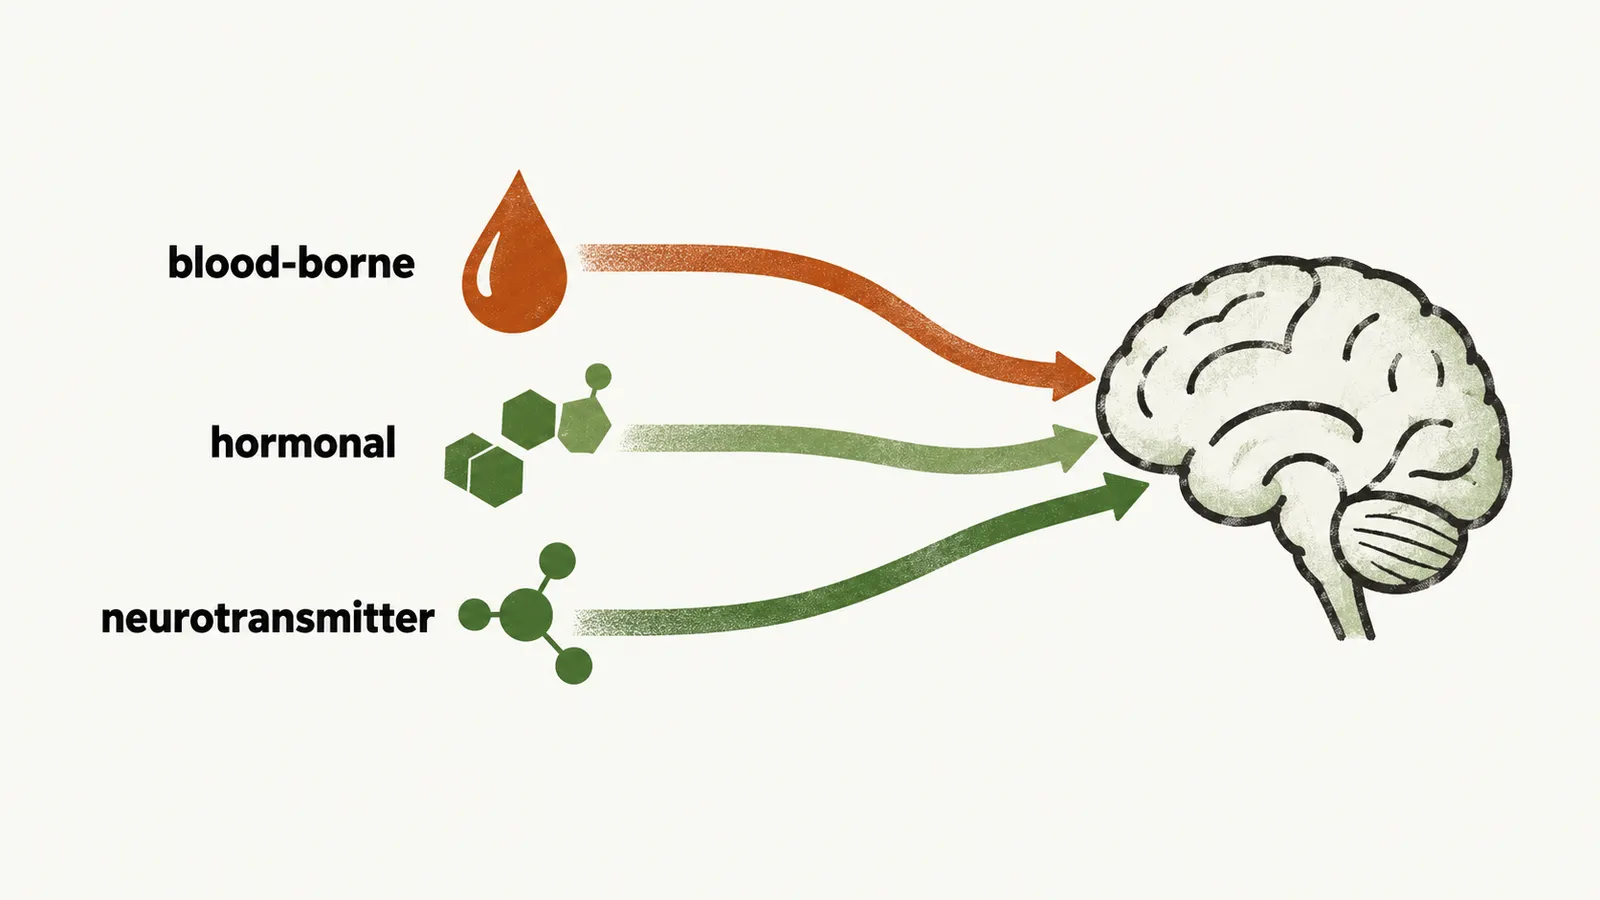
A signal changes eating once it reaches the brain, where it is interpreted as the desire to eat. The signals come in three kinds:
- blood-borne, for example the blood glucose level;
- hormonal, for example leptin and insulin;
- neurotransmitter, for example dopamine, a messenger of the reward circuit, so a signal acting through dopamine changes how good food feels and not only whether the body needs energy.
Why are there two kinds of circuit?
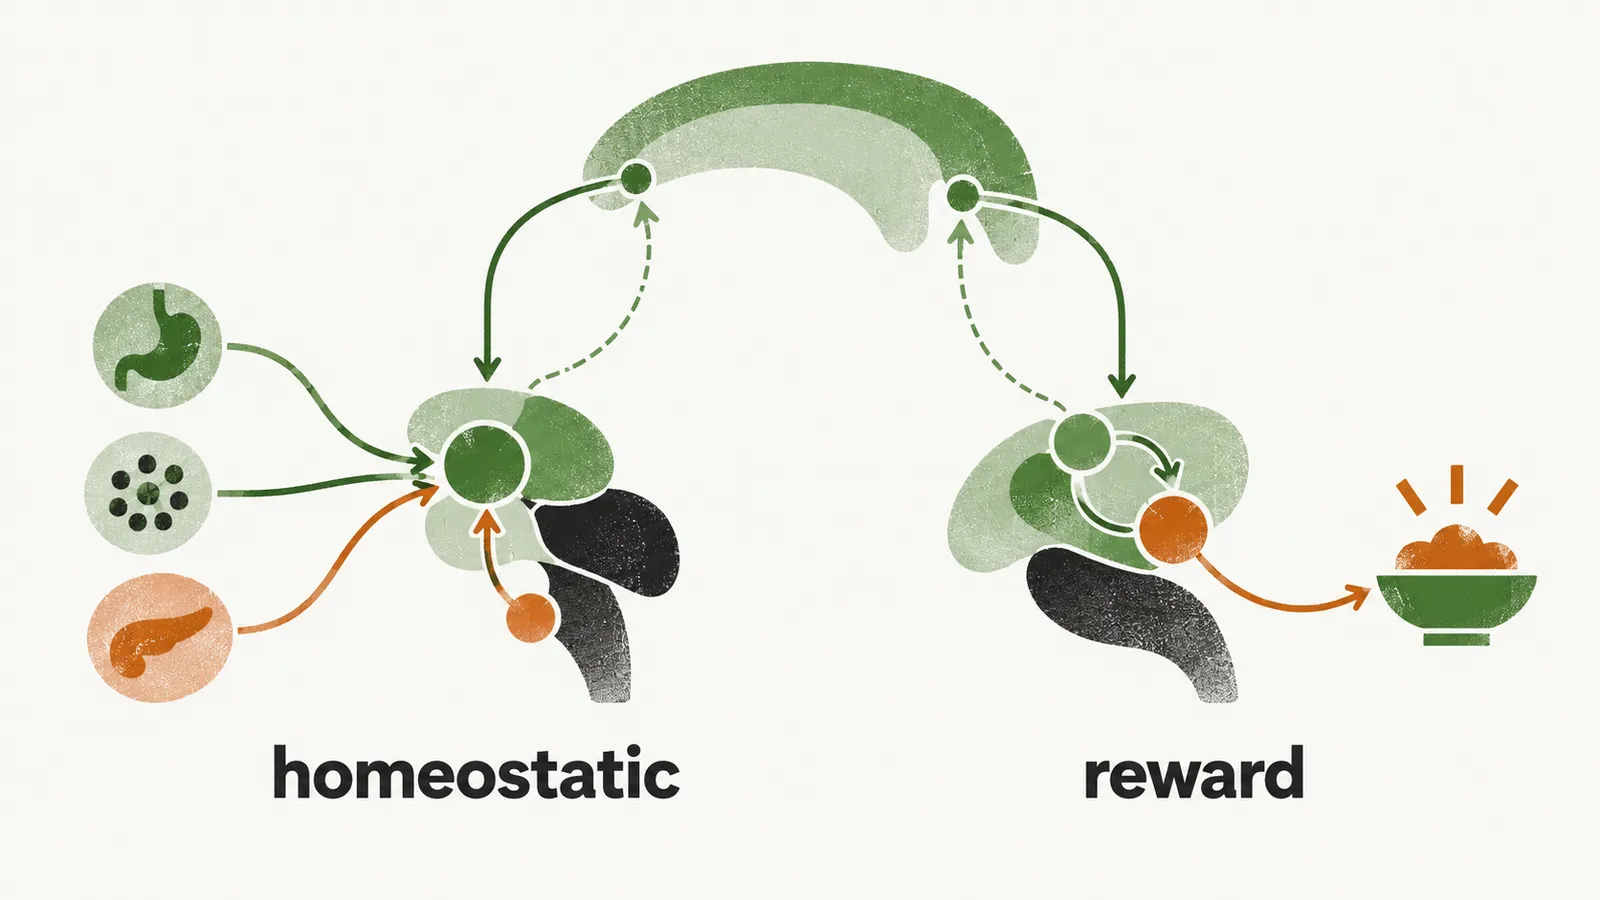
The signals reach a homeostatic circuit, but not all eating is homeostatic. The hunger-controlling brain regions fall into two groups. One group is homeostatic, and another responds to the pleasure of food.
The older circuits, in the hypothalamus and midbrain, are homeostatic, and they are found in all mammals and preserved through evolution. The reward circuit responds to the pleasure of food and not to the body’s energy need, so it is non-homeostatic. The newer circuits are cortical regions sitting above the older ones. They are non-homeostatic too, and they are found in humans.
Where do the hunger and fullness signals meet?
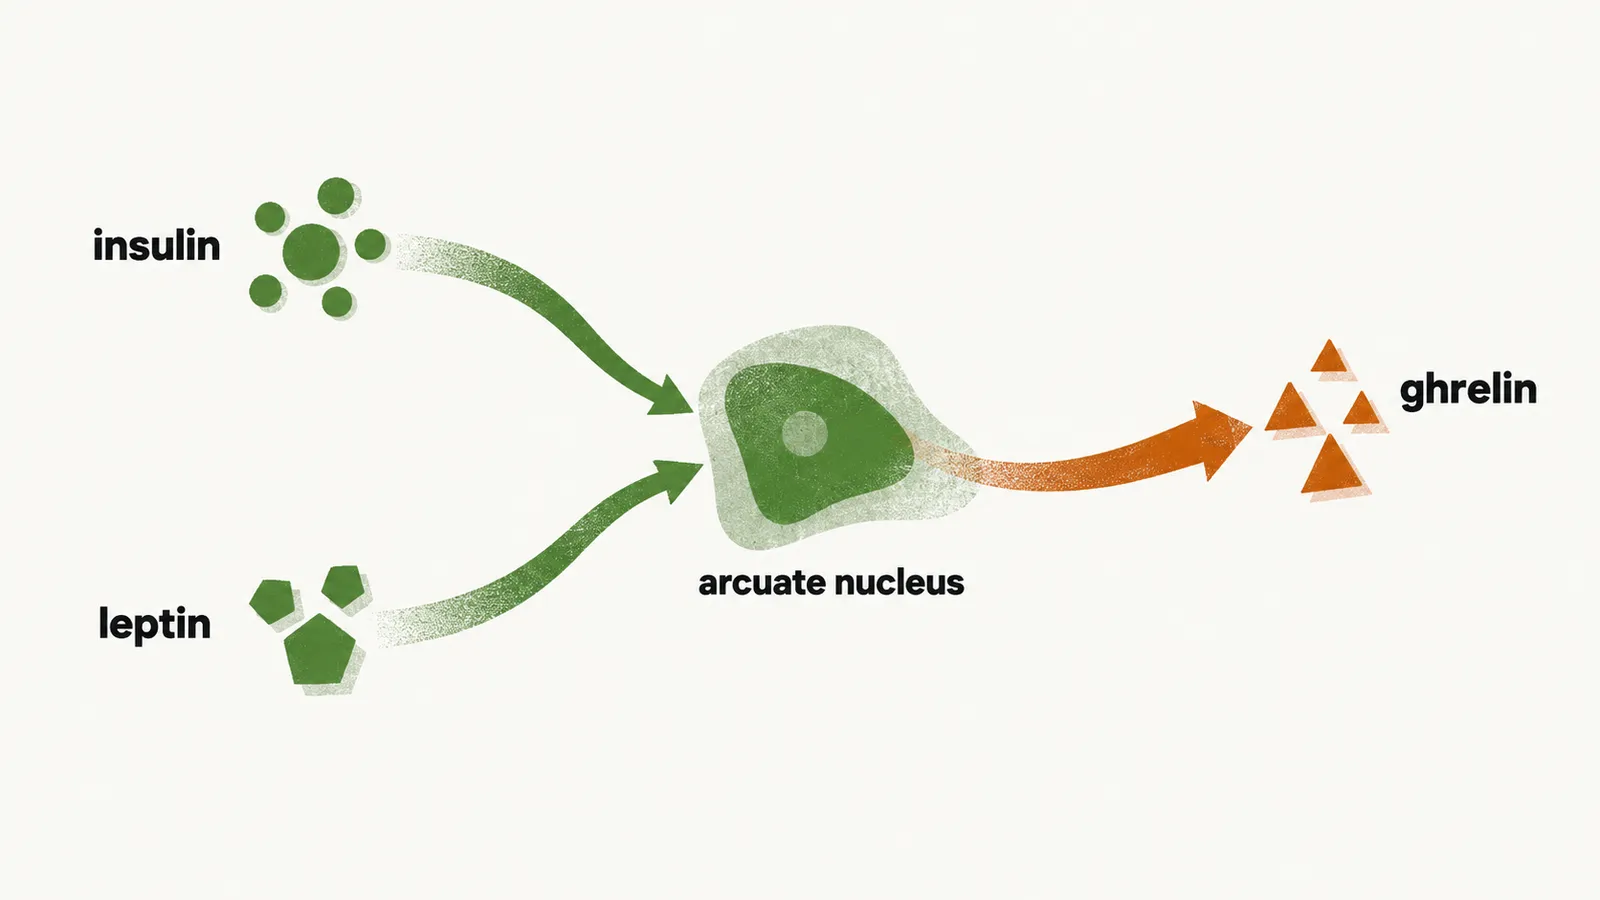
The main region of the homeostatic circuit is the arcuate nucleus in the hypothalamus. It is the main region that responds to anorexigenic and orexigenic signals. So this is where body signals meet the control of eating.
The arcuate nucleus receives three signals in particular: insulin, leptin and ghrelin. Insulin and leptin are satiety signals, and ghrelin is an orexigenic hormone, so both kinds of signal reach the same region.
What does insulin do there, and why does it stop working?
Physiologically insulin is a satiety signal. It acts on the hypothalamus in a way that resembles leptin, so in the brain it works like a satiety signal.
In obese patients the CNS is resistant to insulin because of chronic hyperinsulinaemia, a persistently high insulin level. A receptor kept under constant high stimulation tends to turn down its response. As the brain no longer responds, the suppressive effect of insulin on hunger is lost.
What does leptin do, and why does it stop working?
Physiologically leptin is a satiety signal. It reaches the arcuate neurons and acts there to reduce appetite.
A chronically high leptin level makes the CNS resistant to leptin. The logic is the same as for insulin: the hypothalamic response is turned down under constant high levels. So the appetite suppression by leptin is lost in obese patients.
What does ghrelin do, and why does it not switch off?
Ghrelin is physiologically an orexigenic signal that induces hunger. It is released from the oxyntic cells of the stomach, and eating normally stops that release. This is why ghrelin falls after a meal.
In obese patients this fall in ghrelin release after food intake does not occur.
Why does reward matter as well?
The hormones act on the arcuate nucleus, but food also acts on a reward circuit. Besides the arcuate nucleus, the other important homeostatic region in appetite control is the limbic system, especially the amygdala and hippocampus. These regions lie beside the hypothalamus and add reward and memory to the decision to eat.
They are under the control of dopaminergic neurons forming a reward-based system, so reward influences hunger alongside the homeostatic circuit. In obese patients one can speak of addiction to food, or at least to some particular foods.
Particular foods induce dopamine release from these regions and manipulate hunger and appetite through reward. Eating is considered rewarding, which reinforces motivated behaviour.
Do the hormones also reach the reward circuit?
They appear to. It is proposed that homeostatic signals are integrated by these dopamine neurons. Leptin and insulin inhibit the dopaminergic neurons. Ghrelin stimulates dopamine release, in the opposite direction, so hunger may also make food more attractive.
What does GLP-1 add?
The reward circuit and the arcuate nucleus are not the only routes, because GLP-1 acts on both. GLP-1 (glucagon-like peptide-1) is a further hormonal factor in appetite control, alongside insulin, leptin and ghrelin.
It is released by L-cells of the intestine and by some brain cells in response to food intake. It reduces appetite, delays stomach emptying and increases intestinal secretion, among other effects. Released in the brain, it can suppress food intake.
GLP-1 released in the brain comes from neurons of the nucleus tractus solitarius (NTS). These neurons project directly to reward regions. GLP-1 acts on the ventral tegmental area (VTA) to reduce high-fat diet intake; the VTA is part of the dopamine reward system, so this is a proposed route by which GLP-1 reduces the pull of food. GLP-1 also acts on the hypothalamus and on the nucleus accumbens.
What does the cortex add, and why does its brake fail?
Newer cortical regions above the older neuronal regions also affect appetite. The cortex controls the older circuits and gives feedback to them.
The most important region is the orbitofrontal cortex, which suppresses food intake. In obese patients the orbitofrontal cortex is not able to decrease appetite strongly enough.
Failure of these braking signals is one route by which fat accumulates and persists. A proposed explanation is that a weaker brake lets the reward pull on the older circuits go unchecked. If the brain keeps pushing for food and the brake is weak, what does the extra fat do to the rest of the body?