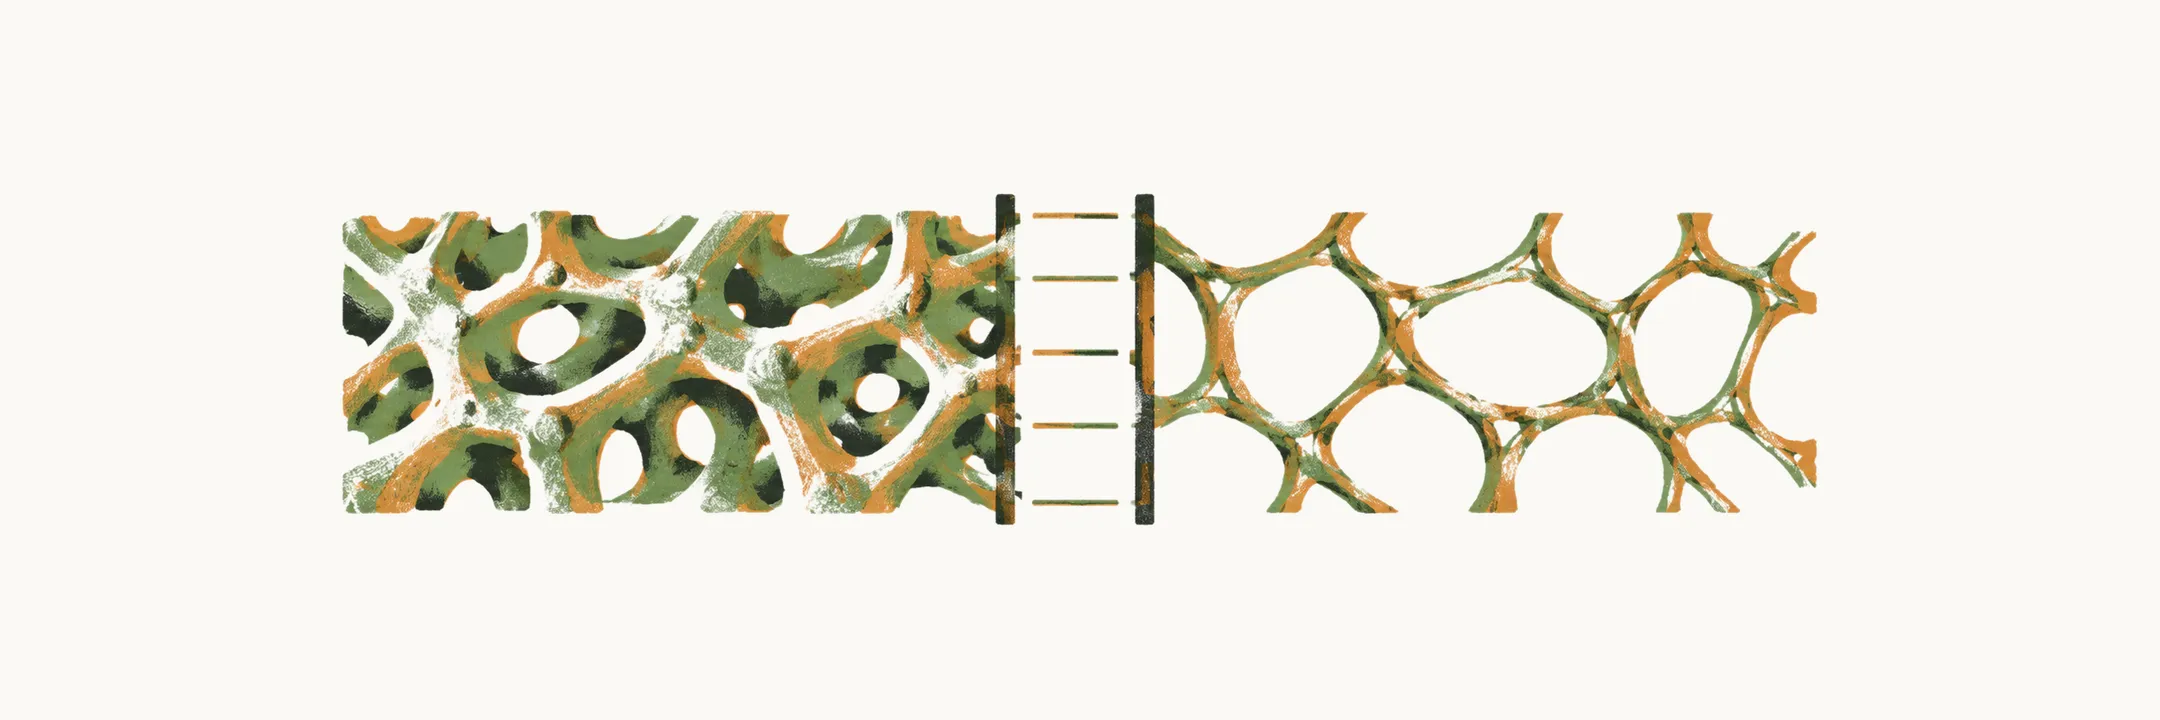
Osteoporosis is a disorder of reduced bone strength. Bone strength is the load a bone can carry before it fails, and a fracture happens when a force, such as one from a fall, meets bone too weak to carry it. A bone’s strength comes from how much mineral it holds, from how that mineral is arranged (a lattice of struts inside and a hard shell outside), and from the quality of the bone material itself. A scan measures the first of these. So density explains part of the risk and never all of it, and the other parts have to be added before the risk can be read properly.
That is why whether a person with osteoporosis fractures depends on more than one factor. The factors that matter most also differ by skeletal site.
Why is bone density the strongest single predictor?
Of those factors, density is the one this section starts with. Low bone mineral density is the strongest single predictor of hip and spine fractures. Bone mineral density is the amount of mineral in a given area or volume of bone, as the earlier note explained.
The relationship between density and fracture is continuous. Risk is expressed as a relative risk for each standard deviation that density falls below the young-adult mean, so density works as a scale and not as a yes-or-no test. At almost any skeletal site, each standard deviation below that mean is associated with a nearly two-fold higher risk of hip fracture. The relationship holds all the way below the mean, without a threshold. A density measurement is informative even in someone who has not yet fractured.
How is bone density measured?
Density comes from a scan, so the next question is what the scan actually sees. Density is usually measured by dual-energy X-ray absorptiometry (DXA), the routine means of predicting fracture risk from density.
A DXA image is flat, so it records mineral per area of the projected bone. This is areal BMD. Volumetric BMD is density per volume, and it is reported by quantitative computed tomography (QCT). Peripheral QCT is called pQCT.
Is bone density the whole of bone strength?
A scan sees mineral, and strength also depends on the structure that mineral forms. Density is not the whole of bone strength. Deficits in cortical and trabecular microarchitecture raise short-term fracture risk independently of DXA BMD and FRAX.
Two further cautions follow. Not every determinant of bone strength can be measured. And not every measurable determinant is a proven risk factor.
Which other factors raise the risk of hip fracture?
Density is not the only factor that matters for the hip. The risk factors for hip fracture are:
- age over 65 years
- a history of spine or hip fracture
- a maternal history of hip fracture
- weight loss after the age of 50
- low body mass index
- poor neuromuscular function
Which factors raise fracture risk apart from density?
Some of these factors act even when density is the same. The clinical risk factors that act on fracture risk independently of density include:
- older age
- any previous fracture
- a higher number of previous fractures
- more severe previous fractures
- the conditions that make falling more likely
How are the other parts of bone strength measured?
Some of the missing parts can be read from images or markers. The table shows which, and how sure the field is about each. A ”+/-” or a ”?” in the second column marks a factor whose status as a risk factor is uncertain.
Two tools in the table need a name. TBS is the trabecular bone score, a measure of trabecular connectivity derived from the DXA image. It reads the grey-level texture of the spine DXA image, and that texture is proposed to reflect how the trabeculae are laid out. VFA is vertebral fracture assessment.
| Factor | Recognised risk factor | Clinically measurable |
|---|---|---|
| Areal BMD | Yes | Yes (DXA) |
| Volumetric BMD | Yes | Yes (QCT) |
| Microcracks | No | No (histology) |
| Trabecular connectivity | Yes | Yes (TBS, DXA) |
| Periosteal circumference | No | Yes (pQCT/DXA) |
| Cortical thickness | +/- | Yes (pQCT/DXA) |
| Bone turnover | Yes | Yes (markers) |
| Previous osteoporotic fracture | Yes | Yes (radiographs or VFA) |
| Mineralization and cortical porosity | ? | No/yes (back scatter EM), sometimes with high resolution microCT |
Two rows deserve a comment. The hip fails in bending, in torsion, or by local buckling, which happens in the case of excessive cortical thinning. Even so, cortical thickness stays uncertain as a risk factor in the table. And bone turnover is the rate at which bone is rebuilt. Bone is rebuilt continuously, with resorption and formation coupled at varying rates, and markers measure that rate.
What does FRAX combine, and what does it leave out?
The tool that brings the measurable factors together is FRAX. FRAX is the best tool for putting these pieces together. It combines femoral neck bone mineral density with clinical risk factors. These clinical risk factors include previous fracture, glucocorticoid intake, alcohol consumption and others. Glucocorticoids impair bone formation and enhance bone resorption, so they push the balance of remodelling the wrong way.
FRAX gives a 10-year probability of hip fracture and of major osteoporotic fracture. Density remains its main predictor because density is quantitative.
FRAX cannot weigh fully the qualitative properties of bone. It is built from the clinical risk factors and femoral neck density, so a property of bone that is not one of those inputs is not weighed.
Which qualities of bone does FRAX not weigh?
FRAX has no input for these qualities:
- bone turnover rate
- trabecular bone connectivity
- cortical and periosteal bone size
- skeletal morphometry
This matters because two people can have the same bone mineral density and still differ in risk. The one whose trabecular network is more disrupted has less of the internal architecture that carries load. What makes bone turnover and its lattice change in the first place?