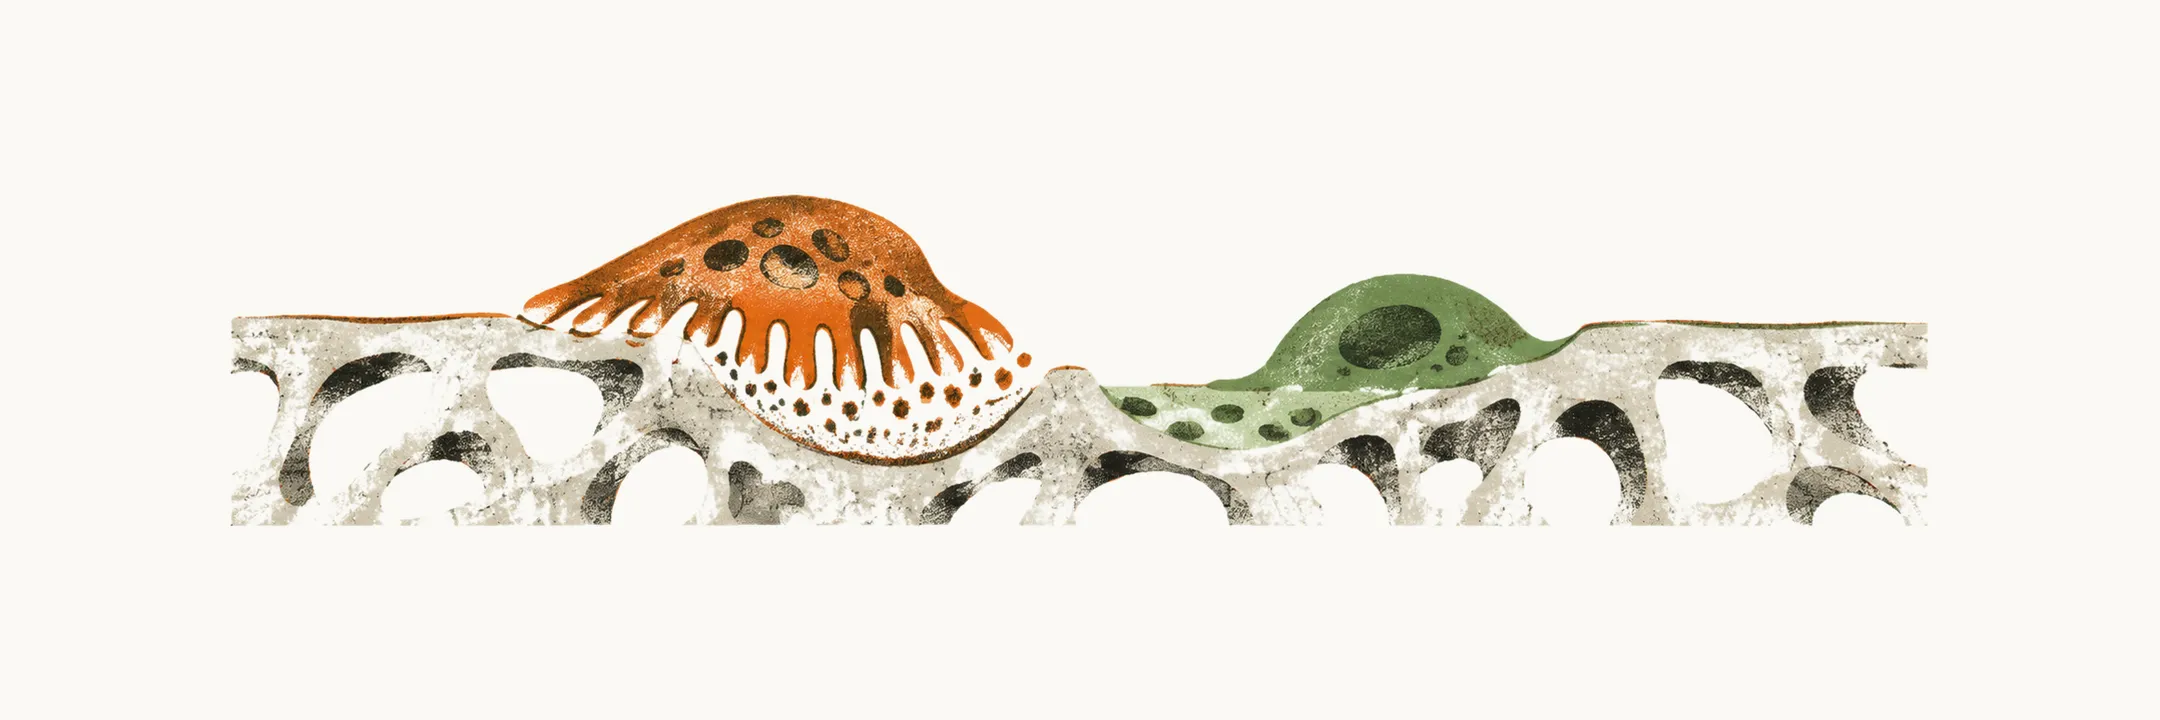
Bone is living tissue that is rebuilt all the time. A small amount of old bone is removed and new bone is laid down in the same place, and this cycle runs across the whole skeleton. Adult BMD is the end result of two processes: peak bone mass acquired in adolescence, and bone loss in middle and later years.
Bone is not finished when growth ends, so the density an adult has is what was built earlier, less what has been lost since. Peak bone mass is one of the strongest determinants of fracture decades later. Anything that lowers peak bone mass or accelerates later loss lowers the density at which a person eventually fractures. So the starting level matters, and the next question is when it is built.
When is peak bone mass built, and who builds more?
Peak bone mass is the highest BMD a person ever attains, and it is reached during puberty. Two states reduce BMD sharply. One is the years of rapid linear growth in adolescence, when the expanding skeleton temporarily outruns mineralisation. The other is the years after the menopause in women.
Boys and girls do not build the same amount. Peak bone mass is higher at all skeletal sites in boys than in girls, and boys reach it about two years later than girls. Part of the male advantage reflects a larger cross-sectional bone area.
Timing matters as much as size. The gonadal steroid surge matters in its timing as much as in its size. The window in which bone formation is favoured lasts no more than about three years. A person who goes through puberty late reaches lower peak BMD and lower stature than one with normally timed puberty. This is an association; late puberty is linked with lower bone mass at maturity, and it is not shown to cause it.
What decides how much bone is built?
Puberty sets the window; what fills it? Peak mass is built from several inputs at once, so none of them decides it alone. The determinants are nutrition, including calcium and vitamin D; growth hormone and IGF-I (insulin-like growth factor I); estradiol and testosterone; and genetics.
Genetics is the largest single influence, and at least 50% of peak bone mass is determined by genetic factors. BMD is a polygenic trait shaped by gene–gene and gene–environment interaction. Identifying the individual genes has proved difficult.
Why does estradiol matter in both sexes?
Estradiol is one of those inputs, and men who lack it show why. Estradiol is required for peak density in both sexes. It closes the epiphyseal plates. Aromatase deficiency is a rare disorder in which humans have too little estrogen, so men who lack aromatase, or a functional estrogen receptor, show what the skeleton is like without estradiol: they are tall with unfused epiphyses and very low bone mass.
How does diabetes interfere with peak mass?
Not every input is hormonal; diabetes in youth can interfere with the same building. Type 1 diabetes, especially when it begins in childhood or adolescence, is associated with low bone mass and higher fracture risk. It disrupts musculoskeletal development during the years when peak bone mass is acquired, so the deficit falls on the building phase. It disrupts the marrow niche and uncouples remodelling, so formation no longer keeps pace with resorption during those years.
Type 2 diabetes carries roughly a 20% higher fracture risk even though areal BMD is normal. Its fractures are usually peripheral.
What happens to bone once peak mass is reached?
After peak mass, bone is renewed, and renewal is what keeps it strong. What happens to bone after peak mass depends on how it is renewed, which is the work of remodelling. Density is not the whole of bone strength, as the fracture-risk note explains.
Bone remodelling is the continuous cycle in which a small volume of bone is resorbed and then replaced at the same site. Because the two halves act at the same site, the bone removed is replaced. Resorption demineralises bone, and that is how remodelling releases calcium into the extracellular fluid on demand. After growth, the skeleton keeps its strength by replacing its own bone, so remodelling renews bone so that it keeps its elasticity and strength, matching it to the stresses placed on it.
Remodelling is more active in trabecular bone, for example in the vertebrae and proximal femur. Trabecular bone has much greater surface area and lies close to the marrow. The marrow is the most metabolically active compartment of the skeleton.
Who runs the remodelling cycle?
Renewal needs a controller. Coordination of the remodelling cycle rests with the osteocyte. Osteocytes sense fluid shifts and microcracks, which is how the skeleton detects mechanical load and damage. They release the signals that start a new remodelling cycle. The osteocyte is therefore a mechanosensor and orchestrator, the cell that links load and damage to the next round of remodelling.
The osteocyte comes from the osteoblast. After osteoblasts lay down new matrix, some are enclosed by it and become osteocytes. Osteocytes are less metabolically active than osteoblasts but remain central.
Osteocytes and marrow stromal cells are the main source of RANKL.
What sets how fast bone is resorbed?
Resorption is the first half of the cycle; something sets its rate. RANKL drives osteoclast precursors to differentiate into bone-resorbing osteoclasts. Osteoprotegerin (OPG) is a soluble decoy receptor made by osteoblasts. It binds RANKL and prevents it from activating the osteoclast. RANKL and OPG act on the same pathway that controls osteoclast differentiation, so the RANKL–OPG balance sets the rate of resorption.
How is formation kept in step?
The same cycle has a brake on formation. Once resorption is under way, the osteoclast signals back to osteoblast precursors through Wnt and sphingosine. Osteocytes restrain the same pathway by secreting sclerostin, which blocks Wnt signalling inside the osteoblast. Sclerostin binds the Wnt co-receptor Lrp5/6 and suppresses bone formation, which makes it the osteocyte brake on the osteoblast. Sclerostin has become a drug target because of this restraint.
Activated osteoblasts release IGF-I, IGF-II and TGF-β (transforming growth factor beta), which recruit further osteoblasts to the site. Growth factors deposited in the matrix during formation are stored there and released again during the next resorption. This storage and release is one way the cycle is kept coupled.
Where do the bone-forming cells come from?
Formation depends on having bone-forming cells, and their fate is set early. The fate of a new bone cell is decided before it forms. Mesenchymal stem cells become osteoblasts under the transcription factors RUNX2 and Osx. The same cells become adipocytes under PPARγ. Osteoblasts and fat cells come from the same marrow progenitors, so any signal that pushes the decision toward fat removes potential bone-forming cells, and defective osteoblast differentiation is associated with increased marrow adipogenesis. Glucocorticoid excess is accompanied both by fewer osteoblasts and by more fat in the marrow.
What happens when formation falls behind?
When formation keeps pace, the cycle is balanced; when it does not, each cycle leaves less. In healthy bone, resorption and formation are coupled, so the bone removed in each cycle is replaced. In osteoporosis, resorption and formation are uncoupled and resorption predominates. Every cycle then leaves the skeleton with slightly less bone.
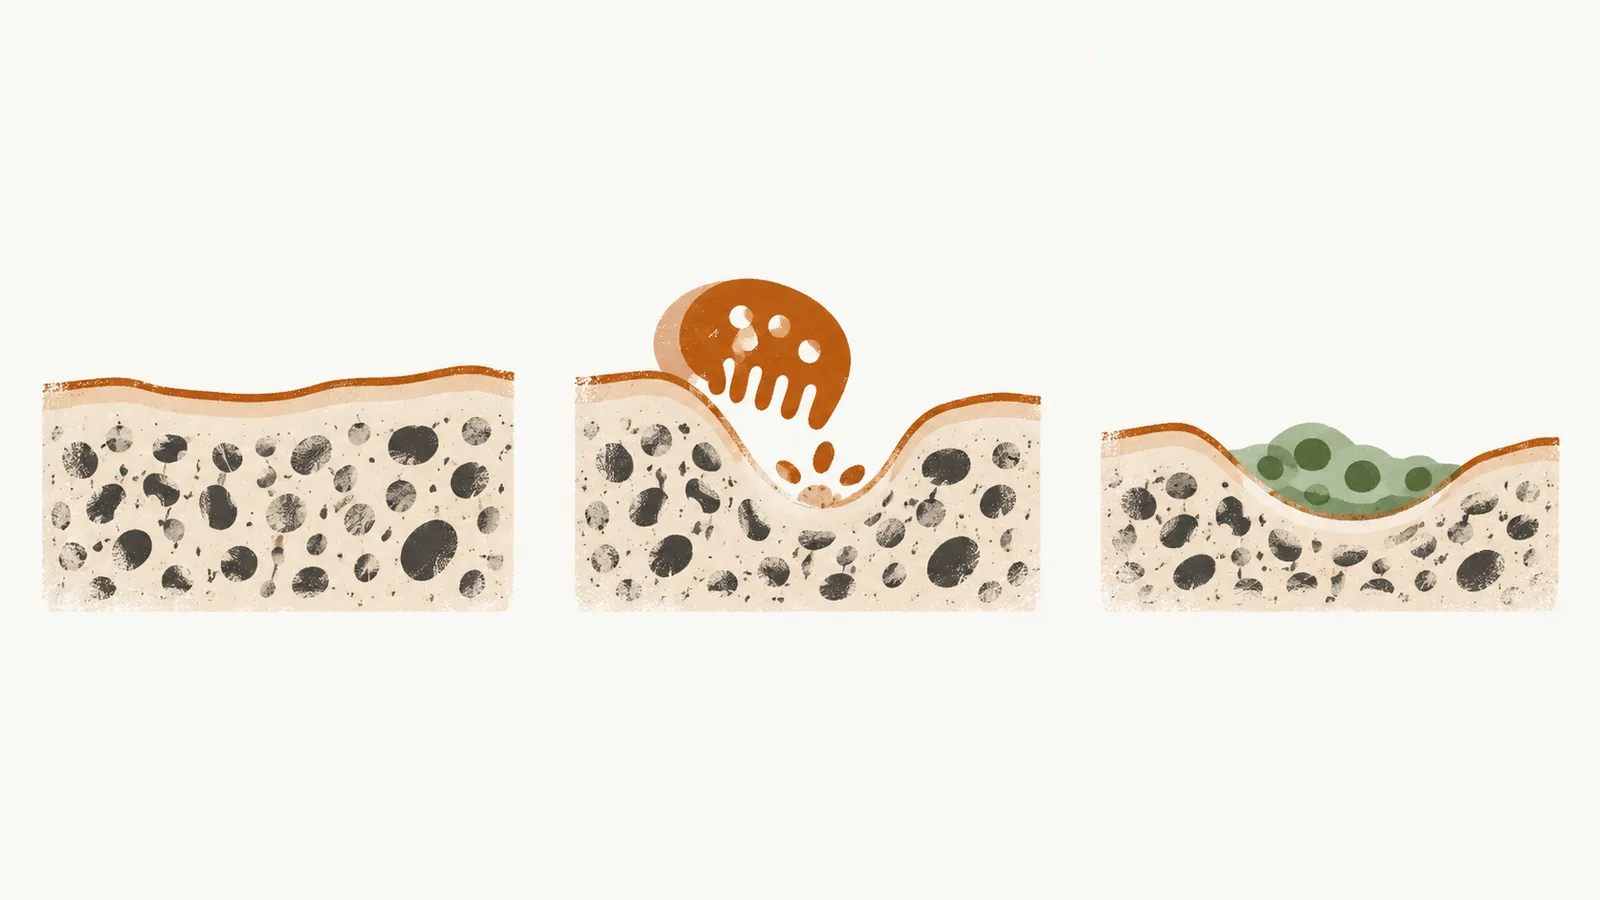
Time works against repair. Resorption takes only about 10 to 13 days, whereas formation takes months. So once the cycle accelerates, destruction outruns repair. What tips remodelling toward resorption differs by setting.
What tips the balance in primary osteoporosis?
After the menopause it is estrogen. Loss of estrogen is the most important driver of primary osteoporosis; estrogen loss at the menopause is the single most important driver. Estrogen deficiency is a pivotal cause of postmenopausal bone loss, and it explains the steep bone loss of the years immediately after menopause. In a small fraction of women, estrogen loss is unusually rapid. Two signals are thought to contribute to this rapid loss. The first is the fall in estrogen itself, since estrogen deficiency causes bone loss that estrogen replacement can prevent.
How could losing estrogen speed bone loss?
The steep loss after the menopause needs a mechanism, and the exact molecular link between the fall in estrogen and bone loss is not settled. Some studies suggest estrogen normally restrains transcription of IL-6. IL-6 promotes resorption. On that view, losing estrogen removes that brake.
Is estradiol needed in men too?
The estrogen point is not limited to women, and here the support from the clinic is stronger. Men with an aromatase mutation or a mutated estrogen receptor develop severe osteoporosis. These men cannot make or respond to estradiol despite normal testosterone. In men, estradiol is responsible for effects once attributed to testosterone. So estradiol, not testosterone alone, is the key hormone for the skeleton in both sexes.
Is there a second signal?
A second signal is proposed for the fast loss: follicle-stimulating hormone (FSH). In a mouse model, high FSH was associated with greater bone loss independently of estrogen. This FSH link has not been confirmed in humans.
What do calcium and vitamin D change?
Remodelling also responds to the calcium supply. Among people in their 80s and 90s, and especially women, a serum 25-hydroxyvitamin D level below 20 ng/mL leads to secondary hyperparathyroidism. The low calcium supply drives PTH up. PTH stimulates osteoblasts and provokes remodelling. Each cycle needs formation matched to resorption so that the bone removed is replaced, but bone formation in the elderly does not rise in step with resorption. The cycle becomes further uncoupled and bone loss accelerates.
Why are glucocorticoids such a strong cause?
A drug can tip the balance too, and glucocorticoids do it quickly. They are the second most common cause of low bone mass in the general population, and one of the most common causes of osteoporotic fracture. Glucocorticoids act through several routes at once. Some are indirect, through parathyroid and gonadal hormones and calcium handling; others act directly on bone cells.
Bone loss begins within the first few months of therapy. Glucocorticoid-induced bone loss is both rapid and sustained. The early loss is followed by a more gradual loss, partly due to decreased osteoblastogenesis and osteoblast and osteocyte apoptosis.
How do they act through hormones and calcium?
Some of their effects are indirect. Each of the following routes ends in bone loss:
- Glucocorticoids increase PTH secretion, which increases bone resorption and decreases bone formation, causing rapid loss of bone.
- They decrease luteinizing hormone and FSH secretion, which increases bone resorption due to loss of estrogen.
- They impair calcium absorption because of decreased 1,25-dihydroxyvitamin D, which increases PTH and bone resorption.
- They increase calcium loss in urine, which causes a secondary increase in PTH and bone resorption.
How do they act on bone cells?
Others act directly on the cells that build and remove bone. Glucocorticoids acutely suppress osteoblasts and cause apoptosis, inhibiting osteoblastogenesis and promoting apoptosis of osteoblasts and osteocytes. This reduces bone formation and causes gradual bone loss. They also stimulate osteoclastogenesis, increasing bone resorption and causing rapid loss of bone.
Why does bone loss go unnoticed?
Bone loss gives no symptoms of its own. The disorder usually first shows itself through what it does to the skeleton. If the loss makes no noise, what does a person first notice, and how does the history point toward the cause?