
Osteoporosis weakens bone by lowering its density and disrupting its structure, as the earlier epidemiology note explained. Treatment has a single aim: to reduce the risk of fracture.
Bone is never finished. It is renewed all the time by remodelling, in which osteoclasts remove old bone and osteoblasts lay new bone in its place, as the pathophysiology note explained. In osteoporosis that balance shifts toward removal, so the bone thins and its structure weakens. Every osteoporosis drug acts on that one cycle, and every drug is judged by the same result: it works if fewer bones break.
Why is a normal scan not the goal?
Bone mineral density is used to follow the response to treatment. It is the amount of mineral in a given area, measured by DXA, as the diagnosis note described. The target is not a normal scan.
Why not? A person who has already fractured, or who has a very low density, remains at high risk even if treatment raises the density into the normal range. The reason is that the deterioration in bone architecture persists, and, as the fracture-risk note explained, density is not the whole of bone strength. So treatment is continued and the risk reassessed, rather than stopped when the numbers improve.
What does every person at risk do?
Density is a number to follow, so the next question is what a person does alongside any drug. Everyone at risk, whether or not on medication, is advised on measures that support bone health and reduce the chance of falling.
Calcium is one of them. The total intake should be 1000 mg/day for men aged 50–70 years, and 1200 mg/day for women aged 51 and over and men aged 71 and over. It is taken from the diet where possible, and as supplements where not. Vitamin D is given at 800–1000 units/day, with the aim of a serum 25-hydroxyvitamin D of at least 30 ng/mL.
The other measures are:
- Stopping smoking and moderating alcohol intake.
- Weight-bearing and muscle-strengthening exercise, together with balance training.
- Removing or reducing the causes of falls: sedating medications, postural hypotension, poor vision and hazards in the home.
The last item matters because a fall puts a large force on the hip, as the epidemiology note explained. These measures are not a substitute for drugs in a patient who has already fractured or who has osteoporosis by densitometry.
When is a drug offered?
Because the non-drug measures do not replace a drug for those patients, the next question is who is offered a drug. Pharmacological treatment is considered in postmenopausal women and men aged 50 years or older with any of the following:
- A hip or vertebral fracture, regardless of T-score.
- A fracture of the pelvis, proximal humerus or distal forearm, together with low bone mass.
- A T-score ≤ -2.5 at the femoral neck, total hip, lumbar spine or 33% radius.
- Low bone mass with a FRAX 10-year probability of major osteoporotic fracture of 20% or more, or of hip fracture of 3% or more.
The T-score and FRAX were explained in the earlier diagnosis and fracture-risk notes. The same thresholds are used to diagnose osteoporosis in the diagnosis note. Here they mark the point at which treatment is worth starting.
What are the two families of drugs?
The thresholds say who needs a drug. The drugs themselves act on the cycle of renewal, and they fall into two families.
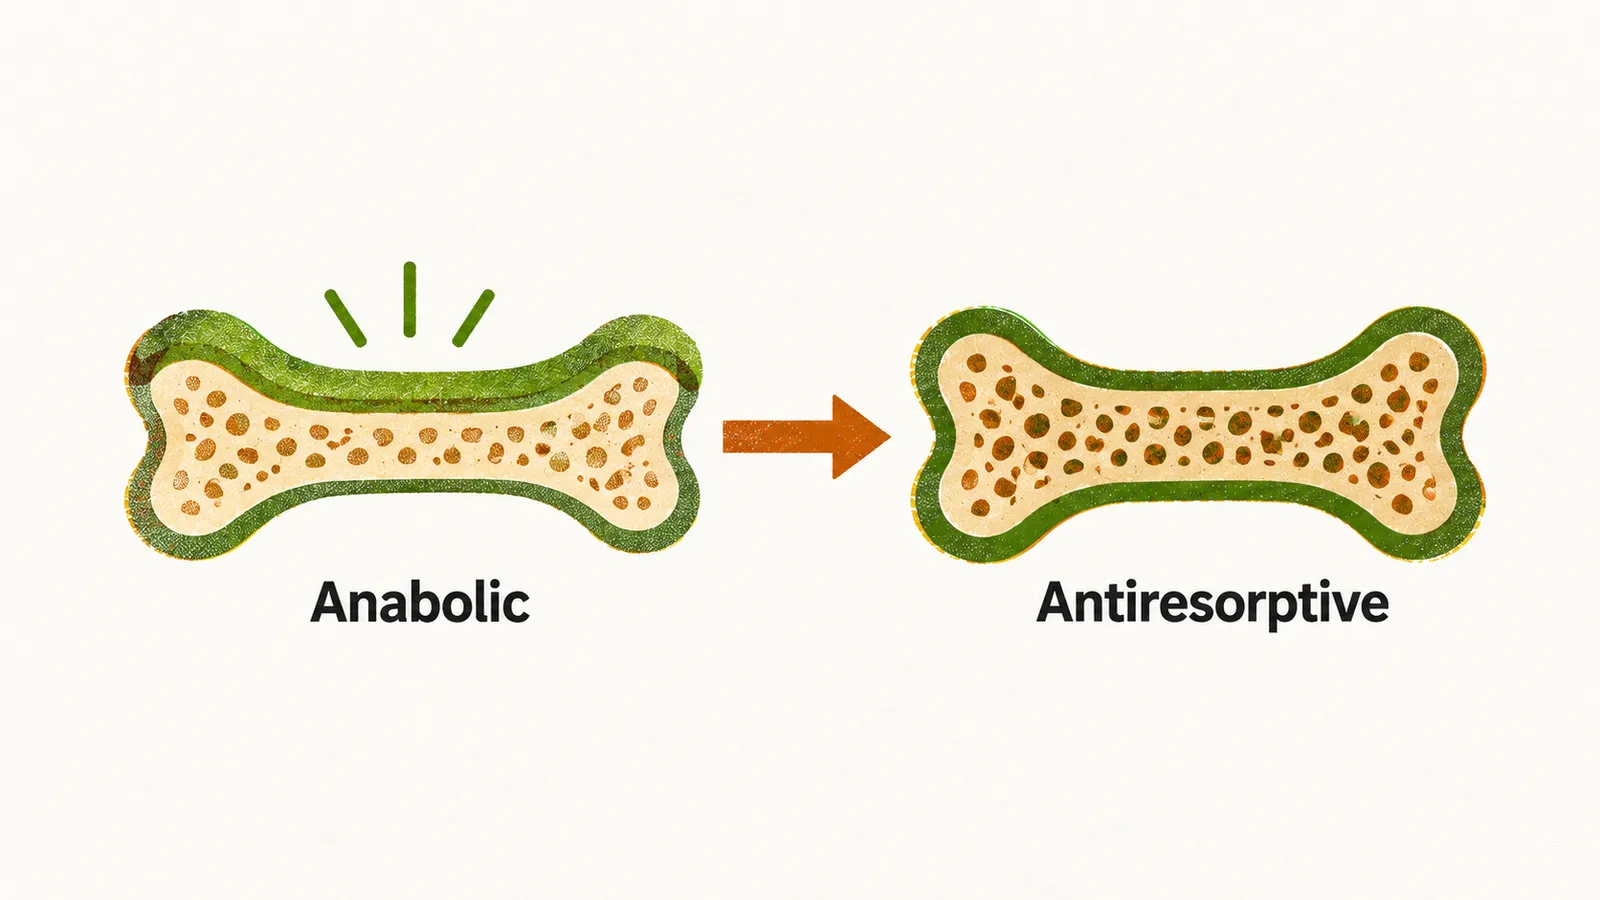
Antiresorptives slow bone loss by suppressing osteoclast activity. They hold on to the bone that is there, but they do not build new bone. Anabolics build bone by stimulating osteoblasts, so the skeleton gains bone. That difference is why the two families are not used in the same way.
A bisphosphonate is an antiresorptive that sits in the bone. As the osteoclast removes that bone, the drug is released and impairs the osteoclast’s ability to continue bone resorption.
Which drug is started first?
For most patients at high risk, treatment begins with an oral bisphosphonate, alendronate or risedronate. The next question is how it is taken.
Both are given orally once a week, and also daily or monthly. They are taken on an empty stomach with plain water, and the patient stays upright for 30 minutes. Food is likely to reduce how much of the drug is absorbed, and the drug can cause esophagitis.
Both are contraindicated if the eGFR is below 30–35 mL/min. The drug is primarily excreted through the kidneys, so when they filter poorly it builds up.
Ibandronate is another bisphosphonate, given orally every month or intravenously every 3 months. It reduces vertebral fractures but not non-vertebral fractures.
What if a tablet cannot be taken?
The oral route has limits, and those limits are the reason an alternative is needed. Oral bisphosphonates cannot be used in some patients, for example with uncontrolled esophageal disease, which makes an irritating tablet unsafe, or with an eGFR below 30–35 mL/min, where the drug would build up.
Where the oral route is unsuitable, intravenous zoledronic acid is used. A drug given into a vein avoids the problems of absorption and of irritation of the gullet. The dose is 5 mg once a year. It has the same renal contraindication as the oral drugs, and a flu-like reaction is common after the first dose.
Denosumab is the alternative antiresorptive, preferred when oral bisphosphonates cannot be used. It is a monoclonal antibody and, unlike a bisphosphonate, it does not bind to bone matrix. It is not swallowed, so the oral limits do not apply.
Why does a bisphosphonate keep working after a dose?
A bisphosphonate binds to bone mineral and stays bound for a long time. When an osteoclast removes that bone, the drug is released and acts on the cell. So its effect outlasts the dose.
This makes a pause possible. Bisphosphonates are the only osteoporosis drugs that can be temporarily paused, because the drug stays in bone and a pause in dosing does not end its effect at once. After 5 years of oral treatment or 3 years of intravenous treatment, a patient who is no longer at high risk, with a T-score above -2.5 and no new fracture, can stop. This is a drug holiday, and protection continues while the drug stays bound in bone. A patient who remains at high risk continues, up to 10 years on an oral bisphosphonate or 6 years on annual intravenous zoledronic acid.
What happens when denosumab is stopped?
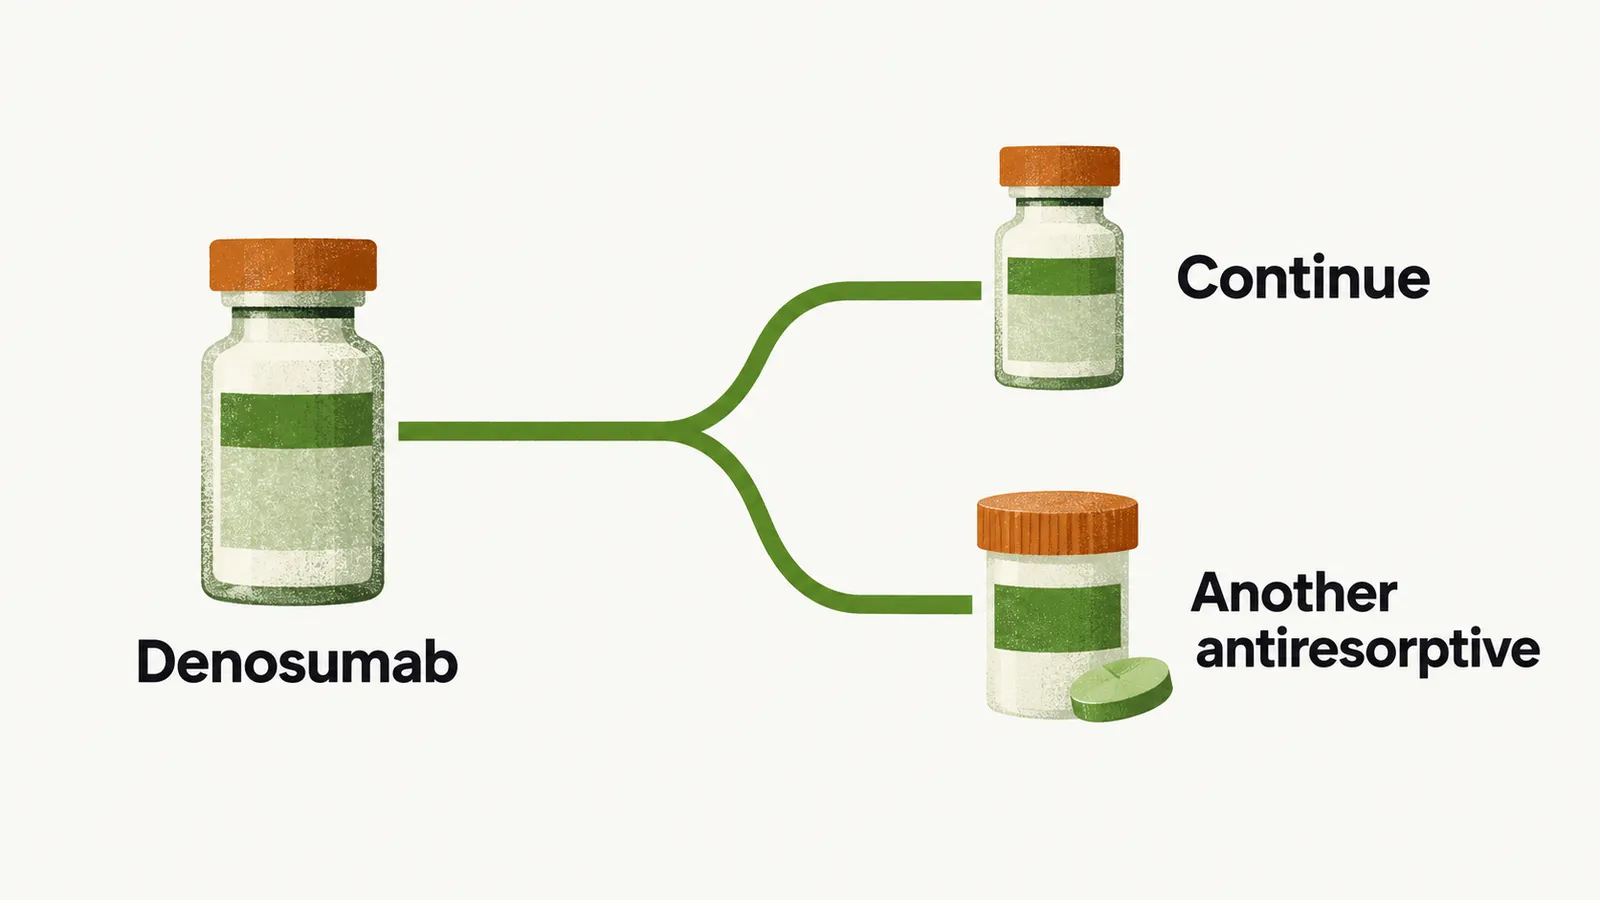
A bisphosphonate that is bound in bone keeps acting, but denosumab is the exception, because its effect does not stay in bone. Denosumab is a RANKL inhibitor and an antiresorptive, given as 60 mg subcutaneously every 6 months. It blocks RANKL, the signal that drives osteoclast formation.
Denosumab does not bind to the bone matrix, so its effects are reversible. The effect disappears within months of the next missed dose, and once the drug stops, the bone gains from treatment are rapidly lost. Stopping denosumab can therefore cause rapid bone loss and multiple vertebral fractures.
For this reason denosumab must not be paused. It is either continued long term or followed immediately by another antiresorptive.
Who needs an anabolic drug first?
An antiresorptive holds the bone that is there, so for some patients the bone has to be built up first. These are patients at very high risk: those with multiple vertebral fractures, a recent fracture, or a very low T-score. For them an antiresorptive alone may not lower the risk enough.
Treatment therefore starts with an anabolic agent for 1 to 2 years, followed by an antiresorptive to hold the gain. The order in which drugs are given matters. An anabolic agent works less well after a potent antiresorptive. In a study of the bisphosphonate tiludronate, the anabolic effect of parathyroid hormone was blunted when bone resorption was blocked. A proposed explanation is that active resorption is needed for the anabolic effect. So when the two are combined in sequence, the anabolic is given first and the antiresorptive afterwards.
What do the anabolic drugs do?
For very high risk, the anabolic drugs are the ones given first, so the next question is what each of them is and what it needs.
- Teriparatide is a parathyroid hormone (PTH) analog, given as 20 µg subcutaneously daily.
- Abaloparatide is a parathyroid hormone-related protein (PTHrP) analog, given as 80 µg subcutaneously daily, and used as for teriparatide.
- Romosozumab is a sclerostin inhibitor, given as 210 mg subcutaneously monthly for 12 months.
Teriparatide is followed by an antiresorptive, so the anabolic builds and the antiresorptive keeps what was built. It is avoided with skeletal malignancy, Paget’s disease, previous skeletal radiotherapy, and in a raised alkaline phosphatase of unknown cause.
Romosozumab carries a cardiovascular warning. In a trial against alendronate it showed a numerical imbalance in major cardiovascular events in the first year. That is why it is avoided in patients who had a myocardial infarction or stroke in the previous year.
Which weaker options remain?
When the first-line drugs cannot be used, a weaker option is kept for specific reasons. Raloxifene and calcitonin are weaker options that reduce vertebral but not non-vertebral fractures. They are reserved for patients who cannot take first-line drugs or who have an additional reason to prefer them.
Raloxifene is a selective estrogen receptor modulator, given as 60 mg orally daily. A high risk of breast cancer is an example of an additional reason to prefer it. It reduces vertebral fractures but not non-vertebral fractures, and it increases venous thromboembolism.
Calcitonin is an antiresorptive, given as 200 units intranasally daily. It is second line and reduces vertebral fractures only.
Estrogen or estrogen–progestin therapy is also an antiresorptive, in various doses. Estrogen is used mainly for younger postmenopausal women with vasomotor symptoms who cannot take a bisphosphonate or denosumab. A progestin is required with estrogen if the uterus is intact.
Which rare harms limit how long treatment runs?
Choosing a drug and its order is part of the decision. How long the drug is given matters too. Adverse effects are uncommon, but two matter because they shape how long treatment is continued: osteonecrosis of the jaw and atypical femoral fracture.
Both occur rarely with antiresorptives and become more likely with longer treatment. Osteonecrosis of the jaw is thought to follow trauma to bone that has limited capacity to heal under the effect of the drug. Atypical femoral fracture is thought to follow long suppression of bone turnover, so that microfractures are no longer repaired. The risk of either is far smaller than the fracture risk of leaving osteoporosis untreated.
What is checked, and how is treatment followed?
The long-term harms make the length of treatment matter, so the question is what must be checked along the way.
Hypocalcemia must be corrected before a bisphosphonate or denosumab is given. Denosumab inhibits osteoclast resorption, which lowers the calcium released from bone into the blood, so a patient who is already low in calcium can become lower still.
Bone mineral density is re-measured 1 to 2 years after treatment is started or changed, and the patient is reassessed periodically. Adherence is checked at every encounter. A large proportion of patients stop treatment within the first year, and non-adherence is itself associated with more fractures. What keeps a patient on treatment?