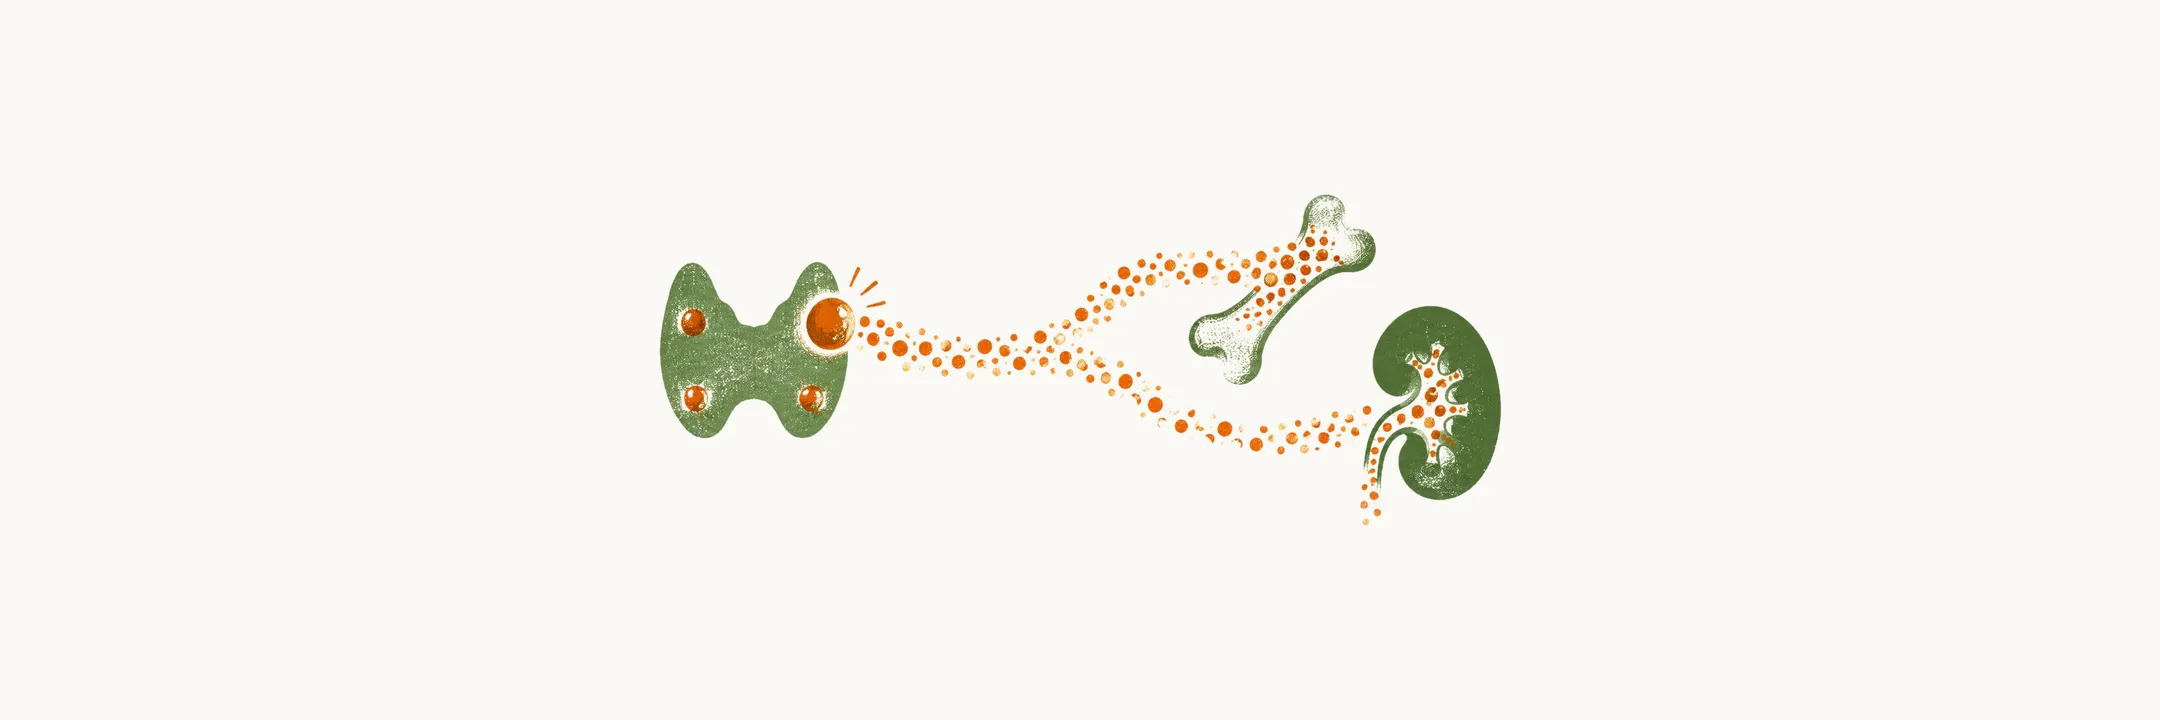
Primary hyperparathyroidism (PHPT) means a high blood calcium together with a PTH level that is high or inappropriately normal. It arises when one or more parathyroid glands make too much PTH. It is one of the most common causes of hypercalcemia.
What question do the satellites answer?
The question is this: what happens when one or more glands keep making PTH while the blood calcium is high, and where does the extra calcium show? Calcium and PTH act on many tissues, and the effects of PHPT spread across organ systems. They reach the skeleton, the kidneys, and the cardiovascular, nervous and gastrointestinal systems. Clinical presentation of primary hyperparathyroidism explains how PTH raises blood calcium through bone, kidney and gut.
Where do the satellites fit?
The question has five parts, and each part is one satellite. They are listed in learning order.
- Epidemiology and pathogenesis of primary hyperparathyroidism: where the glands sit, who develops PHPT, and how one or more glands come to overproduce PTH.
- Clinical presentation of primary hyperparathyroidism: how PHPT shows across the kidney, heart, nervous system and gut, and the disorders linked with it.
- Bone disease in primary hyperparathyroidism: the skeletal changes, the cortical-predominant loss of bone, and why fractures are site-specific.
- Unusual forms of primary hyperparathyroidism: the neonatal forms linked to CaSR mutations, PHPT in pregnancy, acute PHPT or parathyroid crisis, parathyroid carcinoma and parathyromatosis.
- Diagnosis and treatment of primary hyperparathyroidism: the biochemical grounds for diagnosis, how PHPT differs from secondary and tertiary hyperparathyroidism and from hypercalcemia of malignancy, the workup, and the criteria that make surgery first-line for asymptomatic patients.
Where should you start?
Start with the first satellite, because the satellites lean on one another and the first one holds the glands and the set point that the rest use. So the first question is this: where do the glands sit, who gets the disease, and how does one gland start making too much PTH?