Bone is not a fixed frame. It is rebuilt all the time: osteoclasts take bone away and osteoblasts lay new bone down in its place. The skeleton is one of the main targets of PTH, as the clinical presentation note showed. In primary hyperparathyroidism (PHPT), excess PTH raises bone turnover. It does this through the bone-removing cells, not by dissolving bone directly: PTH makes bone-forming cells send signals that produce more osteoclasts, so bone resorption rises.
Which part of the bone does the extra PTH reach?
If turnover speeds up everywhere, does bone disappear everywhere equally? No, because bone comes in two parts that do not respond in the same way.
- Cortical bone is the dense outer shell of the long bones.
- Trabecular bone is the spongy network inside the vertebrae and at the ends of the long bones.
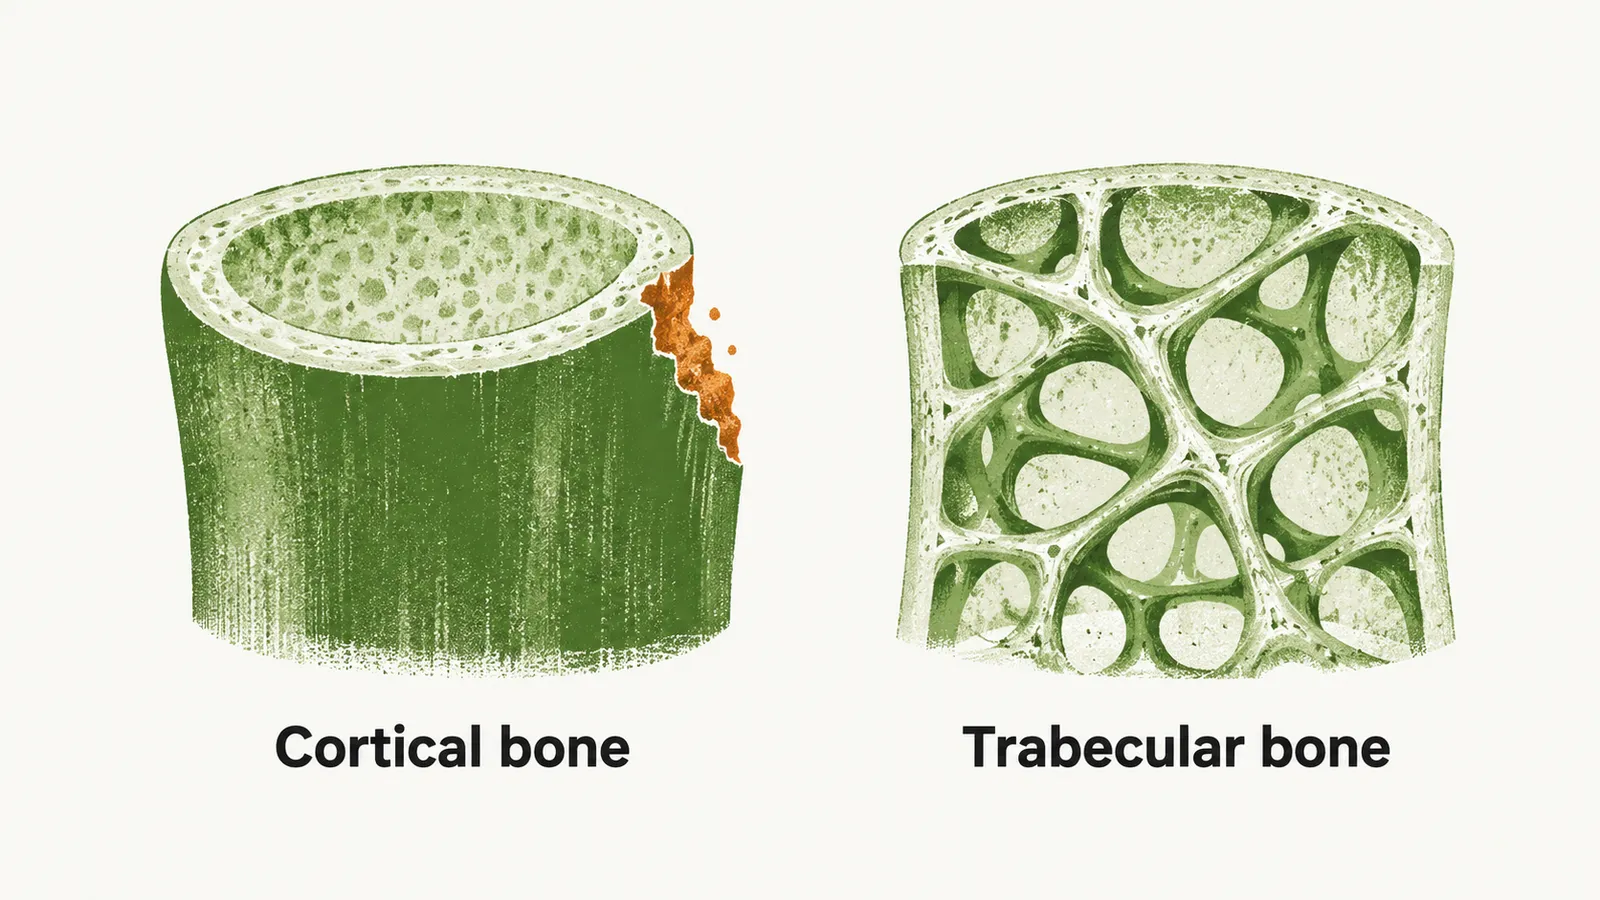
The net bone loss falls more heavily on cortical bone than on trabecular bone. Osteoclasts are thought to cut deeper along the corticomedullary junction under the influence of PTH, and that is a proposed reason why the cortex loses more.
This asymmetry explains the patchy bone disease of PHPT. Each site shows mainly the change of the part that makes up most of it, so cortical sites lose bone while trabecular bone stays relatively preserved.
Why does the same disease look different from site to site?
If the two parts respond differently, a scan of each site will give a different result. The density read at a site reflects the kind of bone that site is made of, so bone density reads differently at different sites.
Bone densitometry measures bone mineral density (BMD). The conventional method is dual-energy X-ray absorptiometry (DXA). In PHPT, bone density is decreased mainly in cortical bones and is not decreased in cancellous (trabecular) bones. Because the loss shows at cortical sites, sites with cortical bone are considered the best target for densitometry.
Where does the scan show the loss?
The site commonly preferred is the distal third of the radius. It has enough cortical bone and is easy to reach. In PHPT the bone density is reduced at the distal third of the radius. At the lumbar vertebrae, which are mostly trabecular, there is minimal change in bone density.
What did the disease look like before automated testing?
The cortical loss used to be visible on the skeleton itself, and not only on a scan. In the past the incidence of skeletal problems caused by PHPT was high. Nowadays it is less than 2% in the US. The classic changes were:
- osteitis fibrosa cystica
- a salt-and-pepper appearance of the skull
- tapering of the distal third of the clavicle
- sub-periosteal bone resorption of the phalanges
- brown tumors
Osteitis fibrosa cystica is the classic severe picture: resorbed bone is replaced by fibrous tissue. Brown tumors are osteoclast-rich fibrous lesions that form within it.
Radiographic signs of skeletal change are now rare. Yet recent advances in bone imaging show that most patients have bone involvement in PHPT. The bone is involved even when the disease is subclinical and the patient has no symptoms.
How is bone turnover read from blood markers?
The classic skeleton showed the result of bone removal. Blood markers show the activity of the cells that do the work. Bone turnover markers separate into bone formation markers and bone resorption markers. Formation markers reflect osteoblast function, and resorption markers reflect osteoclast number and function.
The formation markers are products of the bone-forming cells, so they track formation:
- bone-specific alkaline phosphatase
- osteocalcin
- amino terminal propeptide of type 1 collagen (P1NP)
The resorption markers are collagen breakdown products released when bone is removed, together with an enzyme released by the bone-removing cells, so they track resorption:
- hydroxyproline
- pyridinium cross links PYD and DPD
- TRAP (tartrate-resistant acid phosphatase)
- NTX and CTX (N- and C-telopeptides of type 1 collagen)
What happens to the markers after surgery?
Once the markers can be read, the question is what changes when the excess PTH is removed. After parathyroidectomy, markers of bone resorption and of bone formation both decrease. The resorption markers fall because resorption itself falls once the excess PTH is gone. The formation markers decrease more gradually than the resorption markers. A proposed explanation is that continuous PTH lengthens the life of the bone-forming cells, so formation keeps running for a while after the hormone is removed.
Can turnover be seen in the bone itself?
Bone histomorphometry looks at the bone tissue itself and measures bone turnover directly. It uses histological study of a bone biopsy taken mainly from the iliac crest.
Histomorphometry measures static and dynamic changes. A static change is a feature of the bone at one time point. A dynamic change comes from comparing two or more snapshots in time. To measure dynamic values the patient is given dyes. Double tetracycline labelling is used as a gold standard marker of bone turnover: each label is laid into the bone being formed at the time it is given, so the space between the two labels is the bone laid down in the interval. The change in the location of the dye, driven by the balance of bone formation and bone resorption, is read.
What does the trabecular network look like?
The biopsy shows that the trabecular network is preserved in one sense, and the question is what that means. Two of the most important histomorphometry indices are trabecular density and trabecular connectivity, which is the degree to which the trabecular struts remain joined to one another.
In PHPT, trabecular connectivity is preserved. This is in contrast to postmenopausal women with estrogen-dependent osteoporosis, in whom connectivity is reduced in the iliac crest. One explanation for the preservation is that PTH acts more on cortical bone than on trabecular bone. Another proposed explanation is the longer active formation period, which follows from the longer life of the osteoblasts under the continuous effect of PTH.
Patients with PHPT even have higher trabecular density and higher trabecular connectivity than a healthy control group. But preserved or increased density and connectivity do not mean that trabecular bone is healthy. Trabecular plates are often considered the most critical determinant of the strength of the bone, so density and connectivity alone do not show strength. Even in the early stages and in mild PHPT, pathology is present in the trabecular bone.
What changes inside the trabeculae?
Connectivity is kept. The trabecular pathology in PHPT has three parts:
- the trabecular bone is thinned
- the trabeculae are more irregularly spaced
- the organization is rod-like rather than plate-like
A common structural change in trabecular bone is perforation of plates, which turns plates into rods, and this fits the shift away from plate-like organization. Connectivity is preserved or even increased in PHPT, but the quality of the bone is very low.
Why does the spine fracture when its density looks normal?
A preserved trabecular network and thin, weak struts together make a puzzle that the spine density cannot answer. Bone mineral density in PHPT is preserved in the vertebrae, yet vertebral fracture is increased. This is a paradox. It suggests that areal BMD does not capture all the determinants of bone strength.
Understanding the paradox requires newer imaging techniques, which show the microarchitecture that areal density misses. Conventional DXA measures a two-dimensional, plate-like density. HRpQCT measures three-dimensional density and is more precise than conventional DXA. It is mainly used to measure bone density in the radius and tibia.
Why do the methods disagree?
HRpQCT studies show that patients with PHPT have a decrease of trabecular bone density. This opposes what is seen with histomorphometry. The two can be put together: connectivity is preserved or even increased, but the quality of the bone is very low. Together, the HRpQCT and histomorphometry findings answer the paradox of increased vertebral fracture despite DXA-preserved vertebral BMD.
Why do fractures happen where they do?
In PHPT the trabeculae are thin. Thin trabeculae carry less load and are more prone to microdamage, which makes them prone to fracture. Because cortical and trabecular bone are affected differently, bone fracture in PHPT is highly site-specific. The pattern follows the part of the bone that is affected.