Why is the cardiovascular system the main target?
Cushing’s syndrome is a chronic excess of glucocorticoids, and the cardiovascular system is where that excess does most of its lasting harm. Glucocorticoid receptors sit in most tissues, including the kidney, the vessel wall and heart muscle, so cortisol can act on the circulation by several routes at once. Cortisol raises blood pressure, so the heart works against a higher load. It changes how the body handles glucose and lipids, and that feeds atherosclerosis. It also tips the blood toward clotting. These are separate lines of damage that add up, and cardiovascular complications are the primary cause of death in Cushing’s syndrome.
The damage is not limited to the period of active disease. Part of the vascular and metabolic change is thought to be structural, so it is not simply undone when cortisol falls, and much of the risk remains raised after the excess is corrected. Cardiovascular risk here is not only a direct effect of cortisol on the heart and vessels, but also the metabolic environment that cortisol creates.
How does cortisol raise blood pressure?
Hypertension is very common in Cushing’s syndrome, and it arises from more than one mechanism. Cortisol acts on the kidney’s mineralocorticoid receptor, on the vessel wall and its tone, and on the renin-angiotensin system. The overall picture is complex and only partly understood.
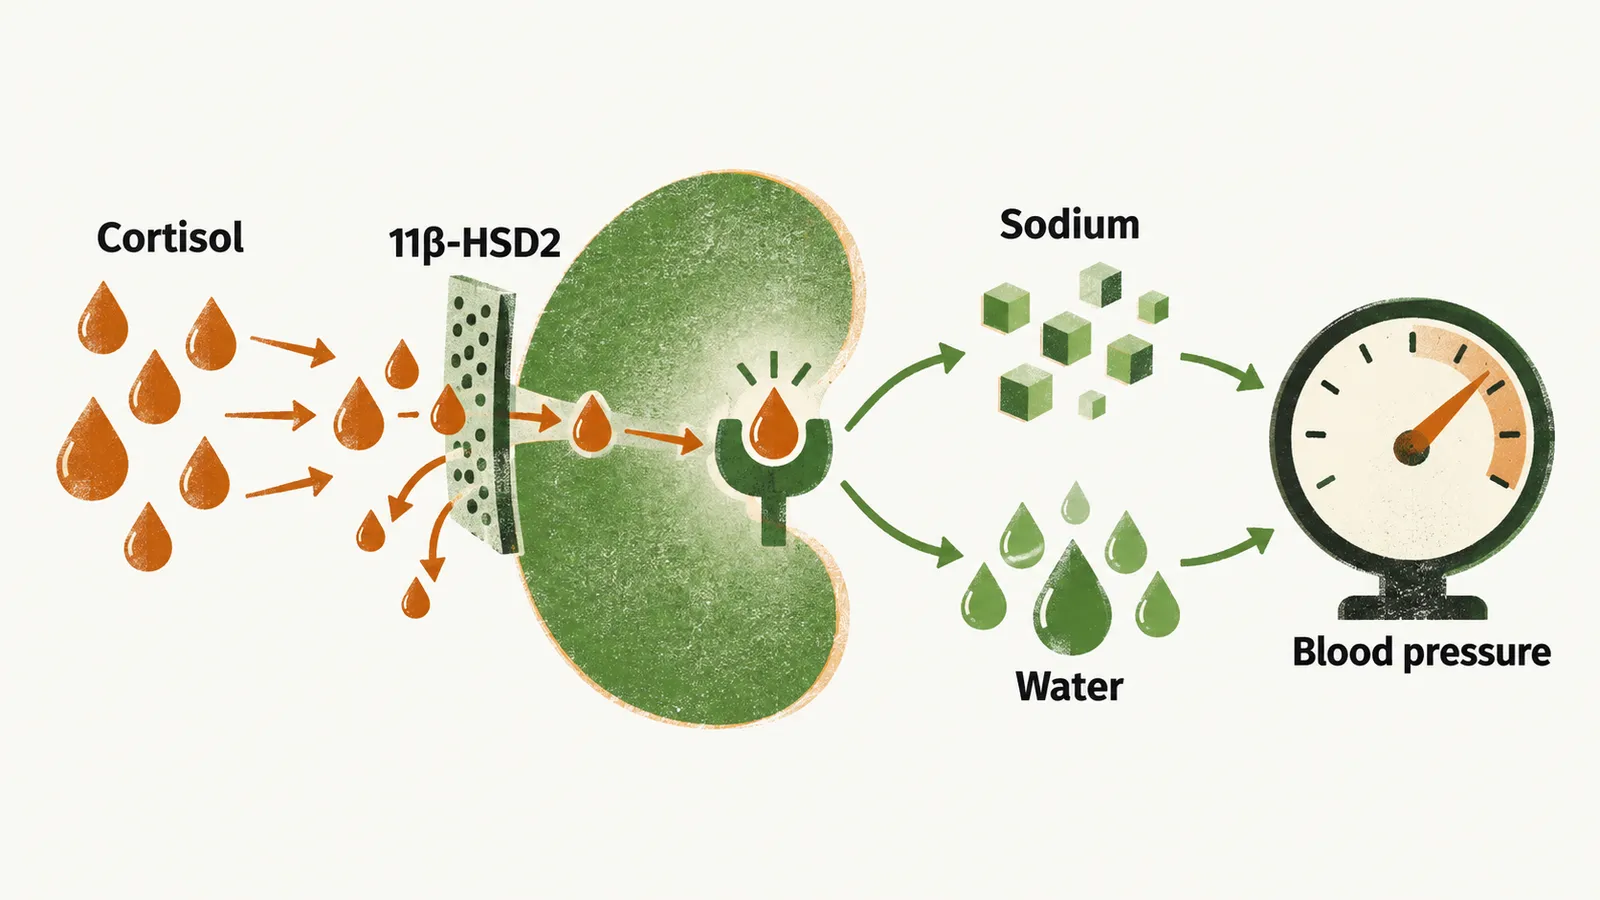
The most specific mechanism is mineralocorticoid receptor activation. Cortisol normally has the same affinity for the receptor as aldosterone, but the kidney protects the receptor by converting cortisol into inactive cortisone with 11β-hydroxysteroid dehydrogenase type 2 (11β-HSD2). When cortisol production outruns the enzyme, cortisol reaches the receptor (Clinical Manifestations of Cushing’s Syndrome gives this in more detail). Cortisol at the receptor copies aldosterone and promotes sodium retention and potassium loss. The retained sodium holds water, so extracellular fluid volume expands and blood pressure rises. This route is one mechanism and not the whole story.
Increased peripheral vascular resistance contributes to the hypertension as well. Proposed explanations are that glucocorticoids blunt vasodilating signals, such as the nitric oxide pathway, and increase the responsiveness of vessels to constrictors, and the renin-angiotensin system is thought to be involved.
Blood pressure is the first thing cortisol pushes, and it is the load the heart then carries.
What does this do to the heart?
Chronic glucocorticoid excess and the accompanying hypertension leave structural and electrical marks on the heart. Two lines of cause are possible: the pressure on the heart from the hypertension and, from experimental work, a possible direct effect of cortisol on heart muscle through its glucocorticoid receptor.
The structural mark is left ventricular hypertrophy. It develops as the ventricle adapts to a raised afterload, the pressure it has to pump against, as in other pressure overload. Cortisol itself may also contribute.
The electrical mark is a prolonged QT interval on the ECG, a recognised change that carries a risk of ventricular arrhythmia. In Cushing’s disease the QT prolongation appears to be independent of hypertension, which suggests a direct cardiotoxic effect of cortisol.
Pressure is not the only strain on the vessels; the changes cortisol makes in glucose and lipids add to it.
How does the metabolic side feed atherosclerosis?
Glucose tolerance decreases, in the direction of diabetes. Glucocorticoids raise glucose output from the liver and reduce insulin-dependent glucose uptake in muscle and fat, and cortisol’s catabolic action also supplies glucose from amino acids, as the clinical manifestations note explains. Dyslipidemia develops as well. It belongs to the metabolic syndrome that comes with visceral adiposity and insulin resistance.
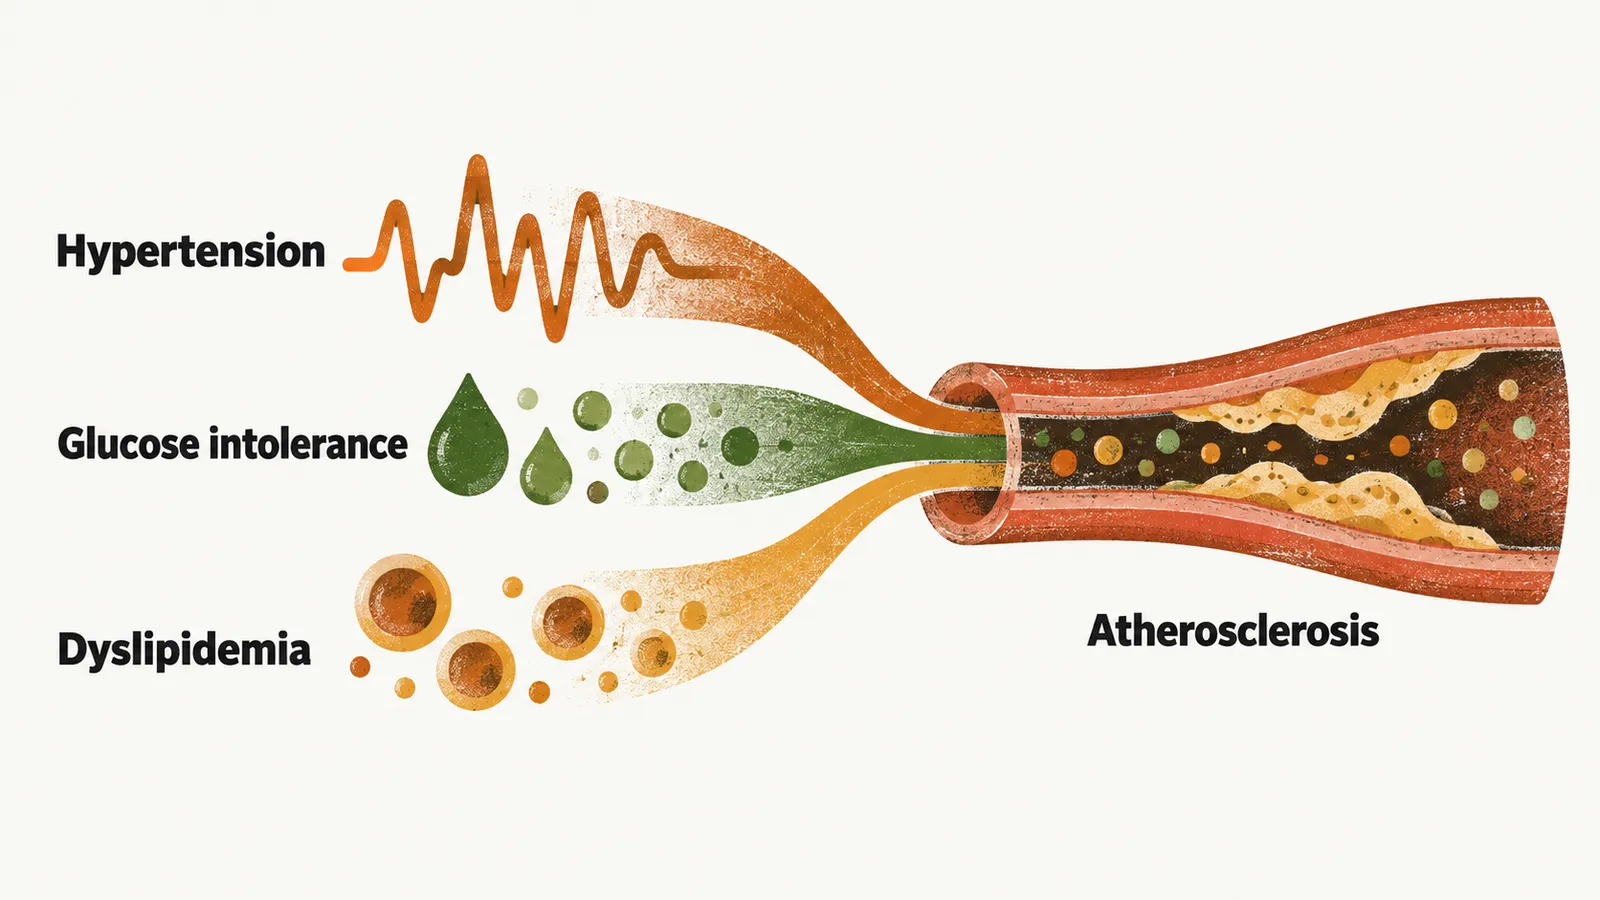
Glucose intolerance and dyslipidemia are two metabolic changes that add to the vascular burden. Together with hypertension, they accelerate atherosclerosis: the three injure the vessel wall together, and visceral adiposity and insulin resistance are linked to early atherosclerotic changes of the carotid wall. This is why the cardiovascular risk is the metabolic environment as well as the direct effect of cortisol.
Besides arterial disease, the blood itself is changed.
Why do clots form so readily?
Cushing’s syndrome causes a hypercoagulable state, alongside the arterial disease. The state is thought to be an imbalance between the pro- and anticoagulant pathways, and both arterial and venous sides are exposed. The risk is high for deep vein thrombosis and pulmonary embolism, since a clot formed in the deep leg veins can travel to the lungs.
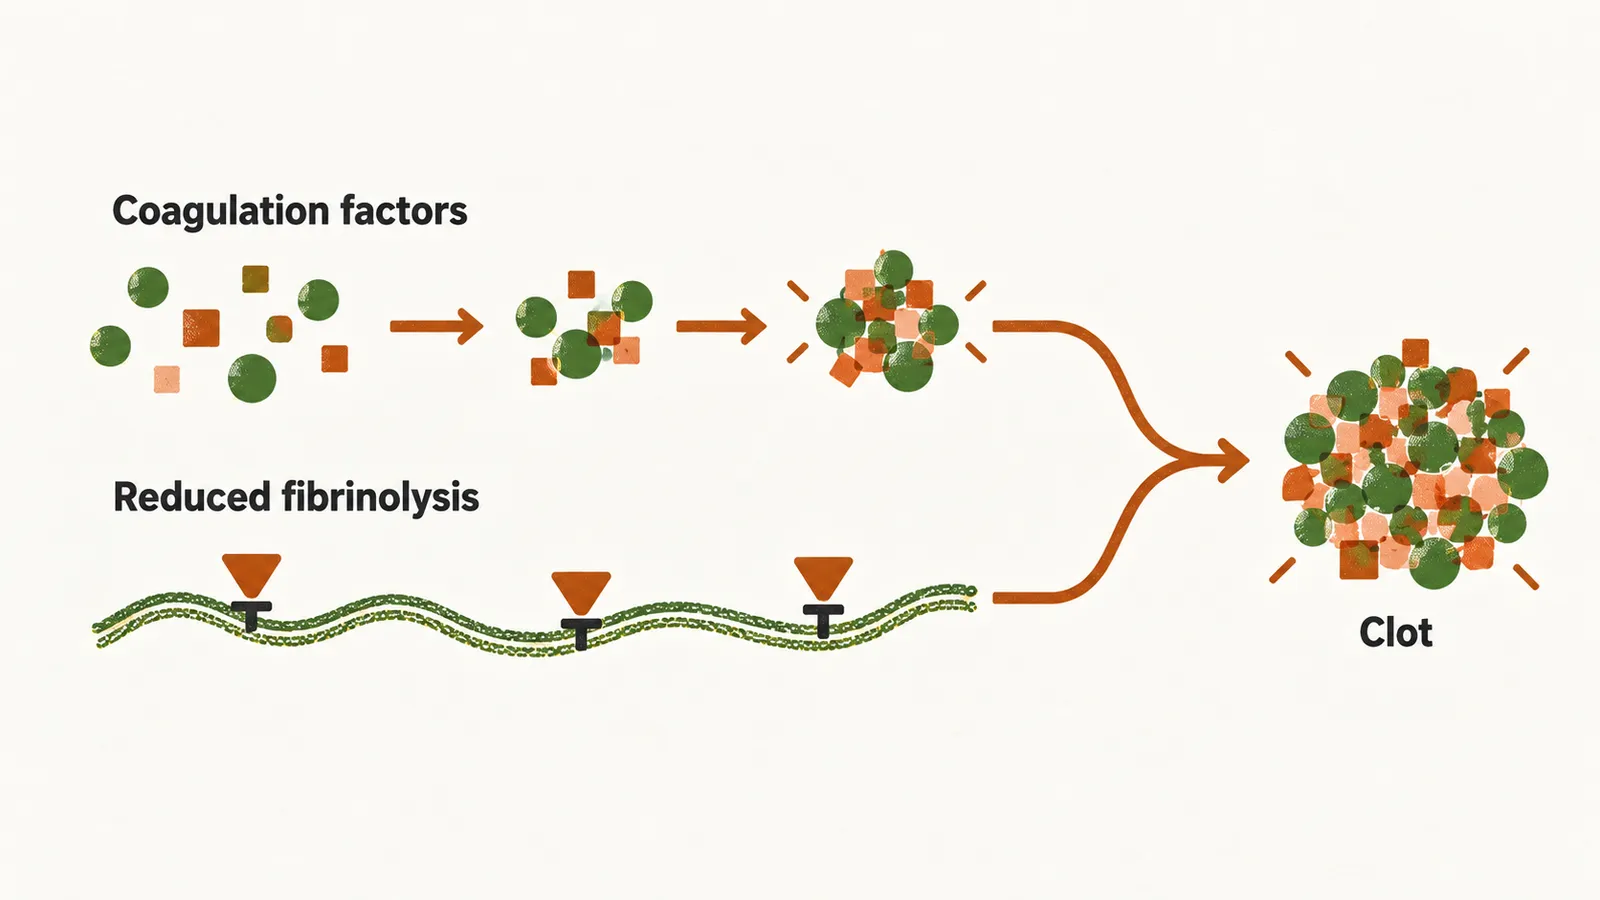
Two things tip the balance. Hypercortisolemia increases coagulation factors, including factor VIII, fibrinogen and von Willebrand factor, and glucocorticoids are thought to stimulate the production of these procoagulant factors directly. Hypercortisolemia also reduces fibrinolysis by increasing plasminogen activator inhibitor 1 (PAI-1) and antiplasmin, proteins that restrain clot breakdown. The result is that blood forms clots readily and dissolves them slowly. The risk of thromboembolic complications is 18-fold higher than in the normal population.
This prothrombotic state coexists with fragile, easily bruised skin, and the two come from different tissues. As the clinical manifestations note explains, the thin dermis and weak vessel walls make the skin bruise. So the bruising is not a bleeding tendency: it reflects the skin and not the clotting system, and it does not protect against thrombosis. The same patient can bruise easily and still be at high thrombotic risk.
All these routes add up.
Why does cardiovascular disease dominate mortality, and why does the risk stay?
Hypertension, cardiac change, the metabolic burden and thrombosis each add to the cardiovascular risk, and cardiovascular disease becomes the leading cause of death through these mechanisms. A higher risk of infections and a higher risk of suicide are also reported.
The excess risk does not disappear when hypercortisolemia resolves. Cardiovascular risk tends to remain the same even after cortisol excess has been treated. This persistence is thought to reflect structural vessel change and metabolic change that persist, together with clotting factors that normalise slowly in some patients. That is why cardiovascular follow-up continues after remission.
Because the risk is so persistent, recognising the syndrome and proving the cortisol excess reliably is the first task. If the risk stays this high, how is the cortisol excess recognised and proven reliably?