
Who should be tested for Cushing’s syndrome?
Single clinical features of Cushing’s syndrome are non-specific. Obesity, depression, diabetes, hypertension and menstrual irregularity are common in people who do not have the disorder, so the diagnosis can be missed unless someone thinks of it. The diagnosis therefore starts with a decision to test, and the situations that prompt it share one theme: the feature is unusual for the patient’s age, or a disease is not behaving as it should.
- Hypertension in young adults, or resistant hypertension.
- Poorly controlled diabetes despite appropriate therapy. About 4% of patients with type 2 diabetes mellitus have Cushing’s syndrome.
- Fragility fractures in eugonadal subjects (people with normal gonadal function).
- Decreasing growth velocity or weight gain in children.
- Adrenal incidentalomas, adrenal masses found by chance on imaging done for another reason.
- Signs of hypercortisolism, such as striae and muscle weakness, among others.
- Use of exogenous glucocorticoids. Excluding this first removes the most common cause of the syndrome.
What does the work-up have to establish, and how many tests are enough?
Once the suspicion is there, the first job is to show that the excess is real. Cushing’s syndrome has to be confirmed biochemically before its cause is sought. The clinical features are non-specific and the causes are diverse, so treating before knowing the cause would aim at the wrong target, and the cause-finding tests only mean something once the excess is proven. The diagnosis is therefore built first from tests that show cortisol excess itself, and only then do tests and imaging separate ACTH-dependent from ACTH-independent causes. This gives two challenges: to distinguish a pathological glucocorticoid increase from the physiological causes of high cortisol production, and then to determine the cause of the pathological excess. The cardiovascular risk of the syndrome is persistent, which is a reason to confirm it carefully.
No single result settles the first challenge. The diagnosis is considered established when the results of several tests are consistently suggestive of Cushing’s syndrome. How many tests are needed depends on the pre-test probability. When it is mild to high, 2-3 screening tests should be used. When it is low, a single negative test is enough to exclude the syndrome.
How do the three groups of screening tests catch a broken HPA axis?
The adrenal cortex makes cortisol under ACTH from the pituitary, and ACTH is driven by CRH and vasopressin from the hypothalamus. Cortisol feeds back negatively on that drive, and the whole axis runs on a daily rhythm. In Cushing’s syndrome the loop breaks in recognisable ways, and the screening tests fall into three groups, each exploiting a different normal property of the hypothalamic-pituitary-adrenal (HPA) axis that is lost in the disease: total cortisol output over a day, the negative feedback, and the circadian rhythm.
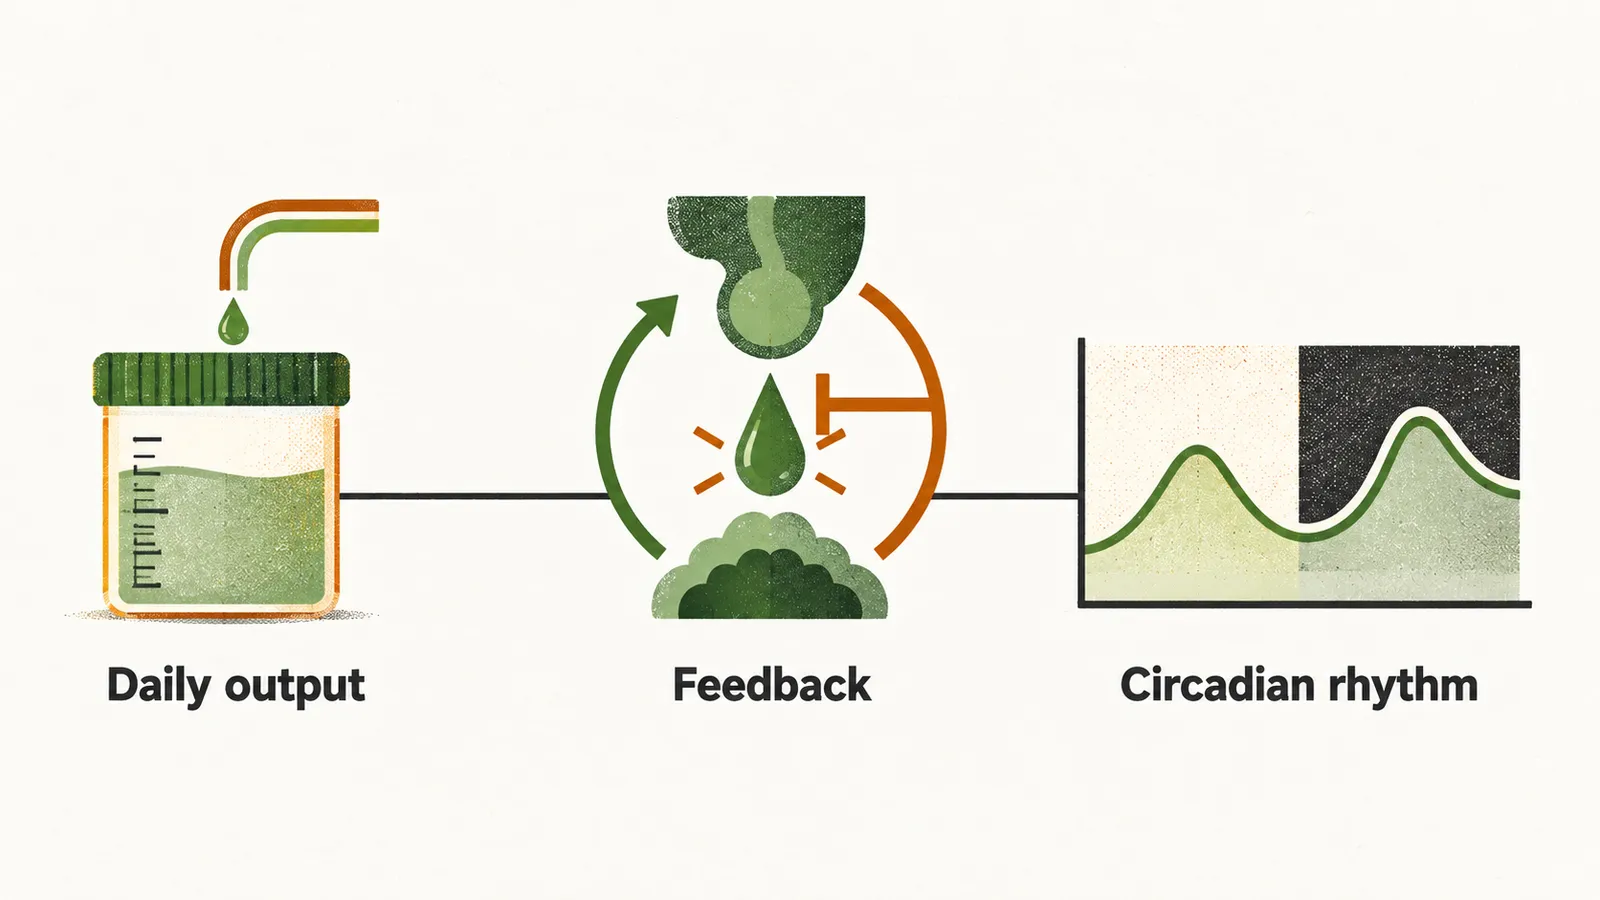
Urinary free cortisol
Urinary free cortisol (UFC) is the most commonly used screening test and the first line. It is measured as free cortisol in 2-3 different 24-hour urine collections. Its sensitivity for hypercortisolemia is about 95% in Cushing’s disease and about 88% in ectopic forms and adrenal masses.
Several collections are needed because a single one can mislead. The collection must be complete, since a partly collected day gives a falsely low or high result, so creatinine excretion is measured to check it. Creatinine excretion should be about 1 g/day in a patient of about 70 kg. The cortisol/creatinine ratio is more informative than cortisol alone, and a cortisol-to-creatinine ratio of more than 25 nmol/mmol is suggestive of Cushing’s syndrome.
UFC reflects only the free cortisol in blood, not the cortisol bound to transcortin (corticosteroid-binding globulin, CBG). A change in the binding protein therefore does not shift it, which is why, in patients with an altered CBG level, UFC is more specific for hypercortisolism than serum tests.
Dexamethasone and the feedback
Physiologically, cortisol feeds back negatively on CRH and vasopressin, which stimulate ACTH release. In Cushing’s syndrome this negative feedback is resisted. Dexamethasone is a synthetic steroid that normally suppresses the axis, so cortisol that will not fall after dexamethasone shows that the feedback is lost. The test is used in two ways:
- The low-dose dexamethasone suppression test (LDDST) gives a low dose of dexamethasone and then measures glucocorticoid in the urine.
- The overnight dexamethasone suppression test (ONDST) gives 1 mg of dexamethasone at 11 pm and measures plasma cortisol at 9 am.
The ONDST is easier than collecting urine after a longer course, so it is the one used today. It is also the most sensitive test among these, with a sensitivity of 98-99% at a cut-off of 50 nmol/L.
Midnight cortisol and the rhythm
Cortisol normally follows a circadian rhythm, with a peak around 7-8 in the morning and a low level during the night. In Cushing’s syndrome this rhythm is disrupted. In some patients the morning peak remains, so a morning value cannot be used for this purpose. In most patients the midnight nadir is lost and cortisol stays high at midnight. Because a healthy person’s cortisol is lowest at night, a high midnight value is abnormal in itself, and any screening test at midnight has high diagnostic value.
Midnight salivary cortisol is a convenient way to sample that time point. It is very easy and non-invasive, and the patient can collect it at home. Its sensitivity is 92% and its specificity 96%.
What can make a screening test mislead?
A test is only as good as the conditions in which it was done. Three pitfalls are worth knowing:
- An incomplete 24-hour urine collection, covering more or less than a full day, gives a misleading UFC.
- A drug that induces CYP3A4, such as rifampicin or an antiepileptic, increases the metabolism of dexamethasone, so less is left to suppress cortisol and the dexamethasone test is weakened.
- An oral contraceptive increases the CBG level and so total cortisol, which can mask the effect of the dexamethasone test. If so, the test is repeated 4-6 weeks after withdrawal of estrogen.
A different problem is pseudo-Cushing’s syndrome, in which a patient has the clinical features of Cushing’s syndrome plus some biochemical evidence of hypercortisolemia. These patients recover once the predisposing factor resolves. In these conditions the axis is thought to be driven from higher brain centres, which raise CRH and activate the whole axis. Negative feedback still partly restrains the result, which is a proposed reason why the biochemical excess is only partial. Pseudo-Cushing’s syndrome occurs mostly in depression, alcohol abuse, pregnancy, morbid obesity and poorly controlled diabetes mellitus.
What if the first-line tests do not settle it?
When the first-line tests and their pitfalls leave the diagnosis unclear, there are two second-line tests. One samples the midnight nadir directly, and the other tests the pituitary response to desmopressin. The first looks again at the rhythm, and the second at how the pituitary responds.
Midnight serum cortisol was, before salivary cortisol, the only reliable test for the midnight nadir. It is hard for the patient, because the cortisol must be sampled while the patient is asleep and calm. That requires an inpatient clinic stay of at least 48 hours, and the sample is taken 5-10 minutes after waking the patient during the night. A plasma level of less than 50 nmol/L excludes Cushing’s syndrome. False positives occur in the critically ill, in acute infections and in heart failure. In short, late-night salivary cortisol is an outpatient test and midnight serum cortisol is an inpatient test.
The desmopressin test is the other second-line option. Corticotroph cells of the anterior pituitary, and corticotroph adenomas, carry V3 receptors that desmopressin can activate, so desmopressin raises ACTH and cortisol.
Once the excess is proven, is ACTH high or low?
After hypercortisolemia is confirmed, the next step is the differential between ACTH-dependent and ACTH-independent disease. An adrenal source that works independently switches ACTH off by negative feedback, so the ACTH level tells which side the excess comes from. The differential begins with a plasma ACTH measurement. If ACTH is inappropriately normal or increased, the disease is ACTH-dependent.
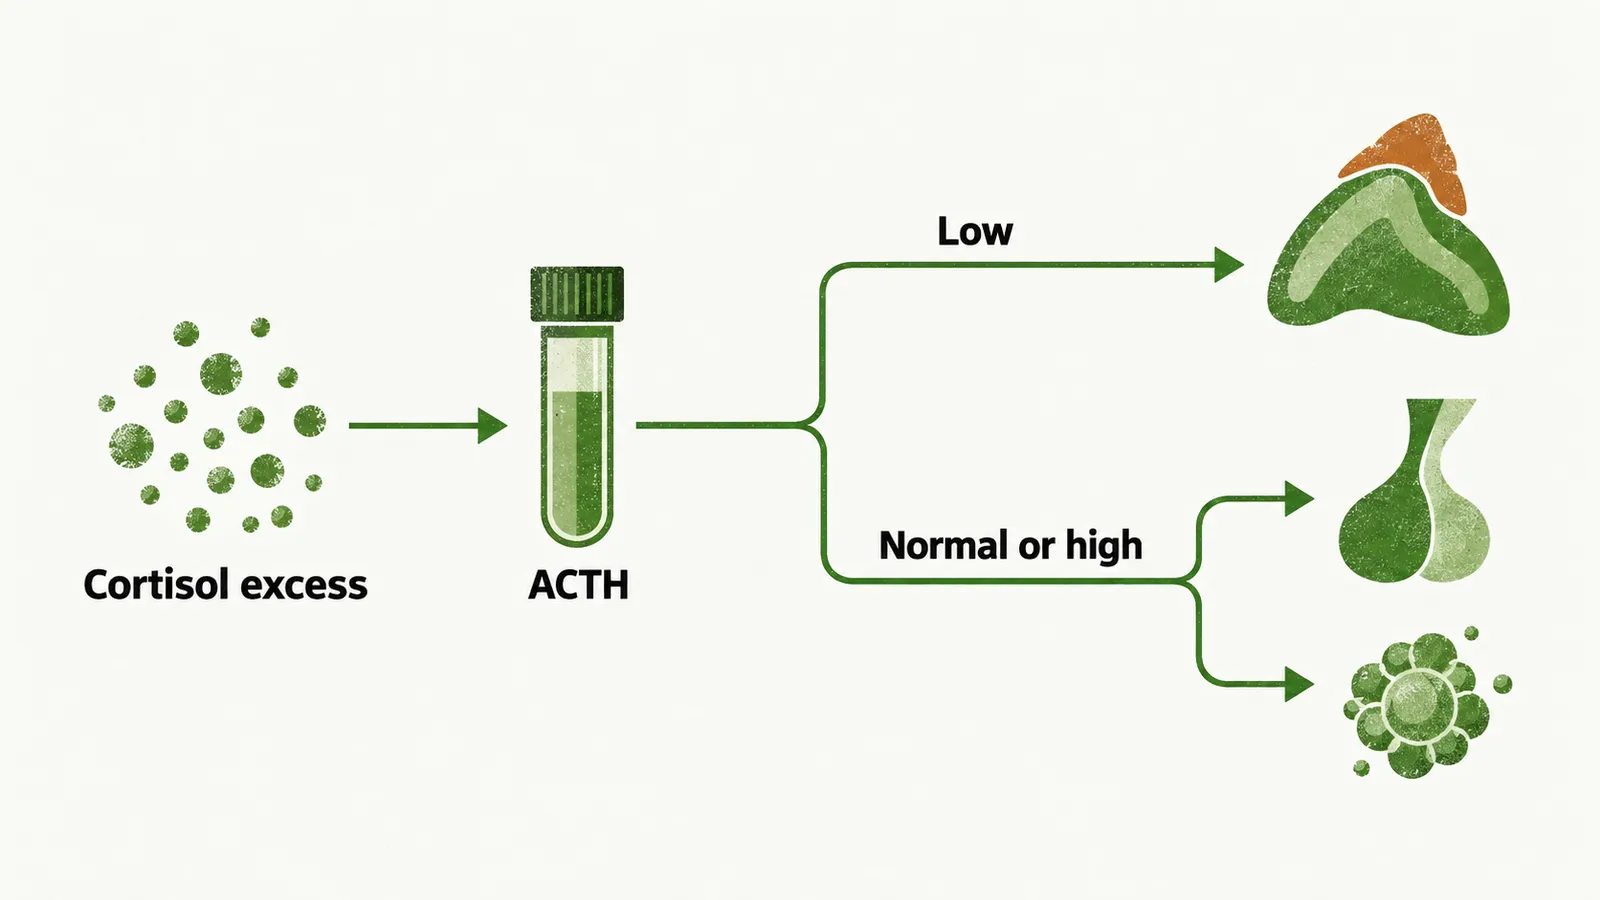
The plasma ACTH sample is taken at about 8-9 am. It is suggested to test twice, because some patients show an occasional low plasma ACTH of less than 10 ng/L. An ACTH of less than 10 ng/L suggests ACTH-independent Cushing’s syndrome, since a silenced pituitary points to the adrenal as the source. An ACTH that is consistently more than 20-30 ng/L suggests Cushing’s disease or ectopic Cushing’s syndrome, that is, an ACTH-producing source. An intermediate level, between 10 and 20-30 ng/L, is studied further with a CRH or desmopressin test.
Which organ do we image, and how do we separate the pituitary from an ectopic source?
Imaging comes only after these findings, because the ACTH result narrows the search to specific organs and only that organ needs to be imaged. In ACTH-independent disease the adrenal gland is imaged with un-enhanced CT (CT without contrast). In ACTH-dependent disease the pituitary gland is imaged with MRI, and adrenal imaging is not indicated, since the adrenals are driven from outside. A pituitary microadenoma may be too small to see: in about 40% of cases the adenoma is missed on MRI because of its size.
Imaging therefore cannot settle ACTH-dependent disease alone. A biochemical test is always needed after imaging to distinguish ectopic production from a pituitary adenoma. The reason is that a pituitary adenoma retains some response to dexamethasone for negative feedback, while ectopic disease mostly does not. In clinical practice the patient is mostly tested first with the high-dose dexamethasone test (HDDST), and then the high-dose test is repeated. If cortisol is resistant to suppression on the second test, ectopic ACTH production is probable. A positive response means plasma cortisol is suppressed to less than 50% of the basal level.
If the HDDST and the CRH test give incompatible results, inferior petrosal sinus sampling (IPSS) can be used. It samples blood draining the pituitary on each side and compares it with peripheral blood: after a CRH injection, the petrosal/peripheral ACTH ratio is compared at baseline and 5 minutes after the injection. A pituitary source gives a gradient between the petrosal and peripheral samples, and an ectopic source does not. IPSS has very high sensitivity and specificity for Cushing’s disease when the ratio is greater than 2 at baseline and greater than 3 five minutes after the injection. It is also used to confirm Cushing’s disease when MRI is not sensitive enough to detect an adenoma smaller than 10 mm.
When ectopic ACTH-dependent Cushing’s syndrome is suspected, the tumour can lie anywhere along the chest and abdomen, so CT of the chest and abdomen is used to locate it. If no lesion is found, MRI of the chest or abdomen can be used, and it may show a carcinoid lesion better. The most common sources of ectopic ACTH are bronchial neuroendocrine tumours, which account for 25% of ectopic ACTH-dependent Cushing’s syndrome. Small cell lung carcinoma accounts for 19%.
One more clue comes from the hormones themselves. High ACTH drives adrenal androgens alongside cortisol, so ACTH-dependent Cushing’s syndrome and ectopic carcinoma commonly have hyperandrogenism alongside the high glucocorticoid level. In ACTH-independent Cushing’s syndrome there is mostly only a high glucocorticoid level.
Once the source is located, how is the cortisol excess removed or controlled?