Where does the cortisol excess come from?
Cortisol is made by the adrenal cortex under a loop. The pituitary releases ACTH, which instructs the adrenal cortex to produce cortisol, and cortisol in turn feeds back to switch the hypothalamus and pituitary off. Cushing’s syndrome is defined by chronic glucocorticoid excess, and it arises when this loop goes wrong.
Most often the excess is iatrogenic: it follows glucocorticoid treatment given for another reason, for example immunosuppression. Glucocorticoids are widely prescribed for other conditions, which is why this form is the most common. The endogenous forms, in which the patient’s own cortisol production is excessive, are much rarer, with an incidence of about 1-2 new cases per million people each year. They are the subject here.
Does the adrenal answer to ACTH, or act alone?
To tell the endogenous causes apart, one question is enough: are the adrenals driven from outside, or are they the source themselves?
In ACTH-dependent disease, a tumour secretes ACTH. The ACTH signal travels through the blood and reaches both glands, so both adrenals become hyperplastic and overproduce cortisol.
In ACTH-independent disease, an adrenal gland makes cortisol on its own. The loop itself is intact, so the cortisol excess shuts down ACTH through the normal negative feedback of the hypothalamic-pituitary-adrenal axis.
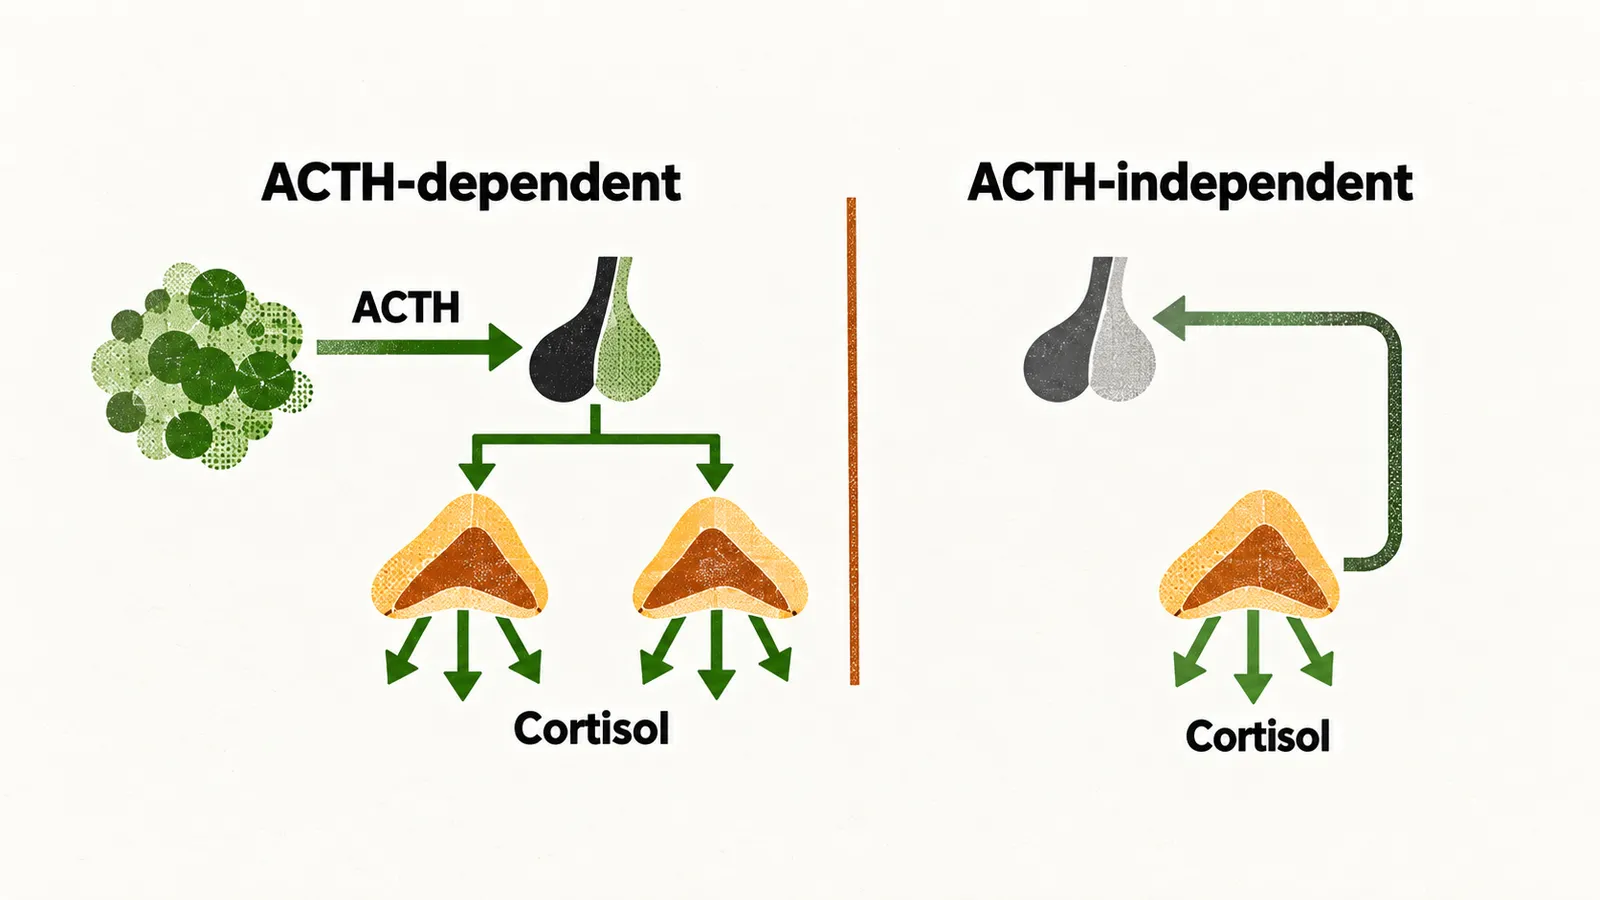
This distinction is not only descriptive. It determines which hormone is measured next: the plasma ACTH level is the first step in separating the two groups.
How common is each group?
Once the two groups are known, how many cases fall in each? About 80-85% of endogenous cases are ACTH-dependent, and 15-20% have their primary cause in the adrenal gland. ACTH-dependent disease has two sources: a pituitary adenoma, and an ectopic ACTH-producing tumour outside the pituitary. The pituitary adenoma accounts for most ACTH-dependent cases.
What is Cushing’s disease?
Most of the ACTH-dependent group is one tumour. Cushing’s disease is the term reserved for a pituitary corticotrope adenoma, a benign tumour of the pituitary cells that normally produce ACTH. It is the most common endogenous cause overall.
Cushing’s disease is more common in women, with a female-to-male ratio of about 4:1. In the pre-pubertal years it is more prevalent in boys. A proposed explanation for the sex difference is that oestrogens may play a role.
Two features of the adenoma matter in practice: its size and its origin.
- A microadenoma is less than 1 cm across. It is present in more than 90% of cases of Cushing’s disease.
- A macroadenoma is more than 1 cm across. It is found in a minority of patients, about 10% of cases.
A microadenoma can be too small to see. The tumour is small, not absent, so negative imaging does not exclude Cushing’s disease.
As for origin, the adenoma usually occurs sporadically. In rare cases it appears in the context of MEN1 (multiple endocrine neoplasia type 1) as familial Cushing’s disease.
What changes in the adenoma cell?
The molecular basis of the adenoma is partly known. A somatic mutation of the USP8 gene, meaning one acquired in the tumour cells and not inherited, is present in 35-62% of corticotroph adenomas.
The effect follows a chain. The EGF (epidermal growth factor) receptor is normally tagged with ubiquitin, the tag that marks a protein for destruction, and its signal ends when it is destroyed. USP8 is a deubiquitinase: it removes ubiquitin from the EGF receptor and so shelters the receptor from degradation. The recurrent USP8 mutations are gain-of-function, making the enzyme constitutively active, so the mutant USP8 deubiquitinates the receptor more than usual. The EGF receptor escapes degradation and its signalling persists. That persistent signalling drives transcription of POMC (pro-opiomelanocortin), the precursor from which ACTH is cleaved; the intermediate steps are thought to run through the signalling pathway. The tumour therefore secretes ACTH without the usual hypothalamic drive.
When does ACTH come from somewhere else?
The pituitary is not the only source of ACTH. Ectopic ACTH production means ACTH made by a tumour outside the pituitary. Such a tumour is not under the control of the hypothalamic-pituitary loop, and it drives both adrenals as any ACTH source does. Ectopic ACTH production is more common in males.
The ACTH comes most often from bronchopulmonary neuroendocrine tumours, including carcinoids. It also comes from small cell lung cancer and from carcinoids of the thymus and pancreas. In very rare cases, ectopic production of CRH (corticotropin-releasing hormone) and/or ACTH is also seen with thyroid medullary carcinoma and pheochromocytoma.
When does an adrenal gland act alone?
Now the ACTH-independent group, where the adrenal itself is the source. In the majority of patients with endogenous ACTH-independent Cushing’s syndrome, the cause is a cortisol-producing adrenal adenoma. These primary adrenal forms are more common in females than in males.
About 40% of these adenomas carry a mutation in PRKACA, the gene for the catalytic subunit of protein kinase A (PKA). PKA is normally held switched off by a regulatory subunit. ACTH raises cAMP, the regulatory subunit lets go of the catalytic subunit, and the catalytic subunit drives cortisol synthesis. The mutation weakens the binding of the regulatory subunit that keeps the enzyme switched off. So PKA is constitutively active and drives cortisol synthesis without ACTH.
Adrenocortical carcinoma is a rarer adrenal cause.
What are the rarer adrenal forms?
The adrenal adenoma is not the only adrenal source. Three uncommon adrenal causes, PBMAH, PPNAD and McCune-Albright syndrome, each pair a distinctive mechanism with a characteristic association. The first two act, like the PRKACA mutation, through the PKA pathway.
PBMAH
PBMAH is primary bilateral macronodular adrenal hyperplasia. It is characterised by low circulating ACTH, so the nodules must be stimulated by other means. There is evidence of autocrine stimulation of the cortisol-producing cells through intra-adrenal ACTH production; this is thought to be one route. The nodules also often carry GPCRs that the adrenal gland does not express physiologically, including receptors for vasopressin, GIP (glucose-dependent insulinotropic peptide), LH (luteinizing hormone) and serotonin. These receptors activate the PKA pathway, so ordinary circulating signals can drive further cortisol release.
Germline mutations of the tumour suppressor gene ARMC5, meaning present in every cell of the body, are found in about 20-25% of apparently sporadic PBMAH cases and in most familial PBMAH cases.
PPNAD and Carney’s complex
PPNAD is primary pigmented nodular adrenal disease. It carries a germline mutation in PRKAR1A, one of the regulatory subunits of PKA. The mutation releases the enzyme from inhibition, the same PKA logic as the PRKACA mutation.
PPNAD is part of Carney’s complex, an autosomal dominant multiple neoplasia condition. It combines PPNAD with cardiac myxomas, Sertoli cell tumours and lentiginosis. The cardiac myxomas are benign tumours of connective tissue inside the heart chambers, and they are the main cause of morbidity and mortality in these patients.
McCune-Albright syndrome
McCune-Albright syndrome is caused by a mutation in the G protein alpha subunit 1 (GNAS1). The mutation arises after fertilisation, so it is present in only a proportion of the body’s cells. This mosaicism is why the syndrome is not inherited, and why its features vary in extent from patient to patient. It is associated with polyostotic fibrous dysplasia, precocious puberty and unilateral café-au-lait spots.
What does the cortisol excess do?
Whatever the source, the result is the same cortisol excess. What does that excess do to the patient?