
Treatment of Cushing’s syndrome removes the source of the cortisol excess or blocks it. The source differs between causes, so the choice of treatment follows the classification in Causes and Classification of Cushing’s Syndrome.
How is the excess treated, and why does the choice depend on the cause?
In ACTH-dependent disease an ACTH-secreting tumour drives both adrenal glands, and that tumour lies in the pituitary or elsewhere. In ACTH-independent disease the adrenal gland makes cortisol on its own, and the tumour lies in the adrenal gland. The source has to be found first, as set out in Diagnosis and Differential Diagnosis of Cushing’s Syndrome.
The first-line principle is the same in all forms: remove the causal tumour when possible. Removing the tumour stops the excess at its origin. It also leaves the hypothalamic-pituitary-adrenal axis intact, so the normal axis is still there to recover, and the patient is not committed to lifelong replacement therapy. The exception is removal of both adrenal glands, because then no adrenal tissue is left to make cortisol. Which operation is used depends on where the tumour lies.
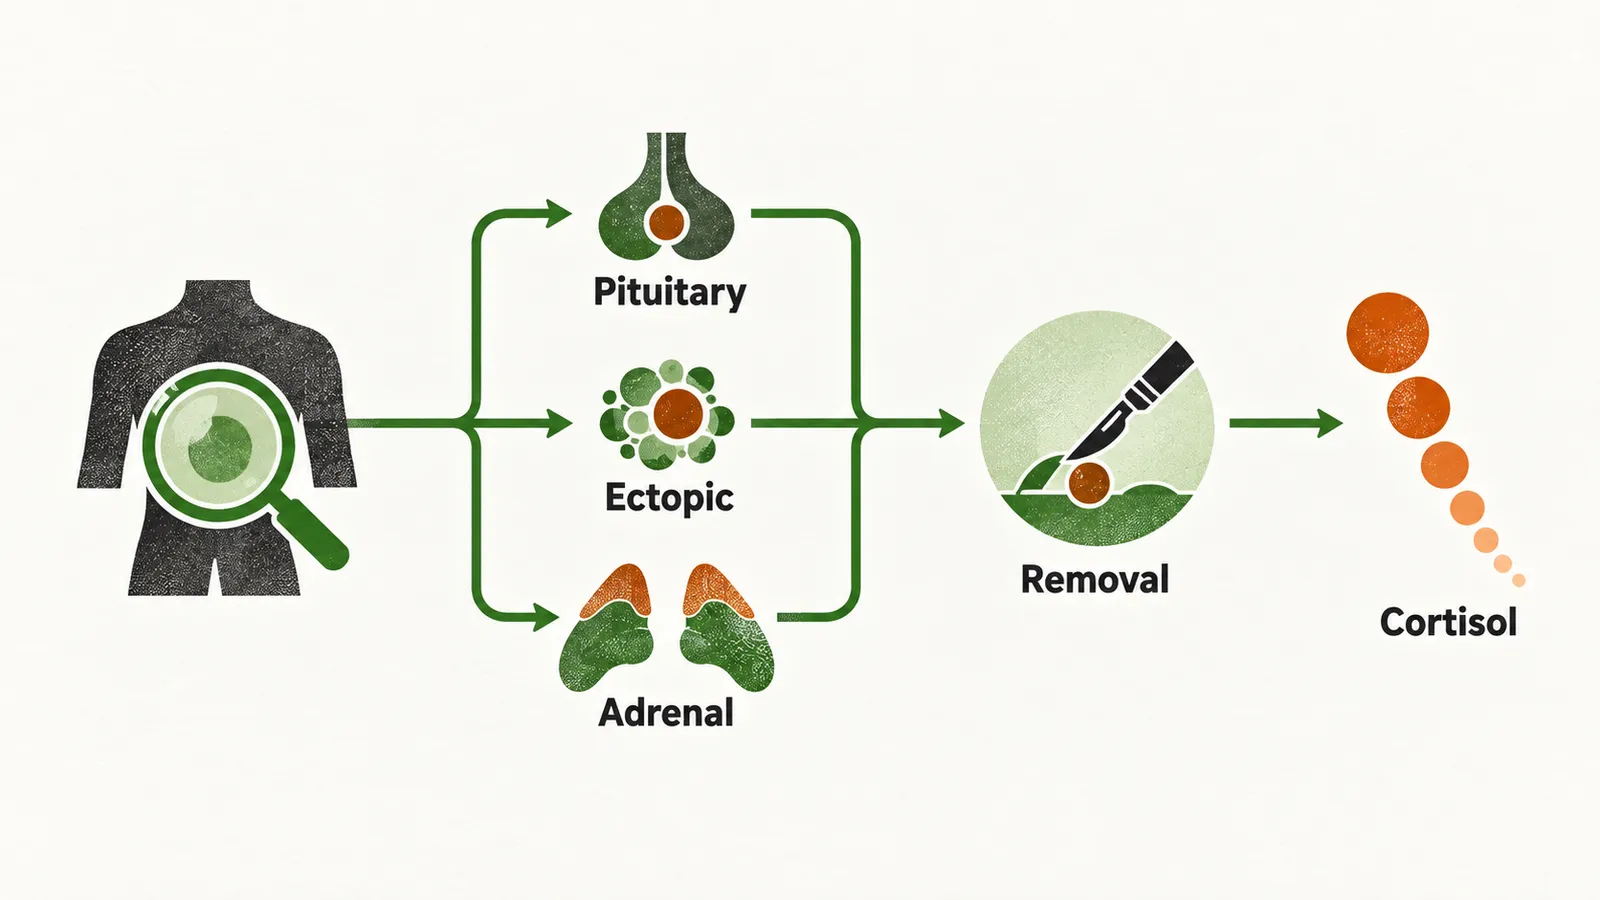
How is each tumour removed?
Which operation depends on where the tumour lies, so each site has its own route.
Pituitary: Cushing’s disease
In Cushing’s disease the tumour is a pituitary corticotrope adenoma. First-line treatment is transsphenoidal surgery, removal of the adenoma through the sphenoid sinus. The pituitary lies just behind that sinus, so the surgeon reaches the gland without going through the brain. The operation is performed by an experienced pituitary surgeon, because the result depends on the surgeon’s skill.
Remission follows in most patients when the adenoma is a microadenoma, and in fewer patients when it is a macroadenoma. A small tumour is thought to be easier to remove completely than a large one. Recurrence years later is common enough that long-term surveillance is needed. The hormone-secreting cells may remain, or the adenoma may regrow, so the axis has to be checked again over time.
Ectopic ACTH
When ACTH comes from an ectopic tumour, that tumour is treated by resecting it when it can be found. If the tumour is not located, has metastasised or cannot be resected, the cortisol excess is controlled medically instead.
Adrenal gland
In ACTH-independent disease the adrenal gland is the target. A cortisol-producing adrenal adenoma is the source, so it is treated by removing the affected adrenal gland. Adrenocortical carcinoma is treated by resection, often combined with mitotane. Mitotane is both a steroidogenesis inhibitor and adrenolytic, so it blocks cortisol synthesis and is also toxic to adrenal tissue.
When surgery is not enough, what do drugs do?
Surgery does not always control the cortisol, and some patients cannot have it. Medical therapy lowers cortisol without operating on the tumour. It works by blocking cortisol synthesis or the signal that drives it, so it controls the excess but does not remove the source. Its four main roles are the situations in which surgery has not controlled, or cannot control, the cortisol:
- persistent hypercortisolism after surgery;
- a patient who is not a surgical candidate;
- ectopic disease whose tumour cannot be found or removed;
- controlling cortisol while waiting for radiotherapy to take effect.
The main group is the steroidogenesis inhibitors. Cortisol is built in the adrenal cortex step by step by enzymes, so blocking one of those enzymes cuts the product. The group contains:
- ketoconazole and levoketoconazole (its isomer);
- metyrapone;
- osilodrostat;
- mitotane.
Osilodrostat inhibits both 11β-hydroxylase and aldosterone synthase.
Etomidate is also in the group and is its only parenteral agent. It is the fastest, lowering cortisol within hours. An intravenous drug does not depend on absorption from the gut. Etomidate is used in the intensive care setting for severe, life-threatening hypercortisolemia, where the patient cannot take oral drugs and needs the fastest control, which needs close monitoring.
The second group acts on the pituitary: pasireotide, a somatostatin analogue, and cabergoline, a dopamine agonist. They act on the corticotrope tumour to reduce its ACTH output, so they apply to pituitary disease and are generally not expected to help adrenal causes.
Treatment is monitored by measuring urinary free cortisol, which reflects the daily output and so shows whether the dose is enough. The dose is adjusted until the level is controlled.
What can radiotherapy and bilateral adrenalectomy add?
If neither drugs nor surgery on the tumour control the excess, two more options remain.
Pituitary radiotherapy
Pituitary radiotherapy is a second-line option for Cushing’s disease that persists or recurs after surgery. It does not act at once: its effect develops over months to years. Medical therapy is therefore used to control cortisol during that interval.
Bilateral adrenalectomy
When the excess cannot be controlled by other means, bilateral adrenalectomy removes the source definitively, because with both adrenal glands gone no cortisol is made, whatever drives them. The cost is permanent glucocorticoid and mineralocorticoid replacement, since the adrenal cortex makes both kinds of hormone and both glands are removed.
A specific complication is Nelson’s syndrome. The adrenal glands had also restrained the pituitary adenoma through cortisol feedback, and removing them removes that restraint. In the proposed explanation the adenoma is then released and can grow into a large ACTH-secreting macroadenoma. The adenoma makes much more of the precursor from which ACTH and the melanocyte-stimulating peptides are cut, which would explain why Nelson’s syndrome produces hyperpigmentation, as described in Clinical Manifestations of Cushing’s Syndrome. It also produces visual field defects through compression of the optic chiasm, because the chiasm lies just above the pituitary and a growing macroadenoma presses on it.
Prophylactic pituitary radiotherapy at the time of adrenalectomy is used to attempt to lower the risk of Nelson’s syndrome. Its benefit is not established, and it is not standard practice.
What happens to the patient’s own cortisol after the source is removed?
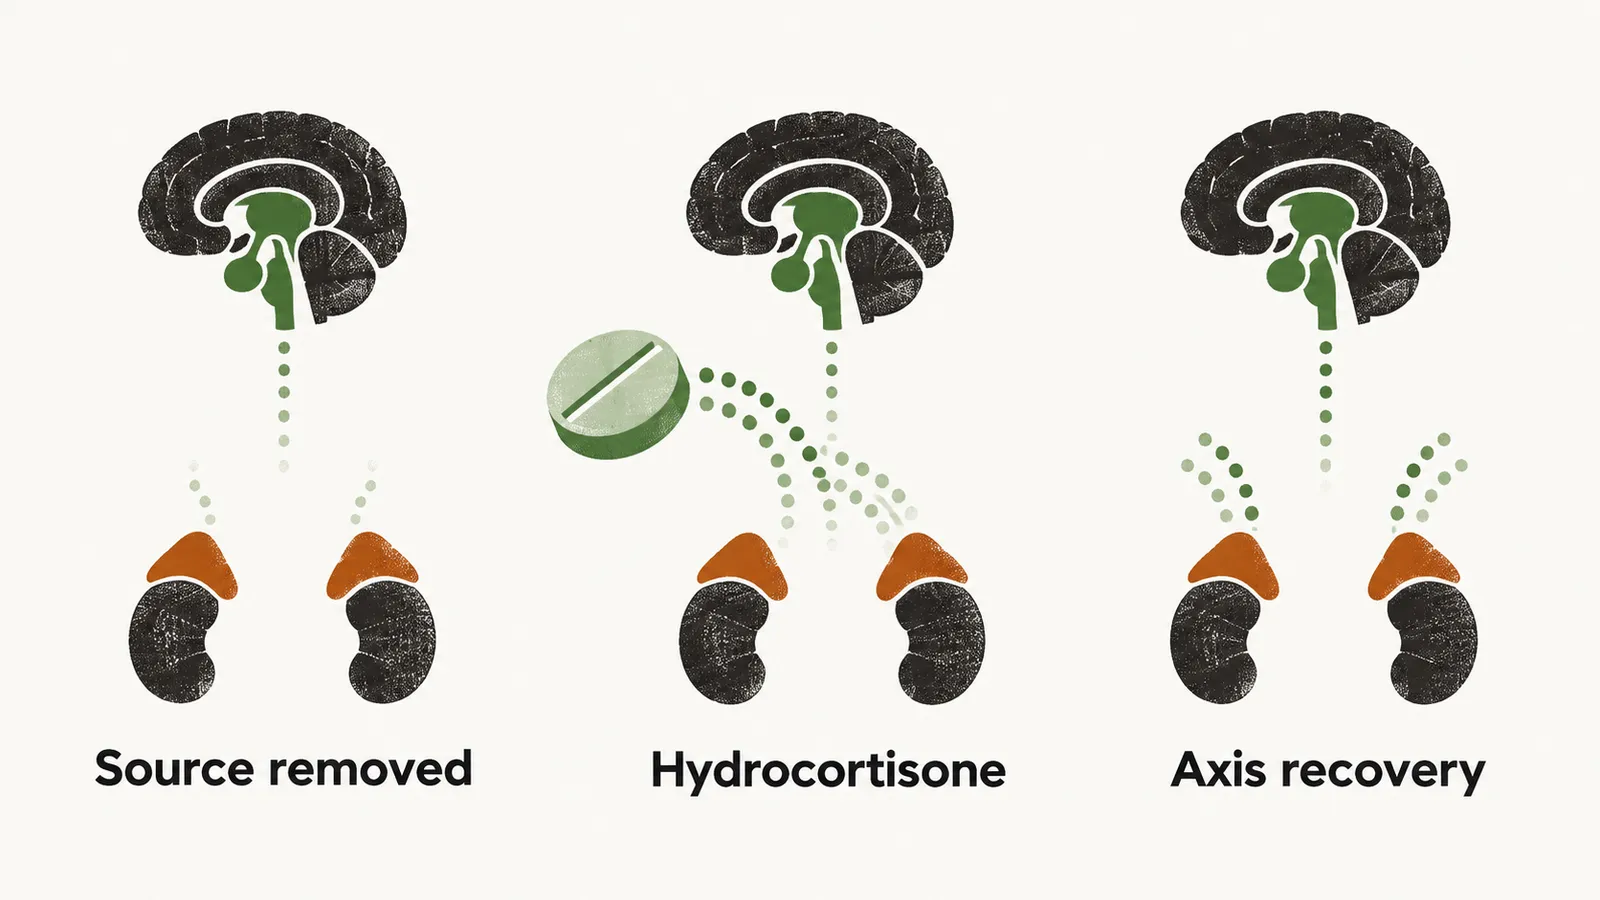
Whichever way the source is removed, the patient’s own axis has been suppressed. Successful removal leaves the patient temporarily adrenal insufficient, unable to make enough cortisol, because the normal cortisol-producing tissue was suppressed for as long as the disease lasted. Sustained high cortisol puts the normal axis to sleep, so when the source goes, nothing replaces it for a time.
Hydrocortisone, the medicinal form of cortisol, is therefore needed after surgery to fill the gap. Additional hydrocortisone doses are given during illness, because a normal gland would raise cortisol then and this patient cannot. Replacement continues until the axis recovers, which can take from a few months to a year or more. It is reassessed periodically rather than stopped abruptly, because stopping before the axis can make cortisol on its own would leave the patient without any.
Why does follow-up continue after remission?
Cure of the source is not the end of care. Follow-up serves three purposes.
First, recurrence is common, so cortisol is reassessed at regular intervals.
Second, the complications of excess do not all reverse with cortisol. Hypertension, diabetes, osteoporosis and raised cardiovascular risk need continued management. The hypercoagulable state described in Cardiovascular Complications of Cushing’s Syndrome persists around surgery and into early remission. Coagulation stays altered after surgical cure and surgery adds its own risk of venous thrombosis, which is the reason thromboprophylaxis is considered after pituitary surgery, particularly in patients at higher risk of venous thromboembolism.
Third, the thyroid. Patients successfully treated for Cushing’s syndrome have a significant increase in the prevalence of autoimmune thyroid diseases. Hypercortisolemia appears to mask underlying autoimmunity, so it is thought that when cortisol is normalised the masked autoimmunity can surface early. Thyroid function should therefore be followed after remission.
Once the cortisol excess has been removed, which of the damage it did will be reversed, and which will stay?