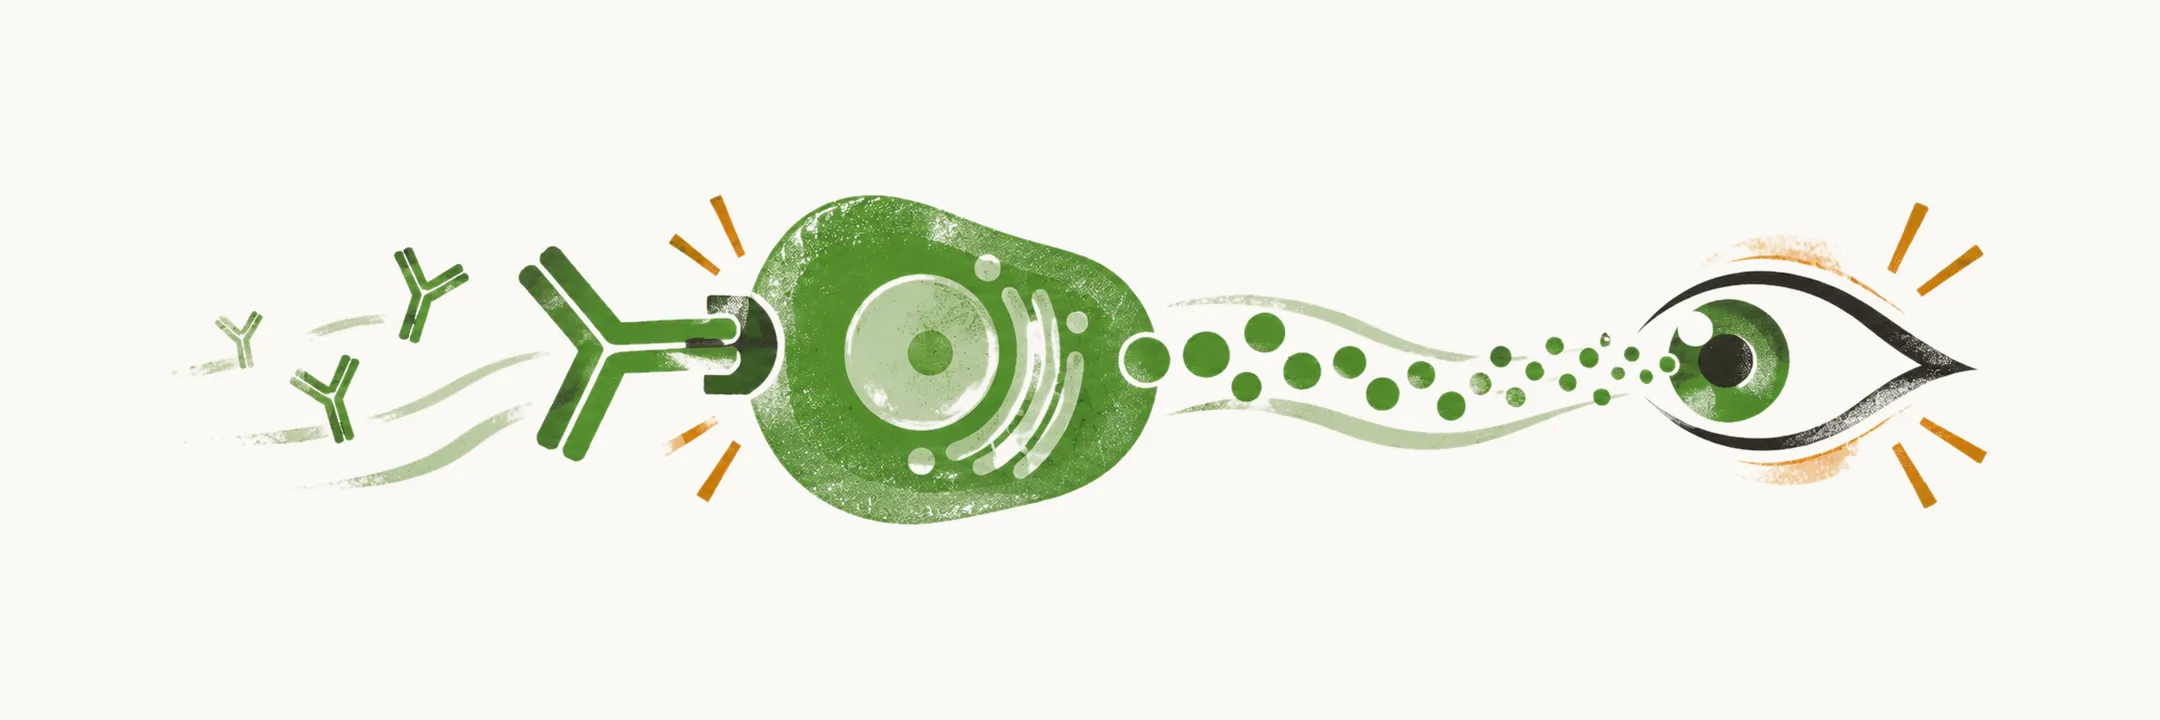
In the thyroid, TSH from the pituitary binds the TSH receptor on thyroid cells, and that binding makes thyroid hormone. In Graves disease the immune system makes antibodies against that same receptor. The receptor is not found only on the thyroid: fibroblasts in the orbit carry it too. So the autoimmune attack has a second target, and the eye is that target. The rest follows that one picture.
Graves disease is the most common cause of thyrotoxicosis and accounts for about 60-80% of cases. It is roughly ten times more common in women than in men, with a prevalence of about 2% in women and 0.2% in men. Whether Graves develops depends on genetic predisposition together with the level of iodine exposure.
Why does the immune system attack the thyroid?
Part of the answer is inherited. The onset of autoimmunity is a mix of inherited risk and environmental triggers, and inherited variants change how easily the immune system goes wrong. As in autoimmune hypothyroidism (Hashimoto thyroiditis), inherited variation predisposes to Graves disease.
The main identified genes fall into two groups. The first group is immune-regulatory:
- HLA-DR polymorphisms change how thyroid antigens are presented to T cells.
- CTLA-4, CD25 and PTPN22 polymorphisms, together with CD226, affect the signalling that keeps T cells in check, so a variant in one of them changes how well T cells are held back.
The second group is thyroid-specific. A TSH-R polymorphism alters the receptor, and that is the very receptor the antibodies target.
Together these variants lower the threshold at which the immune system attacks the gland. A lowered threshold still has to be crossed by something.
What tips the balance?
Several triggers are known:
- A sudden increase in iodine intake raises the incidence of Graves disease.
- The incidence of Graves disease rises three-fold after childbirth.
- Drugs that disturb immune regulation can also bring on Graves disease. Such drugs include highly active antiretroviral therapy (HAART), immune checkpoint inhibitors and alemtuzumab.
What do the antibodies actually do?
The hyperthyroidism of Graves is caused by thyroid-stimulating immunoglobulins (TSIs). These are antibodies made by lymphocytes residing in the thyroid gland, the bone marrow and the lymph nodes. The antibodies bind the TSH receptor and switch it on in place of TSH, as the earlier note showed. The gland is not switched off by feedback, the point that note made for autonomous tissue, so hormone production and gland growth go on without control.
Because these antibodies are the central driver of the disease, thyrotoxicosis with TSH-receptor antibodies in the blood defines Graves disease.
Other antibodies are present as well. Antibodies against thyroid peroxidase (TPO) and thyroglobulin (Tg) are found in more than 80% of cases. A thyroiditis can damage the gland at the same time as the TSIs stimulate it, and the balance between the damage and the stimulation differs between patients. The clinical progression of Graves disease is difficult to predict.
Why does the same attack reach the eye?
The same immune attack reaches the eye because the TSH receptor is also expressed in the orbit. It is found on orbital fibroblasts, where it is proposed as the link between thyroid and orbit. Ophthalmopathy is one of the most prominent clinical manifestations of thyrotoxicosis, including Graves disease.
After the antibodies bind the receptor on orbital fibroblasts, activated B and T lymphocytes are drawn into the orbit. Ophthalmopathy begins when T cells infiltrate the extraocular muscles and release cytokines. The cytokines involved include TNF, IL-1 and IFN.
The cytokines activate orbital fibroblasts to make glycosaminoglycans (GAGs). GAGs are hydrophilic, so they attract and trap water in the tissues around and behind the eyeball, and those tissues swell.
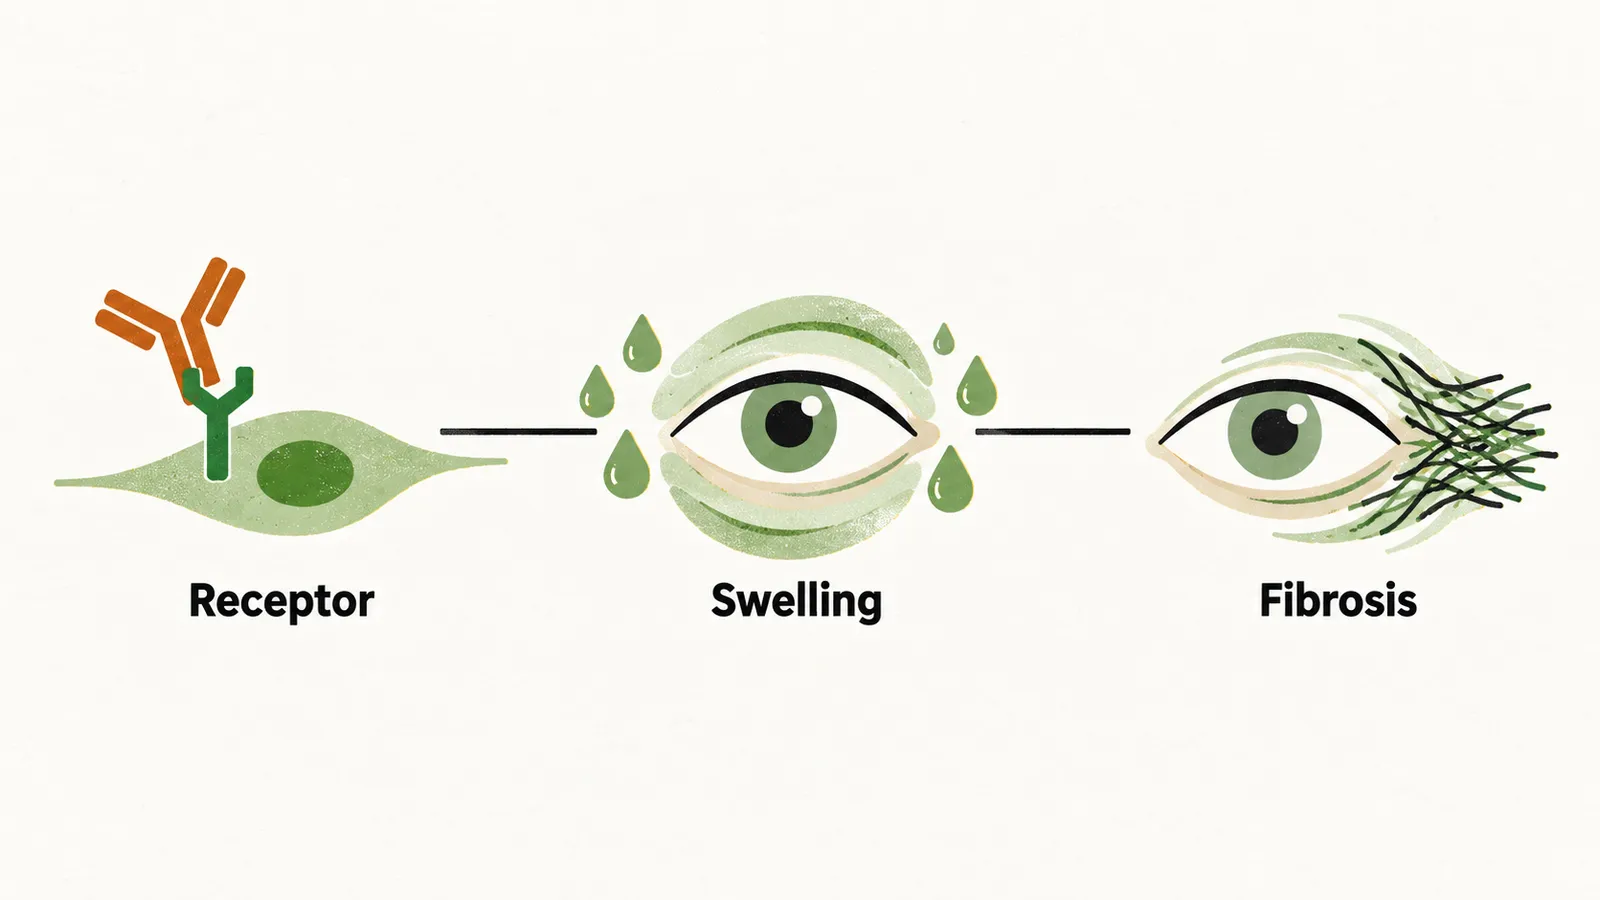
In the late stage the process turns into irreversible fibrosis, the scar-like end stage of the ophthalmopathy. It is accompanied by fat accumulation around the eye, which arises through new fat-cell formation in the orbit.
What do the changes do to the eye?
The enlarged muscles do not move the eye as they should. The eyes no longer line up, and the brain reads this as double vision, so ophthalmopathy can cause diplopia. Expansion of the fat and muscle behind the eyeball pushes the eye forward out of its socket, which gives proptosis. Enlarged muscle can also press on the optic nerve behind the eye, and this compression is the mechanism of the nerve damage, so ophthalmopathy can cause optic neuropathy.
These are the eye signs, but which of them does a patient show first, and what else does the disease do to the body?