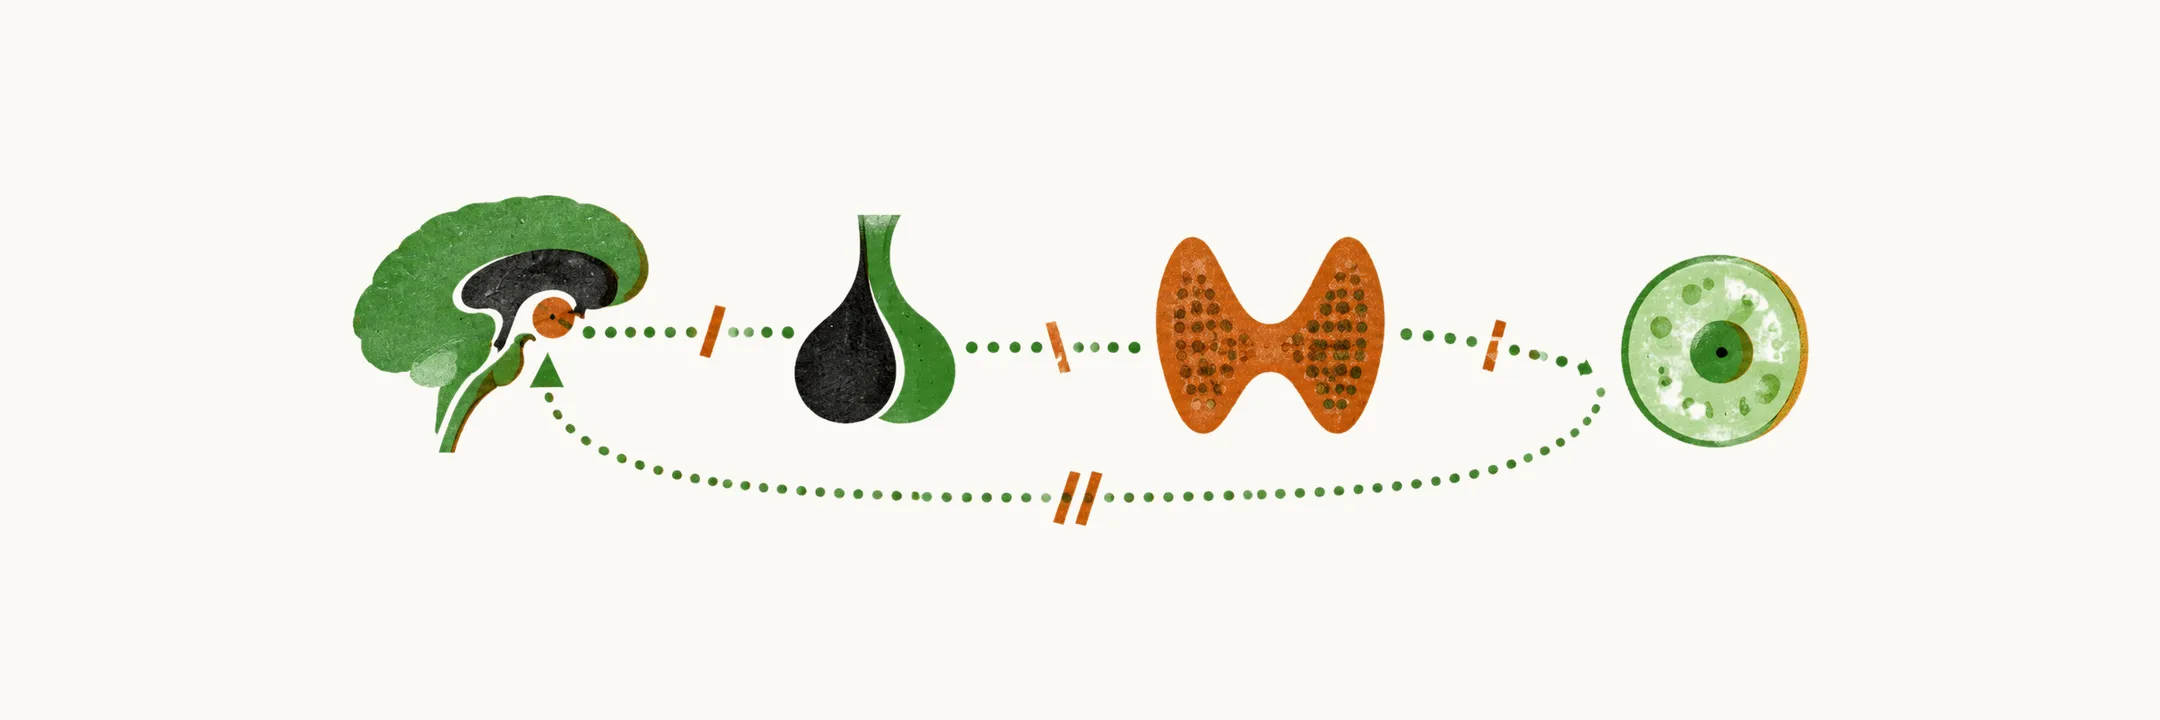
Hypothyroidism is low production of thyroid hormone. The hormone is made by the thyroid gland, and the gland is only the last link in a chain, so the first question is where in that chain the failure starts.
Where can the failure start?
The hypothalamus releases TRH, and TRH drives the pituitary to release TSH. TSH is the signal that tells the gland to make hormone. The hormone then feeds back on the pituitary and the hypothalamus, so when hormone falls, TSH rises.
Because TSH is the main stimulus for the gland’s hormone production, low production can come from two places: the gland itself, or the signal that drives it. The site of the fault decides which test can be trusted and what treatment is needed.
- Primary hypothyroidism: the thyroid gland itself cannot make enough hormone.
- Central hypothyroidism: the gland is capable, but the pituitary supplies too little TSH, the signal that drives it.
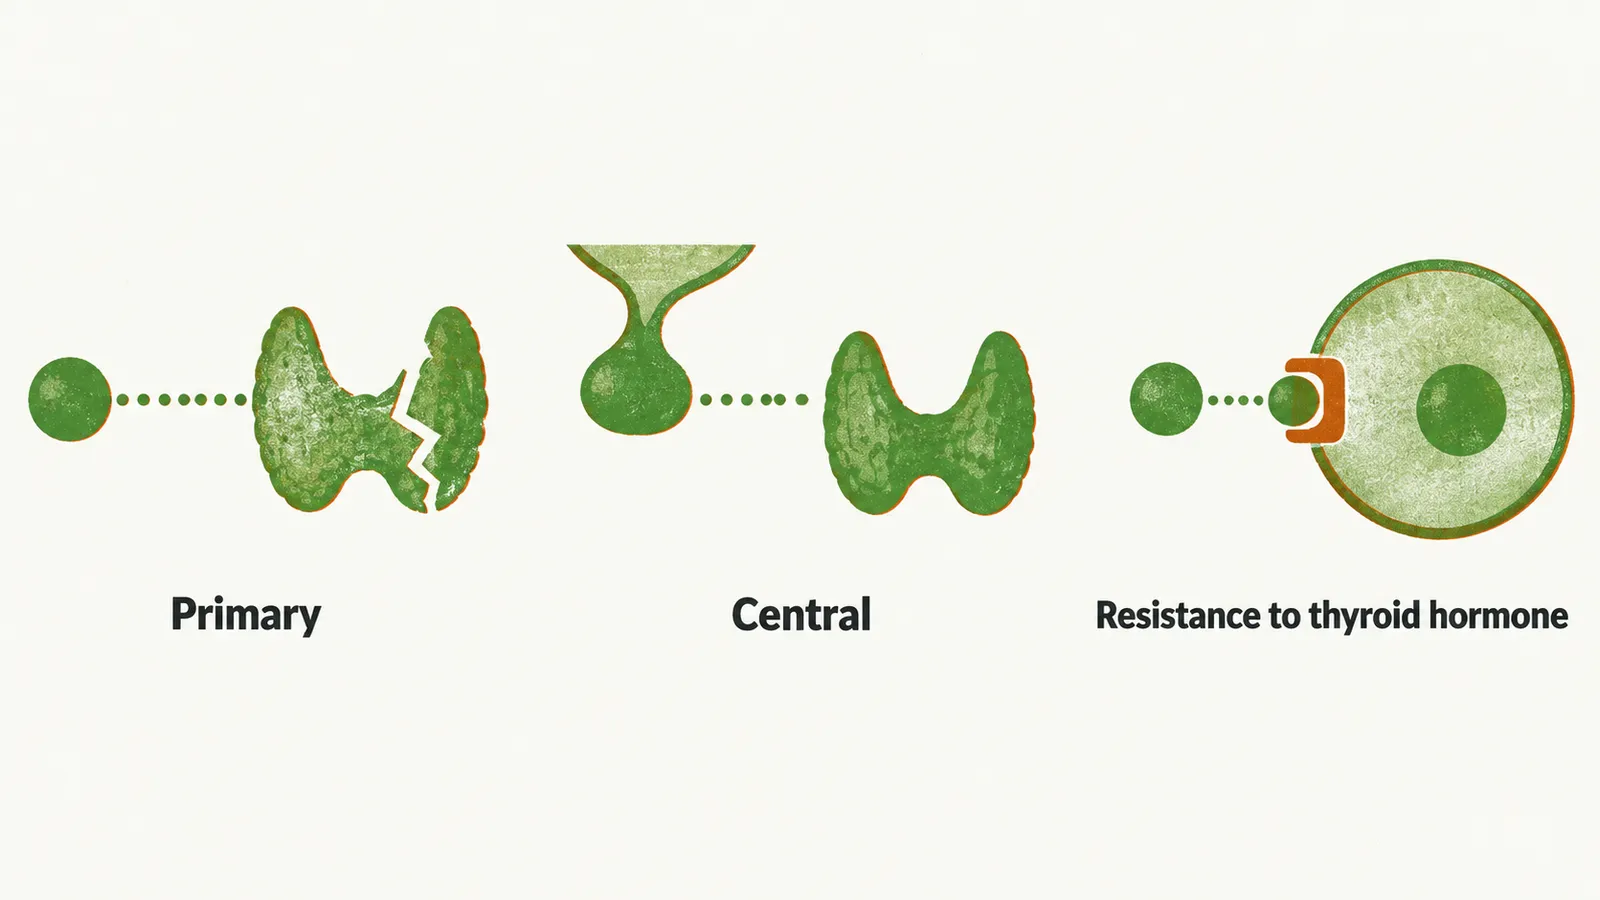
What does the pituitary do when the gland is the fault?
If the gland is the failing link, the pituitary is still working. It is healthy and it senses the falling hormone, so it sends out more TSH to push the gland harder. This is the feedback loop doing its job.
That explains why, in primary hypothyroidism, the TSH rise makes TSH the sensitive first test.
What happens when the pituitary is the fault?
In central hypothyroidism the disease lies in the pituitary or the hypothalamus. The hypothalamus releases TRH, which stimulates the pituitary to secrete TSH, so disease at either site removes the drive to the gland. The gland then gets too little signal, even though it could make hormone.
The pituitary cannot mount the TSH response that we saw in primary disease. The gland depends on TSH from the pituitary, and without working thyrotrophs hypothyroidism follows. Because TSH is the message to the gland, a TSH value no longer tracks the gland’s output when the pituitary is the fault. So TSH may be low, normal, or even slightly raised.
This is why distinguishing the central form matters. TSH reaches the gland through the pituitary, so once the pituitary is the fault, TSH can no longer be trusted to show how the gland is doing.
Why is free T4 the marker to follow?
TSH can no longer be trusted, so the reader needs another guide. TSH is only the stimulus. The gland’s output is the hormone itself, and free T4 (thyroxine) is the level that still reflects the gland when the signal does not. So in central hypothyroidism, the free T4 level becomes the marker to follow instead. The choice of lab test to follow changes with the site of the fault.
What if the tissues are the fault?
The third group is failure of response, not failure of supply. This is resistance to thyroid hormone.
Thyroid hormone acts through nuclear receptors that regulate genes. If the receptor is faulty, the hormone has nothing to act on. Resistance to thyroid hormone is usually caused by a mutation in the thyroid hormone receptor.
Hormone is measured in the blood, but the fault lies in the cell, where the receptor fails to pass the signal on. So the hormone level may be normal or high while the tissues respond poorly. A person can therefore show features of hypothyroidism despite adequate hormone in the blood.
Why would the gland lack its building block?
Back at the gland, there is a cause that has nothing to do with the signal. Iodine is built into thyroid hormone, so a diet short of iodine leaves the gland without the material to make it. Worldwide, iodine deficiency is the most common cause of hypothyroidism wherever dietary iodine is low.
What destroys the gland where iodine is sufficient?
When iodine is enough, something else takes over. In iodine-sufficient areas, autoimmune thyroiditis, mainly Hashimoto’s thyroiditis, is the most common cause. In Hashimoto’s thyroiditis, lymphocytes infiltrate the gland and destroy it gradually. Because the destruction develops slowly, the gland can pass through a long subclinical phase before hypothyroidism becomes overt.
What else damages the gland?
After autoimmune destruction, the next cause in iodine-sufficient areas is treatment. This is iatrogenic hypothyroidism. It results from treating hyperthyroidism by surgery, radioiodine, or antithyroid drugs, or from irradiation to the neck. Here the cause is already known from the patient’s treatment for hyperthyroidism.
Why does a baby’s gland fail?
Congenital hypothyroidism has a separate start: it is present from birth. The loss of gland function is there when the infant is born, so the baby has little hormone from the start. It is usually due to a gland that never developed normally or to a defect in hormone synthesis. A gene fault, either in the development of the gland or in a step of hormone making, can explain such cases.
What covers the rest of the causes?
The remaining causes fall into groups by mechanism. Some are neither gland, pituitary nor receptor failures. The central and congenital groups are described above. The other two are:
- Drug-induced hypothyroidism: from drugs that interfere with hormone synthesis or release, such as amiodarone and lithium. Amiodarone releases iodine as it is broken down, and that iodine can impair thyroid function.
- Altered metabolism of thyroid hormone: reduced conversion of the prohormone T4 into active T3, or increased deactivation of the hormone. Much of the active T3 comes from conversion of T4 in peripheral tissues. Amiodarone, for example, reduces that production by inhibiting 5’-deiodinase.
Which two causes matter most at the bedside?
At the bedside, two causes deserve particular attention: autoimmune destruction and the iatrogenic group. The iatrogenic cause is already known from the patient’s treatment. Autoimmune destruction develops slowly. So how can a gland be failing for a long time before any sign shows?