Why does fat tissue belong in this disease?
Adipose tissue is an active participant in T2DM, not a passive fat store. Its inflammation is largely commanded by cytokines released by the adipocytes themselves, and these cytokines are known as adipokines.
Obesity places adipose tissue at the centre of the disease: more than 85% of patients in the US who have T2DM are obese. If these cells work against insulin, what changes inside them?
What changes inside a fat cell?
Insulin holds fat cells back from breaking down their triglyceride and pulls fatty acids out of the blood into them, as the normal glucose homeostasis note sets out. The question now is what happens to the store once the cells stop answering insulin.
In T2DM the adipocytes become insulin-resistant, and both of these insulin effects weaken. Insulin is a brake on fatty acid flow out of fat, so when its effect weakens, fat leaves the store freely. Free fatty acids (FFA) are normally taken back into cells from the blood, so when that uptake fails, they stay in the blood. With no brake and no uptake, the result is a high concentration of circulating FFA that lasts all day.
Where does the leaked fat go?
Excess FFA work against insulin themselves, worsening tissue sensitivity, and they accumulate in liver and muscle. Excess lipid is harmful in itself, and this direct injury is called lipotoxicity.
How does that fat stop insulin’s signal?
Fatty acids that enter the cell do not only build up; they reach the signal itself. A high level of FFA in cells and in the circulation promotes insulin resistance, and it does so in several ways: through an oxidative burden inside the cell, which is followed by endoplasmic reticulum stress, and through the steps below.
First, FFA inhibit insulin receptor substrate (IRS). Diacylglycerol-driven PKC activation phosphorylates IRS and blocks it. IRS carries the insulin signal inside the cell, so blocking it stops that signal.
Second, FFA reduce insulin’s vasodilatory effect on the endothelium. Nitric oxide (NO) production is controlled by the IRS pathway. If the pathway is blocked, the vasodilator effect is reduced.
Why does fat burning cut glucose use in muscle?
Fat in muscle does more than block the signal; it changes which fuel the cell burns. The Randle cycle explains the effect of accumulated FFA on glucose use. Muscle is the main place where glucose is taken up after a meal, as the normal glucose homeostasis note explains.
The steps run in a chain of inhibitions:
- A high FFA level drives high β-oxidation of FFA in mitochondria, and this chain-reacts through the cell.
- High β-oxidation produces a large amount of acetyl-CoA, which inhibits pyruvate dehydrogenase.
- It also raises the NADH/NAD ratio. The Krebs cycle enzymes are NADH-dependent, so the raised ratio slows the cycle.
- The stalled Krebs cycle lets citrate accumulate, and citrate is a potent inhibitor of the enzyme PFK.
- With PFK inhibited, glucose-6-phosphate accumulates, and entry of glucose into the muscle cell falls.
- With less glucose entering, there is less glycogen synthesis and less glucose oxidation.
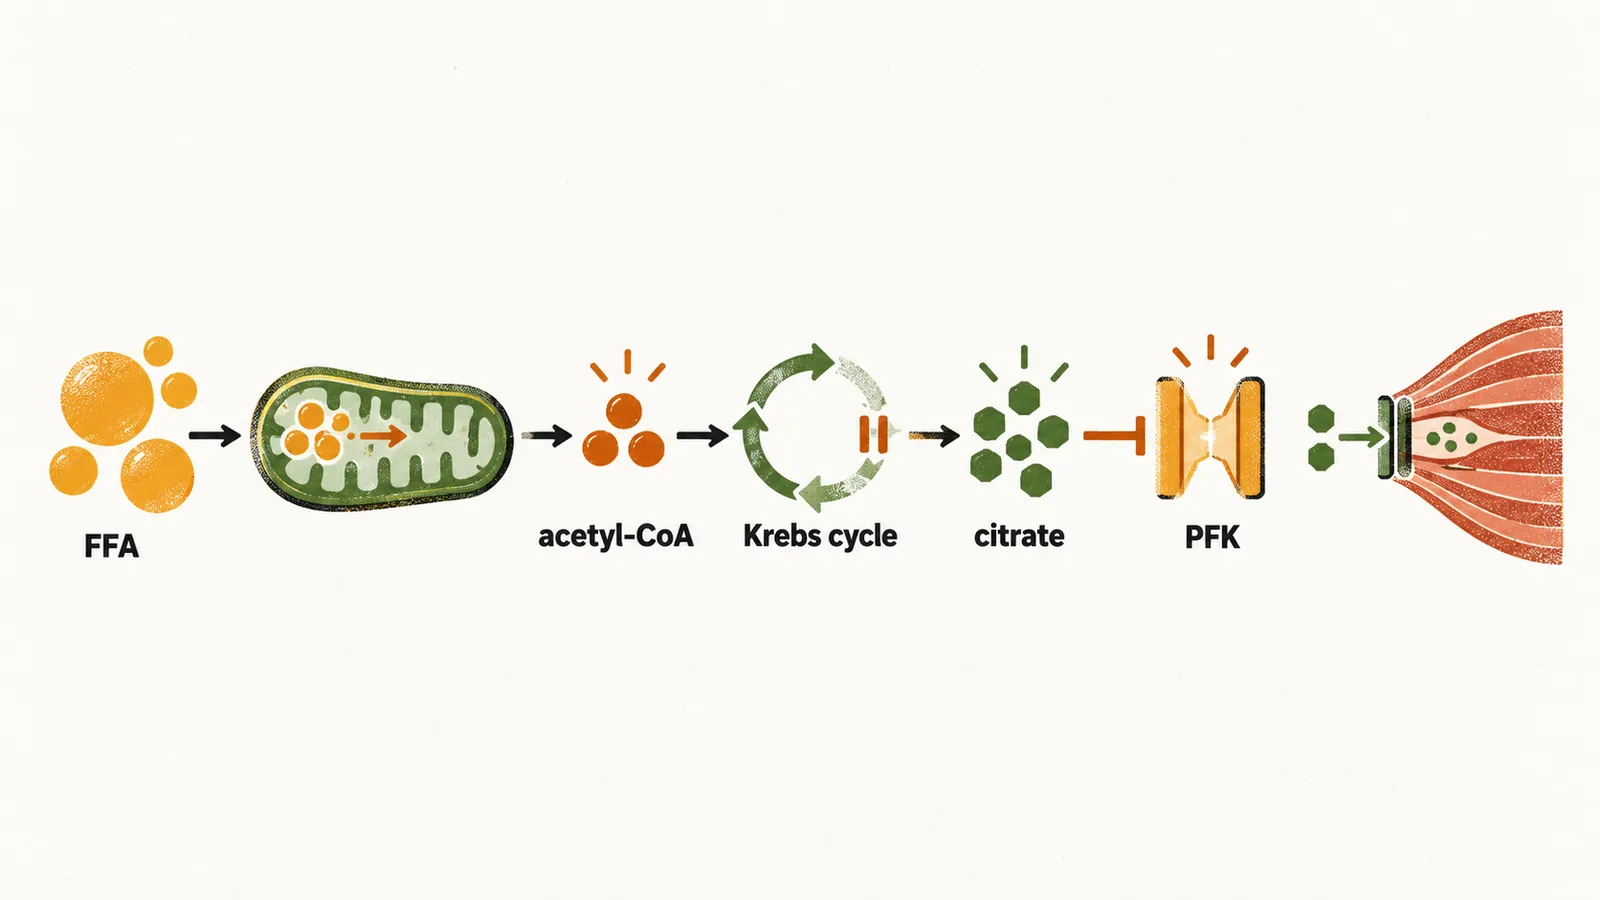
The conclusion is that a high oxidation rate of FFA reduces uptake, oxidation and use of glucose in cells.
Are there other routes from fat to resistance?
Blocking IRS and starving glucose use are not the only routes the research has found. More recent human studies show that a rise in FFA β-oxidation does not only reduce glucose oxidation and glycogen formation. It can also induce insulin resistance through other signalling pathways. Through these pathways, FFA β-oxidation inhibits PKC, and inhibited PKC inhibits IRS. It also inhibits PKB, and inhibited PKB inhibits glycogen synthase.
Do the fat cells’ own messengers add to this?
The fat cells also send their own messengers, and these add to the same damage. Chronic, low-grade inflammation of adipocytes has been suggested to increase the chance of insulin resistance and of developing T2DM. Immune cells gathering in fat release cytokines that likely impair insulin signalling in liver and muscle. Several adipokines are relevant to the pathogenesis of T2DM.
Adiponectin is inversely related to metabolic syndrome, T2DM and atherosclerosis. This is its protective pattern, because it is anti-diabetic, anti-inflammatory and anti-atherogenic. It increases oxidation of FFA, reduces glucose production by the liver, and suppresses the effect of tumour necrosis factor (TNF) and NF-κB. It falls in obesity, which removes a protective signal.
Human resistin is a cytokine released by immune cells that infiltrate adipose tissue, and it triggers those immune cells to produce adipokines.
Leptin is physiologically a suppressor of appetite, but obese patients are resistant to it. Hyperleptinemia can therefore be found in obese patients because of leptin resistance, and it is associated with an inflammatory state in the body.
Visfatin is an adipokine that is increased in obese patients and has a pro-inflammatory effect.
What happens when the fat reaches the liver?
The liver is the next place this fat goes. The incidence of metabolic dysfunction-associated steatotic liver disease (MASLD), formerly called non-alcoholic fatty liver disease, is rising, and complications tightly related to insulin resistance in T2DM have become more common with it.
In MASLD there is steatosis, the accumulation of FFA inside hepatocytes. Insulin resistance with hyperinsulinemia stimulates triglyceride synthesis and accumulation in the liver, and this accumulation is the steatosis. It makes hepatocytes vulnerable to injury and fibrosis. In patients with T2DM the same progressive insulin resistance reaches the hepatocytes, and the accumulating FFA lead to MASLD formation. They also lead to progression toward severe and fibrotic forms of MASLD.
Two processes acting together drive this progression. The first is insulin resistance with further FFA accumulation in hepatocytes. The second is formation of reactive oxygen species during β-oxidation of those FFA.
What pushes glucose up in T2DM, and how do those causes add together? The Eight mechanisms of hyperglycemia in type 2 diabetes mellitus note takes this up.