
Normal glucose homeostasis does two jobs. It keeps blood glucose steady between meals, and it disposes of the glucose load after eating. Both rest on one idea: blood glucose is the difference between what enters the blood and what leaves it. If the two flows match, the level holds. If they differ, the level moves.
The body describes its glucose state in two phases. The post-absorptive state is 10–12 hours after fasting. The post-prandial state follows the ingestion of glucose. Why do the two differ? Because the liver makes glucose during fasting and stores it after a meal.
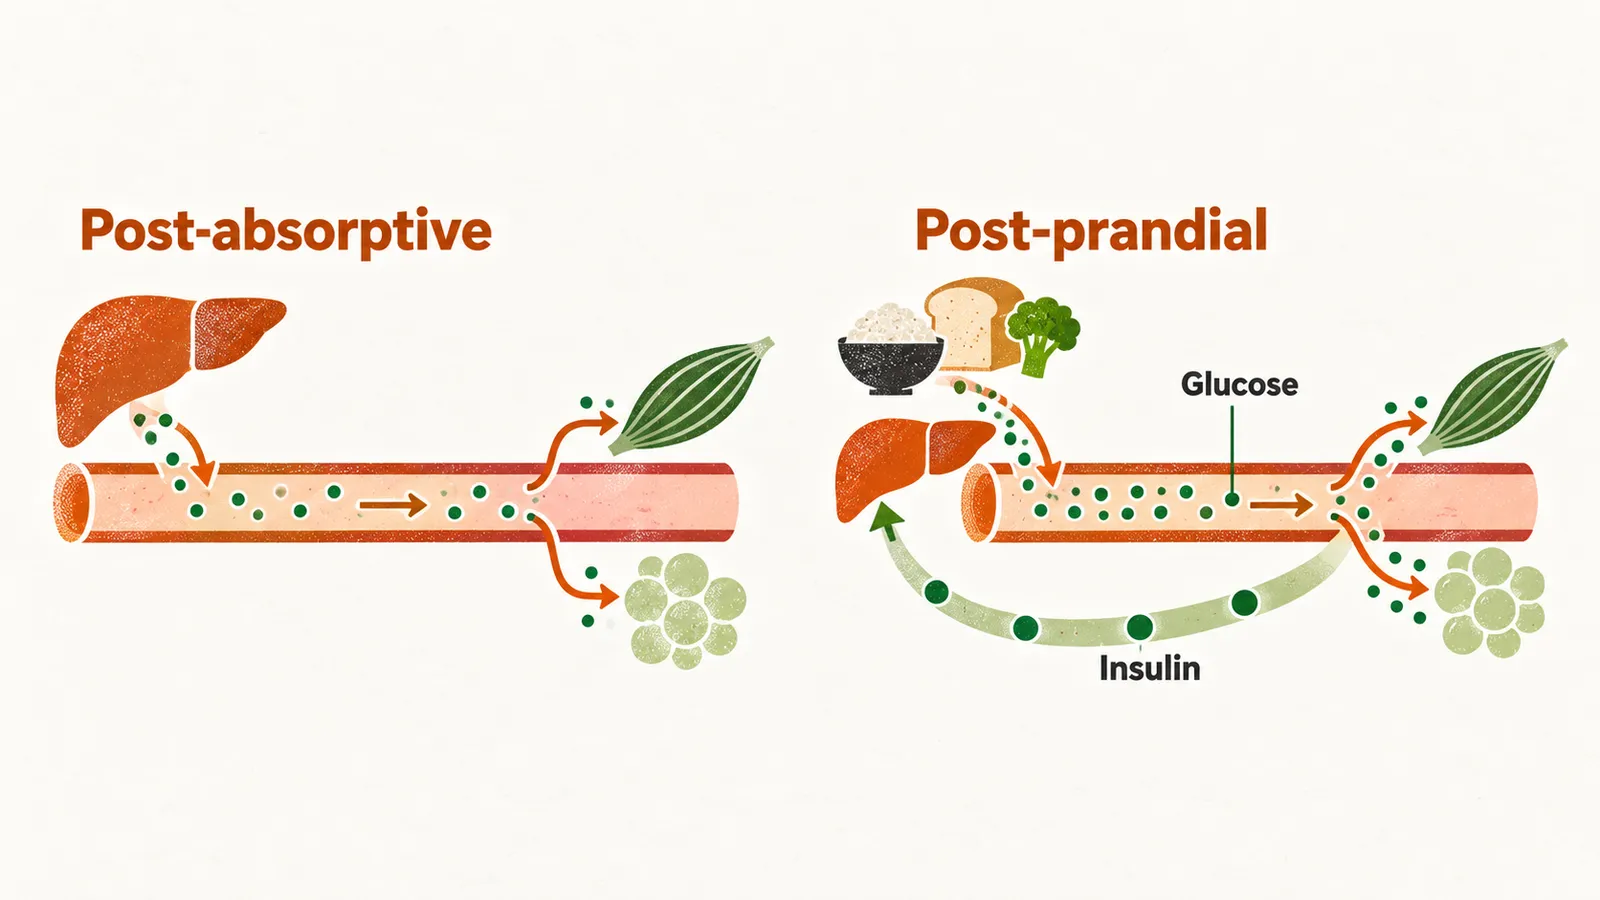
Between meals no glucose comes from food. So where does the blood glucose come from?
Where the body’s own glucose comes from
In the post-absorptive state the blood level depends on what the body releases into the blood itself. This is endogenous glucose production (EGP). The body makes glucose through metabolic reactions that keep the blood level constant in fasting.
More than 85% of EGP comes from the liver. The liver holds glycogen and can make new glucose, which is why it is the main source. The kidney also makes glucose, but its contribution is smaller.
Nothing else supplies glucose in the fasting state, so the basal glucose utilisation rate has to match EGP precisely. It averages around 2 mg/kg.min. The result is a perfect balance between EGP and the body’s glucose need.
Once that glucose is in the blood, which tissues take it up?
Who uses the glucose between meals
In the post-absorptive state the glucose used in the body is distributed among three consumers:
- the brain, 50% of the glucose;
- the splanchnic area, 25%;
- insulin-dependent tissue, mainly muscle, 25%.
The brain and the splanchnic area use glucose without needing insulin. Brain uptake is not affected by insulin, so it does not change with the insulin level. Muscle works differently: it takes glucose in through transporters tied to insulin.
What changes when a meal arrives?
What a meal changes
The balance between EGP and the body’s glucose need is disrupted once exogenous glucose is introduced. A meal adds glucose from outside the body, and it reaches the liver first through the portal vein.
After a glucose-containing meal, hyperglycemia and hyperinsulinemia increase glucose absorption into the splanchnic and peripheral tissues. Of the glucose taken up in the periphery, about 85% is disposed of in muscle tissue, which is the main site of glucose deposition during meals. About 5% is metabolised by adipocytes.
Insulin does more than drive uptake. It reduces EGP: insulin acts on the liver to suppress glucose output. It also lowers the plasma free fatty acid (FFA) concentration, because its effect on adipose tissue is to suppress lipolysis, so fewer FFA reach the plasma.
Insulin does all this, but how does it get to the muscle cells?
How insulin reaches the muscle
Insulin has to cross the capillary wall into muscle before it can act. So the first and rate-limiting step of its effect on peripheral tissues, mainly muscle, is the transport of insulin from plasma to muscle cells.
This step is thought to depend mainly on insulin receptors on endothelial cells and on activation of nitric oxide (NO) synthase in endothelial cells. Insulin is thought to widen muscle capillaries through a nitric-oxide-dependent action. A proposed explanation is that the wider capillary bed lets more insulin reach the muscle fibres.
These shares were measured with intravenous glucose. What do those measurements show?
What intravenous measurements show
The results above relate to the intravenous route, which bypasses the gut. In normal subjects, whole-body glucose uptake with intravenous glucose is around 7 mg/kg.min.
CNS glucose uptake is constant at around 1–1.2 mg/kg.min. It is the same in normal and diabetic patients and in the post-absorptive and post-prandial states. This is because brain uptake is insulin-independent.
Splanchnic glucose uptake, mainly in the liver, is only about 0.5 mg/kg.min in the post-prandial state. It is similar in normal subjects and in patients with type 2 diabetes. The majority of the glucose, more than 85%, is taken up by muscle tissue.
A meal is taken by mouth, so does the route change the picture?
Glucose taken by mouth
It does. Oral glucose ingestion distributes the load differently. Glucose by mouth goes to the liver through the portal vein, so the gut and liver see glucose before the rest of the body. This route raises net hepatic uptake compared with intravenous delivery. That is why splanchnic uptake plays an important role after oral glucose: splanchnic tissues take up 28% of the oral glucose, and peripheral tissues take up 72%.
Within the peripheral fraction, brain uptake is still 1–1.2 mg/kg.min. Muscle tissue takes up 45% of the total oral glucose. Peripheral uptake is quantitatively smaller by the oral route, but peripheral tissue is still the largest single destination of oral glucose.
Insulin reaches the liver through the portal vein and directly suppresses liver glucose output. Basal hepatic glucose production (HGP) declines by 53% after oral glucose. Even so, EGP is less suppressed than after intravenous glucose. Endogenous glucose therefore continues to be produced after oral ingestion, because the suppression of EGP is incomplete.
This works while insulin secretion keeps pace with tissue response. How is that balance kept?
How β-cell secretion keeps pace with sensitivity
The same balance applies to insulin itself. Glucose homeostasis depends on a hyperbolic relation between insulin sensitivity and β-cell function. Compensation is measured as the product of the two, and that product stays roughly constant.
So if tissues respond more, less insulin is needed from the β cells. If tissues respond less, more is needed. Because of this link, a change in one shifts the other.
What happens when the tissues stop responding and the β cells can no longer make up the difference?