Diarrhea is not one disease. It is the shared end point of several failures in how the intestine handles water. The mechanism matters because it predicts the electrolyte pattern of the stool, the response to dietary change and the approach to rehydration.
The mechanism is a failure of something the bowel does every day, so that is where to start.
How does the bowel normally keep its water?
The body pours a great deal of its own fluid into the gut: saliva, gastric juice, bile, pancreatic juice and intestinal secretions. This endogenous fluid forms a large daily volume entering the small intestine. The lining moves water and salts in both directions, and along the length of the bowel it takes back almost all of that volume before the stool is formed. That is why only a small amount of water normally leaves the body this way.
Diarrhea means that the reabsorption has failed, and the loose stool is the visible result.
In how many ways can reabsorption fail?
Because diarrhea means reabsorption has failed, the next question is how it fails. There are three routes:
- More solute is left in the lumen than the mucosa can carry.
- Secretion into the lumen overtakes absorption. The same lining can secrete as well as absorb, so the balance can tip toward secretion.
- The absorbing epithelium is damaged. Rotavirus, for example, infects the absorbing cells and destroys them, which removes the absorptive surface.
Damaged absorbing epithelium is the commonest route in children with acute gastroenteritis. The reason is that rotavirus preferentially infects the enterocytes of the mature small intestine and destroys them.
What happens when solute stays in the lumen?
The first route leaves solute behind. In osmotic diarrhea, osmotically active solute remains in the lumen and keeps water with it. Lactulose is the clean prototype. It is a sugar that normal mucosa does not absorb, so it stays in the lumen and the water stays with it. Unabsorbed carbohydrate behaves the same way: it stays in the lumen, and water follows it.
What does a virus do to the absorbing cells?
The commonest route in children is damaged absorbing cells, so the question is what the virus does to them. In viral gastroenteritis the same osmotic logic applies, but through damage. Rotavirus is likely to cause osmotic diarrhea through the loss of absorptive enterocytes.
The virus injures the small-bowel epithelium. The brush-border enzymes, lactase among them, are made by the absorbing cells, so when the cells are destroyed the enzymes fall with them. Carbohydrate that would normally be digested and absorbed stays in the lumen, and water follows it. The mucosa is also anatomically abnormal, so its digestive and absorptive function are both compromised, and absorption is lost as well as enzyme activity.
That is why the usual cause of osmotic diarrhea in children is viral enteritis with loss of brush-border enzymes. Rotavirus damages the absorbing cells, which is likely to produce the osmotic picture.
What happens when the lining secretes instead?
When the mucosa is intact, the route is secretion. Secretory diarrhea occurs on an intact mucosa: the lining stays in place, and the same cells that normally absorb now secrete. The trigger is an enterotoxin or an endogenous secretagogue. Cholera is the classical example.
The mucosa looks normal under the microscope. The cells keep their structure while their transport behaviour changes, so the fault lies in what the cells do and not in what they are.
What does the toxin switch on?
The toxin acts through a signal inside the cell. The trigger raises intracellular second messengers. In experimental cholera the epithelial cells show a raised level of cyclic AMP, and studies of heat-labile enterotoxins show that they act through adenylate cyclase. The raised signal makes the epithelium secrete chloride into the lumen, and water follows the salt. The epithelium also stops absorbing sodium. In children, an enterotoxin acting on an intact mucosa produces the secretory picture.
How does the stool show which mechanism is at work?
Both pictures pass water, so what differs is the makeup of the stool. Stool osmolality is normally close to that of plasma, because the lumen contents equilibrate with plasma water. This is still true when unabsorbed solute holds water in the lumen. What changes is the makeup of the osmoles.
In osmotic loss, sodium and potassium account for only a small share of the stool osmoles. In secretion-driven loss, stool sodium and bicarbonate appear in far higher concentrations than usual.
What does the osmotic gap measure?
The gap is a test that separates the two pictures. The fecal osmotic gap is the plasma osmolality minus twice the sum of the stool sodium and potassium. It asks how much of the stool’s osmolality comes from something other than sodium and potassium.
A large gap means that much of the osmolality is from something other than sodium and potassium. That points to an osmotic mechanism, and it fits with the low share that these ions carry. A small gap means sodium and potassium account for the osmotic load, which points to a secretory mechanism. The gap can be calculated at the bedside in watery diarrhea.
The gap belongs more to the chronic or unexplained picture than to ordinary acute gastroenteritis, where the mechanism is usually apparent from context.
How do the two pictures compare?
With each mechanism and its test in view, the question is how each picture settles.
| Osmotic | Secretory | |
|---|---|---|
| Mucosa | Damaged | Intact |
| Usual cause in children | Viral enteritis with brush-border enzyme loss | Enterotoxin, as in cholera |
| Stool sodium | Low relative to plasma | High, close to plasma |
| Fecal osmotic gap | Large | Small |
| Settles when | The offending solute is removed or the epithelium regenerates | The toxin is cleared |
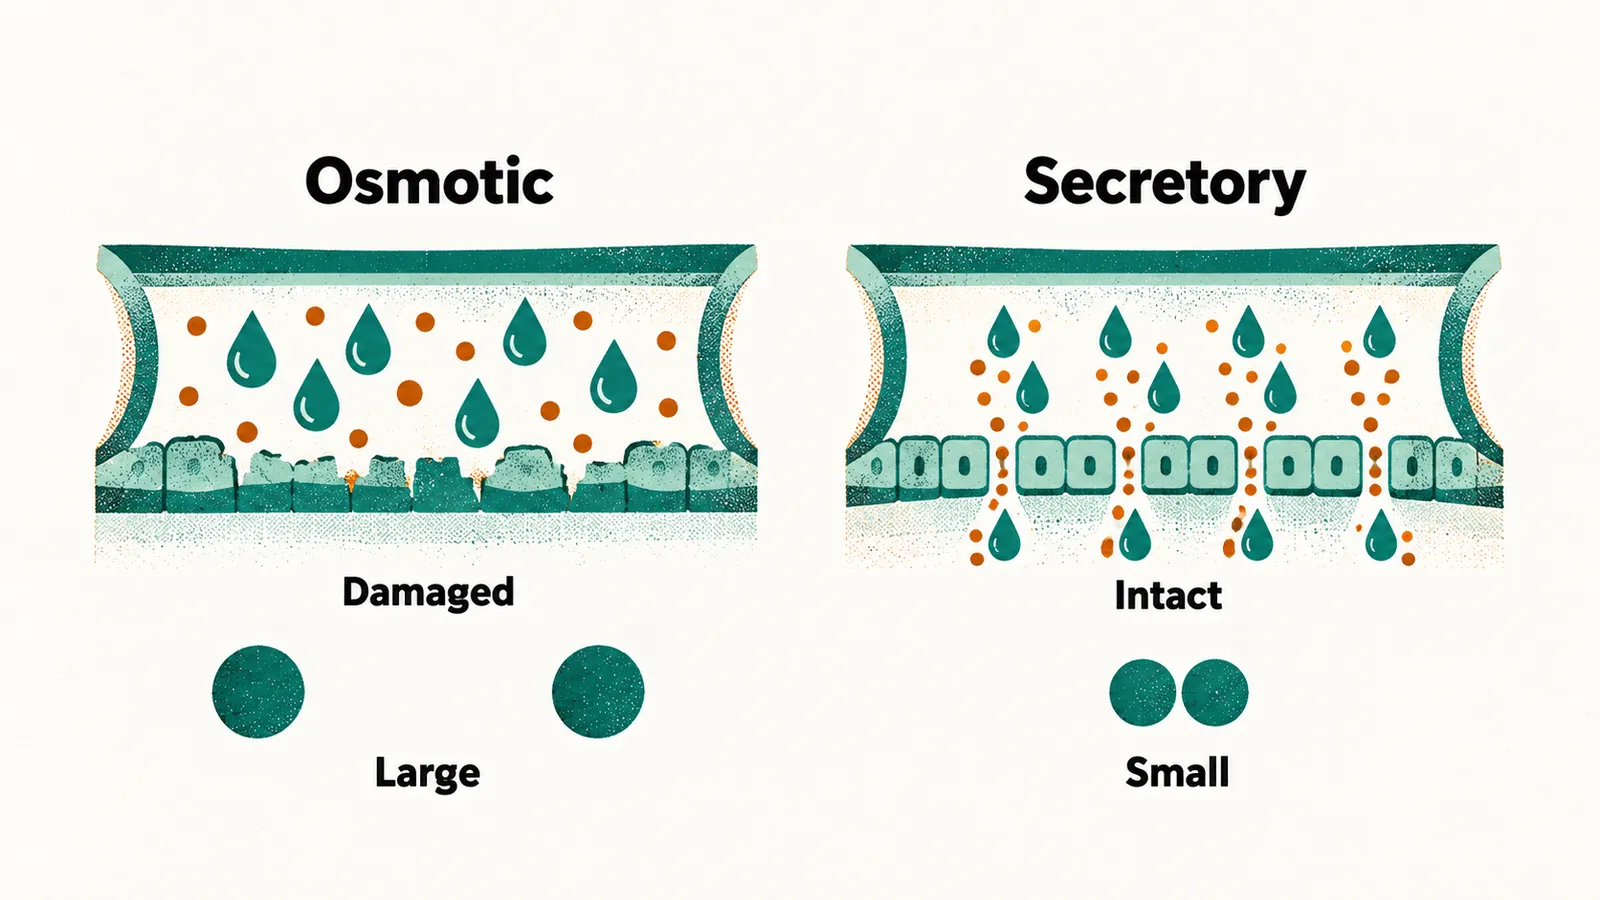
A toxin that drives chloride into the lumen brings salt with it, so stool sodium is not depleted as it is in the osmotic picture. Osmotic diarrhea has structural repair to wait for, which is why dietary decisions matter in viral disease. Secretory diarrhea has no structural repair to wait for.
Why does lost water make diarrhea dangerous?
Whatever the mechanism, the water the bowel fails to take back is lost from the body. This loss is what makes diarrhea dangerous. The result is dehydration: loss of body water with a matching fall in plasma volume.
Why do children dehydrate sooner?
Children reach dehydration sooner than adults. They turn over more water per kilogram, and they have a larger surface area relative to their weight. They also lose more through the skin and lungs. In early infancy they concentrate urine less effectively. Acute diarrhea is the most common cause of dehydration in early childhood.
Which routes take water out of the body?
The gut is one of four routes that produce dehydration: gastrointestinal, renal, cutaneous and insensible loss.
- Gastrointestinal loss is the dominant route in children, and acute gastroenteritis is the prototype.
- Renal loss occurs through osmotic diuresis in diabetes, free-water loss in diabetes insipidus, adrenal insufficiency and chronic renal impairment.
- Cutaneous loss occurs in burns.
- Insensible loss means that fever and tachypnea increase the loss through the skin and lungs without anything visible being lost. The water leaves as vapour.
What does the sodium level decide?
Plasma sodium concentration decides whether the deficit is replaced with a relatively sodium-poor or a relatively sodium-rich fluid, and therefore how quickly sodium may safely be corrected. Recognising the sodium pattern belongs to Clinical Assessment of Acute Diarrhea and Dehydration. Correcting sodium belongs to Rehydration Management in Acute Diarrhea.
Does the mechanism decide when feeding can restart?
Each picture settles in its own way, and that decides when the gut is ready to be fed again. Osmotic diarrhea settles when the offending solute is removed or the epithelium regenerates. Secretory diarrhea settles when the toxin is cleared. The dietary consequences of a damaged brush border belong to Refeeding and Drug Therapy in Acute Diarrhea.
Which organisms produce which picture?
The mechanisms are now in place. Viral enteritis injuring the small-bowel epithelium produces the osmotic picture in children, and an enterotoxin acting on intact mucosa produces the secretory picture. Knowing which organisms are common, and the pattern each produces, is the next step in reading a child with acute diarrhea. So which organisms cause acute diarrhea in children, and how do their clinical patterns differ? Etiology and Risk Factors of Acute Diarrhea in Children answers that.