
Rehydration management means replacing the water and salts a child with acute diarrhea has lost, and continuing that replacement while the illness runs its course. It starts from two bedside findings, the severity of dehydration (no or minimal, mild-to-moderate, severe) and the serum sodium, both taken from the Clinical Assessment of Acute Diarrhea and Dehydration note. Once the child is out of shock, management becomes arithmetic. Serum sodium decides how fast one of the volumes may be given. Plasma sodium decides whether the deficit is replaced with sodium-poor or sodium-rich fluid, as the Pathophysiology note showed.
Why are there three separate volumes?
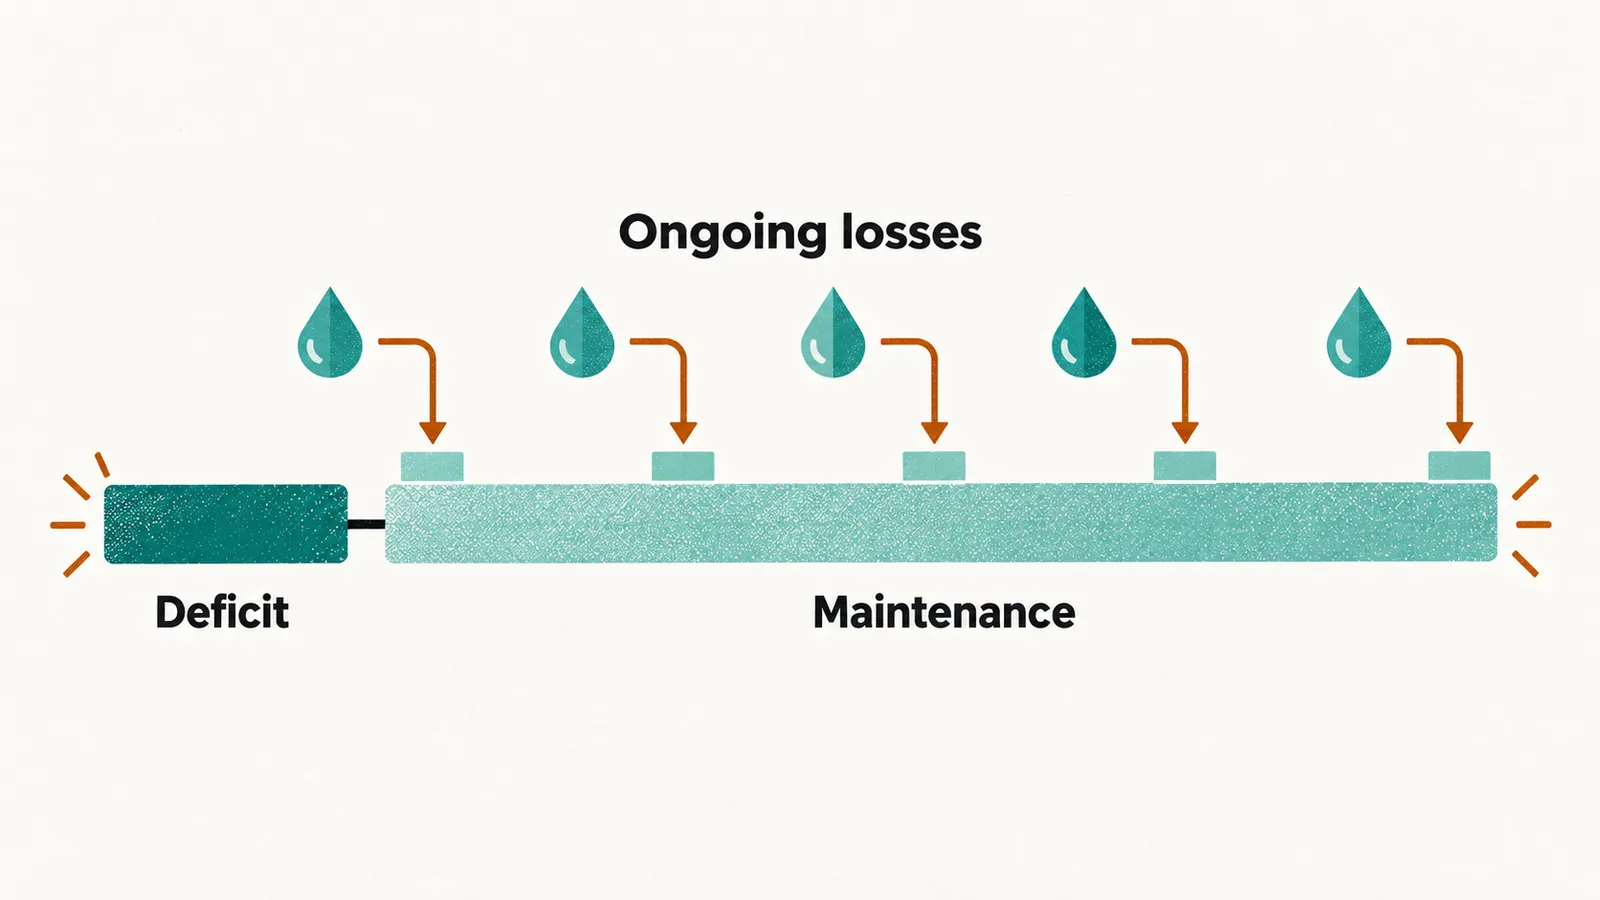
Three separate volumes are estimated, and each has its own time window. The child needs a different amount for each of three reasons, and the three answer different questions: what was lost, what is needed to keep going, and what is being lost right now.
- The deficit is what has already been lost.
- Maintenance is what the child needs each day to keep going.
- Ongoing losses are what is still leaving in stool and vomit.
The three volumes are added, not merged. Their time windows, not their sum, determine the prescription. Placed in time order, the volumes become the phases of treatment.
Where does the shock bolus fit?
Before the three amounts, a child in shock needs one step first. A child in shock gets the bolus first, as the Admission and Shock Management in Acute Diarrhea note set out. The bolus restores intravascular volume: 1-3 doses of 20 mL/kg, each given over 10-15 minutes, using 0.9% saline or lactated Ringer’s. A child who is not in shock has no bolus phase.
How much water has the child already lost?
The first amount is the water already gone, and it has to be estimated. When a recent pre-illness weight is known, it gives an estimate of the water lost, because the weight that has gone is the water that has gone. A child weighed 8 kg before the illness and 7.5 kg now has lost 500 g, so 500 mL has to be replaced.
The deficit follows a formula based on the percentage lost:
deficit in mL = percentage lost x weight in kg x 10
A 5% deficit in a 10 kg child is 500 mL. A 9% deficit in the same child is 900 mL.
The pre-illness weight is often unknown. The deficit is then estimated from the clinical severity grade instead, because the severity grade sets the size of the water gap, as the Clinical Assessment note showed.
How fast is the deficit replaced?
The deficit can be replaced rapidly, but the number is only an estimate. No formula gives the deficit exactly, so the child is reassessed during the replacement period rather than the calculated figure being followed blindly; the child’s response is the check on the number. In rapid rehydration the deficit already lost is replaced at about 20 mL/kg/h for 2-4 hours, using 0.9% saline.
How much water does the child need each day?
Separate from the deficit, the body needs water every day, whether or not the child is ill. That daily need is worked out from energy expenditure, which is why it follows a standard scheme banded by body weight:
- First 10 kg: 100 mL/kg.
- Next 10 kg: 1000 mL plus 50 mL/kg for each kg above 10.
- Each kg above 20: 1500 mL plus 20 mL/kg for each kg above 20.
An 8 kg child therefore needs 800 mL a day, a 12 kg child 1100 mL and a 25 kg child 1600 mL. Maintenance is spread over 24 hours.
Does the water still being lost change the sums?
The third amount is the water still leaving the body. Stool and vomit losses continue while the deficit is being replaced. They are replaced as they occur, not predicted. A conventional figure is an oral rehydration solution of roughly 10 mL/kg, up to 240 mL, after each diarrheal stool. Where the child can drink, this is how the ongoing losses are replaced after each episode.
What does fever change?
Fever raises insensible loss, so fluid needs rise with it. There is no single validated multiplier for the fever-related increase.
What do the three volumes add up to for an 8 kg child?
Putting the three amounts together shows what the first day looks like. Take an 8 kg child whose clinical picture is consistent with a 5% deficit.
- Deficit: 5% x 8 x 10 = 400 mL, replaced during the rapid phase.
- Maintenance: 100 x 8 = 800 mL over 24 hours, about 33 mL/h if given continuously.
- Ongoing losses: about 10 mL/kg of oral rehydration solution after each stool.
The first-day target is the deficit plus maintenance, here roughly 1200 mL. The ongoing losses are added on top of that target and replaced as they occur.
Where does the fluid go: by mouth, by tube or by vein?
The sums stay the same whatever the route, so the next question is the route. Oral rehydration is the treatment of choice and should start as soon as possible. It is superior to intravenous rehydration. When oral intake is not feasible, nasogastric rehydration comes next. Oral rehydration comes first and nasogastric before intravenous, which has more adverse effects, as the Admission and Shock note set out. Intravenous therapy is reserved for the situations listed in that note.
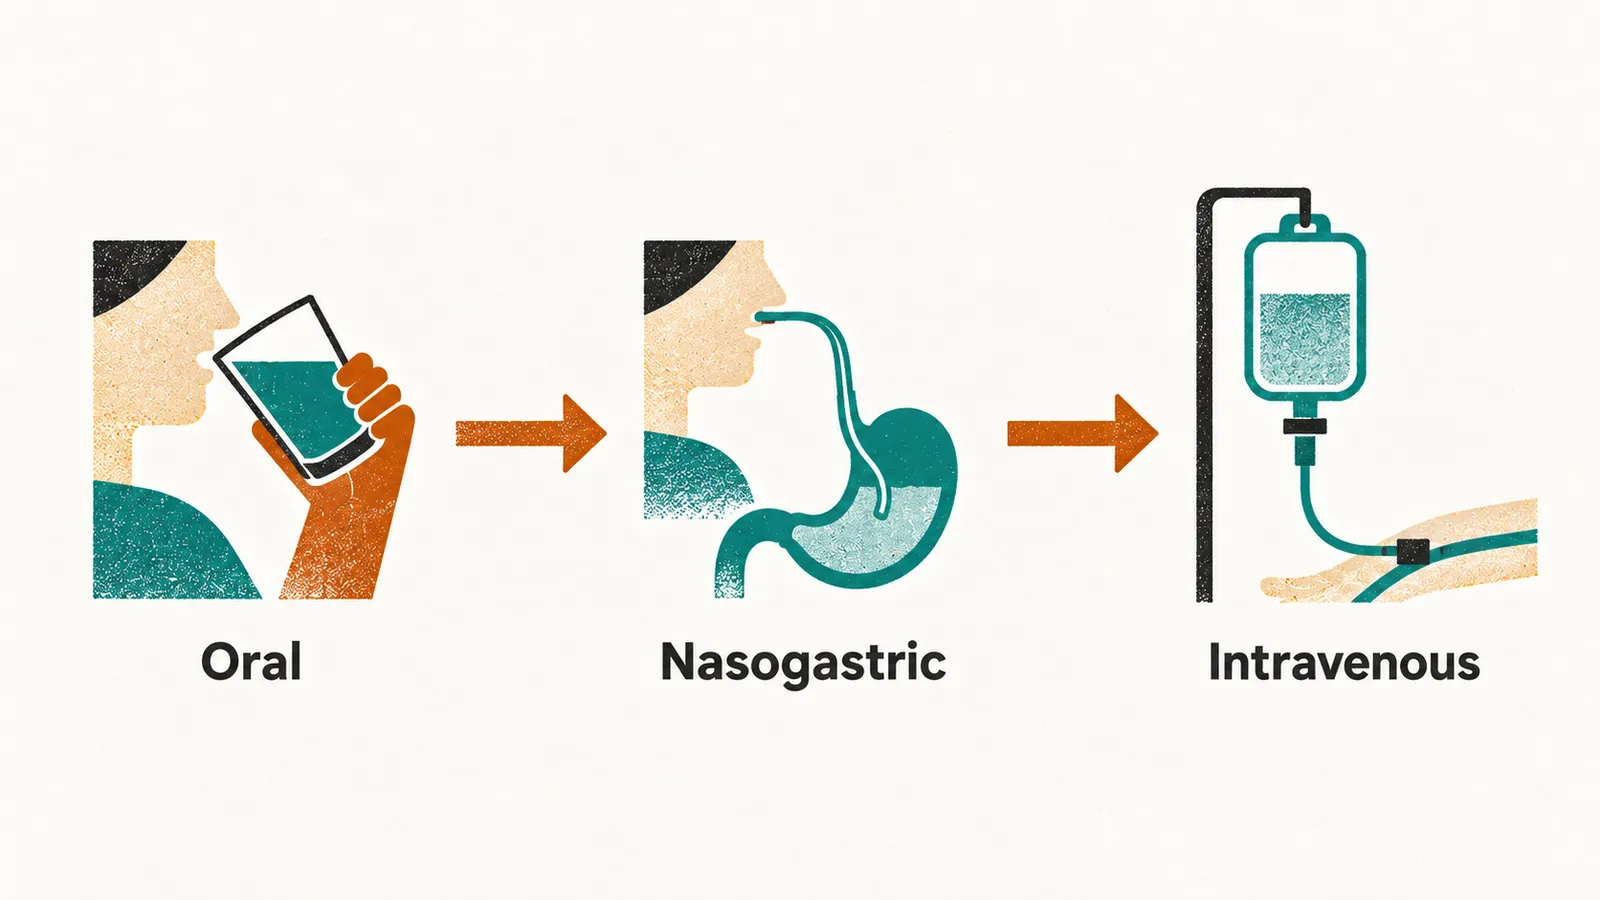
The route does not change what has to be calculated. A child managed enterally never has an intravenous phase. The same three volumes are still worked out; they are delivered by a different route. If the child can drink, the oral solution is preferred, given in divided amounts over the replacement window. If vomiting prevents oral intake, the same volumes are given intravenously, following the composition rules for intravenous solutions.
What goes into the oral solution?
When the child can drink, the drink has to be built correctly. A reduced-osmolarity oral rehydration solution, one less concentrated than the original full-strength formula, with sodium 50 to 60 mmol/L, should be first-line therapy. This is a strong recommendation on moderate-quality evidence. The reduced-osmolarity solution is more effective than the full-strength one by stool output, vomiting and need for supplemental intravenous therapy. The ESPGHAN solution may be used in children with acute gastroenteritis.
Composition matters because of the sodium-glucose cotransporter in the small intestine. It carries sodium and glucose across together, and water follows osmotically. The carrier moves them in a fixed pairing, so changing the sodium-glucose ratio makes transport lose efficiency.
Beverages with a high sugar content should not be used; this is a strong recommendation. Unabsorbed solute holds water in the bowel, as the Pathophysiology note showed, so excess sugar adds to the osmotic load rather than relieving it.
What goes into the intravenous solution?
When the drink is not enough, the intravenous fluid has its own rules. Isotonic 0.9% saline effectively reduces the risk of hyponatremia, and it is recommended for initial rehydration in most cases. A hypotonic fluid lowers plasma sodium, as the Clinical Assessment note showed, which is why isotonic fluid is the default; sodium matters in the opposite direction too, and this is one reason isotonic rather than hypotonic fluid is used to start. Lactated Ringer’s is recommended in rare but extremely severe cases of shock.
There is no standard intravenous composition for acute gastroenteritis. Most reported intravenous schemes rest on historical recommendation rather than trial evidence.
During the first 24 hours of intravenous therapy, the solution should contain not less than 0.45% saline (at least 77 mEq/L sodium) to prevent hyponatremia. A sick child may release antidiuretic hormone without the usual trigger, so the child keeps water, and a fluid with little sodium then lowers plasma sodium. If intravenous therapy is needed, an isotonic solution is used for both deficit replacement and maintenance.
When do glucose and potassium join the saline?
Once the volume is back, the fluid changes. Glucose may be added to the saline for the maintenance phase, which is a weak recommendation on low-quality evidence. The addition marks the boundary between replacing volume and sustaining metabolism. Potassium waits for urine, because most potassium leaves the body in urine. Once the child is passing urine and the electrolytes are known, 20 mEq/L potassium chloride may be added.
Why are faster schemes not used?
Schemes more rapid than the regimen described are not recommended. Rapid schemes are associated with electrolyte abnormalities and a longer time to hospital discharge. Ultrarapid schemes are not superior to standard ones and may raise readmission rates.
What changes when sodium is high?
When sodium is high, the plan changes. Hypernatremic dehydration means a serum sodium above 145 mmol/L. It is uncommon in acute gastroenteritis and is treated more cautiously than the rest. High sodium draws water out of brain cells, as the Clinical Assessment note showed, and the usual signs of volume loss can understate the deficit.
Oral or nasogastric rehydration with a hypoosmolar solution is effective and safe in hypernatremia, and it has fewer adverse effects than intravenous rehydration. The caution applies chiefly to the intravenous route.
How fast may the sodium come down?
The deficit is replaced slowly, typically over 48 hours, aiming to bring serum sodium down by less than 0.5 mmol/L per hour. That hourly ceiling corresponds to no more than 12 mmol/L over a day. Plasma sodium is monitored frequently during correction. Correcting faster risks shifting water into brain cells faster than the brain can adapt.
Sodium is measured in every child on intravenous therapy, because a high or low value changes the rate at which fluid is given, as the Investigations note set out.
When does the child go back to food and drink?
Enteral and oral routes are resumed as soon as the indications for parenteral therapy are gone. Ongoing losses are then replaced orally, and the child is fed again. When should feeding start, what should the child eat, and does any drug add to rehydration? Refeeding and Drug Therapy in Acute Diarrhea sets this out.