
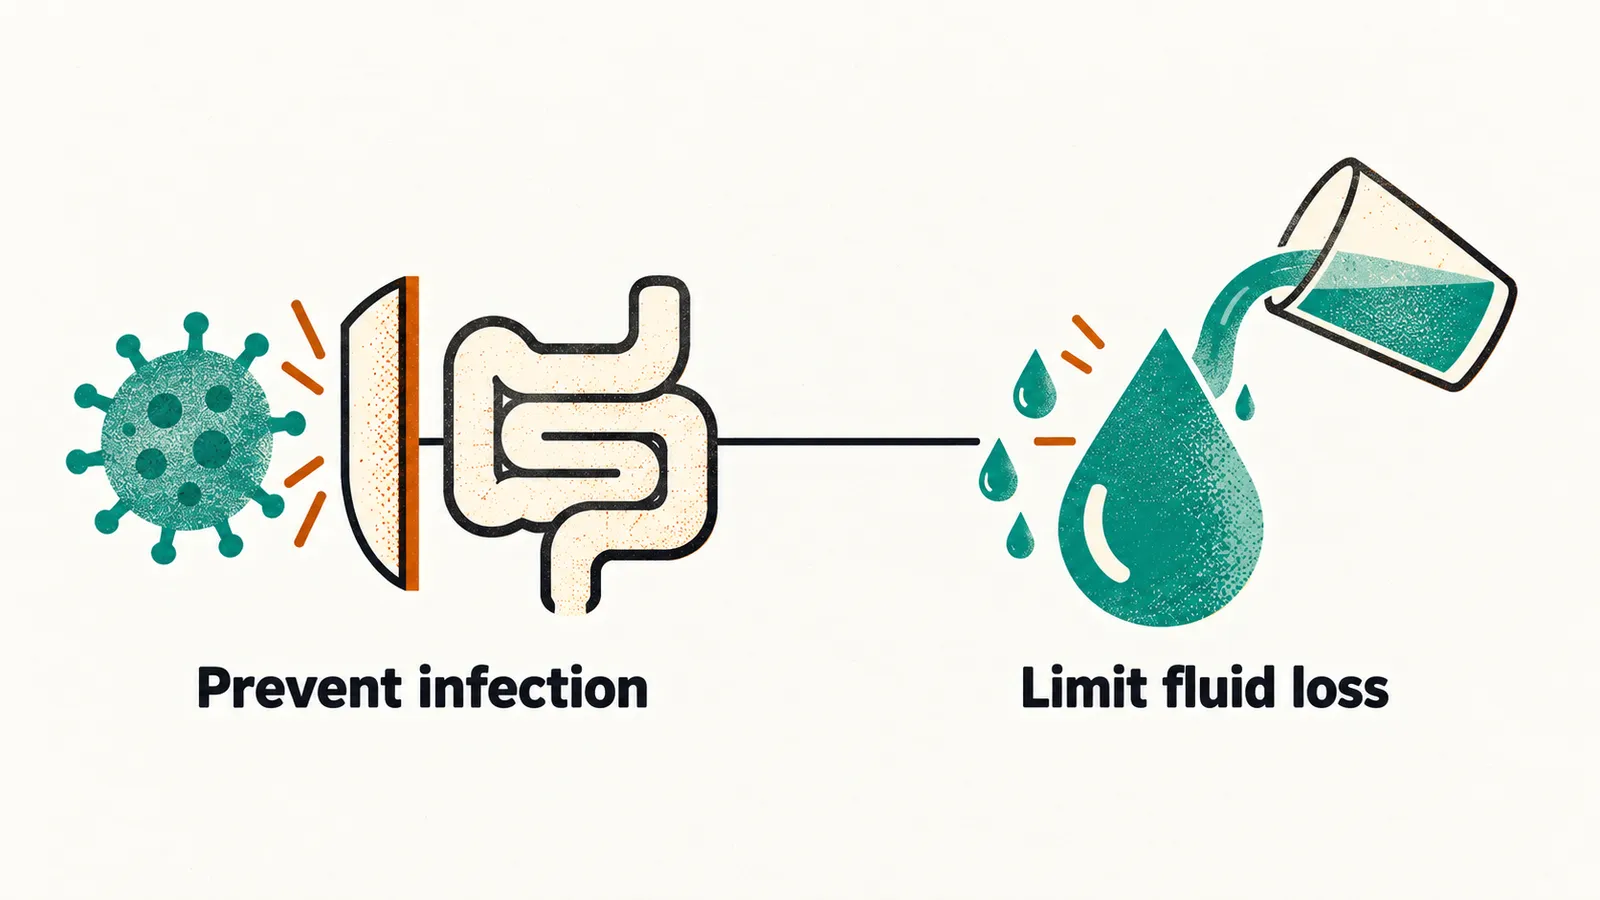
Diarrhea is common in early childhood, so prevention cannot mean eliminating it. In Europe the incidence is estimated at 0.5 to 2 episodes per child per year in children under 3 years, and gastroenteritis is a major reason for hospital admission at that age. Prevention therefore has two targets, and they need different measures.
Why are there two targets?
The first target is the infection itself: how often children are infected and how severe the infection is. The second target is the fluid loss that follows infection, because that loss turns an ordinary illness into a dangerous one. Fluid loss also lowers the plasma volume, as the Pathophysiology note showed. So a measure that keeps a mild episode mild matters as much as a measure that prevents infection.
How does rotavirus vaccination work?
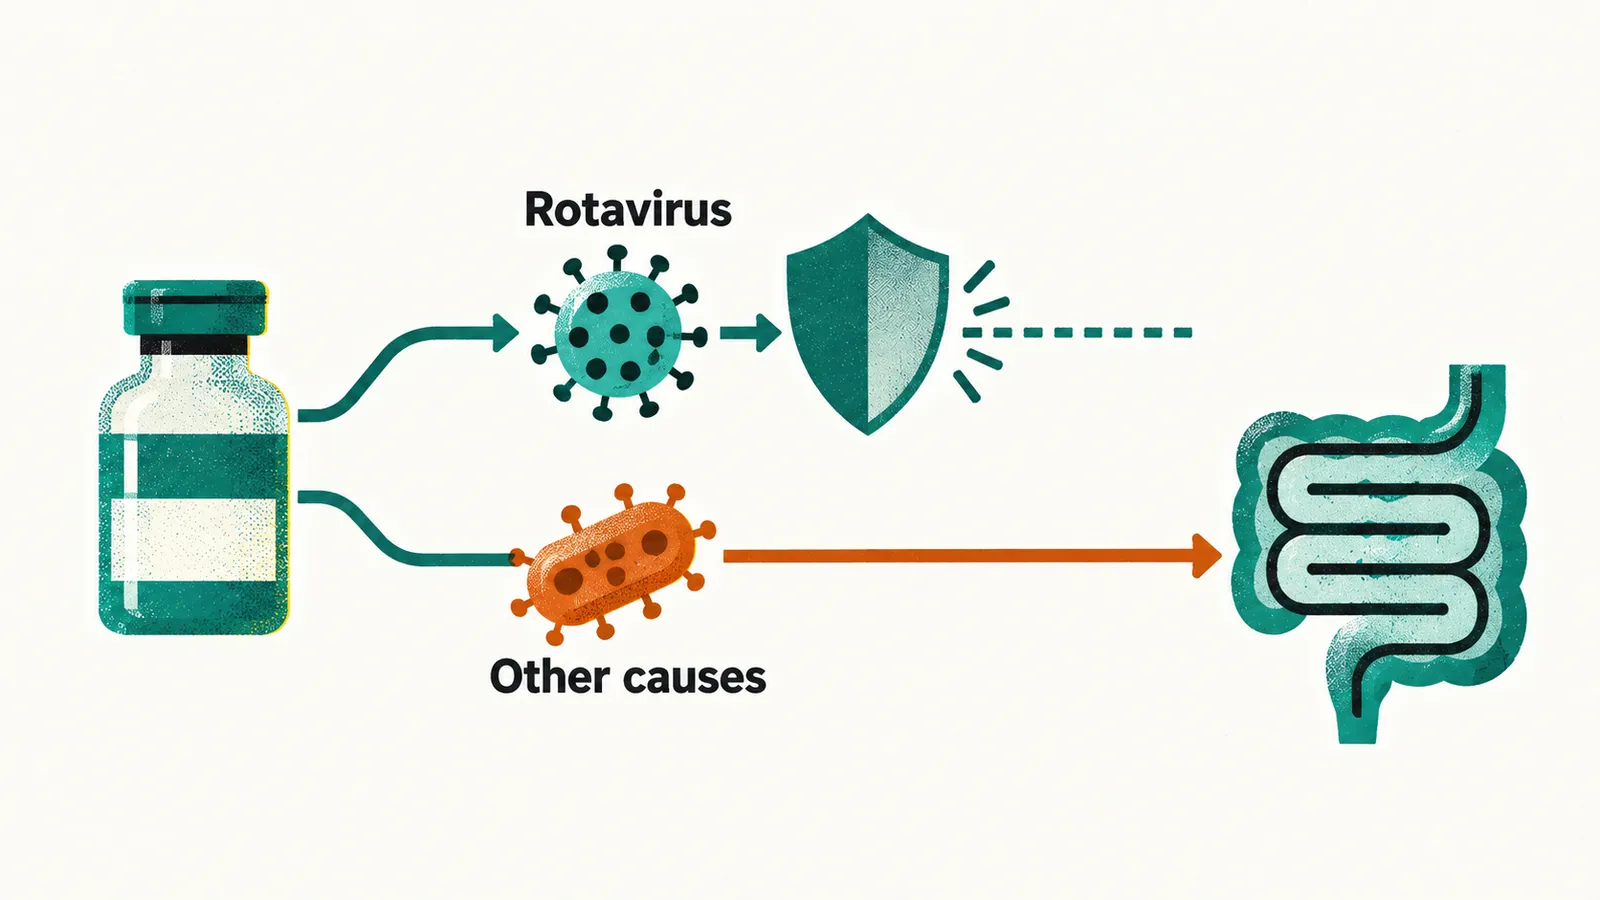
Rotavirus vaccination is the one measure that targets a named cause. Rotavirus is one cause of gastroenteritis, and the vaccine is aimed at that virus. Where routine programs exist, admissions for rotavirus gastroenteritis have fallen. A Belgian hospital-based case-control study found that two doses prevented about 90% of admissions for laboratory-confirmed rotavirus gastroenteritis (95% CI 81 to 95).
The vaccine is not recommended for infants with severe immunodeficiency.
Who is vaccinated, and when?
Once the vaccine is chosen, the schedule and eligibility are what a clinician needs. The evidence-based recommendations of ESPID and ESPGHAN state that rotavirus vaccination should be offered to all healthy infants. The first dose is given between 6 and 12 weeks of age, and the schedule is completed by 6 months. It is either 2 doses of monovalent vaccine or 3 doses of pentavalent vaccine.
The vaccine may be considered in preterm infants and in those with HIV infection, at the physician’s discretion.
WHO recommends that rotavirus vaccine be included in all national immunization programs. It advises the first dose as soon as possible after 6 weeks of age, and no vaccination after 24 months.
Why does vaccination not end the problem?
Rotavirus is not the only cause of gastroenteritis. Wherever vaccine coverage is high, it is not even the leading cause of medically attended gastroenteritis, and norovirus has taken its place as the leading cause. Large amounts of rotavirus are present in the stool of infected persons, and it is easily spread on contaminated hands and objects. Rotavirus and norovirus spread the same way, so hygiene keeps its importance alongside vaccination.
How does hand hygiene stop spread?
Hygiene is the measure that covers the other causes, because hands carry the organisms. Hand hygiene is therefore the measure that covers the rest. Hospital-acquired gastroenteritis can be prevented by adherence to hand-hygiene measures, since hospital spread follows the same hand route.
In day care, diaper changes and shared equipment move the organism to food and to other children. Stringent hygiene reduces transmission: diaper changes, hand washing, alcohol-based hand rub and clean food-preparation equipment.
Hand washing is thought to be effective for preventing transmission of diarrhea pathogens, and soap and running water help remove the organism from the hands. So the advice is to wash hands with soap and dry them carefully, especially after diaper changes or toilet use and before preparing or eating food.
A towel is a shared object, and it can carry the organism too. So a towel used by an infected child should not be shared.
How much does hand washing reduce illness?
The evidence for hand washing is the next question. A Cochrane review of hand-washing promotion programs found around 30% fewer diarrheal episodes in children at day-care centers and schools in high-income countries. The rate ratio was 0.70 (95% CI 0.58 to 0.85), and the evidence was of high certainty. The effect was larger where soap was supplied.
How is spread limited outside the home?
The child is kept out of the settings where the organism spreads. A child should stay away from school or childcare while there is diarrhea or vomiting, and until at least 48 hours after the last episode. The child should also stay out of swimming pools for 2 weeks after the last episode of diarrhea.
Which measures matter most in Europe?
In Europe, person-to-person spread, day care and hospital exposure account for more of the burden. Because that spread moves by hands, vaccination and hygiene are the measures a clinician is most likely to use.
Breastfeeding is a measure as well. Predominant breastfeeding for the first 4 to 6 months reduces the risk of gastroenteritis in European infants. Breast milk carries factors associated with protection against infection, as the Etiology note set out. The recommendation for predominant breastfeeding is strong, on moderate-quality evidence.
Where do water and sanitation come in?
Outside Europe, the water route is the one that cannot be assumed away. Exclusive breastfeeding for 6 months is one of WHO’s core prevention measures, together with safe drinking water, sanitation and food hygiene. Microbial contamination of drinking-water by faeces poses the greatest risk to drinking-water safety, so where water cannot be assumed safe, that is the route these measures block. That is why safe drinking water, sanitation and food hygiene carry most of the weight where water and sanitation cannot be assumed.
Why is early fluid part of prevention?
Fluid replacement starts before the child looks unwell. Once illness has started, prevention means replacing fluid earlier than the child’s appearance seems to demand. Compensation holds the blood pressure up, so a child can look well while the fluid deficit grows, as the Admission and Shock note set out.
Caregivers should therefore have oral rehydration solution at home and start giving it as soon as symptoms begin. Oral rehydration works because sodium and glucose are absorbed together across the gut lining, as the Admission and Shock note set out. Early oral rehydration reduces complications and the need for a medical visit, because a smaller deficit leaves less for the body to make up. It is also the reason a telephone assessment can often manage an uncomplicated case.
What does a child keep taking in?
Fluids and feeds continue. Breastfeeding and usual milk feeds continue during the illness. The lining is kept working by the food that passes over it, as the Refeeding and Drug Therapy note set out, so food is not withheld: feeding resumes during or shortly after rehydration, not after the diarrhea stops.
A child who is not dehydrated should be encouraged to drink. The water the bowel does not take back is the water that is lost, as the Pathophysiology note showed, so drinking replaces it.
Fruit juices and carbonated drinks are the exception. Unabsorbed solute holds water in the bowel, as the Pathophysiology note showed, so their sugar adds to the osmotic load rather than relieving it.
Interrupting breastfeeding is itself a risk factor for severe dehydration, not a treatment for it. It removes the fluid and food, and the protective factors, that a child needs while losing water, as the Refeeding and Drug Therapy note set out.
When should a family seek review?
Continued feeding at home needs a clear point at which the family asks for help. Review is sought early. The point at which home management stops being appropriate is defined by age, the number of stools and vomits, and the family’s report of dehydration.
Does zinc change the course?
Zinc is a further measure aimed at the duration of the episode. Zinc has a role in immune function and in regulating the gut lining, as the Refeeding and Drug Therapy note set out. It shortens the episode in children over 6 months in populations where zinc deficiency is common, and for that benefit it is part of the World Health Organization’s treatment package. In regions where zinc deficiency is rare, no benefit of zinc is expected. Zinc is not a European recommendation.
Why do children still reach a doctor?
Even with vaccination and hygiene, gastroenteritis remains one of the most common reasons a young child is brought to a doctor. A caregiver who starts oral rehydration solution on the first day, continues feeding, and seeks review when the child stops improving does most of the work before a clinician is involved, because early replacement and feeding keep the deficit small.
What happens when home fluid cannot keep up?
A small number of children still arrive with a deficit that replacement cannot keep up with, so what does the clinician do for the child whose fluid loss has already outrun the fluid given?