How does the virus move through the body?
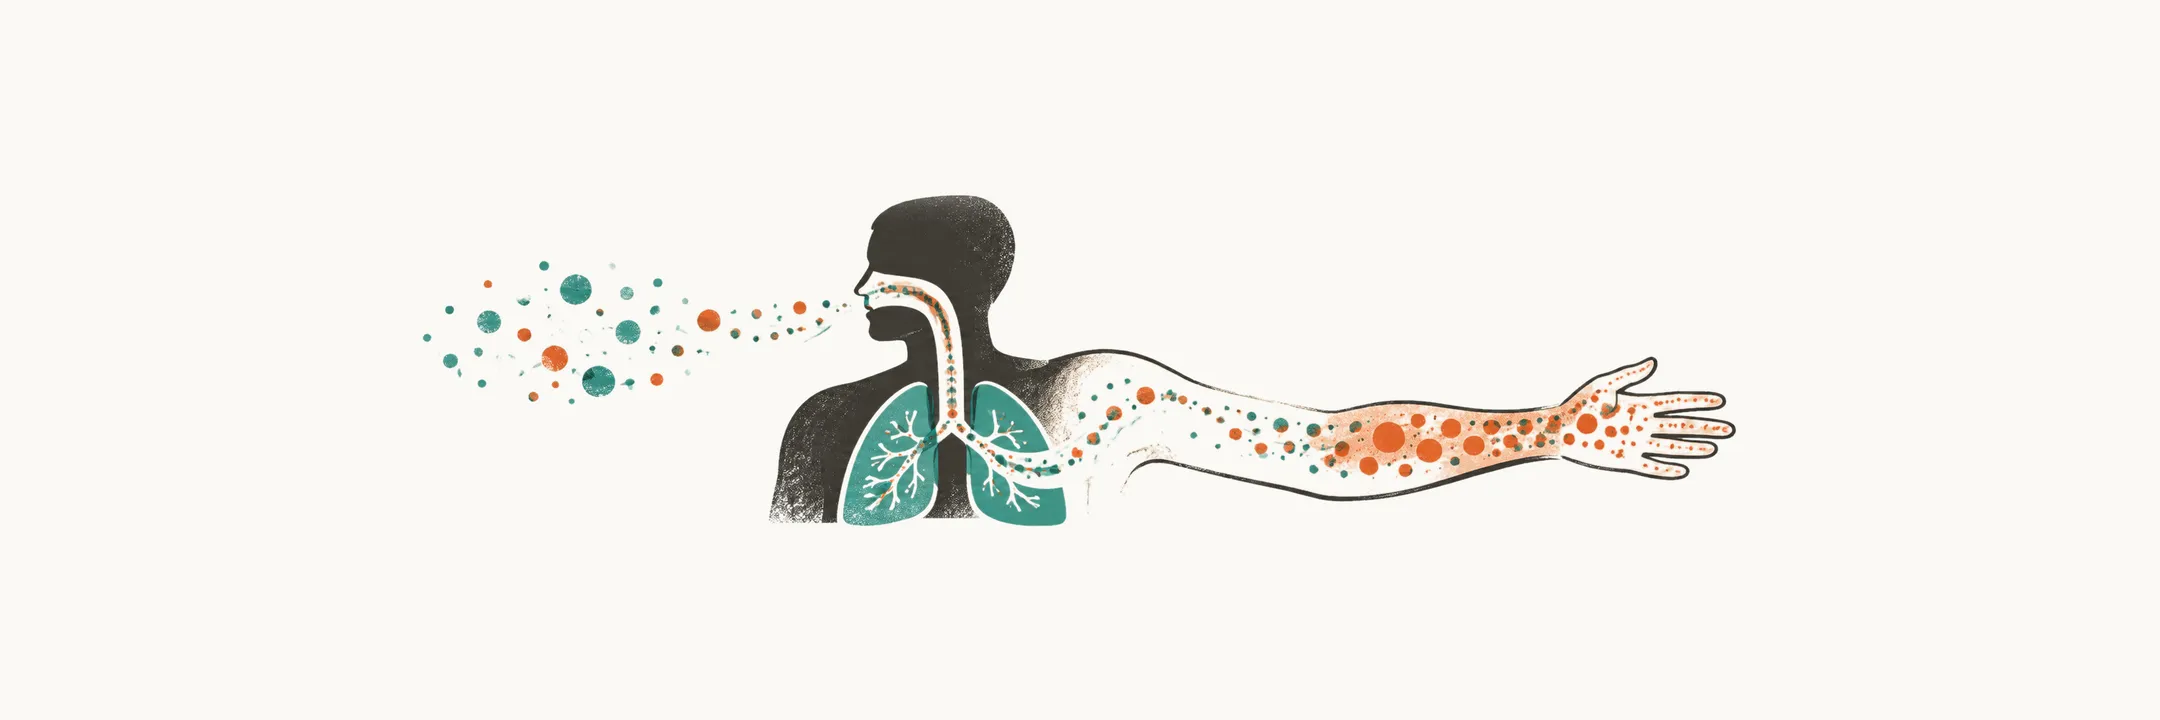
Measles is a single-stranded RNA virus of the Paramyxoviridae family, and humans are its only reservoir: there is no animal reservoir. It does not simply infect the skin. It is carried by immune cells, and that one idea explains much of the illness.
The virus enters through the respiratory tract and replicates first in the nasopharyngeal mucosa and the regional lymph nodes. Current work suggests that the first cells infected are immune cells in the airway lining, such as macrophages and dendritic cells, which carry the virus to the lymph nodes.
From there infected immune cells enter the blood in two successive rounds of viraemia (virus circulating in blood). The first round seeds organs rich in lymphoid tissue. The second spreads the virus to the epithelial surfaces, so it delivers virus to skin, conjunctiva and respiratory epithelium. This is why measles is a systemic illness, and why its first symptoms appear in the eyes and the airway.
Two features of the second round matter later. Conjunctivitis is part of the prodrome (the symptomatic phase before the rash) because the virus reaches the conjunctiva; local infection and the immune response to it are the likely mechanism. And cough outlasts the rash by days or weeks because the virus infects the lining of the bronchi and bronchioles, and that epithelial damage induces cough.
The airway is also the exit. Infected airway cells release virus back into the airway, and the child coughs it into the air. So the cough that makes the child ill also makes the child contagious. Why does that make measles so much more transmissible than the other classic exanthems?
Why is measles so contagious?
Measles is the most transmissible of the six classic exanthems. Its basic reproduction number (R0), the average number of people infected by one case when everyone around is susceptible, is generally estimated at 12-18 in fully susceptible populations. That is among the highest of any directly transmitted infection.
Three properties together account for this: heavy shedding of virus by coughing, a small dose of virus being enough to infect, and virus that stays infectious in the air. A closed space can keep the virus infectious for up to 2 hours, so the virus remains suspended in the air of a room up to 2 hours after the child has left. Transmission therefore does not require face-to-face contact with the infectious child.
The timing adds to this. A child with measles is contagious for days before the rash appears; contagiousness begins about 4 days before the rash. Virus is already replicating and being shed from the airway during the prodrome, so the child is transmitting while the illness looks like any other febrile upper respiratory infection. That is why the diagnosis has to be considered early. Measles is also the classic exanthem that most often becomes a serious illness rather than a self-limited one.
High R0 and survival in the air together set an unusually high bar for population protection. The more infectious a virus, the larger the share of the population that must be immune to break the chains of spread, and measles elimination requires vaccination coverage in the range 93-95% with two doses.
The 4 days of silent shedding lead straight into the course of the illness itself.
What are the three phases of the illness?
The illness runs through three clinical phases: incubation, prodrome and the exanthematous phase. They follow the biology of the two rounds of viraemia.
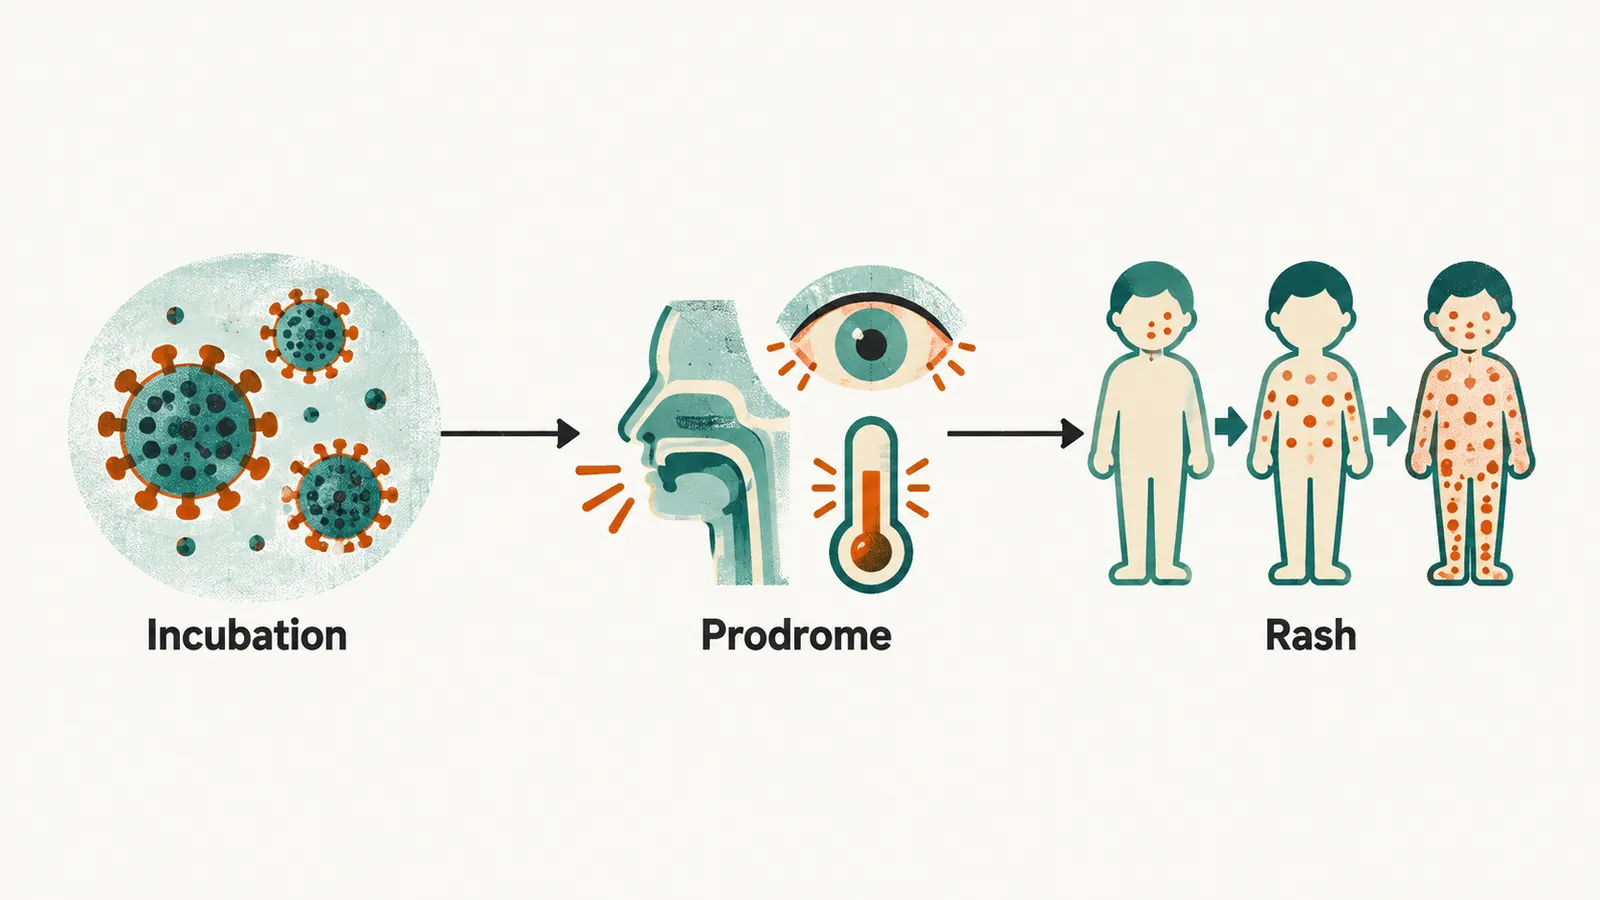
Incubation. Symptoms appear 7-14 days after exposure. The incubation is asymptomatic: the virus is spreading through the body before any symptom, and contagiousness begins about 4 days before the rash appears.
Prodrome. The prodrome lasts 3-5 days and is built around three C’s: cough, coryza (runny nose) and conjunctivitis. These are all surfaces reached by the second round of viraemia. The fever climbs and may exceed 40 °C. Vomiting, diarrhoea and lymphadenopathy also occur in the prodrome, which fits the spread to lymph nodes and the gut.
Koplik spots appear 2-3 days after the first symptoms. They are small white lesions on the buccal mucosa (the inside of the cheeks), and sometimes also on the conjunctiva or the vaginal mucosa. They are the mucosal counterpart of the rash, appearing first on the mucosa; microscopically they resemble the skin rash and may contain syncytia. They are the most specific finding of the whole illness. They disappear as the rash appears, so they are visible only within a narrow window.
Rash. The rash appears 3-5 days after the first symptoms. It starts as flat red spots at the hairline and behind the ears, then spreads cranio-caudally (from the head downwards): face, then neck, trunk, arms, legs and feet, over about 3 days. It fades in the order in which it appeared and leaves a fine desquamation (peeling of the skin). The rash usually lasts 4-8 days, and the fever often spikes again as it appears. Cough is the longest-lasting symptom, often around 10 days.
The rash is thought to appear when measles-specific T cells reach the infected skin cells and clear them. That would explain why it comes after the prodrome, when the immune response is mounting, and why immunocompromised patients often do not develop a rash although the disease is typically severe.
With a prodrome, Koplik spots and this sequence of rash, can the diagnosis be made at the bedside?
How is measles confirmed?
Measles is diagnosed clinically in a child with the characteristic prodrome, Koplik spots and a cranio-caudal maculopapular rash. Laboratory confirmation is by measles-specific IgM in serum, the antibody class of recent infection, which appears from about 3 days after rash onset. It can also be confirmed by RT-PCR (reverse-transcription polymerase chain reaction, which detects viral RNA) on a throat or nasopharyngeal swab.
Notification is required in countries with mandatory surveillance. Laboratory confirmation should be sought for every suspected case, because the public health consequences of a false positive are considerable.
Once the diagnosis is made, what can the illness do?
What can go wrong during the illness?
Most measles complications arise during or just after the acute illness, when virus is in the airway, gut and lymphoid tissue and the immune system is suppressed. The exception is (SSPE), which appears years later.
- Otitis media: about 1 in 10 children, the commonest of the common complications. Airway-lining infection and immune suppression are thought to make secondary infection of the middle ear more likely.
- Diarrhoea: fewer than 1 in 10. The virus also infects the gastrointestinal tract, and fluid loss contributes to dehydration and, in low-resource settings, to mortality.
- Pneumonia: as many as 1 in 20 children, and the commonest cause of death from measles in young children. It may be viral, bacterial or mixed: the virus damages the airway epithelium and, by suppressing immunity in airway-associated lymphoid tissue, can let bacteria in.
- Acute encephalitis: about 1 in 1,000, and it can leave deafness or intellectual disability. One acute form is proposed to be immune-mediated, with molecular mimicry between viral proteins and myelin as one suggested mechanism, although how this is induced is poorly understood.
Death occurs in 1-3 per 1,000 reported cases, predominantly from respiratory and neurological complications.
These rates are not uniform across settings. Case fatality is much higher where malnutrition, vitamin A deficiency and limited access to care are common, and WHO attributes more than 95% of measles deaths to low-income countries with weak health infrastructure. Children under 5 years and adults over 30 are at highest risk of complications in any setting.
Some damage outlasts the acute illness. What does measles leave behind?
What does measles leave behind?
Measles depresses immunity for weeks to years afterwards, so a child is more vulnerable to other infections after recovering than before the illness. A proposed explanation is “immune amnesia”: the virus is thought to infect memory T and B lymphocytes preferentially, and the immune system then destroys them, so previously acquired immune memory is damaged. New lymphocytes expand and the blood count recovers quickly, which is a proposed explanation of why the drop in lymphocytes is brief while the suppression lasts.
The other late harm is SSPE, a progressive, fatal inflammatory disease of the central nervous system. It is caused by persistent measles virus infection long after apparent recovery; where the virus persists and how it spreads remain unknown. SSPE typically develops 7-10 years after the acute illness. It presents with behavioural change and cognitive decline, and progresses to myoclonic jerks (sudden, brief muscle twitches), ataxia, seizures and ultimately a . There is no curative treatment, and SSPE is always fatal.
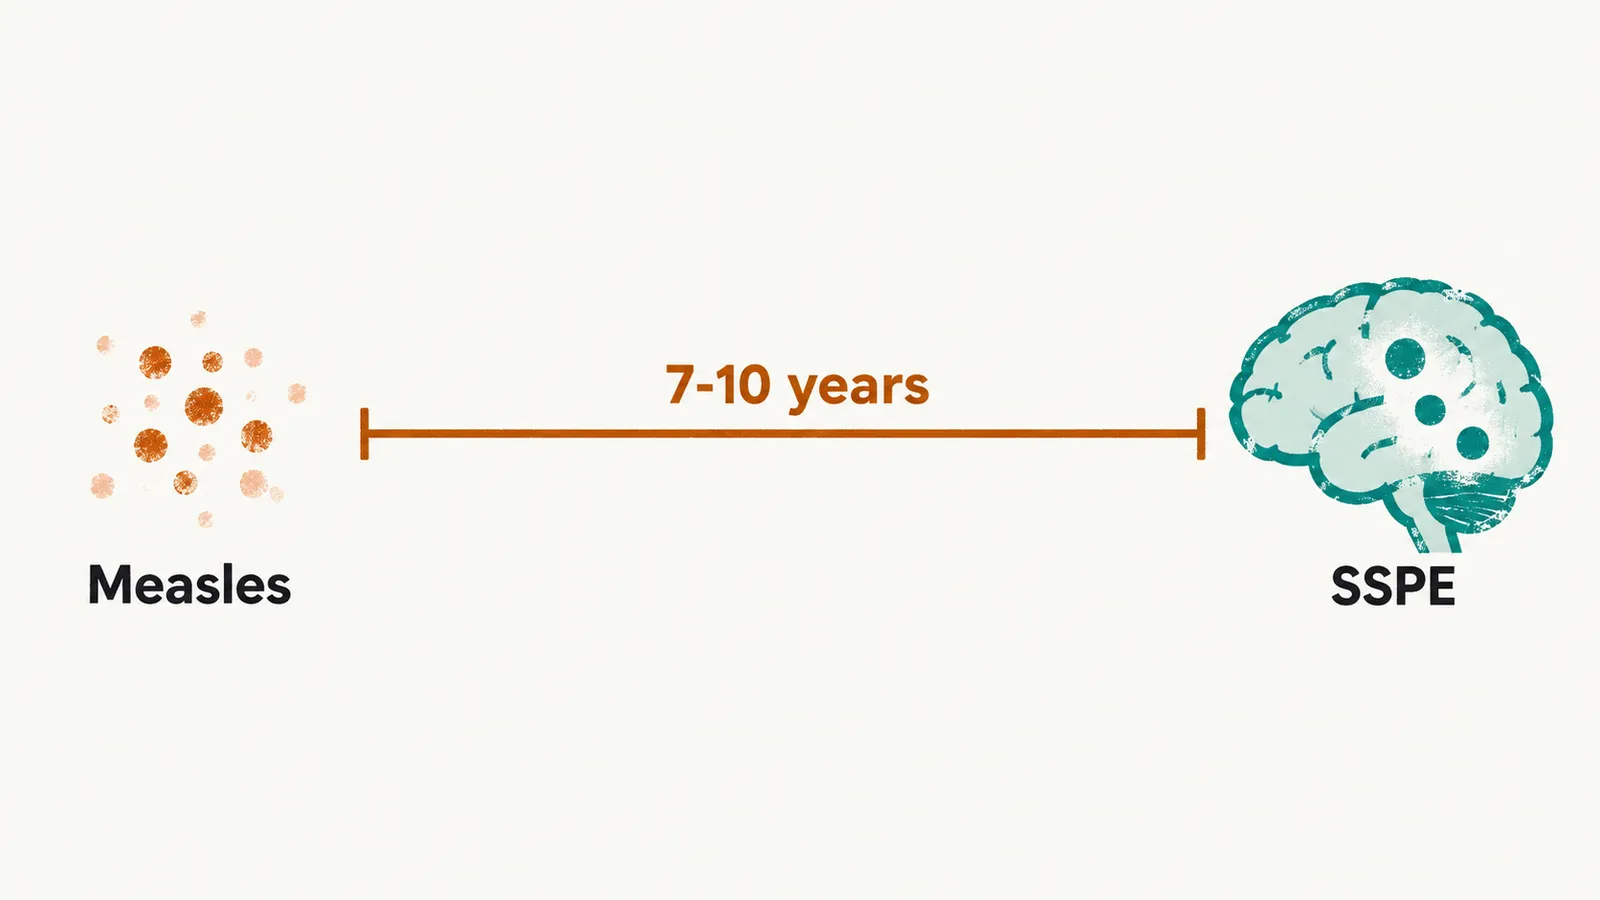
The risk is about 1 in 1,367 if measles occurred before age 5, and about 1 in 609 if it occurred before 12 months. So the risk is not evenly distributed: it is highest when the primary infection happens in infancy. Infancy is also the age group in which maternal antibody interferes with vaccination. Catching wild measles before the first birthday is therefore the worst version of the disease, not the mildest.
Since nothing removes the virus once it is established, what can be done for a child who is ill?
What can be done once a child is ill?
There is no specific antiviral for measles. Treatment is supportive: fluids, paracetamol or ibuprofen for comfort, and antibiotics only for bacterial complications. Antibiotics do not touch the virus; they are for the bacterial pneumonia or otitis that may follow.
Because the child is highly contagious, the child should be kept away from susceptible contacts, particularly infants and immunocompromised people.
WHO recommends vitamin A for all children with measles, two doses on consecutive days. The dose per day for the 2 days depends on age:
| Age | Vitamin A per day, for 2 days |
|---|---|
| Under 6 months | 50,000 IU |
| 6-11 months | 100,000 IU |
| 12 months and over | 200,000 IU |
A third dose 4-6 weeks later is recommended if there are clinical signs of vitamin A deficiency. The evidence for a mortality benefit is strongest in children under 2 years in populations where deficiency is present.
Treatment is supportive. How is measles prevented?
How is measles prevented?
Two doses of live-attenuated MMR (measles-mumps-rubella) vaccine prevent measles. A second dose exists because some children do not respond to the first. The Italian national vaccination plan (PNPV 2023-2025) gives the first dose in the second year of life and a booster at 5-6 years.
The delay beyond the first birthday is mechanistic: maternal antibody neutralises the vaccine if it is given earlier. That leaves infants exposed in the very age group where the disease is worst.
Post-exposure prophylaxis for susceptible contacts can attenuate or prevent disease. MMR works if given within 72 hours of exposure. Immunoglobulin is given within 6 days to contacts who cannot receive the vaccine: infants under 6 months, pregnant women and immunocompromised people. Immunoglobulin supplies ready-made antibody and does not depend on the person’s own immune response, and the live vaccine is not given in pregnancy or severe immune compromise.
Not every red rash with fever is a virus multiplying in the skin. What if the rash comes from a toxin released at a distant site, with no organism in the skin at all? That is the question of Scarlet Fever.